The Programmer Who Forgot to Breathe: Can Shallow Screen-Time Breathing Contribute to Rib, Mid-Back, and Low-Back Stiffness?
Abstract: Long coding sessions can change how you sit, move, and breathe. When the rib cage stays compressed and the trunk barely changes position, some people notice rib stiffness, mid-back tightness, low-back fatigue, or a deep breath that feels restricted. This article explains how the diaphragm, ribs, thoracic spine, abdominal wall, and lumbar stabilizers work together, what rehabilitation may address, and which breathing or chest symptoms need medical evaluation first.
A programmer can spend two hours solving one problem and barely notice anything below the neck. Then the task ends. The shoulders drop. The person sits back, tries to inhale deeply, and suddenly feels the ribs resist, the mid-back ache, or the low back feel tired.
That experience does not prove that “bad breathing” caused back pain. Pain is rarely that simple. However, prolonged flexed sitting, low movement variety, and shallow breathing can change how the chest wall and trunk share mechanical work. Research has linked prolonged sitting with immediate increases in low-back discomfort in some adults. A small laboratory study also found that greater posterior pelvic tilt reduced thoracic expansion and respiratory measures in healthy young men (De Carvalho et al., 2020; Aramaki et al., 2021).
The Diaphragm Is Also Part of Trunk Control
The diaphragm is the dome-shaped muscle beneath the lungs. When it contracts, it descends and helps draw air into the chest. It also works with the abdominal wall, pelvic floor, multifidus, and other trunk muscles to manage pressure and support the spine during movement.
That dual role matters at your desk. Your trunk must remain stable enough for typing, reaching, standing, and lifting while still allowing the ribs and abdomen to expand. Research on chronic low-back pain suggests that breathing and diaphragm function may interact with trunk control, but the evidence does not show that diaphragm dysfunction causes every back problem. Breathing is one variable in a much larger mechanical system (Chen et al., 2026; Li et al., 2026).
What a Long Screen Session Can Change
Picture a developer leaning toward a laptop during a difficult debugging session. The pelvis rolls backward, the low back rounds, the thoracic spine stays flexed, and the lower ribs move closer to the pelvis. That position may continue for long periods with little movement outside the hands.
Several changes can follow:
Rib movement can feel limited. A compressed trunk position may make comfortable expansion harder.
Thoracic motion narrows. The mid-back spends less time extending and rotating.
Support muscles stay active. Spinal and abdominal muscles continue to provide low-level control.
Breathing may become smaller. Some people brace the abdomen, briefly hold their breath, or breathe mainly into the upper chest when concentrating.
One position becomes the problem. There is rarely one perfect posture; low movement variety may be more important than a single snapshot of alignment.
These changes can help explain why the first deep breath after a long work block feels stiff, but they do not establish a simple cause-and-effect relationship between shallow breathing and pain.
Why Rib, Mid-Back, and Low-Back Symptoms Can Travel Together
The ribs attach to the thoracic spine, so every comfortable breath includes small movements through rib joints, chest-wall tissues, the thoracic spine, the diaphragm, and abdominal muscles. If the upper body stays flexed and still, those tissues may feel temporarily stiff.
The low back can fatigue at the same time because trunk control is shared. The diaphragm helps regulate pressure while the abdominal wall and spinal muscles manage load. That is why a useful examination should look beyond “take deeper breaths.”
A clinician may assess:
thoracic and rib mobility;
lumbar control and sitting tolerance;
hip mobility and trunk endurance;
symptom reproduction with breathing or movement;
neurological findings; and
whether breathing changes during reaching, lifting, or exercise.
The goal is to identify what is actually limiting function rather than assigning every symptom to posture.
Can Breathing Exercises Help?
Possibly, as an adjunct to rehabilitation.
A 2026 systematic review of 17 randomized trials found that breathing exercises may improve pain and function in chronic nonspecific low-back pain, but the evidence was low to very low certainty because studies varied and several had a high risk of bias (Chen et al., 2026). A separate 2026 meta-analysis found moderate-certainty evidence that diaphragmatic training may reduce pain and disability when added to care, while longer-term effects still need clarification (Li et al., 2026).
The practical message is not “breathe correctly and fix your back.” You can train breathing alongside mobility, strength, coordination, and graded activity when the examination suggests it matters.
A Five-Step Mechanical Reset
For ordinary screen-related stiffness, and only when no medical warning signs are present, a simple reset can restore movement options:
Change position. Sit taller, stand, or walk briefly, then take a deep breath.
Let the lower ribs widen. Place your hands around the lower rib cage and allow gentle expansion without straining.
Move the mid-back. Add comfortable extension, rotation, or reaching instead of repeatedly stretching only the low back.
Release unnecessary bracing. If you have been gripping your abdomen, let it soften enough for normal breathing.
Reload the trunk. Follow mobility with walking, light resistance, or prescribed stabilization exercises so the change transfers into function.
The target isn’t perfect posture. It improves variability, trunk capacity, and coordination.
When Chiropractic and Rehabilitation Fit
For mechanical rib, thoracic, or lumbar complaints, chiropractic and rehabilitation may be appropriate after excluding dangerous or non-musculoskeletal causes. Care may combine spinal or rib-joint assessment, manual treatment when indicated, mobility work, progressive trunk training, ergonomic changes, and exercise.
A 2026 review found that thoracic manual techniques and breathing exercises may improve pain or disability in some low-back-pain populations, but the certainty was low and treatment effects varied (Seyedhoseinpoor et al., 2026). That supports personalized care, not a one-size-fits-all breathing plan.
At El Paso Back Clinic, the useful outcome is physical function: sitting with less fatigue, moving more comfortably, tolerating work demands, and building capacity without rushing toward invasive treatment.
Red Flags: When Breathing Is Not a Posture Problem
Difficulty taking a satisfying deep breath can be musculoskeletal, but unexplained shortness of breath can also reflect heart, lung, vascular, infectious, or other medical conditions.
Seek emergency care for sudden severe shortness of breath, unexplained chest pain or pressure, fainting, blue lips or nails, confusion, or major breathing difficulty. New breathlessness after prolonged immobility, surgery, illness, or a long trip also deserves prompt medical attention because a blood clot is one possible cause (Mayo Clinic, 2025).
A persistent cough, fever, wheezing, worsening exercise tolerance, or breathlessness that doesn’t match your activity level deserves medical evaluation. Chiropractic treatment should not delay that workup.
Integrated Care, Informed Choices
When symptoms appear mechanical, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, can connect chiropractic assessment, rehabilitation, and medical evaluation within one coordinated plan. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with over 40 years of experience, provides medical direction when cardiopulmonary, metabolic, medication-related, or other non-musculoskeletal factors need consideration.
This approach supports beneficence, non-maleficence, and autonomy: use care that is likely to help, avoid unnecessary risk, and give patients enough information to choose among reasonable options. Prioritize non-invasive treatment when appropriate, and add imaging, laboratory testing, referral, or medical treatment when findings justify it. Care can also coordinate with the patient’s existing medical team.
The Bottom Line
Screen-time breathing is not a diagnosis. Prolonged flexion and low movement variety may reduce rib and thoracic motion and alter how the diaphragm, abdominal wall, and spinal muscles share work. For some people, that pattern can accompany rib stiffness, mid-back tightness, or low-back fatigue.
Do not obsess over every breath. Restore movement options, strengthen the trunk, vary posture, and investigate symptoms that do not behave like ordinary mechanical stiffness. If pain keeps returning or breathing feels genuinely abnormal, get evaluated before assuming the screen is the only factor.
A practical starting point is simple: notice when concentration makes your body rigid, then change position before discomfort becomes the only signal you hear. Small, repeated movement choices throughout the workday can support comfort without turning posture or breathing into another performance task that creates unnecessary worry during demanding coding sessions.
The Hip That Hurts After Sitting: Is Your Low-Back Problem Actually Being Driven by the Hip?
Abstract: Prolonged sitting holds the hip in flexion, reduces usable hip extension, and can force the lumbar spine to move more than it should. Programmers, engineers, data analysts, gamers, and remote workers often feel these symptoms as front-of-hip tightness, buttock discomfort, or low-back pain after a long session. This article explains those mechanics and when structural care, mobility, strengthening, or decompression belong in the plan.
The call ended an hour ago. You are still in the chair. When you stand, the front of one hip feels pinched, the buttock feels thick, and the low back won’t straighten. A few steps later, the back eases. That pattern is common in people who sit to think. It doesn’t prove that every desk worker has tight hip flexors. Sitting changes the hip, but a stretch does not automatically repair the spine.
What Sitting Does to the Hip
Sitting is a flexed-hip posture. The thigh stays bent toward the trunk, often near 90 degrees, for hours, and the tissues around the hip adapt to that demand (Chamberlain, 2021).
The hip is designed for large ranges of motion. The lumbar spine is built for a smaller, more controlled range.
In a typical sit, the pelvis tilts backward slightly and lumbar lordosis decreases. That sit-to-stand strategy is normal, not a diagnosis by itself (Devin et al., 2012).
Perching on the chair edge or gaming with a collapsed trunk keeps the hip bent while the low back flexes or twists.
Front-of-hip tissues can feel short because they have been held short, because the joint does not tolerate end-range flexion, or because a lumbar nerve refers symptoms to the groin or buttock.
The useful question is not “Are the hip flexors tight?” It is “Where is motion missing, and what is setting the limit?”
When the Hip Cannot Extend, the Low Back Often Pays
Hip extension takes the thigh behind the body. Walking needs only about 10 to 15 degrees of that motion. If the hip does not extend, the pelvis and lumbar spine often finish the job by extending or rotating more than they should (Gómez-Hoyos et al., 2020).
That is the core of hip-spine thinking. Offierski and MacNab described coexisting hip and lumbar problems that can mimic, amplify, or hide each other (Offierski & MacNab, 1983). Later reviews add a practical rule: if the hip cannot supply sagittal motion, the lumbopelvic region often will (Devin et al., 2012).
For a desk-based engineer or analyst, the day can look like hours of hip flexion, brief standing with a hip that no longer extends easily, extra lumbar motion to keep the trunk upright, and a return to the chair before the hip practices the missing motion. People with low back pain often show reduced hip range of motion and weaker hip extensors and abductors than pain-free adults (Pizol et al., 2024). That does not make the hip the villain in every case. It does show that the hip and low back share a job.
Reduced Gluteal Capacity Is a Loading Problem
The gluteal muscles extend and stabilize the hip. In sitting, they are lengthened, unloaded, and rarely asked to produce force. Capacity drops because they are undertrained for controlling the pelvis when you stand or walk. If the hip cannot create or control extension, lumbar extensors often work harder. The back starts doing a hip job. That can feel like a tight belt after a long coding block or a late gaming session.
Adding hip strengthening to a low-back plan can reduce pain and disability in nonspecific low back pain (Santamaría et al., 2023). That is not a reason to load the glutes on day one. If the hip joint is irritated, aggressive bridging can increase groin pinch instead of building capacity.
Hold four targets at once: the hip needs motion, the gluteals need force and endurance, the trunk needs to stabilize instead of steal extra motion, and the workday needs more than one posture.
Tight Muscle, Stiff Joint, or Nerve Irritation?
A stretch that feels good in the front of the hip does not identify the source.
Adaptive muscle stiffness
The front-of-hip muscles have spent the day in flexion. They may resist lengthening when you stand. Symptoms often ease after walking, without catching or a sharp groin pinch at the end of range. This is the usual tight-flexor pattern, not the only one.
Hip joint limits
Intra-articular problems such as femoroacetabular impingement, labral irritation, or early degenerative change often prefer the groin. Sitting, crossing the legs, or tying a shoe can pinch. Clicking or limited internal rotation raises concern that the joint, not just the muscle, is setting the barrier (Chamberlain, 2021; Enseki et al., 2023).
Extra-articular hip pain
Lateral hip pain with side-lying or stair climbing can point toward gluteal tendon irritation. Deep buttock pain can come from posterior hip muscles, the sacroiliac region, or referred lumbar symptoms.
Nerve-related pain
A lumbar disc or irritated nerve root can send symptoms into the buttock, thigh, or groin. Numbness, tingling, shooting pain, or true weakness are not flexor tightness. They need a spinal and neurological exam.
Seek prompt evaluation for fever, unexplained weight loss, unchanging night pain, progressive weakness, or bowel or bladder changes. Those signs are not stretch problems.
A Direct Plan That Respects Both Regions
El Paso Back Clinic treats this as a mechanical problem first. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, evaluates spinal motion, hip motion, strength, and nerve signs in the same visit. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, provides medical direction when findings suggest more than postural overload.
A useful exam compares hip and lumbar motion, sit-to-stand quality, single-leg control, and nerve tension tests. The goal is to decide whether the low back is primary, the hip is primary, or both share the load. That is beneficence: treat the driver, not only the loudest complaint.
Chiropractic structural care can improve joint mechanics in the lumbar spine, pelvis, and hips when restriction is present. The intent is to give each region its own range so one area stops compensating for the other. Gentle hip mobilization may help when the capsule, not the muscle, is the barrier. Aggressive end-range stretching is a poor first choice if groin pinching suggests impingement.
Mobility work should look like the missing task: hip extension without extra lumbar arching, rotation without twisting through the lowest lumbar joints, and sit-to-stand without a lurch. Movement variability—standing, walking, sitting, and changing sides—reduces the hours the hip spends in one angle.
Once pain allows, training should include quiet hip hinges or bridges, side-lying or standing abduction, split-stance work that asks one hip to extend, and trunk endurance that resists motion instead of creating it. A programmer who sits for ten hours does not need a max squat in week one. They need a hip that can stand and walk without handing the job to the low back.
Non-surgical spinal decompression is a targeted tool for disc-related compression and selected nerve findings. It is not a default treatment for a stiff hip. If an exam and imaging support a disc or stenosis driver, decompression may reduce neural irritation while rebuilding capacity. If the spine is quiet and the hip is the limiting factor, the plan should focus on the hip. Choosing a non-invasive path first can reduce the rush toward long-term medication or surgery when those steps are not required. That is how the plan avoids adding risk the patient does not need.
What You Gain When Both Regions Share the Work
The outcomes patients want are practical: stand after a long review without grabbing the chair, walk without a chopped stride, and sit through focused work without a pinched groin or a locked low back. The hip should supply motion and force. The low back should supply controlled motion and stability.
Autonomy means you leave with a map: which symptoms are reasonable to train through, which signs should stop a stretch, and how this plan can sit alongside the care you already receive from your medical team.
Next Step With the El Paso Back Clinic Team
If sitting leaves a mark on the hip or low back, a focused exam can separate a short, adapted muscle from a joint or nerve problem. That is the difference between stretching what is loud and treating what is driving the load. Schedule an evaluation with Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, and the collaborative medical team directed by Dr. Maria Guadalupe Cardenas, MD, so structural care, hip mobility, progressive strengthening, and—only when spinal findings justify it—decompression can be matched to your exam, not to a generic desk-stretch list.
Devin, C. J., McCullough, K. A., Morris, B. J., Yates, A. J., & Kang, J. D. (2012). Hip-spine syndrome. Journal of the American Academy of Orthopaedic Surgeons, 20(7), 434–442.
When the Standing Desk Starts Hurting: Why Standing All Day Is Not the Opposite of Sitting All Day
Abstract
Buying a standing desk feels like a solution. For many programmers, engineers, remote workers, and analysts, it is not. This article explains why standing all day is not the opposite of sitting all day. It covers static loading, lumbar compression, hip position, foot fatigue, and movement variability, then shows how a structural exam, chiropractic care, decompression when indicated, and trunk-hip conditioning shift the load away from the furniture.
You did the responsible thing. After months of low-back tightness at the keyboard, you raised the desk and promised to stand through stand-ups and tickets. For two weeks it felt like progress. Then the low back felt heavy by afternoon, one hip locked, and the feet ached. By dinner, standing no longer felt like relief.
That pattern is common among programmers, engineers, remote workers, and analysts who treat furniture as the solution. A standing desk can be useful. It is not a cure. The spine needs a changing load, not one perfect posture.
The Myth of the Perfect Desk Posture
The sales pitch is simple: sitting compresses the discs, and standing unloads them, so more standing should mean less pain. The body does not work that way.
Sitting and standing are both static postures. In both, the pelvis, lumbar segments, and hips hold a relatively fixed shape while the eyes stay on a screen. The muscles that keep you upright do not rest. They hold. After enough minutes, they fatigue, the pelvis drifts, and the lumbar curve collapses or over-arches. Pain follows the drift, not the desk brand.
Research on sit-stand workstations is mixed. Some reviews show a modest drop in low-back discomfort when people alternate positions (Agarwal et al., 2018). A Cochrane review of workplace standing and walking interventions found no clear reduction in musculoskeletal symptoms (Parry et al., 2019). Changing position tends to matter more than choosing one “better” position and staying there.
What Static Loading Actually Does
Static loading means a tissue is compressed, stretched, or contracted without enough change in length or force. Holding a grocery bag with a straight arm is the same idea. The bag is not heavy. The hold is.
In a standing workday, that holds stacks up:
The lumbar discs and facet joints accept a steady compressive force.
Hip and gluteal muscles co-contract to keep the pelvis from tipping.
Calves and foot muscles lock to keep you from swaying.
Blood return from the lower legs slows because the muscle pump is not cycling during walking.
Prolonged constrained standing has been linked to low-back discomfort, leg fatigue, foot pain, and venous pooling (Waters & Dick, 2015; EU-OSHA, 2021). Standing more than about four hours a day, especially without walking breaks, is also associated with a higher risk of chronic venous problems (Hirsch et al., 2024). The standing desk concentrated these loads into eight hours of “optimal posture.”
Lumbar Compression: Sitting Is Not Always Worse
Classic studies suggested sitting raised disc pressure compared with standing. A 2022 systematic review found that sitting often produces higher pressure in healthy discs, but later studies and studies of degenerated discs often show little difference between the two postures (Li et al., 2022).
That matters if you already have disc irritation or chronic lumbago. Switching desks may not unload the segment that hurts. Locked knees, a forward head, and a distant mouse can raise lumbar shear even as you feel “more active.” Laboratory work found standing produced the most fidgeting and the highest front-to-back shear, while both prolonged sitting and prolonged standing increased low-back discomfort (Le & Marras, 2016; Park & Srinivasan, 2021). Alternating sit-stand blocks changed trunk stiffness and muscle activity more favorably than either posture alone.
If your low back hurts after two hours of sitting, two hours of standing is not automatically medicine. It is a different static load.
Hips, Feet, and the Standing Fatigue Pattern
Desk workers who stand for long blocks often describe a cluster:
A dull lumbar ache below the belt line
One hip that feels pinched or stuck
Tightness across the front of the thighs
Heaviness in the calves
Tired, hot feet by mid-afternoon
Standing with the pelvis tucked under flattens the lumbar curve and keeps the hip flexors short. Standing with an exaggerated arch jams the lumbar facets. Neither version includes the motion those joints were built for: flexion, extension, rotation, and weight shift. Without walking, the calf pump is quiet, fluid pools, and the plantar fascia takes a continuous load. A thick mat can delay the complaint. It does not remove the need to move.
Movement Variability Beats Longer Standing
Tissues tolerate changing forces better than identical forces. Discs like cycles of load and unload. Hips like a changing angle. Feet like a push-off.
A useful work block is not “stand until it hurts, then sit until it hurts.”
Sit for focused typing with the lumbar curve supported.
Stand for shorter review or call blocks with soft knees and weight shifting.
Walk two to five minutes between tickets or meetings.
Change the mouse side or foot position before symptoms peak.
The goal is not to collect standing minutes. The goal is to interrupt the hold.
Change the Load, Don’t Just Change the Furniture
A standing desk is a tool. So is a chair. Neither one evaluates a stiff thoracic spine, a rotated pelvis, a weak hip abductor, or a disc that does not tolerate axial load.
El Paso Back Clinic starts with the structure, not the catalog. A focused exam looks at lumbar motion, hip extension and rotation, trunk endurance, foot and ankle stiffness, and nerve tension if pain travels into the leg. Imaging and medical screening are added when red flags appear.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, evaluates both the mechanical pattern and the medical context. His dual licensure as a Doctor of Chiropractic and a board-certified Family Practice Nurse Practitioner allows structural care to work alongside appropriate diagnostics. Dr. Maria Guadalupe Cardenas, MD, Board-Certified in Internal Medicine, provides medical direction and laboratory oversight when metabolic or vascular issues could be amplifying fatigue or delaying recovery.
That collaboration is the ethical core of the visit. Beneficence means the plan exists to restore function and spare a larger intervention the patient may not need. Non-maleficence means starting with non-invasive, drug-sparing options instead of unnecessary surgery or long-term medication dependence. Autonomy means the patient sees the findings and chooses the next step with their existing medical team still in the loop.
What Care Looks Like When the Desk Is Not the Diagnosis
Chiropractic structural care
Adjustments and mobilization restore motion where the lumbar spine, pelvis, and hips have locked into a standing or sitting pattern so one joint is not doing the work of three.
Non-surgical decompression when indicated
If exam and imaging point to disc-related lumbago or radicular irritation, computer-guided non-surgical spinal decompression may be appropriate. In selected patients, adding decompression to standard physical care has improved pain, motion, endurance, and function compared with physical therapy alone (Amjad et al., 2022; Schueren et al., 2025). It is a targeted option when disc load, not furniture, is the limiter.
Mobility and progressive trunk-hip conditioning
Remote workers and engineers also need hip extension they can use at a desk: split-stance hip-flexor and calf lengthening, thoracic rotation, ankle rocks, and pain-free lumbar motion. Once irritability drops, the program targets weak areas with hip abduction, anti-extension trunk work, sit-to-stand control, and short carries.
A Practical Desk Reset
You do not need a new desk to start changing the load.
Cap uninterrupted standing at 20 to 30 minutes until hips and feet tolerate more.
Cap uninterrupted sitting the same way.
Use shoes with a stable heel if you stand at home.
Raise the monitor so you don’t fold your neck.
Walk during calls that do not require a shared screen.
Stop standing the moment the low back starts to brace. Bracing is a warning, not a badge.
If pain, numbness, or leg heaviness persists after you rotate positions, bring that data to a structural exam.
The Point
Desk workers did not fail the standing desk. Sitting overloads the lumbar spine in one pattern. Standing overloads it in a different way. The solution is a spine, pelvis, and hip complex that can change shape, share load, and recover. Change the load. Do not just change the furniture.
If standing still leaves a heavy low back, a locked hip, or tired legs, schedule a structural evaluation at El Paso Back Clinic. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, and Dr. Maria Guadalupe Cardenas, MD, coordinate chiropractic alignment, decompression when indicated, mobility training, and medical oversight on one plan. Bring your desk-setup notes and leave with a load strategy for Monday.
The Server-Rack Crouch: How Mid-Back Stiffness, Hip Restriction, and Awkward Reaching Overload the Lumbar Spine
Abstract: Data center technicians and network engineers crouch behind racks, kneel on hard floors, pull cables, and lift gear in tight aisles. When the mid-back cannot rotate, and the hips cannot flex well, the lumbar spine takes on extra bend, twist, and shear. This article maps that kinetic chain, shows what a structural exam should measure, and outlines alignment, mobility work, mechanical rehab, lifting strategy, and spinal decompression to keep a mechanical problem from becoming a disc or nerve injury.
The job does not look like heavy construction. You slide a switch into a dim rack, kneel to dress fiber, and then stand when a ticket hits. By day three, the low back feels thick and unreliable. Calling that “bad posture” does not tell you what to change.
The real issue is load sharing. The lumbar spine is built to carry compression and resist excess rotation. It is not built to supply the turn your mid-back should provide, or the hip bend your hips should provide, while you also reach and lift. When those neighbors stiffen, the low back becomes the available joint—and available joints get overloaded.
The Kinetic Chain Behind the Rack
Treat the trunk as a three-part system.
The thoracic spine and rib cage should rotate and extend so the arms can reach without dragging the pelvis.
The hips should flex and extend so you can drop or rise without folding the lumbar discs to their end range.
The lumbar spine should stay relatively stable while those two regions move.
When thoracic rotation is limited, the trunk borrows from the lumbar segments. Mobilizing restricted thoracic joints increases thoracic rotation and reduces lumbar rotation during the same turn (Yasuda et al., 2023). Modeling also shows that a stiffer thoracic spine raises lumbar disc stress and L5 pars stress (Morimoto et al., 2024). That is the server-rack crouch: you rotate to see a port, the ribs do not turn, and L4–L5 or L5–S1 supplies the missing degrees.
Hip restriction writes the same story in the sagittal plane. If hip flexion is short, a squat or kneel-to-stand uses extra lumbar flexion. Available hip flexion is linked to how much the lumbar spine flexes during a squat lift (Patterson et al., 2022). People with poorer hip and lumbar mobility also place higher bending stress on the spine during everyday lifts (Dolan & Adams, 1993). On the floor, this means hinging to pick up a box rather than rounding through the belt line.
Awkward reaching multiplies both problems. A reach around a rack post is flexion plus rotation plus a long lever. Confined-space research shows spinal load stays high in restricted height, though kneeling can cut shear compared with stooping because the trunk can stay more upright (Weston et al., 2020). Behind a rack, you often experience the worst mix: a stooped torso, rotated shoulders, and a load at arm’s length, then a sudden stand.
Why This Pattern Progresses
A single shift rarely herniates a disc. The pattern does. Repeated end-range lumbar flexion and rotation under load stress the annulus, facets, and ligaments. Over months, you may notice morning stiffness, a catch when standing from a kneeling position, or buttock pain after a long pull. Those are mechanical warnings. If the segment keeps moving past its useful range while a disc is already irritated, nerve roots can become inflamed. That is a load problem, not “tight muscles.”
What a Structural Assessment Should Measure
A useful exam maps missing motion and excess motion.
Mid-back and rib cage
Seated and quadruped thoracic rotation with the pelvis held still
Thoracic extension, watching for lumbar substitution
Rib and segmental joint play through the levels used in reaching
Hips and pelvis
Hip flexion, extension, and rotation
Hip-hinge quality from standing and from a half-kneel
Pelvic control during sit-to-stand and floor-to-stand
Lumbar spine and nerves
Segmental motion and tenderness
Repeated-movement testing to see whether flexion or extension changes symptoms
Nerve tension signs if pain or tingling travels below the knee
Imaging and a neurologic exam when weakness or progressive numbness appears
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, uses that map with medical screening. Dual licensure lets structural findings sit next to a review of inflammation and medication risk. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, provides collaborative oversight so care stays coordinated with your existing medical team. That is beneficence: the plan exists to protect the disc and the person.
Alignment First: Restore the Joints That Should Move
If the mid-back is locked and the hips are stiff, adjusting only the sore lumbar joints may provide temporary relief, but the improvement often fades by the next session.
Alignment at El Paso Back Clinic restores motion where it belongs:
Thoracic and rib work to return rotation and extension to the cage
Pelvic and hip work so the femur can flex without flattening the lumbar curve
Specific lumbar adjustments after neighboring regions can share load
Patients keep autonomy here. You should know which joint is being treated, why, and how you’ll measure change at the next visit.
Non-maleficence sits in the same step. Skilled, non-invasive adjustments and graded loading can reduce the rush toward long-term medication or surgery while the problem is still mechanical. Surgery has a place for true neurologic emergencies. Most back problems become that case only after the same compensation runs for years.
Mobility Restoration You Can Own
Clinic work does not replace the shift.
Thoracic rotation in a half-kneel, ribs turning, pelvis quiet
Hip-flexor length after long kneeling, so standing does not yank the lumbar spine
Hip-hinge rehearsal so the crease is at the hips, not at the belt
Ankle motion, because a stiff ankle forces an extra lumbar fold when you drop
Short sessions beat heroic stretching after the damage is done. Two minutes before a rack walk and two minutes after is a plan most crews can keep.
Mechanical Rehabilitation and Lifting Strategy
Mobility without strength leaves a new joint unprotected.
Hip-dominant hinges and split-stance pulls so the glutes lift the torso
Anti-rotation holds so the lumbar spine can resist twist while the arms reach
Tall-kneeling and half-kneeling work that mirrors floor-to-stand cable tasks
Gradual loading of lift height and mass so the hips take the extra demand
Lifting rules:
Get the load close before it leaves the floor or the cart
Turn the feet instead of twisting the belt line
Prefer a kneel with an upright trunk over a full stoop when the aisle is low
Split the task: slide, then lift, then turn
Use a partner or lift aid for awkward chassis
Confined work will never be perfect. The goal is fewer cycles at end-range lumbar flexion and twist.
When Spinal Decompression Belongs in the Plan
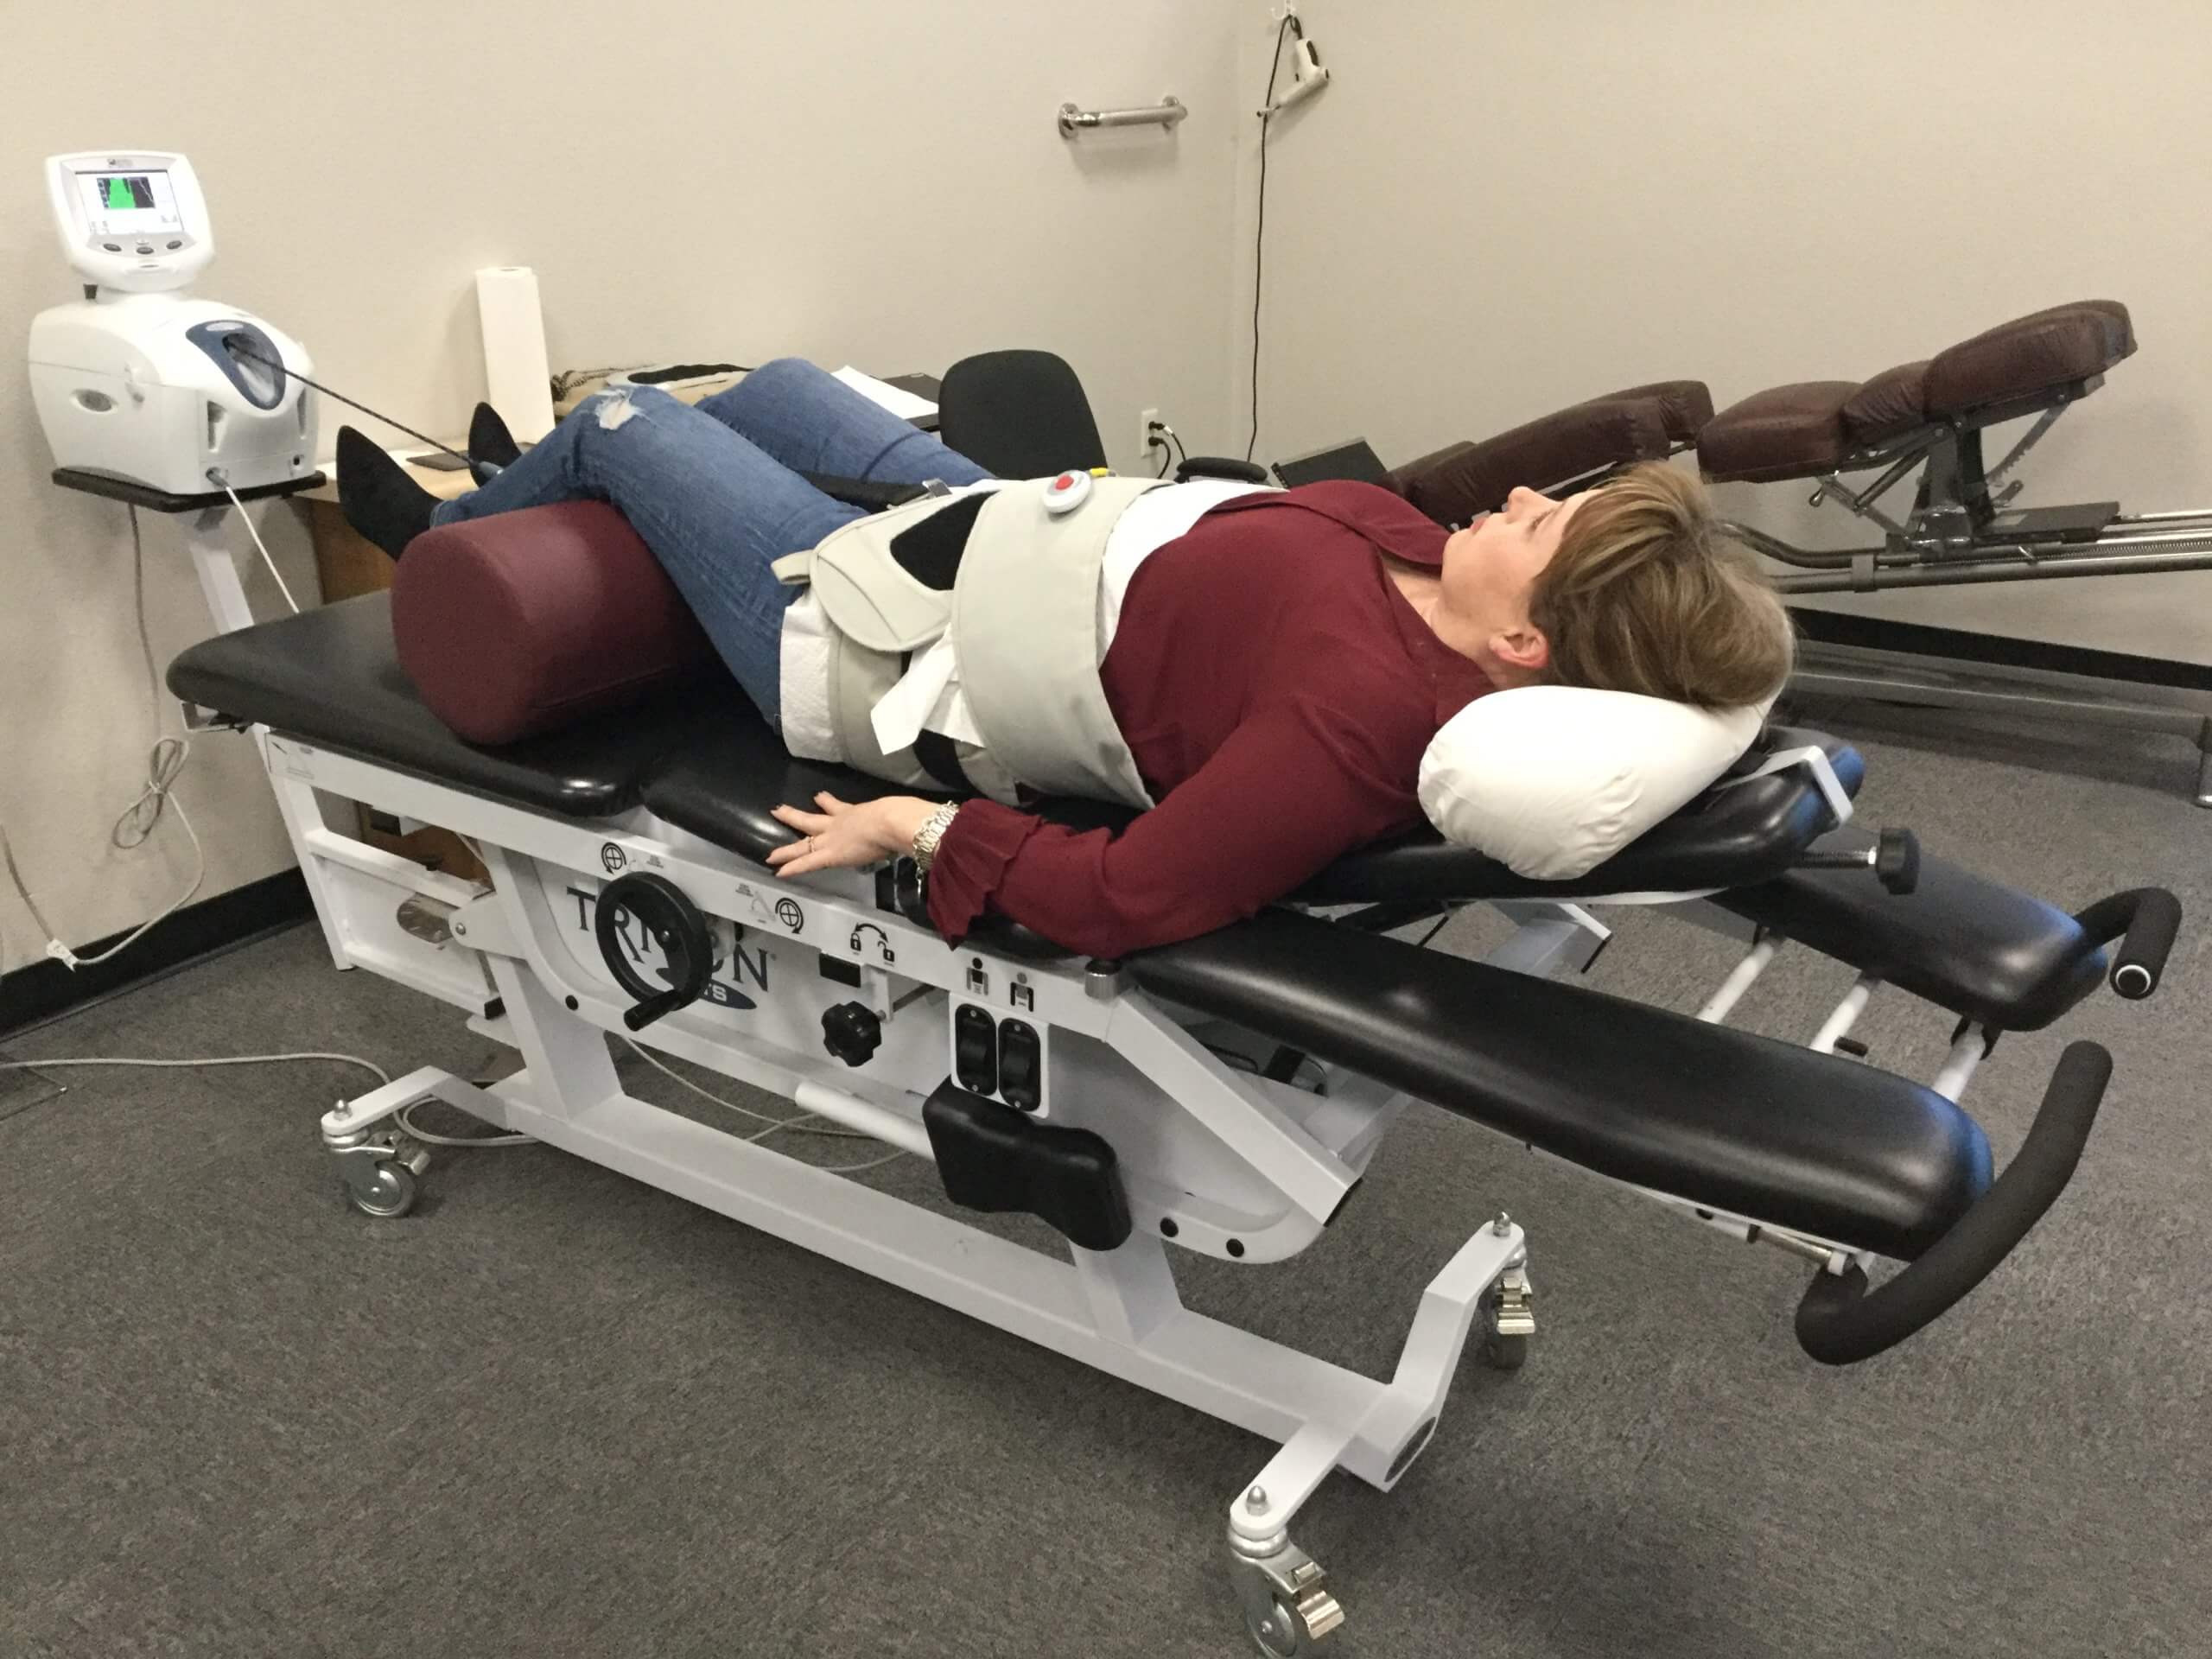
If the disc is already irritated, alignment and exercise may not be enough in the first weeks. Non-surgical spinal decompression uses controlled traction to reduce load on an injured disc while you rebuild the kinetic chain. In lumbar radiculopathy, adding decompression to routine physical therapy improved pain, lumbar motion, endurance, and disability more than therapy alone over four weeks (Amjad et al., 2022).
Decompression is not a substitute for finding the stiff thorax or the restricted hip. It is a tool to calm a loaded segment so those corrections can stick. At Injury Medical Clinic PA in El Paso, decompression is paired with alignment and, when indicated, medical review by Dr. Cardenas so inflammation and nerve status are not ignored.
A Direct Plan for the Next Cutover
If your low back catches when you stand from behind a rack, treat it as a mechanical diagnosis.
Get a structural exam that measures thoracic rotation, hip motion, and lumbar control.
Restore motion to the mid-back and hips, then protect the lumbar segments.
Rebuild hinge strength and anti-rotation capacity for kneeling and reaching.
Change the lift: closer load, feet turn first, upright kneel in a low aisle.
Use decompression when disc or nerve signs are present, under a plan you understand.
You remain the decision-maker. Integrative care at El Paso Back Clinic is designed to work with your current physicians, not around them. The aim is simple: keep the lumbar spine from doing a job it was never meant to do.
Server Rack to Desk Chair: Why Data Center and IT Work Can Trigger Chronic Low-Back Pain—and What You Can Do About It
A shift can change quickly. For one hour, you sit and answer tickets. The next, you are standing on a server-room floor, crouching behind a rack, reaching for cables, or lifting hardware. By day’s end, your low back may feel tight, tired, or familiar.
For El Paso’s IT professionals, data center technicians, and network teams, recurring low-back pain rarely comes down to one “bad posture.” Sitting, standing, bending, twisting, and lifting can contribute to symptoms, but no single exposure consistently explains every case (Swain et al., 2020). The better question is which combined loads, habits, and recovery limits keep your back irritated.
Why Tech Work Can Become a Mechanical Load Problem
Your lumbar spine is built to move and carry load. Problems can appear when tissues face more stress than they comfortably recover from.
Long desk sessions reduce movement variety. Prolonged standing can also become uncomfortable; substantial occupational standing has been associated with more low-back symptoms, though it has not been proven that standing itself causes pain (Coenen et al., 2018). Add crouching, cable work, twisting, and equipment lifting, and the demand changes again.
The goal is not to fear movement. It is to improve how well your body handles it.
Sitting, Hip Stiffness, and the “Locked Up” Feeling
After hours seated, many workers stand feeling stiff through the hips and lower back. It is tempting to blame “tight hip flexors,” but low-back pain is more complex than one muscle group.
Limited hip motion can change how you bend, squat, or reach. The lumbar region may then take on more motion during some tasks. Hip mobility, trunk control, and movement variety can therefore be reasonable rehabilitation targets without claiming that tight hips automatically cause back pain.
Standing on Concrete Is Not Automatically Better Than Sitting
A standing desk may help, but standing all day is not a cure. Technical workspaces may require long periods on firm surfaces while monitoring equipment.
Variation is usually practical: sit, stand, walk, change foot position, and move when the job permits. NIOSH identifies static posture, heavy physical work, lifting, bending, and twisting among contributors to work-related musculoskeletal stress (National Institute for Occupational Safety and Health [NIOSH], 2024a).
Think “best next position,” not “perfect position.”
Crouching, Cable Work, and Rack-Side Repetition
Working behind equipment can place you in deep hip flexion, kneeling, squatting, rotation, or sustained forward bending. None is inherently dangerous. Trouble may develop when exposure is prolonged, repeated, heavily loaded, or performed while fatigued.
Bring tools closer. Raise work when possible. Use a kneeling pad or stable support when appropriate. Alternate sides instead of always rotating one way. Brief movement breaks can reduce unnecessary repetition.
Lifting Hardware: Control the Load, Not Just Your Back
Servers, batteries, monitors, and UPS components can be awkward or hard to grip. Safe lifting is not simply “keep your back straight.” Weight, distance, height, twisting, frequency, grip, and repetition matter. The Revised NIOSH Lifting Equation estimates physical stress from two-handed lifts and supports safer job design (NIOSH, 2024b).
Get close to the load, use a stable stance, avoid rushed twisting, and use team lifts or assistance when appropriate. Lifting limits should reflect the task and your current capacity.
What a Structural Assessment Should Actually Look For
Recurring low-back pain deserves more than a quick label.
At El Paso Back Clinic, a mechanical assessment can consider spinal and pelvic motion, painful patterns, hip mobility, trunk endurance, lifting mechanics, neurological findings, and positions that change symptoms. The goal is not to claim every painful back is “out of alignment,” but to identify modifiable findings and whether conservative care is appropriate.
Imaging is not necessary for every episode. History and examination help determine when testing may be appropriate. New bowel or bladder problems, saddle numbness, progressive leg weakness, major trauma, fever, or systemic symptoms require prompt medical evaluation.
Mechanical Rehabilitation: Build Capacity for Your Real Job
Rehabilitation should prepare you for work, not only help you feel better on a treatment table. Clinical guidelines support exercise and selected manual therapies for many people with acute or chronic low-back pain (George et al., 2021).
For an IT professional, rehabilitation might include hip mobility, trunk endurance, hinging, graded lifting, strength, walking tolerance, and desk-position changes. A data center technician may also need loaded carries, squat tolerance, kneeling transitions, reaching, and controlled rotation.
The plan should progress with your response. Some people need mobility; others need strength, endurance, or confidence with painful movements. Patient autonomy matters: you should understand what is tested, why treatment is suggested, alternatives, and how progress will be measured.
Where Chiropractic Care and Decompression Fit
Chiropractic care may be one part of conservative treatment when examination indicates manual care is appropriate. Guidelines include spinal manipulation among options that may help some people with chronic low-back pain, especially when paired with active care rather than used alone (World Health Organization [WHO], 2023).
“Decompression” requires careful thinking. WHO does not recommend routine traction for chronic primary low-back pain because the supporting evidence is uncertain (WHO, 2023). Decompression should not be sold as a guaranteed disc fix or universal answer.
If decompression is considered, it should follow examination, fit the symptom pattern, have clear goals, and be reassessed. Beneficence means choosing care for your clinical needs—not applying the same protocol to everyone.
Integrated Care When Back Pain Is More Than Mechanical
Persistent pain can be influenced by sleep, stress, metabolic health, medication use, recovery, and other medical factors. An integrated team can help when those issues matter.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care, mechanical rehabilitation, and functional medical assessment. Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, provides medical direction and oversight for complex medical or metabolic concerns and clinically appropriate laboratory evaluation.
Collaboration does not remove your voice. You remain the informed decision-maker.
A Better Back Strategy for El Paso Tech Workers
Whether your day moves from an El Paso desk to a server room, network closet, help-desk station, or equipment floor, your back needs more than perfect posture. It needs movement variety, smart load management, recovery, and enough strength for the work.
Start with small changes: interrupt long sitting, vary standing, improve workstation reach, keep loads close, plan awkward lifts, and build capacity gradually. If pain keeps returning, limits work, radiates into the leg, or changes how you move, seek a qualified evaluation.
At El Paso Back Clinic, our goal is to identify changeable drivers, explain your options clearly, and coordinate structural chiropractic care, mechanical rehabilitation, and medical oversight when indicated. We build the safest plan around your findings, goals, and informed choices. That approach supports safer movement, stronger function, and more confident workdays ahead.
References
Coenen, P., Willenberg, L., Parry, S., Shi, J. W., Romero, L., Blackwood, D. M., Maher, C. G., Healy, G. N., Dunstan, D. W., & Straker, L. M. (2018). Associations of occupational standing with musculoskeletal symptoms: A systematic review with meta-analysis. British Journal of Sports Medicine, 52(3), 176–183. https://doi.org/10.1136/bjsports-2016-096795
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. https://doi.org/10.2519/jospt.2021.0304
Swain, C. T. V., Pan, F., Owen, P. J., Schmidt, H., & Belavy, D. L. (2020). No consensus on causality of spine postures or physical exposure and low back pain: A systematic review of systematic reviews. Journal of Biomechanics, 102, 109312. https://doi.org/10.1016/j.jbiomech.2019.08.006
World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. World Health Organization. https://www.who.int/publications/i/item/9789240081789
Unlocking Relief: A Closer Look at Occipital Nerve Blocks for Head and Neck Pain
Abstract
This educational guide offers an in-depth, first-person look at managing head and neck pain, focusing on conditions like occipital neuralgia and cervicogenic headaches. I will walk you through the diagnostic process. Additionally, I explain how occipital nerve block injections help diagnose and treat this type of debilitating pain.
We will explore the underlying anatomy and physiology, detailing how irritation of the occipital nerves can lead to widespread symptoms. This post explains the rationale behind using a combination of a local anesthetic (lidocaine) and a corticosteroid (cortisone) to provide immediate relief. It also shows how this combination helps reduce inflammation over the long term.
We will also discuss how this intervention is a crucial part of our integrative care model at Injury Medical Clinic. This model combines medical oversight from Dr. Maria Guadalupe Cardenas, MD, with chiropractic care, functional medicine, and comprehensive rehabilitation. Together, these approaches address the root causes of pain, restore function, and promote lasting wellness.
By the end of this article, you will understand how we diagnose, treat, and holistically manage complex head and neck pain syndromes.
The Journey to Diagnosing Complex Head and Neck Pain
Hello, I’m Dr. Alex Jimenez. At our clinic, we frequently see patients who have been suffering from persistent, often debilitating, head and neck pain for months or even years. They come to us describing symptoms that can range from a dull, constant ache at the base of their skull to sharp, shooting, or electrical-shock-like sensations. These sensations may travel up the back of their head. Sometimes they even reach behind their eyes. These symptoms are characteristic of occipital neuralgia.
Occipital neuralgia occurs when the greater or lesser occipital nerves, which emerge from the upper cervical spine (neck) and run up through the scalp, become inflamed or irritated. This irritation can be caused by various factors, including:
Muscle Tension and Spasms: Chronic tension in the suboccipital muscles at the base of the skull is a primary culprit. These muscles can tighten from poor posture (like “text neck”), stress, or previous injury, compressing the nerves that pass through them.
Trauma: Injuries such as whiplash from a car accident can directly damage these nerves or cause inflammation and muscle guarding that entraps them.
Spinal Misalignments: Structural issues in the cervical spine, particularly the upper vertebrae (C1/Atlas and C2/Axis), can impinge on the nerve roots that form the occipital nerves.
Degenerative Changes: Conditions like osteoarthritis in the cervical spine can lead to bone spurs that narrow the spaces through which the nerves travel.
The journey to an accurate diagnosis begins with a thorough history and a detailed physical examination. For a patient presenting with these symptoms, I focus my evaluation on the suboccipital region. This area is located at the junction where the neck meets the skull. My goal is to reproduce the patient’s familiar pain through careful palpation.
Pinpointing the Source: A Hands-On Approach
In a recent case, I was working with a patient who had been experiencing significant posterior head pain. As I gently but firmly applied pressure to specific points along the occipital ridge, I asked for feedback. “Is that hurting right there?” I inquired. The patient’s immediate, affirmative response—”That’s it”—is a crucial diagnostic clue. This process, known as provocative testing, helps us confirm that the occipital nerves are indeed the source of the pain.
Once I identify the point of maximum tenderness, I need to mark it for the next step. This can be tricky, especially in the hairline, where traditional ink marks can be hard to see. To ensure precision, I use a two-step method. First, I use the tip of a capped ballpoint pen to create a small, temporary indentation in the skin directly over the tender spot. This provides me with a tactile landmark. Then, just below it, I place a small ink mark as a visual guide. I repeat this process to identify a second tender spot, as multiple points along the nerve’s path are often irritated.
The Occipital Nerve Block: A Targeted Intervention
After identifying and marking the precise locations of nerve irritation, the next step is to perform an occipital nerve block. This procedure serves a dual purpose: diagnostic and therapeutic.
Diagnostic Purpose: If injecting a local anesthetic provides immediate and significant pain relief, it confirms our diagnosis that the occipital nerve is the primary pain generator.
Therapeutic Purpose: The injection delivers medication directly to the site of inflammation, providing both short-term and potentially long-term relief.
Preparing for the Procedure
Before any injection, patient safety and comfort are paramount. I begin by thoroughly cleaning the marked areas with alcohol swabs to minimize the risk of infection. While a stronger antiseptic like Betadine is often used for other procedures, its application in the hairline can be messy and less practical. Given the small needle size and the superficial nature of the injection, rigorous cleaning with alcohol is sufficient.
The medication I use is a carefully measured mixture of two key components:
Lidocaine: A fast-acting local anesthetic. Its primary role is to block the sodium channels in the nerve fibers. By preventing sodium ion influx, lidocaine stops the nerve from transmitting pain signals to the brain. This is why patients often experience relief within minutes of the injection. The immediate feedback is invaluable—if the pain disappears, we know we’ve targeted the right spot.
Cortisone: This is a type of corticosteroid, a powerful anti-inflammatory agent. While lidocaine provides immediate relief, its effects are temporary. The cortisone addresses the underlying physiological problem: inflammation. It works at a cellular level to suppress the inflammatory cascade, reducing swelling, irritation, and pressure on the nerve. The therapeutic effects of cortisone develop over the coming days and can provide relief for several weeks or even months.
For this procedure, I use a thin, 1-inch, 25-gauge needle to minimize discomfort. In many cases, I would use a topical freeze spray (ethyl chloride) to numb the skin before the injection. However, in the scalp and hairline, the spray can run down into the patient’s face, eyes, or ears, which is uncomfortable and potentially hazardous. So I proceed without it. Instead, I rely on a quick, precise technique. I always communicate this to the patient: “You’re going to feel a little bit of a stick here. Is that all right?” Informed consent and clear communication help alleviate patient anxiety.
The Injection Technique: Precision and Safety
With the patient ready, I locate the first marked spot. I brace my hand and, on a count of three, gently insert the needle. The goal is to advance the needle until I feel it make contact with the surface of the occipital bone. This provides a safe and solid backstop, ensuring I don’t inject too deeply.
Before injecting the medication, I perform a critical safety assessment called aspiration. I gently pull back on the syringe plunger to see if any blood enters the syringe. If it does, the needle tip is in a blood vessel. Injecting the medication, especially the corticosteroid, directly into the bloodstream can cause systemic side effects and would not be effective locally. Seeing “nothing on aspiration” confirms the needle is in the correct tissue plane—the perineural space around the nerve.
Satisfied with the needle’s position, I slowly inject half of the medication from the syringe, bathing the inflamed nerve and surrounding tissues. I then withdraw the needle. Next, I repeat the exact same process at the second marked location, injecting the remaining half of the mixture.
Immediate Feedback and Post-Procedure Care
Immediately after the injections, I gently massage the areas. This helps spread the medication throughout the suboccipital tissues. This helps ensure the medication reaches all irritated nerve branches. This also helps alleviate some of the initial post-injection soreness.
The final and most rewarding step is to re-evaluate the patient’s pain. I apply firm pressure to the same spots that were excruciatingly tender just moments before. “Does that hurt right there?” I asked the patient. Their response changed from a pained wince to a simple “Pressure.” When I asked if it was better, they replied, “Feels better.” We checked the second spot, which had also improved significantly.
This immediate pain reduction confirms the block’s success. The lidocaine is already at work, silencing the overactive pain signals. The patient leaves the room with hope and immediate relief, while the cortisone begins its slower, more sustained work of healing the inflammation.
The Power of Integrative Care: Beyond the Injection
An occipital nerve block is a powerful tool, but it is rarely a standalone cure. At Injury Medical Clinic, we view it as one critical piece of a much larger, comprehensive puzzle. As a Family Nurse Practitioner (APRN, FNP-BC), I am qualified to perform these procedures. In addition, my foundation as a Doctor of Chiropractic (DC) and my advanced certifications in Functional Medicine (CFMP, IFMCP) provide the framework for a truly holistic approach. This is all done under the medical direction and collaboration of our esteemed internist, Dr. Maria Guadalupe Cardenas, MD. Her decades of experience provide invaluable medical oversight.
Our philosophy is that true healing requires addressing the root cause, not just masking the symptoms. The nerve block provides a crucial window of opportunity. By significantly reducing the patient’s pain, it allows us to implement other therapies effectively. These are treatments that were previously too painful to perform.
Integrating Chiropractic and Rehabilitation
This is where my expertise as a chiropractor becomes essential. With the patient’s pain under control, I can begin to address the underlying biomechanical dysfunctions. Our integrated approach includes:
Chiropractic Adjustments: Gentle, precise adjustments to the cervical spine, particularly the C1 and C2 vertebrae, can relieve mechanical pressure on the nerve roots and improve overall spinal alignment. This restores proper motion and reduces the structural stress that may have been compressing the occipital nerves.
Myofascial Release and Soft Tissue Therapy: The nerve block calms the nerve, but it doesn’t release the chronically tight muscles that are strangling it. I use advanced soft tissue techniques to break down adhesions and trigger points in the suboccipital, trapezius, and other neck muscles. This improves blood flow, reduces muscular tension, and creates more space for the nerve to function without compression.
Corrective Exercises and Rehabilitation: We provide a personalized rehabilitation program. This includes specific stretches to maintain flexibility in the neck and shoulders, along with strengthening exercises to improve postural endurance. The goal is to correct poor postural habits (like forward head posture) that often contribute to occipital neuralgia and prevent recurrence.
By combining the immediate relief of the medical injection with the long-term structural correction of chiropractic care and rehabilitation, we create a synergistic effect. The injection breaks the pain-inflammation cycle. Moreover, rehabilitative therapies address the underlying cause, supporting sustainable recovery. This multidisciplinary model—where medical, chiropractic, and functional medicine professionals work hand in hand—is the future of effective pain management and injury care.
References
Choi, H. J., & Oh, I. H. (2021). The effect of greater occipital nerve block on pulseless disease (Takayasu arteritis) with occipital neuralgia. The Korean Journal of Pain, 34(1), 126–129. https://doi.org/10.3344/kjp.2021.34.1.126
Dach, F., & Eckeli, A. L. (2021). Occipital nerve block for cervicogenic headache: A systematic review. Cephalalgia: An International Journal of Headache, 41(14), 1476–1489. https://doi.org/10.1177/03331024211027464
Naja, Z. M., El-Rajab, M. A., Al-Tannir, M. A., Faysal, W. M., & Ziade, F. M. (2006). Occipital nerve blockade for cervicogenic headache: A double-blind, randomized, controlled clinical trial. Pain Practice, 6(2), 89–95. https://doi.org/10.1111/j.1533-2500.2006.00068.x
SubQ Testosterone for Women: Dosing, Monitoring, and Muscle Support
Abstract: Testosterone is not a male-only hormone. Women make more of it than estrogen by weight throughout much of their adult lives, and those levels decline with age. The strongest research supports low-dose therapy for postmenopausal women who have distressing low sexual desire. Subcutaneous injections place a modest, consistent amount of the hormone into the fat under the skin so blood levels can return to a typical female range. This article explains how that route works, who may be a candidate, how clinicians monitor the dose, how muscle and bone support movement, and how integrative chiropractic care in El Paso can work alongside medical oversight to treat the spine, joints, and hormones as one system.
Why Women Need Testosterone, Too
Testosterone is not just a leftover male hormone; women produce it in significant amounts. Across most of adult life, a woman’s ovaries and adrenal glands produce more testosterone than estrogen by mass. That output falls with age and drops further after the ovaries are removed (Davis et al., 2019; Hatzilabrou, 2025).
When levels sit at the low end of a woman’s own range, some women notice a persistent, unwanted loss of desire. That problem has a name: hypoactive sexual desire disorder, or HSDD. Distress is the key. A quiet fade that does not bother her is not the same as a loss that troubles her every day (Davis et al., 2019; Parish et al., 2021).
Pooled randomized trials in thousands of women show that restoring testosterone into the normal premenopausal range can improve desire, arousal, orgasm, pleasure, and satisfaction, and can lower sexual distress. The gains are real and consistent, but they are moderate, not magic, and a strong placebo response is part of the picture (Islam et al., 2019; Hatzilabrou, 2025).
What Subcutaneous Injections Actually Do
A subcutaneous (SubQ) injection delivers medicine into the fatty layer just under the skin, not deep into muscle. Typical sites are the abdomen or outer thigh. The needle is short and thin. Oil-based testosterone—often testosterone cypionate—then seeps out slowly, which can keep blood levels steadier than a large intramuscular shot (FOLX Health, n.d.; Hone Health, 2024).
Think of it as a small, measured drip rather than a flood. Women need far less than men, often about one-tenth of a typical male dose. Clinics that use weekly SubQ cypionate often start in a low milligram range and then adjust to a lab result, not to a feeling (Highland Longevity, n.d.; Hone Health Help Center, n.d.).
Keep these route facts in view:
Most high-quality trials in women used patches, creams, or gels, not weekly shots (Hatzilabrou, 2025).
One older implant study in women was positive for desire and bone density, but fixed pellets can overshoot the female range and cannot be turned down once placed (Hatzilabrou, 2025).
No published milligram conversion exists from a 300-microgram patch to a SubQ syringe. The honest method is to dose to a measured blood level (Davis et al., 2019; Hatzilabrou, 2025).
No testosterone product is FDA-approved for women in the United States. Use is off-label and requires informed consent (Cedars-Sinai, n.d.; Parish et al., 2021).
Some compounding programs offer low-concentration, prefilled single-dose syringes of testosterone cypionate in MCT oil for SubQ use. A ready syringe does not change the rules. Exposure still has to stay inside the female physiologic band (Hatzilabrou, 2025; Medivant Health, n.d.).
The Target Is Narrow, Not “Bigger Is Better”
A healthy young woman typically has a total testosterone level of about 15 to 46 ng/dL. That is a sliver of the male range. The job of therapy is to land inside that band and stay there (Hatzilabrou, 2025; Braunstein et al., 2011).
Pushing past the ceiling does not add extra desire. It shows up as acne, extra facial hair, scalp thinning, voice change, and other androgen effects (Islam et al., 2019; Parish et al., 2021).
A practical path looks like this:
Confirm HSDD with real distress after other causes are checked.
Draw a baseline total testosterone with a sensitive LC-MS/MS test, not a routine immunoassay built for men (Rosner et al., 2007).
Start low.
Recheck the level and symptoms at about 8-12 weeks.
Assess benefit at 3 to 6 months. If distressing low desire has not improved, stop rather than climb (Davis et al., 2019; Parish et al., 2021).
Baseline testosterone does not diagnose HSDD. It is a safety tool once treatment starts (Hatzilabrou, 2025).
Two problems are often mistaken for low desire. Antidepressants, especially SSRIs, can blunt desire on their own. Genitourinary syndrome of menopause—dryness, atrophy, and pain with sex—can look like low desire when the real issue is pain. Local estrogen, not a systemic androgen, is built for that problem (Parish et al., 2021; Cedars-Sinai, n.d.).
What the Body May Gain Beyond Desire
Sexual function is the outcome with the firmest trial support. Other claims need a quieter voice.
Muscle and strength. Testosterone helps muscle protein building in both sexes. Some women report better lean mass and training response when testosterone levels return to a mid-physiologic range. Large pooled trial data in women have not shown a robust body-composition effect at the low doses used for HSDD, so frame this as possible support, not a guarantee (Islam et al., 2019; Hatzilabrou, 2025).
Bone. One small two-year implant trial found faster gains in spine, hip, and total-body density when testosterone was added to estradiol. Guidelines still do not list bone as an approved reason to prescribe it because the study was small and not designed to prevent fractures (Davis et al., 1995; Wierman et al., 2014).
Energy and mood. Early and smaller studies sometimes showed better well-being. Dedicated trials and systematic reviews have been mixed or null for mood, fatigue, and cognition. Societies do not endorse testosterone as a general menopause tonic (Islam et al., 2019; Dichtel et al., 2020; Cedars-Sinai, n.d.).
Red blood cells. Testosterone can raise red-cell production. That is a monitoring issue at higher exposure, not a reason to treat ordinary anemia in women (Hatzilabrou, 2025).
For the spine and joints, even modest improvements in muscle and bone health matter. Stronger hip and core muscles help the pelvis stay level. Better bone quality supports the vertebrae that a chiropractor adjusts. After a car crash, a work injury, or months of guarded movement, patients who can train without crashing energy often stay in rehab longer (Jimenez, n.d.-a).
Safety, Side Effects, and the Long View
Short- and medium-term data at physiologic doses are generally reassuring for the day-to-day effects clinicians watch: acne, extra hair, and oily skin. Those effects are usually dose-related and often fade if the dose is cut (Islam et al., 2019; Nachtigall et al., 2011).
What is missing is the long view. Adequately powered trials have not settled cardiovascular and breast outcomes over many years. That gap—not a proven harm signal—is a main reason no female product has been approved (Hatzilabrou, 2025; Cedars-Sinai, n.d.).
Therapy is not for pregnancy, breastfeeding, or people trying to conceive. Women with high baseline heart or breast-cancer risk need an especially clear shared decision (Hone Health Help Center, n.d.; Parish et al., 2021).
How Integrative Chiropractic Care Fits
Hormones don’t exist apart from the skeleton. Low energy, weaker muscles, and slower recovery make spinal joints stiffer and make rehab after an auto accident harder. Integrative care treats that loop instead of handing a woman only a syringe or only an adjustment.
At Injury Medical Clinic PA in El Paso, Texas (11860 Vista Del Sol, Suite 128), we build care as a team. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, is dual-licensed as a chiropractor and board-certified family nurse practitioner. His clinical writing stresses that female testosterone use is not a copy of male replacement: the best randomized evidence is still transdermal; SubQ use in women is an individualized off-label choice, and the goal is a physiologic range with a stop rule if desire does not improve (Jimenez, n.d.-b).
Dr. Maria Guadalupe Cardenas, MD, is his internist and is board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), with more than 40 years of experience. She serves as medical director and collaborative physician. In this model, the internist provides medical direction, reviews labs and overall health, and helps keep advanced or off-label therapies within safe bounds. The chiropractor restores joint motion, posture, and neuromuscular control. Functional medicine looks at sleep, gut health, thyroid, iron, and medications that can blunt desire. Personal injury and rehabilitation services rebuild strength after crashes, falls, and sports injuries, so a hormone plan isn’t asked to do the work of a weak core or an unhealed disc (Jimenez, n.d.-a).
That mix is common in integrated injury clinics: an MD directs the medical lane while a DC treats the mechanical lane. For a woman on low-dose testosterone, the practical payoff is simple. If the muscles around the spine hold better, adjustments last longer. When bone and lean mass improve, fall risk and “I feel fragile” complaints may ease. If pain and sleep improve, desire often has a clearer path—without pretending testosterone is a cure for every menopausal complaint.
A Clear Path Forward
Testosterone treatment in women is neither a wellness trend nor a male protocol scaled down by guesswork. It is a narrow, evidence-backed option for postmenopausal HSDD with distress, given at a female physiologic dose, watched with the right lab, and stopped if it does not help.
Subcutaneous injections can deliver that modest, steady dose into the fat under the skin. They ask for discipline: start low, measure, stay inside the range, and pair the hormone with the rest of the care—local vaginal treatment when dryness is the real problem, medication review when an antidepressant is the real problem, and hands-on musculoskeletal care when the spine and hips cannot carry the load.
In El Paso, that whole-person path is the point of the collaboration between Dr. Cardenas’s internal medicine oversight and Dr. Jimenez’s chiropractic, functional medicine, and injury rehab work. The hormone is only one tool. The goal is a woman who can move, recover, and feel like herself again.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine