Back Clinic Personal Injury Chiropractic Team. Injuries from an accident can not only cause physical harm to you or a loved one, being involved in a personal injury case can often be a complicated and stressful situation to handle. These types of circumstances are unfortunately fairly common and when the individual is faced with pain and discomfort as a result of trauma from an accident or an underlying condition that has been aggravated by the injury, finding the right treatment for their specific issue can be another challenge on its own.
Dr. Alex Jimenez’s compilation of personal injury articles highlights a variety of personal injury cases, including automobile accidents resulting in whiplash, while also summarizing various effective treatments, such as chiropractic care. For more information, please feel free to contact us at (915) 850-0900 or text to call Dr. Jimenez personally at (915) 540-8444.
Why the Base of Your Skull May Hurt After a Car Accident
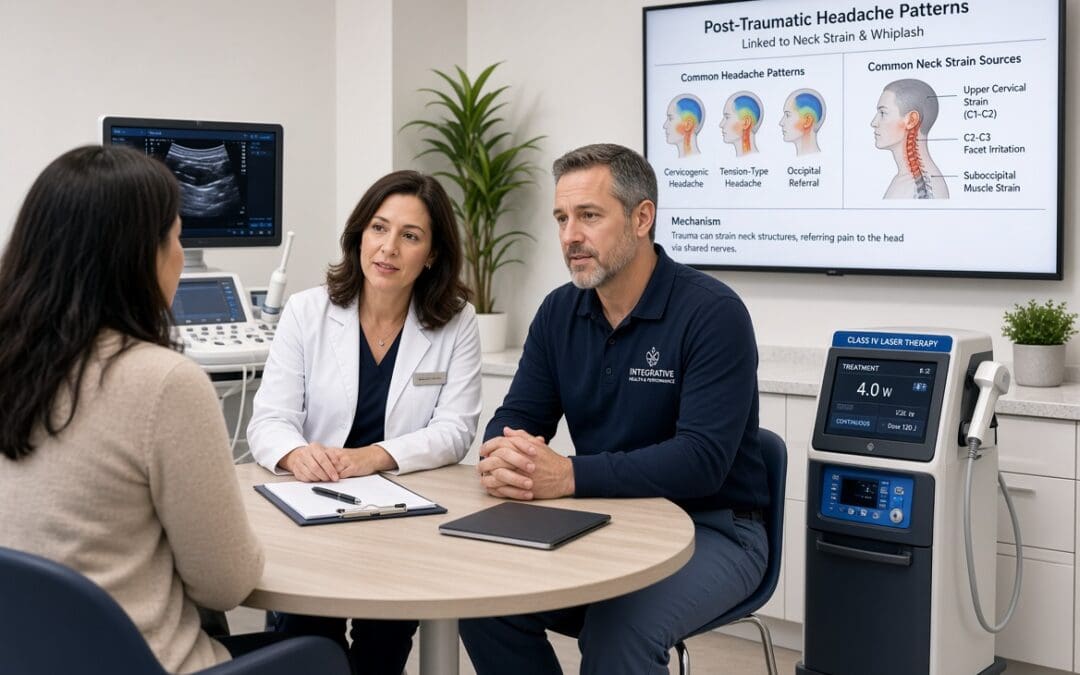
After a rear-end collision on I-10 or Loop 375, many people focus on the stiff, aching feeling in the neck and shoulders. They notice they can’t fully turn their head. Their muscles feel tight, and certain positions make everything worse. However, what often goes unrecognized is that the same forces can produce persistent discomfort right at the base of the skull. This is the sub-occipital region where the upper neck meets the occiput. Patients often treat this as “just neck stiffness.” As a result, they may not connect it to the need for a broader evaluation of headache patterns that may develop days or weeks later.
Pain near the base of the skull after trauma does not automatically mean occipital neuralgia or cervicogenic headache. Those are specific clinical diagnoses that require more than pain location. The same area can be involved in myofascial tension or post-traumatic headache patterns. Additionally, migraine can become more frequent after injury. Multiple factors can be at play, too. Distinguishing among them matters because the treatment path and the documentation needed for recovery both depend on an accurate picture of what is driving the symptoms.
How Collision Forces Affect the Upper Neck and Occiput
In a typical rear-end impact, the head accelerates rapidly and then decelerates. The upper cervical segments (C1–C3) and the small sub-occipital muscles experience shear and stretch forces. These muscles—rectus capitis posterior major and minor, obliquus capitis superior and inferior—help control fine head movement and are richly supplied with sensory receptors. When they become irritated, or when protective guarding sets in, patients feel a deep, aching, or pressure-like discomfort at the base of the skull. This discomfort can radiate upward. Alternatively, it can feel worse with sustained postures, such as driving or looking at a screen.
Ligaments and facet joints in the upper cervical spine can also be stressed. Because sensory information from these structures converges with fibers from the trigeminal system in the brainstem (the trigeminocervical complex), the brain can perceive irritation in the upper neck as head pain. This is true even when the primary problem is mechanical. As a result, this referral pattern is common after whiplash-type forces. However it is only one possible contributor.
Why Location Alone Does Not Confirm a Specific Diagnosis
Occipital neuralgia involves irritation or entrapment of the greater, lesser, or third occipital nerves. It typically produces sharper, shooting, or electric-like pain that starts at the skull base and radiates toward the vertex or behind the eye, often with scalp tenderness. The pain is usually unilateral and can be provoked by pressure along the nerve pathway or by certain neck movements. Diagnosis rests on the characteristic quality and distribution of pain, along with clinical findings. Temporary relief after a diagnostic nerve block can also support the impression. However, discomfort location alone is not sufficient.
Cervicogenic headache is a secondary headache attributed to a disorder of the cervical spine or its soft tissues. Formal criteria (ICHD-3) require evidence of a cervical source capable of producing headache, along with a clear link—such as onset or worsening that matches the cervical problem, reproduction of the familiar head pain by neck movement or sustained posture, restricted cervical motion, and improvement when the cervical disorder improves. Pain that simply starts near the base of the skull does not meet these requirements. Many post-collision patients have restricted upper-cervical motion and sub-occipital tenderness without meeting full criteria for cervicogenic headache.
Other possibilities include:
Myofascial pain from trigger points in the sub-occipital group, upper trapezius, or semispinalis capitis that refer pain into the head.
Post-traumatic headache that may take a migraine-like or tension-type form and can coexist with neck findings.
Mixed presentations in which neck mechanics lower the threshold for an underlying migraine pattern that becomes more frequent after trauma.
A thorough evaluation looks at headache quality, frequency, associated features (nausea, light or sound sensitivity, visual changes), and the relationship to neck movement. It also includes neurological screening and objective measures of cervical motion and soft-tissue findings. Imaging may be indicated in selected cases. Still, many relevant findings are clinical.
What a Broader Evaluation Looks Like in Practice
Patients who come in focused only on neck stiffness often benefit when the clinician also asks about headache days. It is important to discuss whether the head pain starts at the base of the skull and moves forward. The clinician should also ask whether certain neck positions reliably trigger it. Evaluation should also cover how it affects sleep, concentration, and daily activities. Digital range-of-motion measurements, segmental palpation, and provocative testing help document the mechanical component. Also, when headache frequency is rising, a simple headache diary helps track whether the pattern is stabilizing or worsening.
Conservative care can address the mechanical contributors without assuming a single diagnosis. Gentle upper-cervical mobilization or adjustment, myofascial release of the sub-occipital muscles, postural retraining, and graded exercises for deep neck flexors often reduce both neck restriction and the referred component of head discomfort. When indicated, neurofunctional acupuncture or electroacupuncture may help modulate local muscle tension and pain pathways. These approaches are chosen because they target stressed structures while minimizing the need for prolonged medication. They also reduce the likelihood of needing more invasive procedures.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, brings dual-licensure training that allows simultaneous attention to soft-tissue mechanics and the broader medical context of post-traumatic symptoms. Working with Medical Director Dr. Maria Guadalupe Cardenas, MD (board-certified in internal medicine), the team can coordinate laboratory evaluation when metabolic or inflammatory factors may be amplifying recovery. Additionally, they provide oversight when headache patterns require medical attention. Injury Medical Clinic PA is one of the only integrated clinics in El Paso that combines this dual-scope expertise under one roof. This arrangement allows soft-tissue findings, functional measures, and medical direction to be documented together. As a result, this coordination supports both clinical decision-making and the clear records often needed when attorneys evaluate causation after collisions on local freeways.
Supporting Recovery While Protecting Patient Choice
Beneficence is served when care targets the actual drivers of symptoms—whether mechanical restriction, muscle guarding, or a developing headache pattern—rather than treating every base-of-skull complaint the same way. Patients typically gain improved neck motion, reduced frequency or intensity of associated head discomfort, better sleep, and a clearer sense of which activities remain limited. Non-maleficence is supported by prioritizing non-invasive options first. Moreover, many people improve with targeted chiropractic and soft-tissue work without progressing to chronic reliance on analgesics or prematurely considering injections or surgery. Explaining the differential clearly reinforces autonomy. This helps the patient understand why a broader headache evaluation is useful even when the most obvious complaint is neck stiffness. Shared records and coordinated communication with the patient’s existing medical team keep the individual in control of decisions.
Objective documentation—timed motion measurements, consistent examination findings, and correlation with the mechanism of injury—helps distinguish traumatic aggravation of upper-cervical structures from pre-existing conditions under the Texas Eggshell Plaintiff rule. When the records show that the collision produced measurable changes in the region that can refer pain into the head, both clinical care and the legal file are strengthened. In addition, the clinic’s resources on integrated headache management, occipital neuralgia approaches, post-accident headache relief, and the role of chiropractic findings in establishing causation also discuss how cervical findings intersect with headache patterns.
If neck stiffness after a collision is accompanied by discomfort at the base of the skull, or if headaches seem to be increasing, a focused evaluation that looks beyond the neck alone can clarify the picture and guide the next steps in recovery.
References
International Headache Society. (2018). The International Classification of Headache Disorders (3rd ed.). Cephalalgia, 38(1), 1–211. doi.org/10.1177/0333102417738202
Bogduk, N., & Govind, J. (2009). Cervicogenic headache: An assessment of the evidence on clinical diagnosis, invasive tests, and treatment. The Lancet Neurology, 8(10), 959–968. doi.org/10.1016/S1474-4422(09)70209-1
Barmherzig, R., & Kingston, W. (2019). Occipital neuralgia and cervicogenic headache: Diagnosis and management. Current Neurology and Neuroscience Reports, 19(7), Article 20. doi.org/10.1007/s11910-019-0933-z
Headache Classification Committee of the International Headache Society. (2018). Headache attributed to trauma or injury to the head and/or neck. In The International Classification of Headache Disorders (3rd ed.). Cephalalgia, 38(1), 1–211.
Bogduk, N. (2001). Cervicogenic headache: Anatomic basis and pathophysiologic mechanisms. Current Pain and Headache Reports, 5(4), 382–386. doi.org/10.1007/s11916-001-0029-7
Explore how causation combined with chiropractic care can alleviate discomfort and improve quality of life for better health from neck pain.
Abstract: Understanding Neck Pain, Whole-Body Symptoms, and the Path to Recovery
Neck pain is more than discomfort between the shoulders and the base of the skull. The cervical spine protects the spinal cord, supports the head, positions the eyes, contributes to balance, and provides movement needed for work, driving, sleep, exercise, and ordinary family life. When cervical muscles, joints, discs, ligaments, or nerves become irritated, the consequences may spread far beyond the neck. A person may experience stiffness, headaches, shoulder pain, tingling into an arm, reduced concentration, fatigue, poor sleep, or fear of movement. Some of these problems arise directly from a cervical disorder; others are associated conditions that require their own evaluation rather than being automatically attributed to the spine.
In this educational guide, I explain the anatomy and physiology of neck pain, its many possible causes, the differences between mechanical pain and dangerous medical conditions, and how symptoms affect physical function and emotional well-being. I describe how chiropractic care, therapeutic exercise, soft-tissue treatment, ergonomic changes, and coordinated medical oversight may support recovery without surgery when appropriate. I also examine the special challenge of personal injury causation: showing that an accident occurred, that a particular injury exists, and that a medically reasonable explanation connects the two. Texas law requires a sound evidentiary foundation, not simply a diagnosis made after a collision.
The approach discussed here reflects coordinated care at Injury Medical Clinic PA in El Paso. I work as a chiropractor and family nurse practitioner alongside Dr. Maria Guadalupe Cardenas, MD, an internist with over four decades of experience who serves as Medical Director and Collaborative Physician. We consider biomechanics, neurological examination, rehabilitation, medical illnesses, medications, sleep, and patient goals together, while respecting each clinician’s distinct responsibilities. The goal is not to promise that every symptom will disappear. It is to identify important diagnoses, protect patient safety, use the best available evidence, document meaningful progress, and help people return to the activities they value.
This article is educational, not a diagnosis or individualized treatment order. New neurological deficits, suspected fracture, stroke-like symptoms, infection signs, or severe headache after trauma require immediate medical assessment.
Why Neck Pain Matters Far Beyond the Cervical Spine
When a person says, “My neck hurts,” the statement may describe many different experiences. One person has a dull ache after eight hours at a desk. Another feels a sharp catch when turning toward traffic. An athlete notices weakness after a collision. A driver develops neck stiffness and headache the morning after being rear-ended. Their complaints may sound similar, but the underlying problems and appropriate next steps can differ greatly. In my clinical work, I start by asking what the patient was doing when symptoms began, what movements provoke them, whether the pain travels, and what has changed in everyday life.
The worldwide burden is considerable. The GBD 2021 Neck Pain Collaborators (2024) estimated that about 203 million people experienced neck pain in 2020 and projected that the number could reach approximately 269 million by 2050. The estimate does not mean every case is severe or traumatic. It does show why prevention, effective triage, and access to conservative care matter. Neck pain affects people who sit for long periods, perform physical labor, care for children, drive for work, play sports, or live with age-related degenerative changes.
The clinical significance of neck pain cannot be measured by an image or a number on a pain scale alone. A patient who rates pain at four out of ten may be unable to shoulder-check while driving, sleep comfortably, or lift a toddler. Someone with a higher score may continue many activities but need to pace. I therefore ask about participation, not just symptoms. How many hours can the person work? Can they turn their head far enough to see an approaching car? How often do they wake at night? Are they avoiding exercise because movement feels threatening? Those answers help shape care and, when an injury claim is involved, create a more complete account of impairment (Blanpied et al., 2017).
Neck pain is a symptom, not a single diagnosis. It may reflect muscle strain, joint sensitivity, disc pathology, nerve root irritation, inflammatory illness, referred pain, or serious but uncommon conditions. A precise explanation begins with understanding the structure and function of the cervical region.
Cervical Spine Anatomy: Seven Vertebrae With Many Responsibilities
The cervical spine contains seven vertebrae labeled C1 through C7. Together with the discs, small joints, ligaments, muscles, nerves, and surrounding blood vessels, these structures permit a remarkable combination of mobility and protection. C1, the atlas, supports the skull. C2, the axis, helps permit head rotation. Lower cervical segments contribute importantly to flexion, extension, side-bending, and combined turning. No single joint completes a normal head movement on its own. Several levels cooperate while muscles guide and stabilize them.
The cervical spinal canal contains the spinal cord. From this central structure, nerve roots exit through openings called neural foramina. Those roots transmit information between the brain and the upper limbs, including movement commands, touch, position sense, and many reflexes. In the neck, structures operate very close together. A painful joint can limit movement and encourage muscle guarding. A disc or narrowing of a neural opening may irritate a nerve root. In contrast, a problem affecting the spinal cord can cause changes in hand coordination, walking, balance, or bladder function that call for a different level of urgency.
The spine also supports the senses. Vision, vestibular information from the inner ear, and sensory input from neck muscles and joints help you know where your head is in space. When pain alters cervical movement or muscular control, some people feel less steady or experience movement-related dizziness. Yet dizziness has many other causes, including vestibular disorders, low blood pressure, medication effects, concussion, and vascular disease. Dizziness alone never establishes a cervical origin.
I explain anatomy to patients because understanding the system can reduce unnecessary fear. A neck that feels stiff is not automatically “out of place,” and a noisy joint is not automatically damaged. The neck is a living, adaptable structure. Recovery generally depends on making a correct diagnosis, selecting safe movement, rebuilding capacity, and addressing associated health factors.
Cervical Discs: Load Sharing, Nerve Space, and Disc Findings on MRI
Between most cervical vertebral bodies sits an intervertebral disc, composed of a gel-like nucleus pulposus surrounded by layers of fibrous tissue called the annulus fibrosus. The disc helps distribute load and allows controlled motion. It is not a simple cushion that can always be “pushed back” into position. Its structure changes with age, loading history, genetics, and disease. An MRI may describe disc desiccation, reduced height, a bulge, a protrusion, or an extrusion. These words describe imaging features; they do not, on their own, determine whether the disc is painful or whether a collision caused the finding.
A cervical disc problem becomes especially relevant when the clinical picture matches its location. For example, a patient with neck pain traveling into an arm, altered sensation in a particular pattern, reduced reflexes, or weakness may have cervical radiculopathy. The clinician compares the neurological examination with imaging when imaging is indicated. A left-sided disc finding may be less convincing as the sole explanation for isolated right-sided symptoms. Likewise, a common age-related bulge without nerve compression should not automatically become the centerpiece of a personal injury claim.
Discs contain biologically active cells that respond to mechanical load and inflammatory signals. Injury or degeneration can change the local chemical environment. In some cases, inflammatory mediators near a nerve root contribute to pain even when physical compression seems modest. This helps explain why pain intensity is not always proportional to the size of a disc abnormality. It also explains why treatment should target the person and functional deficits, rather than an image alone.
When reviewing a cervical MRI, I discuss both its findings and its limits. The scan can reveal anatomy that requires referral or additional care, but it cannot reliably date many degenerative abnormalities. Clinical correlation means matching imaging with symptoms, exam findings, prior records, and the course of recovery. This is essential in medical care and equally important when answering a causation question (American College of Radiology [ACR], 2024a).
Facet Joints, Ligaments, and the Deep Stabilizing Muscles
Each cervical motion segment contains small facet joints behind the vertebral bodies. These joints help guide movement and transfer forces. Their capsules contain sensory nerve endings that may become irritated with injury, repetitive loading, or degenerative change. A patient with facet-related pain may describe local stiffness, pain with rotation or extension, or aching toward the shoulder blade. However, no single symptom or palpation finding conclusively identifies a facet joint as the source. In selected persistent cases, specialist diagnostic blocks may be considered when the result would change care.
Ligaments connect bones and help limit excessive motion. An acute sprain is an injury to ligamentous tissue, while a strain involves muscle or tendon. These terms are often used together after whiplash, but their meanings should not be blurred. Significant ligament instability requires appropriate imaging and specialist judgment before hands-on cervical treatment. Ordinary muscle tenderness does not prove a ligament tear, and post-crash pain does not establish structural instability.
The deep cervical flexors and deep extensors perform important stabilizing and position-sensing roles. Larger muscles, including the trapezius, levator scapulae, sternocleidomastoid, and scalene muscles, help position the head and shoulder girdle. After pain begins, people often recruit large superficial muscles more forcefully while moving with less variety. This protective pattern can become exhausting. It may also contribute to persistent tightness even after the original tissue irritation has improved.
Researchers, including James Elliott and collaborating research groups, have studied cervical muscle composition in people with persistent whiplash-associated disorders. MRI investigations have reported differences in fatty infiltration of some deep cervical muscles between more severely affected groups and controls. These are group-level associations, not a diagnostic stamp proving a particular accident. They support careful study of muscle function and the inclusion of graded conditioning in rehabilitation, while reminding us to interpret each image cautiously (Karlsson et al., 2016; Smith et al., 2020).
Cervical Nerves and Why Neck Pain Can Reach the Shoulder, Arm, or Hand
The nervous system communicates through electrical signaling and chemical transmission. Sensory neurons carry information toward the spinal cord, while motor pathways help activate muscles. A patient with irritated cervical nerve tissue may experience shooting pain, pins-and-needles, burning, numbness, or weakness. These symptoms deserve more attention than ordinary local soreness because they can indicate a nerve-root disorder. The exact pattern matters, but textbook maps overlap, and individual presentations vary.
The clinician checks arm and hand strength, reflexes, sensation, and symptom reproduction through appropriate tests. A diminished biceps reflex, for example, means something different from a diffuse feeling that the entire hand is numb. Problems outside the neck can mimic cervical radiculopathy. Carpal tunnel syndrome, ulnar neuropathy, shoulder disease, peripheral neuropathy, and some systemic illnesses can cause similar symptoms. In uncertain cases, electrodiagnostic studies or specialist assessment may help distinguish peripheral nerve entrapment from cervical-root disease (Coker et al., 2024).
It is important to separate radiculopathy from myelopathy. Radiculopathy primarily involves a nerve root and often produces arm symptoms. Myelopathy involves spinal cord dysfunction and may cause clumsy hands, gait changes, abnormal reflexes, or leg symptoms. Suspected myelopathy changes the treatment plan immediately. It is not a condition to manage with routine cervical manipulation while awaiting spontaneous improvement.
A patient-friendly explanation is that nerves are communication pathways, not merely “wires” that get pinched. They can become mechanically sensitive, inflamed, or impaired by conditions affecting multiple parts of the body. Treatment starts with identifying what is actually involved. The aim is to protect neurological function, reduce avoidable irritation, and restore activity while monitoring for worsening deficits.
Pain Physiology: Nociception, Inflammation, and the Brain’s Protective Response
Nociception is the process by which specialized nerve endings detect potentially damaging mechanical, chemical, or thermal conditions. Pain is the experience the nervous system creates in response to many influences, including nociceptive input, prior learning, attention, sleep, expectations, stress, and the surrounding situation. Pain is real whether imaging shows a dramatic abnormality or not. At the same time, pain is not a direct ruler measuring tissue damage. This distinction is useful when symptoms feel larger than the visible findings.
After an injury, inflammatory cells and local tissues release signaling molecules that help coordinate healing. Some of those signals temporarily lower the threshold of pain-sensitive nerves. The area may feel tender or unusually reactive, and nearby muscles may stiffen protectively. This response can be helpful for a short period because it encourages caution. Problems develop when ongoing sensitivity and avoidance lead to loss of strength, poor sleep, reduced confidence, and less activity. A person may begin to anticipate pain even during safe movement.
Peripheral sensitization describes heightened responsiveness of nerve endings near affected tissue. Central sensitization refers to altered processing within the central nervous system and may contribute to some persistent pain states. These concepts should not be used as catch-all explanations when a diagnosis is uncertain. They describe possible mechanisms, not an accusation that pain is imaginary. Before applying them, clinicians must assess neurological disease, inflammatory conditions, infection, fracture, and other medical explanations when indicated.
In practice, these mechanisms explain why an individualized plan can combine reassurance, graded movement, sleep support, hands-on care, and medical assessment. Each intervention addresses a different part of the problem. Passive relief may make activity more comfortable, but sustainable gains often depend on progressively rebuilding capacity. This is why I ask what a patient can do today, what they could do before symptoms began, and what meaningful change we can measure over time.
Whiplash After a Car Accident: Mechanism, Symptoms, and Clinical Uncertainty
Whiplash is an acceleration-deceleration event involving the head and neck, commonly associated with motor vehicle collisions. In a rear-end impact, the vehicle and torso may move forward while the head initially lags, followed by changes in cervical posture and acceleration. The precise sequence depends on seat position, restraint geometry, head orientation, impact direction, and the circumstances of the crash. Side impacts, falls, and sporting collisions may also produce neck trauma. The term “whiplash” describes an injury mechanism; whiplash-associated disorder refers to the clinical consequences.
Some people have neck pain and stiffness without neurological abnormalities. Others have headache, shoulder pain, altered movement, dizziness, sleep disturbance, or arm symptoms. Not every complaint has the same cause. The patient may have a coexisting concussion, shoulder injury, vestibular disorder, or preexisting degenerative condition. The examination must sort through these possibilities rather than assume that all symptoms flow from a single sprain.
The amount of visible vehicle damage is not a reliable stand-alone measure of injury severity. Nor does a description of a low-speed collision prove that serious tissue injury occurred. Vehicle details contribute to mechanism analysis, but medical conclusions must still be tied to contemporaneous symptoms, physical findings, risk factors, imaging when indicated, and reasonable alternatives. An expert should not infer a specific disc injury from property damage photographs alone.
The early days after a collision are especially important. A person may initially notice generalized soreness and later recognize focal neck pain, headache, or restricted turning. Delayed reporting is possible, but it is not automatic proof of a causal relationship. Accurate documentation should record the earliest remembered symptom, how it changed, what care was obtained, and whether another event occurred. However, never dismiss immediate emergency warning signs as routine delayed whiplash symptoms.
Common Neck Pain Symptoms: Reading the Pattern Instead of Guessing the Cause
The first step in treating neck pain is describing what the patient actually experiences. Pain quality, location, timing, radiation, and triggers can direct the examination. A deep ache after a long workday suggests a different investigation from sudden severe neck pain after a fall. Someone who wakes with stiffness but improves after gentle movement may need a different plan than someone whose arm weakness is progressively worsening. Symptoms provide clues, but clinical interpretation requires examination rather than an internet diagnosis.
Common symptoms include:
Local aching or tenderness near the cervical muscles and joints.
Reduced range of motion, especially when turning the head or looking upward.
Muscle guarding, tightness, or spasms around the neck and shoulder girdle.
Pain between the shoulder blades or discomfort that spreads toward the upper back.
Headache that may accompany neck pain or be provoked by certain neck movements.
Arm pain, numbness, tingling, or weakness that raises concern for nerve involvement.
Movement-related dizziness or a sense of imbalance that requires differential diagnosis.
Sleep disruption, fatigue, and difficulty concentrating associated with persistent discomfort.
The order in which symptoms appear can matter. If a patient reports a new symptom during recovery, I revisit the history and examination rather than simply adding it to the original diagnosis. A new weakness, an increasingly severe headache, or a change in walking may signal a problem requiring urgent reassessment. Conversely, fluctuating soreness during a graded exercise program can occur without a new structural injury. Context determines the response.
It is tempting to divide patients into “minor” and “major” pain categories based on a single number. A more useful clinical picture includes severity, irritability, and functional consequences. Irritability asks how easily symptoms begin, how intense they become, and how long they last after activity. This information guides how much movement or manual treatment is reasonable. It also provides a practical baseline for judging recovery.
Mechanical Neck Pain and Muscle Strain
Mechanical neck pain is a broad term for symptoms influenced by movement, position, or physical loading without a clearly identified serious medical condition. It may arise from several structures at once. A worker who spends hours looking down may report tenderness, reduced rotation, and aching around the shoulder blades. Someone who lifts a heavy object with their arms extended may develop discomfort in the cervical and shoulder muscles. The clinical goal is to determine which tasks exceed present capacity and which movements are safe enough to restore.
A muscle strain can involve microscopic damage or overload of muscle fibers and associated connective tissue. The body responds with an inflammatory and repair process. Most uncomplicated strains do not require advanced imaging, but trauma severity and examination findings can change that decision. Management often starts with tolerable movement, symptom control, and temporary modification of activities that sharply increase pain. Prolonged avoidance may reduce conditioning and increase apprehension.
I explain that muscle tightness can be both a primary problem and a secondary protective response. If a painful cervical joint causes the surrounding muscles to tense, forceful stretching may aggravate the situation. On the other hand, gentle range-of-motion practice, heat in an appropriate setting, relaxation of excess muscular guarding, and progressive endurance work may improve comfort. The treatment is adjusted to tissue irritability, age, medical history, and the person’s actual goals.
The patient should leave with clear answers to three questions: what activities are safe, what changes would be concerning, and how progress will be measured. A home plan might initially use comfortable neck turns and walking, then advance to scapular control and resistance work. Manual care may help create a window for active rehabilitation, but it is not a substitute for restoring strength and confidence in movement.
Cervical Radiculopathy: When Arm Symptoms accompany Neck Pain
Cervical radiculopathy occurs when a cervical nerve root becomes irritated or dysfunctional. Patients may notice pain extending from the neck or shoulder region into the arm, tingling in the fingers, altered sensation, diminished reflexes, or muscle weakness. Pain may be severe even when imaging appears modest, and some people have relatively little neck pain despite prominent arm symptoms. A thoughtful neurological examination is therefore crucial (Coker et al., 2024).
Possible contributors include a disc herniation, age-related neural foraminal narrowing, inflammatory irritation, or combinations of these processes. The clinician should not assume that numb fingers always come from the neck. Median or ulnar nerve entrapment, diabetes-associated neuropathy, and other peripheral disorders may produce similar complaints. I compare symptom distribution with motor function, reflexes, sensory findings, provocative tests, and medical history. If the findings conflict, we reconsider the working diagnosis.
Many patients can begin with conservative management when serious neurological compromise is absent. Depending on the case, treatment may include education, activity modification, appropriately selected exercises, symptom-modifying manual techniques, and medical management. A person with pronounced nerve irritability may initially tolerate small movements better than aggressive stretching or high-force interventions. Persistent or worsening objective weakness, signs of spinal cord involvement, or uncontrolled pain may require imaging and specialist referral.
Research does not support presenting a single nonsurgical technique as a guaranteed cure. A systematic review of conservative care for cervical radiculopathy found that evidence for several interventions remained low or very low in certainty (Plener et al., 2023). More recent reviews comparing surgery with nonsurgical care report a nuanced picture: surgery may offer earlier relief or benefit selected patients, while pooled long-term outcomes can be similar among appropriately selected groups. Those findings do not erase the need for prompt surgical assessment when neurological deterioration or other indications are present (Dar et al., 2026; Kale et al., 2026).
Cervical Myelopathy and Other Neurological Warning Signs
Degenerative cervical myelopathy or traumatic spinal cord compromise should not be confused with ordinary neck stiffness. Spinal cord dysfunction can produce difficulty with buttons or handwriting, repeated dropping of objects, loss of fine motor coordination, unsteady walking, unusual reflexes, and sometimes bowel or bladder changes. Some patients do not report dramatic neck pain. The neurological changes themselves become the most important part of the story.
When I hear about progressive hand clumsiness or gait disturbance, my objective shifts from providing routine pain relief to identifying possible cord disease and arranging appropriate medical assessment. Symptoms may come from several conditions, so the diagnosis requires clinical examination and often MRI. A concerning symptom does not prove myelopathy, but it justifies caution. Manipulation should not proceed as though the person has uncomplicated mechanical neck pain while the possibility of cord compression remains unresolved.
Weakness should be described carefully. A person may feel weak because pain prevents a strong effort, while another has genuine loss of nerve-mediated muscle force. Recording the specific movement, comparison with the opposite side, reflexes, sensation, and change over time is more informative than simply writing “weakness.” This principle matters for both treatment and medicolegal documentation.
The long-term goal is to prevent avoidable harm. Some diagnoses require medications, injections, or specialist surgery rather than a predominantly chiropractic plan. The advantage of multidisciplinary care is not that one team can treat every condition in-house. It is that concerning findings can be recognized, communicated, and directed to the right professional without unnecessary delay.
Cervicogenic Headache and the Neck-Head Connection
A cervicogenic headache is a headache attributed to a disorder of the cervical spine or related structures. The upper neck and head share interacting sensory pathways, often discussed through the trigeminocervical complex. Pain signals originating in upper cervical tissues may be perceived in regions of the head, while headaches of other origins can make the neck feel sore. This convergence explains why location alone cannot separate one headache disorder from another.
A patient may report pain beginning in the upper neck and traveling toward the back of the head or temple, sometimes associated with restricted cervical movement. Those findings raise a possibility but do not establish the diagnosis. Migraine frequently includes neck pain, sensitivity to light, nausea, and changes in activity tolerance. Tension-type headache, occipital neuralgia, temporomandibular disorders, and post-traumatic headache can overlap. A new or unusually severe headache after injury requires evaluation for dangerous causes before being labeled cervicogenic.
When cervical dysfunction is contributing, selected manual therapy and exercise approaches may reduce symptoms. A systematic review published in 2026 found that manual therapy may provide short-term relief for cervicogenic headache, while the certainty of evidence for durable effects and the added benefits of combined treatment was limited (Martins et al., 2026). That result supports trying well-selected care and measuring response, but does not promise that every headache will resolve through spinal adjustments.
Clinical observation can help refine the hypothesis. Does the headache change when cervical movement improves? Do sleep and function recover together? Is headache frequency actually decreasing in a diary? These questions matter because a brief feeling of relaxation after treatment does not equal sustained improvement. When migraine or another primary headache disorder is present, chiropractic care may address coexisting mechanical neck symptoms, but evidence-based headache medicine remains essential.
Occipital Neuralgia and Pain at the Back of the Head
Occipital neuralgia involves irritation or dysfunction of nerves supplying the back of the scalp. People may describe brief shooting, electric, stabbing, or burning pain beginning near the upper neck and moving toward the scalp. Tenderness over an occipital nerve may occur. However, similar discomfort can accompany migraine, cervicogenic headache, local muscle sensitivity, and other conditions. A precise diagnosis depends on characteristic symptoms, examination, and sometimes the response to a specialist diagnostic nerve block.
Why does the distinction matter? Because the treatment target changes. If a patient has prominent upper-neck muscle guarding alongside an established occipital neuralgia diagnosis, gentle soft-tissue techniques and movement rehabilitation may address the muscular component. They do not necessarily correct the underlying nerve disorder. Persistent neuralgic pain may benefit from medical management, specialist assessment, or carefully selected procedures. When a patient reports a sudden new severe posterior headache with other neurological signs, urgent vascular or neurological causes must be considered instead of assuming benign neuralgia.
I also discuss sleep positioning and activities that compress sensitive tissues, such as prolonged pressure against a rigid headrest. A supportive pillow can help comfort, but no pillow shape has been established as a universal treatment. The goal is to find a position that allows rest while keeping the neck comfortable. Excessive attention to perfectly straight posture can increase muscle tension and unnecessary fear.
A symptom diary may clarify whether pain is brief and electric, constant and aching, or accompanied by nausea and light sensitivity. This seemingly simple documentation can prevent misclassification. It also helps medical specialists understand whether treatment is changing the condition that matters most to the patient.
Neck Pain, Dizziness, Balance Problems, and Concussion
Patients sometimes say that their neck injury makes them dizzy. A physiological basis for considering a cervical sensorimotor contribution exists because receptors in neck muscles and joints provide information used alongside vision and vestibular signals. When these inputs disagree, a person may experience disorientation or unsteadiness. Yet cervicogenic dizziness remains a diagnosis of exclusion, and clinicians should not attribute symptoms to the neck before investigating important alternatives.
A motor vehicle collision can produce a concussion even without a direct blow to the skull. A patient may report headache, light sensitivity, slowed thinking, nausea, sleep changes, or difficulty concentrating. Other causes include benign positional vertigo, inner-ear injury, medication effects, dehydration, cardiovascular problems, and uncommon but dangerous vascular injuries. Different problems can coexist. Testing cervical range of motion alone cannot confirm or rule out a concussion.
The CDC (2025) notes that concussion symptoms can appear after a delay and that worsening headache, repeated vomiting, weakness, unusual confusion, seizures, or other danger signs warrant emergency evaluation. That advice is particularly important for patients who interpret every post-collision symptom as whiplash. A properly coordinated care plan can include concussion assessment, vestibular rehabilitation, cervical rehabilitation, and medical follow-up, but each component should be chosen based on findings.
For someone with motion sensitivity, early exercises may be deliberately small and carefully paced. The aim is not to force the nervous system to tolerate severe dizziness. It is to identify the source, establish safety, and gradually reintroduce appropriate sensory and movement challenges. Objective balance measures, symptom logs, and reassessment help determine whether the approach is working or whether the diagnosis must be reconsidered.
Neck Pain, Sleep Disturbance, and Daytime Fatigue
Sleep disruption is one of the most important and frequently underestimated effects of persistent neck pain. A patient may fall asleep normally but wake every time they turn their head. Another may struggle to find a comfortable position. Repeated awakenings can reduce restorative sleep and leave the person tired, irritable, or less able to cope with discomfort the next day. Pain and sleep influence each other in both directions, creating a cycle that can persist even as some tissues heal.
The first step is to ask what is actually interrupting sleep. Is it mechanical discomfort, arm tingling, worry, snoring, medication, or another medical condition? Treating cervical movement limitations will not correct untreated sleep apnea, but better neck comfort may reduce one barrier to restful sleep. A multidisciplinary clinic is well placed to distinguish these contributors and recommend the appropriate next evaluation.
During rehabilitation, I generally emphasize practical sleep habits rather than an expensive collection of accessories. A regular schedule, a comfortable pillow height, fewer prolonged static positions before bed, and manageable daytime activity are reasonable starting points. If symptoms are severe enough to prevent normal rest, medication options and medical review may be appropriate. A pillow that supports the head without forcing end-range rotation is usually more helpful than trying to achieve an idealized posture.
We can track sleep alongside pain and function. Nighttime awakenings, time to fall back asleep, and morning stiffness are useful patient-reported measures. If sleep improves while walking tolerance, work participation, and neck movement also improve, the trend provides a more complete description of recovery than a single pain score. It does not, by itself, identify the anatomical source or prove legal causation.
Neck Pain, Stress, Anxiety, and Fear of Movement
An injury can alter how safe the world feels. A driver who experiences a collision may become tense while approaching intersections. An employee injured at work may worry about losing income. Someone with arm tingling may fear permanent nerve damage even when examination findings are reassuring. These emotions do not mean the symptoms are fabricated. They are understandable human responses that can influence muscle guarding, attention, sleep, activity, and participation.
Fear-avoidance behavior occurs when a person reduces activity because movement seems likely to cause harm. Temporary protection may be appropriate after acute trauma, but prolonged avoidance can reduce strength and endurance. Pain catastrophizing is a research term for patterns of thinking that amplify threat and helplessness; it should not be used as a character judgment. A 2025 systematic review found low- to moderate-certainty evidence connecting higher psychological distress and catastrophizing with persistent or recurrent nonspecific neck pain (Yu et al., 2025).
A compassionate rehabilitation plan makes room for these factors without replacing proper medical evaluation with psychological explanations. I explain the working diagnosis, discuss reassuring findings, identify activities that can be practiced safely, and invite questions. A patient who understands why an exercise was chosen is more likely to perform it consistently. When post-traumatic stress, anxiety, depression, or significant fear restricts function, collaboration with appropriately trained mental health professionals may be important.
Progress can include confidence as well as physical performance. Can the patient ride in a car without gripping the seat? Can they turn their head safely? Do they feel able to resume an enjoyable activity? These are meaningful goals. However, neither the presence nor absence of distress determines whether a cervical injury exists, and psychological scores are not substitutes for neurological testing or medical causation analysis.
Neck Pain, Jaw Pain, and Shoulder Dysfunction
The jaw, upper back, shoulders, and neck operate in a connected movement system. A person who clenches the teeth may also hold tension in the neck muscles. Someone with a painful shoulder may elevate the shoulder girdle and change how the cervical muscles work. Conversely, a patient with cervical radiculopathy may experience pain that feels like a shoulder problem. These relationships explain why a regional examination is sometimes more useful than treating only the spot the patient points to.
Temporomandibular disorders can cause jaw pain, clicking, chewing discomfort, and headache. Cervical dysfunction may coexist, but not every jaw problem originates in the spine. A patient with dental pain, jaw locking, or progressive inability to open the mouth needs appropriate dental or medical assessment. Likewise, a rotator cuff tear, shoulder arthritis, or adhesive capsulitis requires shoulder-focused examination and may need distinct treatment.
I often ask patients to perform simple functional tasks: raise an arm, reach behind the back, turn the head while seated, and describe which movement reproduces the familiar complaint. We evaluate whether the pain changes with neck position, shoulder loading, or both. This makes treatment more precise. For someone whose shoulder weakness stems from a cervical nerve-root problem, repeated shoulder massage alone may miss the main issue. For someone with isolated shoulder disease, an intensive cervical treatment program may be unnecessary.
Integrated rehabilitation addresses the relevant components together. Exercises might restore scapular control, thoracic mobility, cervical endurance, and upper-limb strength. The exact combination depends on examination findings. A shoulder and neck program should not be described as a universal solution, but as a measured response to a patient-specific movement pattern.
Neck Pain, Migraine, Tension-Type Headache, and Other Comorbidities
Comorbidity means another condition exists alongside the main complaint. It does not necessarily mean one caused the other. In people with neck pain, relevant comorbidities may include migraine, tension-type headache, sleep disorder, anxiety, depression, osteoarthritis, chronic widespread pain, diabetes, vestibular conditions, or previous concussion. Some share risk factors or influence recovery. Others are unrelated conditions that happen to occur in the same person.
This distinction is crucial. A patient with migraine may also have tender cervical muscles, especially during attacks. Treating muscular discomfort can be useful, but it does not prove that a cervical joint caused the migraine. A person with diabetes may have hand numbness from peripheral neuropathy rather than a new cervical lesion. An older patient with osteoarthritis may develop new pain after a collision even though degenerative imaging findings were present beforehand. The clinical task is to identify the active contributors and avoid turning temporal association into unsupported cause-and-effect claims.
When I review comorbidities, I look for conditions that affect safety, prognosis, and treatment selection. Bone fragility may change which manual techniques are safe. Anticoagulant use changes the evaluation of trauma and bleeding risks. Diabetes can affect neuropathy assessment and recovery. Sleep problems may lower pain tolerance and exercise adherence. Depression or anxiety may influence participation, but neither discredits the patient’s report of symptoms.
Our medical director and clinical team can help coordinate these issues, with external specialist referral when appropriate. The benefit of comprehensive assessment is not that more laboratory testing is always better. It is that testing and treatment match plausible medical questions. A careful plan avoids both undertreating important illness and adding low-value interventions that do not address a defined problem.
How Neck Pain Changes Driving, Work, Family Life, and Independence
The cervical spine participates in movements people perform without consciously thinking about them. We turn to check a blind spot, look down to read a recipe, lift our eyes toward a shelf, carry groceries, cradle a child, and adjust our posture to speak with someone. Functional disability occurs when pain, stiffness, weakness, fatigue, or fear makes these activities difficult. Two people with similar MRI findings may have very different levels of disability, which is why a treatment plan must be grounded in what the patient needs to do.
Consider driving. A patient recovering from a cervical sprain may have enough comfort to sit in a car but insufficient rotation to see through the side window. The person may compensate by turning the entire torso or avoiding certain routes. This is not merely an inconvenience. Safe driving requires attention, vision, and appropriate movement. We assess whether the patient can perform driving-related tasks before recommending a return to unrestricted driving. If medication causes sedation or neurological symptoms affect coordination, the question extends beyond cervical range of motion.
Work demands are similarly varied. A computer programmer may need sustained attention and frequent position changes. A warehouse employee may lift, reach overhead, and repeatedly look upward. A nurse may reposition patients. A mechanic may work underneath equipment with the neck extended. A professional driver may require prolonged sitting and frequent head turns. Writing “return to work as tolerated” without considering these demands can lead to an unsafe or unrealistic plan.
Family life matters as much. People describe missing a child’s sporting event, being unable to prepare meals, avoiding intimacy because of discomfort, or losing confidence in household tasks. These are valid elements of health-related quality of life. I ask patients to identify specific tasks and rate their ability to complete them. The resulting goals are more meaningful than generic instructions to “improve posture.” In a personal injury setting, they also provide a transparent record of how the condition affected participation, without requiring exaggerated claims.
Occupational Neck Pain in Office Workers and Technology Professionals
Extended computer work does not automatically cause neck injury. The body can tolerate many postures, and no single sitting position is proven to prevent all neck pain. Problems are more likely when prolonged exposure, limited movement variation, workload, stress, insufficient recovery, and reduced conditioning combine in someone sensitive to these factors. A laptop placed low on a desk can encourage sustained downward gaze. Still, the practical solution is often to adjust the workstation and vary activity rather than demand perfect alignment all day.
My occupational assessment includes screen height, chair and desk fit, keyboard and mouse placement, breaks, phone habits, and the physical demands outside work. If a patient spends ten hours typing but also lifts heavy weights after work, both exposures may matter. We distinguish a task that triggers symptoms from a claim that the task is the sole cause of a structural lesion. A symptom diary may show that changing the screen arrangement helps, but that improvement alone does not identify the injured anatomical tissue.
A reasonable program uses short movement breaks, comfortable rotation and extension, scapular endurance, and progressive strengthening. The goal is load tolerance: helping tissues and the nervous system tolerate ordinary tasks with less discomfort. A worker may benefit from a sit-stand arrangement, yet prolonged standing in a fixed posture can also become uncomfortable. Variety usually matters more than adherence to a rigid posture rule.
Where a worker reports new arm numbness, severe headache, or weakness, an ergonomic explanation is not enough. We conduct the appropriate neurological and medical assessment. In occupational medicine, it is important to separate symptoms associated with prolonged work demands from a specific traumatic injury, and to document whether the job aggravates an existing condition. Clear terminology protects both the worker and the clinical record’s accuracy.
Sports-Related Neck Pain and Safe Return to Performance
Athletes expose the cervical spine to forces that vary by sport. Football, wrestling, gymnastics, cycling, volleyball, and weightlifting place different demands on head control, shoulder girdle strength, balance, and rapid movement. A strain during training differs from neck pain after a direct axial load or collision. The mechanism, neurological examination, and trauma history determine whether the athlete needs emergency assessment, imaging, or a simple training modification.
The decision to return to performance should not depend solely on feeling better at rest. An athlete may need sufficient cervical range of motion, muscular endurance, reaction capacity, sport-specific strength, and confidence to tolerate contact or rapid movement. A person returning to overhead lifting must coordinate the upper back, shoulders, and neck under increasing load. A wrestler may need to resist rotational forces, while a cyclist needs to maintain visual orientation in an extended riding position. These tasks require different testing.
Progressive rehabilitation might move from comfortable active range of motion to deep neck muscle training, then scapular and trunk strengthening, and finally sport-specific drills. Training loads increase according to symptom response, neurological safety, movement quality, and performance goals. If an athlete has a suspected concussion, cervical instability, progressive neurological symptoms, or a significant structural injury, return-to-play decisions require more specialized clearance. No hands-on adjustment substitutes for that process.
This principle applies beyond sports. A person can reach maximum medical improvement in the sense of relative medical stabilization and still need conditioning before returning to full athletic performance. Conversely, an athlete may regain high performance but retain a diagnosed condition that merits follow-up. Medical status, disability, and performance are related measures, not interchangeable labels.
Neck Pain in Older Adults and People With Preexisting Degeneration
Aging can change discs, facets, bone density, and muscle function. Many older adults remain active and independent despite these changes. Cervical spondylosis refers broadly to degenerative changes of the cervical spine, and these findings are not automatically painful. An older patient with a degenerative MRI finding may have had no meaningful neck symptoms before a fall or collision. The event may cause a new soft-tissue injury or aggravate an existing symptomatic condition. A thoughtful assessment must distinguish those possibilities.
Safety becomes particularly important when bone health is compromised. Osteoporosis, inflammatory arthritis, prolonged corticosteroid use, malignancy, or a history of fracture can alter the risk associated with manual interventions. A patient with known rheumatoid arthritis may require assessment for cervical instability. A person taking anticoagulants after a fall may need urgent medical evaluation, even with minimal external bruising. These factors influence imaging decisions and the appropriateness of cervical manipulation.
Older adults may also face obstacles that complicate recovery: reduced strength, poor balance, multiple medications, sleep disturbance, and limited access to transportation. A successful rehabilitation plan may focus on getting in and out of a car, performing household tasks, walking safely, and turning the head without losing balance. These goals may be more important to the patient than regaining every degree of motion measured in a clinic.
In a personal injury case, preexisting degeneration should neither be ignored nor used as an automatic reason to dismiss a new complaint. The evidence should address prior symptoms, treatment history, functional baseline, mechanism, clinical course, and any interval changes. A defensible opinion can recognize both chronic anatomy and new functional deterioration without claiming that an accident created every preexisting MRI abnormality.
Pregnancy, Chronic Illness, and Other Factors That Change the Neck Pain Plan
Some patients need modifications because of pregnancy, connective-tissue disorders, inflammatory disease, hypermobility, active infection, malignancy, or significant cardiovascular conditions. A safe approach begins with history and examination, not a fixed chiropractic protocol. Pregnancy may change sleep positions and exercise tolerance; it does not mean every neck intervention is unsafe. Still, when risk factors exist, coordinate treatment selection with the appropriate obstetric clinician.
Hypermobility deserves attention because a person can have a large range of motion and still feel unstable or fatigued. Aggressive stretching may not address the problem. These patients may benefit from carefully dosed muscular endurance and movement-control work. If a hereditary connective-tissue condition or vascular disorder is suspected, the evaluation becomes more complex. The clinician should avoid equating flexibility with a need for further manipulation.
Patients with autoimmune disease, diabetes, thyroid dysfunction, or systemic inflammatory illness may have symptoms that overlap with mechanical neck pain. A fever, unexplained weight loss, pronounced morning stiffness, unusual fatigue, or joint swelling can change the differential diagnosis. Functional medicine discussions may help organize relevant medical history, nutrition, sleep, and lifestyle factors. Still, disease-specific testing must follow accepted clinical indications rather than broad assumptions that all neck pain represents systemic inflammation.
Dr. Cardenas’s internal medicine role is particularly useful when medical comorbidities influence treatment safety or prognosis. Medication reconciliation, targeted laboratory assessment, chronic disease management, and referral decisions are examples of complementary functions. The chiropractic team focuses on mechanical, neurological, and rehabilitative findings, while the medical team evaluates broader health risks. Working together should reduce fragmented decision-making, not blur professional responsibilities.
Neck Pain Red Flags: When Immediate Medical Evaluation Comes First
A life-threatening disorder does not cause most neck pain. However, a small number of conditions require urgent assessment, and missing them can be dangerous. Red flags are features that raise concern for fracture, spinal cord injury, infection, cancer, arterial dissection, or another serious illness. A red flag is not automatically a diagnosis. It is a reason to ask more focused questions, examine carefully, and sometimes arrange urgent imaging or referral (Blanpied et al., 2017; Rushton et al., 2023).
Seek emergency medical care for neck pain accompanied by concerning features such as:
New or progressive arm or leg weakness, marked walking difficulty, or loss of hand coordination.
Sudden severe or unusual headache or neck pain, especially with double vision, speech difficulty, facial droop, imbalance, or other neurological signs.
Significant trauma with suspected fracture or instability.
Fever, severe neck stiffness, or systemic illness suggesting possible infection.
Loss of consciousness, repeated vomiting, increasing confusion, seizure, or another serious head injury sign.
New bowel or bladder disturbance associated with possible spinal cord dysfunction.
Patients sometimes confuse a normal temporary increase in exercise soreness with a red flag. We explain the difference clearly. Mild soreness after unfamiliar muscle work may improve within a manageable time. Progressive weakness, severe neurological symptoms, and systemic signs require evaluation rather than waiting for the next appointment. A good conservative-care practice must be willing to stop treatment and refer when the evidence points outside its safe scope.
This is also why chiropractic adjustments are not automatic on the first visit, especially after trauma. Safety screening comes before technique selection. If fracture, vascular disease, instability, infection, or significant cord compression is suspected, hands-on cervical treatment may be inappropriate until further assessment is complete. Patient safety remains the highest priority even when a person wants immediate relief.
Cervical Artery Disorders and Informed Consent Before Manual Treatment
The vertebral and carotid arteries supply blood to important regions of the brain. Cervical artery dissection is uncommon, but it can present with head or neck pain before obvious stroke-like symptoms appear. Because a person with an evolving vascular problem may initially seek care for pain that resembles a musculoskeletal complaint, clinicians must consider this possibility in the history and examination. The International IFOMPT Cervical Framework emphasizes clinical reasoning, recognition of concerning symptoms, and appropriately adapted examination before planned cervical interventions (Rushton et al., 2023).
Severe new unilateral neck pain or headache, unusual dizziness, visual disturbance, difficulty speaking, facial sensory changes, and other neurological symptoms should not be casually labeled muscle spasm. The clinical picture may require urgent medical referral. A negative single office test does not reliably guarantee the absence of vascular disease. Historical positional screening methods cannot replace comprehensive clinical judgment.
Patients also deserve a clear discussion of manual-therapy risks, benefits, and alternatives. Some techniques may cause temporary soreness. Serious adverse events are rare but potentially severe, and the relationship between cervical manipulation and arterial events is difficult to study because an evolving dissection can cause pain before a person seeks care. The appropriate clinical response is neither to dismiss all concerns nor to claim that any neck movement is inevitably dangerous. We use individualized screening and informed consent, and we select lower-force or non-thrust approaches when appropriate.
For certain patients, active exercise, gentle mobilization, soft-tissue work away from the cervical arteries, or specialist-guided management may be preferable to high-velocity cervical manipulation. When risk cannot be assessed adequately, do not proceed with treatment. Choosing not to manipulate is sometimes the most clinically sound decision a chiropractor can make.
How a Comprehensive Neck Pain Evaluation Begins
The examination starts with a history that is specific enough to explain the patient’s story. I ask when symptoms began, how they changed, what the patient could do before the problem, and which activities now provoke or relieve it. After trauma, I document the event in concrete terms: direction of impact when known, seating position, restraint use, head position, immediate symptoms, emergency care, subsequent changes, and other possible injuries. When details are uncertain, the record should say so rather than filling gaps with confident-sounding guesses.
Next comes a focused medical review. Current medications, prior surgeries, headache history, neurological disorders, systemic illness, and previous neck treatment may change the differential diagnosis. Some patients have a history of intermittent neck soreness but no prior arm symptoms or work restrictions. Others had significant limitations before the event. Both situations deserve faithful documentation. A medical record should distinguish reported history from independently reviewed records.
The physical examination can include posture and movement observation, cervical and shoulder range of motion, palpation, neurological tests, selected orthopedic maneuvers, upper-limb function, balance assessment, and a functional task relevant to the patient’s complaint. The precise components depend on the presentation. For instance, a patient with arm numbness needs a more detailed neurological evaluation than someone with uncomplicated localized stiffness after a day of gardening.
I explain what each finding does and does not prove. Tenderness demonstrates sensitivity at the examined location; it does not identify the microscopic state of every ligament. Reduced range of motion may reflect pain, fear, guarding, or a mechanical restriction. A positive provocative test can support a hypothesis but rarely stands alone. Converging evidence from history, examination, investigations, and clinical course is more persuasive than any isolated finding.
Objective Testing: Range of Motion, Strength, Reflexes, and Function
A common misconception is that all objective information must come from an MRI. In reality, well-conducted clinical measurements can be highly useful. Cervical range-of-motion testing describes whether and how far the patient can turn, bend, or extend. Repeated testing under similar conditions can show progress. Strength testing may reveal a focal deficit, while reflex and sensory testing provide information about nervous system function. Functional tests describe what these findings mean in real life.
Measurements require attention to reliability. If one visit records head rotation while the trunk is free to move, and the next holds the shoulders still, a numerical difference may reflect the method rather than a true change in cervical motion. Likewise, strength scored informally is less precise than standardized testing. I try to use consistent positions, instructions, and documentation. When measurement uncertainty exists, we should acknowledge it rather than present false precision.
Validated questionnaires add another dimension. The Neck Disability Index asks about activities such as personal care, lifting, reading, work, driving, sleeping, and recreation. A pain scale captures intensity but not necessarily participation. A Patient-Specific Functional Scale can focus on tasks the individual chooses. These tools are valuable because they can be repeated to monitor change in a standardized way (Blanpied et al., 2017).
If function improves, it supports a conclusion that the patient is making progress under the overall plan. It does not establish which treatment component produced the improvement, whether natural healing contributed, or whether an accident caused every diagnosis. Clinical testing serves patient care first. Its medicolegal value comes from transparency, consistency, and relevance to the question being asked.
Imaging Decisions: When X-Ray, CT, and MRI Help
Imaging should answer a defined clinical question. X-rays can show alignment and certain bony changes but do not directly display the spinal cord or most soft tissues in detail. CT is often especially useful for evaluating suspected acute bony injury after trauma. MRI provides better information about discs, the spinal cord, nerve-root surroundings, and many soft-tissue structures. None of these modalities is necessary for every patient with neck pain.
The ACR Appropriateness Criteria distinguish acute traumatic cervical injury from nontraumatic pain and from suspected radiculopathy. Clinical rules such as the Canadian C-spine Rule and NEXUS criteria help clinicians determine when imaging may be needed after certain blunt-trauma presentations. For uncomplicated nontraumatic neck pain without red flags, advanced imaging is often not the first step. For chronic radiculopathy, MRI may be appropriate, particularly when symptoms persist or the result would influence treatment or referral (ACR, 2024a, 2024b).
Imaging is especially important when the clinical findings suggest a lesion that could threaten neurological function. At the same time, incidental degenerative findings are common enough that a scan can mislead if read without context. A radiology report may accurately describe a disc bulge while the clinician concludes that the patient’s main problem is a different disorder. These judgments require evidence, not simply a preference for or against imaging.
In my published clinical case discussion, “Evaluating Cervical Spine Injury with Advanced Imaging,” I describe a post-collision patient who presented for a second-opinion evaluation after cervical and arm complaints. The case illustrates why documenting symptom patterns, neurological findings, previous care, and the reason for further investigation matters. A published case report can demonstrate a diagnostic thought process, but it does not prove that the same imaging or treatment decision is right for every patient (Jimenez, 2017).
What Chiropractic Care Is and Where It Fits in Modern Neck Pain Treatment
Chiropractic care is a regulated health profession focused on assessing, diagnosing, and conservatively managing musculoskeletal conditions, particularly those involving the spine and related neuromuscular function. Chiropractic clinicians may use manual therapy, joint mobilization, spinal manipulation, therapeutic exercise, patient education, and other approaches within the scope of their licensing and training. A chiropractic visit should involve clinical reasoning, safety screening, shared decision-making, and appropriate referral. It is not simply an appointment to crack the neck.
A spinal adjustment is one possible intervention, not a required treatment for every patient. In high-velocity, low-amplitude manipulation, a trained clinician delivers a brief, controlled movement to a selected joint. Other approaches use slower mobilization, low-force instruments, positional techniques, or no manual intervention. The audible sound sometimes associated with a thrust is generally related to joint cavitation. This does not mean a vertebra was dangerously displaced or that its position was permanently corrected.
The most defensible purpose of manual therapy is to help improve symptoms and movement in an appropriately selected patient. It may alter local mechanical sensitivity, change sensory input, reduce muscle guarding, or make exercise easier. Researchers continue to study the mechanisms. A meaningful clinical response can occur without proving that a specific bone was “put back in place.” The explanation we give a patient should match the available scientific evidence, not rely on dramatic anatomical claims.
I view chiropractic care as one part of active recovery. If an intervention briefly eases neck rotation, I use that opportunity to help the patient practice movement and strengthen the muscles needed to maintain function. If an intervention does not lead to meaningful improvement, we reassess. If the findings indicate significant neurological disease, infection, fracture, or vascular pathology, the correct action may be referral rather than another adjustment. This is how chiropractic practice can fit responsibly within an integrative medical model.
What the Latest Evidence Says About Manual Therapy and Exercise
The clinical literature is encouraging in some areas and uncertain in others. In a 2025 Cochrane systematic review, Chacko and colleagues examined manual therapy combined with exercise for adults with neck pain. Compared with no treatment, the combination may meaningfully improve pain and function. Compared with placebo, the review found a more limited effect: a moderate functional improvement was possible, but pain reduction was not clearly demonstrated for the primarily chronic cases studied. The review also identified limitations in study quality, reporting, and the evidence base for acute neck pain (Chacko et al., 2025).
This matters because an honest article should not claim that chiropractic treatment cures all forms of neck pain. Evidence-based care means interpreting who was studied, what the comparison treatment was, how long the benefits lasted, and how certain the results were. A treatment may be reasonable even when evidence is not perfect, but uncertainty should be disclosed. Shared decision-making involves discussing expected benefits, alternatives, risks, cost, and the patient’s preferences.
The 2017 neck pain clinical practice guideline from Blanpied and colleagues organizes treatment according to patterns such as mobility deficits, movement-coordination impairments, referred pain, and radiating pain. That framework supports selecting interventions according to findings rather than giving all patients the same set of techniques. It also emphasizes outcomes, patient participation, and the need to recognize serious pathology. These principles remain clinically relevant alongside the newer research.
I explain the difference between short-term symptom modulation and lasting recovery. A person may feel better immediately after massage or mobilization, but if the neck is deconditioned and the work environment remains demanding, symptoms can return. Exercise alone may be challenging when pain is highly irritable. A thoughtful combination can use a brief symptom-relief intervention to support gradual strengthening. The program’s value is judged by sustained function, not by how dramatic the treatment feels during the appointment.
Cervical Joint Mobilization and Low-Force Treatment Options
Joint mobilization uses controlled, usually slower movements within a comfortable range to address stiffness or movement-related pain. It may be selected when a patient is sensitive to sudden movements, prefers a gentler approach, or has clinical factors that make thrust techniques less attractive. Mobilization can target the cervical or thoracic region, depending on the examination. The clinician should explain why they are treating a particular area and what outcome is expected.
For example, a patient with limited cervical rotation but no neurological red flags may have muscular guarding and stiff movement patterns. Gentle mobilization, paired with active neck turns, may help the person explore a comfortable range. If the patient becomes markedly dizzy, develops unusual symptoms, or reports worsening neurological complaints, stop the technique and reconsider the diagnosis. Ignoring the patient’s reaction does not make treatment safer.
Low-force interventions can also help individuals who do not want manipulation. Some benefit from exercise instruction, soft-tissue care, or thoracic movement training without direct cervical thrust procedures. Choosing a different technique is not a failure of chiropractic care. It shows the clinician is tailoring treatment to the individual.
A good plan should specify the clinical reason for the intervention, the expected short-term change, and the method used to test that change. If the goal is improved rotation, measure it consistently before and after and track how it behaves over subsequent visits. If the goal is better tolerance for computer work, ask about work duration and symptom recovery rather than relying only on a treatment-table impression.
Soft-Tissue Therapy and Why Muscles Sometimes Remain Guarded
Soft-tissue therapies include several methods intended to address muscle discomfort and movement restriction. These may involve gentle massage, manual pressure, movement-assisted techniques, or other clinically appropriate interventions. Their effects may arise from sensory modulation, relaxation, altered muscle activation, or changes in the person’s willingness to move. Claims that routine massage permanently breaks up every adhesion or mechanically realigns every fiber usually exceed what clinicians can demonstrate.
Following a cervical strain, muscles may guard to protect a sensitive area. Repeated guarding can create soreness and fatigue. A brief course of soft-tissue treatment may reduce tenderness enough to permit comfortable exercise. However, working aggressively on highly irritable tissue can worsen symptoms. The appropriate dose depends on stage of healing, sensory sensitivity, medical history, and patient preference.
I use hands-on treatment as part of a sequence. We first identify the movement or activity the patient wants to regain. We select a technique that may make that task easier. We then repeat the task or practice a related exercise and check whether the change helps. This approach allows the intervention to support functional recovery instead of becoming an isolated ritual.
For a patient whose upper trapezius feels constantly tight, the longer-term solution may include shoulder strength, breaks from sustained work, improved sleep, and an appropriate activity plan. Massage can be useful, but it should not be described as the sole correction for a problem involving workload, nervous system sensitivity, and deconditioning. When tenderness is unexplained or accompanied by systemic warning signs, further medical evaluation takes priority.
Deep Neck Flexor Training and Cervical Movement Control
The small muscles that help control the head and neck can become less efficient when a patient experiences persistent pain. Deep cervical flexor training aims to improve low-load control and endurance, often using gentle nodding motions rather than large forceful movements. The goal is not to strengthen one magical muscle that solves all cervical pain. It is to restore coordinated participation of different muscles during ordinary tasks.
A patient may initially practice a small chin-nod movement while lying comfortably, keeping the jaw relaxed and avoiding excessive recruitment of large superficial muscles. Explain and supervise the exercise when first prescribed. If the movement triggers headache, severe discomfort, or neurological symptoms, it needs modification or reassessment. A person with high irritability may start with very brief holds, while a well-conditioned athlete may progress to more demanding endurance tasks later.
As tolerance improves, the program may incorporate rotation, resisted movements, and whole-body activities. Neck muscles work with the shoulder girdle and trunk during daily life. Training only in a lying position cannot fully prepare someone to lift boxes, drive, or play sports. Eventually, strengthening must resemble the activities the patient intends to resume.
Progress is monitored through movement quality, symptom behavior, endurance, and function. A patient who can hold a gentle nod longer but still cannot turn while driving may need a different emphasis. Rehabilitation is not a contest to perform the hardest exercise. It is the process of finding the right challenge, then increasing it as the person adapts safely.
Scapular and Thoracic Rehabilitation for Neck Pain
The neck does not move independently of the upper back and shoulders. The thoracic spine provides a base for cervical movement, while the scapular muscles help position the shoulder girdle during reaching, lifting, and desk work. When a patient holds the shoulders elevated or has reduced thoracic mobility, the cervical muscles may work harder than necessary for certain tasks. This connection supports examining the entire upper-quarter movement system.
A program might include comfortable thoracic extension, controlled shoulder-blade movement, rows, modified wall slides, or resistance training. I don’t prescribe these exercises because every person’s scapulae are “misaligned.” I choose them when testing shows a deficit in strength, endurance, control, or load tolerance. Too much corrective emphasis can make patients self-conscious about every posture. I prefer to teach useful movement options rather than demand an unnatural position throughout the day.
The training dose must fit the patient’s capacity. Someone recovering from acute whiplash may need a light band and a few comfortable repetitions. A construction worker preparing to return to repetitive lifting needs a more demanding progression. The program should account for shoulder pain, dizziness, cardiovascular fitness, and the person’s ability to practice consistently at home.
This is particularly important when a patient improves during clinic visits but struggles at work. The gap may reflect insufficient strength or endurance for the actual task. We then adjust the rehabilitation plan, perhaps adding graded carrying, reaching, or overhead activity. Real-world function is the outcome that ultimately matters.
Chiropractic Care for Neck Pain Relief | El Paso, TX (2025 Recovery Guide) Chiropractic Treatment- Video
Gradual Return to Activity Instead of Prolonged Rest
After a serious injury, temporary protection may be necessary. For many uncomplicated mechanical neck pain and whiplash presentations, however, prolonged inactivity is not a desirable long-term strategy. Muscles lose conditioning, movement confidence may fall, and ordinary tasks can begin to feel more threatening. The challenge is to distinguish safe movement from activity that could aggravate an unstable fracture, serious neurological disorder, or another condition requiring restrictions.
I describe rehabilitation as graded exposure. We start with an activity the person can perform safely and predictably, then increase its duration, range, resistance, or complexity. A patient who can turn the head only a little may practice comfortable motion several times during the day. A patient who can work at a computer for twenty minutes may build tolerance with breaks and progressively longer periods. The plan should not force the person through severe symptoms to prove toughness.
A temporary increase in symptoms can occur during exercise, especially after a period of reduced activity. The clinician and patient agree on reasonable limits and reassessment criteria. If soreness worsens progressively, lasts unusually long, or is accompanied by neurological changes, the program is modified. Pushing through new weakness or severe radiating pain is not an evidence-based requirement for recovery.
The same approach applies to returning to recreation. Walking may be an early step; strength training and sport-specific tasks may follow. Progress is individualized rather than dictated by an arbitrary number of visits. This respects the fact that tissue healing, pain sensitivity, conditioning, and social demands do not always change at the same pace.
Cervical Traction and Decompression: Selecting Patients Carefully
Cervical traction uses a controlled pulling force intended to temporarily reduce compressive loading or alter symptoms in some patients with cervical conditions. Consider it for selected cases of radicular pain when assessment suggests possible benefit and contraindications have been excluded. The treatment’s effectiveness depends on the diagnosis, dosage, technique, and the patient’s response. It should not be advertised as permanently restoring the original height or structure of every damaged disc.
The clinician must assess whether traction is appropriate. Instability, certain fractures, severe osteoporosis, significant spinal cord compromise, and some other conditions may make it unsuitable. A patient with increasing neurological deficits requires more than routine decompression sessions. During treatment, the clinician monitors symptom behavior. Improvement in arm symptoms might support continuing a cautious trial; worsening weakness or spreading numbness calls for reassessment.
If traction provides temporary relief, it may support active rehabilitation rather than replace it. The patient still needs strategies to manage daily loading and regain cervical and shoulder function. Insurance documentation and medical-necessity decisions should reflect the specific indication, expected measurable benefit, and response. Simply owning a decompression device is not proof that treatment is needed.
For radiculopathy, the evidence remains mixed, and the stronger clinical message is to use a thoughtful multimodal plan rather than promise that traction is a cure. Patients should understand the uncertainty and alternatives, including exercise, medical evaluation, medication when indicated, and specialist consultation for persistent or progressive problems.
Acupuncture, Heat, Cold, and Other Adjunctive Neck Pain Treatments
Many people ask whether acupuncture, heat, cold, electrotherapy, laser, or shockwave can make the neck heal faster. These modalities differ in mechanism, evidence quality, intended use, cost, and risk. They should not be grouped as proven tissue-regeneration treatments. For uncomplicated neck pain, some may provide temporary symptom relief. That can be clinically valuable if it helps a patient sleep or engage in exercise, but the rationale must remain realistic.
Heat may feel soothing for muscular guarding and stiffness. Cold can help with short-term comfort after an acute strain when the person prefers it. Neither is a substitute for evaluation after significant trauma. Acupuncture may be considered as a symptom-management option for certain patients, with attention to provider training, bleeding risk, and patient preferences. Electrical stimulation or photobiomodulation may be proposed in selected settings, but the evidence for specific cervical diagnoses and protocols varies.
A common problem arises when several passive modalities are scheduled indefinitely without clear measures of benefit. The patient may report that the session feels relaxing but still misses work and avoids everyday activity. This should trigger a reconsideration of priorities. A useful adjunct demonstrably supports a defined goal and does not displace more important care.
In the clinic, I prefer to explain each tool in plain language. We identify the proposed mechanism, the evidence supporting that use, the risks, the expected duration of benefit, and the endpoint for continuing or stopping it. More treatments do not automatically mean better treatment. A coordinated plan is valuable because it reduces unnecessary or overlapping procedures.
Medication, Injections, and Specialty Care as Parts of a Nonsurgical Strategy
An integrative clinic should not treat medication as a failure. Some patients need short-term analgesics or other medical treatment so they can sleep, move, and participate in rehabilitation. Appropriate medication choices depend on age, kidney function, gastrointestinal risk, cardiovascular disease, medication interactions, pregnancy, and other clinical factors. Opioids are generally not first-line long-term treatment for uncomplicated mechanical neck pain because their risks can outweigh sustained benefits.
For selected patients with persistent radicular pain or specific pain generators, a specialist may consider an injection-based procedure. Such decisions require diagnostic clarity, discussion of the quality of evidence, and informed consent. A cervical epidural steroid injection, for example, has specific risks and indications. It is not equivalent to a routine chiropractic procedure and should be performed only by appropriately qualified clinicians in an appropriate setting. Temporary pain relief does not necessarily mean the underlying anatomy has returned to normal.
Surgical consultation is appropriate when serious neurological compromise is suspected or when selected structural conditions fail a reasonable course of nonsurgical management. The purpose of the consultation is not automatically to schedule surgery; it is to compare options based on neurological status, imaging, functional impact, prognosis, and patient preference. Recent evidence reviews show that neither surgery nor nonsurgical care is superior for every person (Dar et al., 2026; Kale et al., 2026).
Dr. Cardenas’s medical oversight and my nurse practitioner role are relevant because medical comorbidities, medication safety, and referrals may need coordination alongside rehabilitation. The patient benefits when the team knows who is responsible for each decision and communicates changes promptly. Integrated care should increase accountability, not obscure it.
Functional Medicine, Nutrition, and Recovery Without Overpromising
Functional medicine in an injury-care context can be understood as a structured interest in lifestyle, nutrition, sleep, physical activity, medical history, and factors that may affect resilience or recovery. The most useful questions are concrete. Is the patient eating adequately while recovering? Is a sleep disorder reducing daytime capacity? Does diabetes affect neurological symptoms? Is a medication contributing to dizziness? Does the person need help building a sustainable exercise routine?
A balanced dietary pattern, adequate protein, appropriate energy intake, hydration, and correction of documented nutritional deficiencies support general health. However, no single supplement has been established as a reliable cure for whiplash, a cervical disc herniation, or personal-injury-related neck pain. Routine extensive laboratory panels without a clinical indication can create misleading findings and unnecessary expense. I distinguish evidence for general health from evidence that a specific nutritional intervention repairs a particular cervical tissue.
Sleep, tobacco exposure, physical activity, and stress management are reasonable topics because they affect overall health and may influence treatment participation. For someone whose recovery has slowed due to poor conditioning, gradual resistance training may matter more than adding another passive procedure. For someone with a medical illness, coordination with the treating physician may be the highest priority.
The interdisciplinary purpose is to identify modifiable contributors while avoiding the claim that every chronic symptom has one hidden metabolic cause. We can be curious without being speculative. Patients deserve a clear explanation of which recommendations are well supported, which are optional adjuncts, and which remain uncertain.
Coordinated El Paso Care With Dr. Alexander Jimenez and Dr. Maria Guadalupe Cardenas
At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, the care model combines chiropractic, advanced practice nursing, medical direction, and rehabilitation. I serve as Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, bringing chiropractic assessment and family nurse practitioner training into the management of musculoskeletal and related medical presentations. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of experience, serves as the practice’s Medical Director and Collaborative Physician. Her verified National Provider Identifier is 1164426748, and her Texas medical license number is J2933.
Dr. Cardenas’s medical role may include evaluating systemic illness, reviewing medications, providing medical direction, assessing risk, coordinating diagnostics, and making appropriate referrals. My work emphasizes cervical biomechanical evaluation, relevant neurological and medical assessment within my licensed responsibilities, nonoperative treatment planning, and functional rehabilitation. In a complicated case, the team can connect the physical findings with chronic disease management, imaging needs, and rehabilitation milestones. This is a recognizable multidisciplinary model in integrative and injury care; it does not imply that every service is appropriate for every patient.
For example, imagine an older patient who has neck pain after a collision, takes anticoagulant medication, reports intermittent hand numbness, and wants to return to caring for a spouse. A careful plan must do more than address muscle tenderness. We need to review trauma-related risks, investigate neurological symptoms, coordinate medication considerations, and choose safe exercise and manual options. If imaging or specialist consultation is needed, it should occur before treatment that might be unsafe.
The benefit of coordination is a shared, updated clinical picture. Each team member contributes expertise without automatically declaring that every complaint has the same cause. The patient’s goals remain central: reducing pain where possible, improving safe movement, preventing avoidable harm, and restoring participation in daily life.
Clinical Observations Published by Dr. Jimenez and How to Interpret Them
In my publicly available El Paso Back Clinic writing, I have emphasized three recurring observations: understanding the mechanism of injury, documenting the patient’s baseline, and revising treatment based on measured function rather than a rigid schedule. The clinic’s published materials describe a young manual laborer whose recovery from one collision was complicated by a later collision. The purpose of discussing that example is not to generalize one patient’s outcome to everyone. It shows why a second event requires a fresh examination instead of simply extending the first plan (Jimenez, n.d.).
The same clinical writings discuss delayed recognition of symptoms after some crashes. A patient who had the head turned toward a window may describe a different sequence of stiffness and headache from someone looking straight ahead. Such observations can guide the questions I ask. They do not establish a universal rule that delayed pain is always traumatic or that all low-speed collisions cause cervical damage. Clinical experience generates hypotheses, but causation must still be supported by the relevant record and scientific reasoning.
I also describe cervical injury cases in which a focused examination and advanced imaging became important after persistent symptoms. These reports highlight the value of asking whether the original working diagnosis still fits. If a patient develops new radicular findings, continued treatment for uncomplicated strain without reassessment may be inadequate. Conversely, if repeat examinations show improvement and no concerning features, escalating to imaging or procedures may add little value.
A single clinic observation cannot prove efficacy in the way a well-designed randomized trial can. Natural recovery, patient selection, co-interventions, expectations, and other influences can change outcomes. I therefore present published clinical observations as practice-based perspectives, not controlled research. Their strongest contribution is explaining how a treating clinician organizes questions, documents change, and knows when a plan must be adjusted.
Neck Pain After Personal Injury: Why Medical Causation Must Be Explained
Medical causation asks whether a particular event caused or materially contributed to a particular medical condition. It is distinct from a medical diagnosis. A clinician may accurately diagnose cervical radiculopathy and still be unable to determine from the available information whether a recent motor vehicle collision caused it, aggravated an earlier disorder, or happened near the time when symptoms emerged for another reason. The difference is not technical wordplay. It protects the reliability of clinical opinions and makes medical records more useful to patients, insurers, attorneys, and courts.
In a Texas personal injury lawsuit, a plaintiff generally must establish that the defendant’s legally relevant conduct caused the event and that the event caused compensable injury. JLG Trucking, LLC v. Garza (2015) emphasizes the importance of evaluating other potentially causal events, including a later collision. In Guevara v. Ferrer (2007), the Texas Supreme Court explained that expert medical causation evidence is generally required for conditions outside the common knowledge and experience of ordinary jurors. The court also recognized a narrower category of obvious injuries and logically traceable events for which lay evidence can sometimes support causation.
Therefore, it would be inaccurate to say that every minor neck strain requires the same type of expert testimony, or that chronology alone proves all cervical diagnoses. A simple visible injury and a complex assertion that an accident caused disc pathology, neurological deficits, and years of treatment raise different evidentiary demands. Legal causation, medical causation, and medical necessity must each be addressed appropriately in the specific case, with qualified legal advice on the applicable rules.
A well-supported medical opinion should clearly state its assumptions. It identifies the diagnosed condition, reviews relevant history, explains why the event could cause or aggravate it, discusses whether the timing and findings fit, and evaluates reasonably supported alternatives. It should distinguish what is known from what remains uncertain. In court, confidence cannot be a substitute for evidence.
The Difference Between a New Injury and an Aggravated Preexisting Condition
Many patients have cervical degeneration, previous minor strains, or an earlier history of intermittent pain. A later accident may cause a new injury, aggravate an existing condition, or have no demonstrated causal relationship to the symptoms under review. Distinguishing these possibilities can be difficult because imaging findings often predate symptoms and medical records may be incomplete. The clinician must be willing to describe more than one contributing factor when the evidence supports it.
Suppose a patient had an old MRI showing a small disc protrusion but worked full-time without arm symptoms or restrictions. After a collision, the patient reports new radiating pain and weakness, and examination identifies a new neurological deficit. The sequence raises a medically reasonable question of traumatic aggravation, especially if the findings are consistent and alternative explanations are considered. It does not prove that the collision newly created the protrusion. The appropriate opinion may involve an exacerbation of symptoms or a superimposed injury rather than an assertion that the entire degenerative condition began on the accident date.
Now consider another patient who had substantial neck and arm symptoms for months before a collision, with little documented change afterward. A crash alone should not transform all preexisting treatment into accident-related care. A sound analysis must compare before-and-after function, symptom quality, objective findings, healthcare utilization, and other exposures. This protects the integrity of care even when the conclusions are less certain than a party might prefer.
A treating clinician can document changes and offer opinions within the limits of training and available evidence. Complex causation questions may require specialists, biomechanical expertise, or other qualified experts. We should not confuse a persuasive medical narrative with proof that every related expense was necessarily caused by one event.
The Four-Part Clinical Chain Connecting an Accident to Cervical Injury
One useful way to organize a medical causation analysis is to examine four connected questions. What happened? What condition exists? Is there a plausible mechanism connecting the event to the condition? What other explanations need consideration? This approach does not replace the legal standard, but it helps the clinician avoid circular reasoning and maintain an evidence-based structure.
First, reconstruct the event from reliable sources. The history may include the direction of impact, vehicle position, head rotation, restraint use, airbag deployment, the patient’s activities, and immediate responses. In workplace incidents, the details may involve lifting, falling, twisting, or being struck. Second, define the condition through history, examination, and tests when warranted. “Neck pain” is not interchangeable with “C5-C6 disc extrusion” or “cervical radiculopathy.” Each diagnosis carries a different degree of specificity and requires an appropriate foundation.
Third, evaluate biological plausibility. A rapid acceleration-deceleration mechanism can be compatible with cervical soft-tissue injury, but the mechanism alone cannot determine the injury. A fracture generally calls for imaging and clinical evidence; nerve-root injury requires neurological and sometimes imaging correlation. Fourth, examine alternative causes, including prior symptoms, age-related changes, other accidents, inflammatory conditions, nerve entrapment, and events occurring during recovery.
The conclusion should match the evidence. It may be reasonable to describe a soft-tissue strain as consistent with an accident while remaining uncertain whether a chronic disc abnormality was newly produced. It may also be reasonable to find that a second event caused a new deterioration. Responsible opinions can contain uncertainty. Causation is an investigation, not a slogan.
Why Symptom Timing Helps but Does Not Prove the Cause
Temporality means that one event occurred before another. If a person had no neck pain on Monday, was involved in a collision on Tuesday, and sought care for new pain on Wednesday, that sequence is important evidence. It does not automatically show that every later diagnosis was caused by the collision. Other factors may have contributed, and some findings may have existed before the event without causing symptoms. At the same time, an absence of immediate severe pain does not prove that an injury is unrelated to trauma.
A careful timeline separates the first symptom, the first medical contact, the date of a diagnosis, and the date of imaging. They may all be different. The first MRI may be obtained weeks after an accident, but the MRI date does not establish when a chronic disc feature developed. Similarly, a new diagnostic label may appear during treatment because testing became more specific, not because a new injury suddenly occurred on that date.
Documentation should describe any interval events. Did the patient return to heavy lifting? Was there a second collision, fall, or sports injury? Did a new symptom begin after a period of improvement? These details can be crucial when comparing competing explanations. The Texas Supreme Court’s discussion in JLG Trucking v. Garza (2015) makes the relevance of a later accident especially clear.
Patients benefit from keeping a truthful timeline rather than trying to make every detail fit a predetermined legal theory. A diary can record when symptoms occurred, what activities were possible, and which treatments were received. Accurate records are more persuasive than an implausibly perfect account that ignores ordinary variability or uncertainty.
Alternative Causation and Why Second Accidents Matter
Alternative causation does not mean that any hypothetical cause automatically defeats an injury claim. It means the evidence should support medically plausible explanations. If a patient was in two collisions, the clinician must investigate both. If the person developed arm symptoms before an accident, the timing deserves attention. If imaging reveals severe longstanding stenosis, that finding may be relevant even when the collision also contributed to symptoms.
In JLG Trucking v. Garza, evidence of a second collision was relevant to whether the first defendant’s conduct caused the damages being claimed. The court’s reasoning emphasizes that decision-makers should be able to consider evidence that bears on competing causal explanations. From a clinical perspective, a second event is an opportunity for a new baseline assessment. The clinician documents current complaints, compares prior examinations, and identifies any meaningful change in function or neurological status.
A later event does not necessarily erase the effects of the first one. A patient may have residual symptoms that were already improving when another injury occurred. The analysis should attempt to separate the effects when reasonably possible and honestly describe when the records do not allow precise allocation. Simply assigning all symptoms to the first event or all symptoms to the second creates an unreliable picture.
This is one reason I value repeated, standardized outcome measures. If cervical rotation, grip strength, and work participation were measured before and after each event, the resulting timeline may support a clearer explanation. The measurements are not infallible, but they can help establish that an actual functional change occurred, rather than relying only on memories reconstructed months or years later.
Imaging in Court: What an MRI Can and Cannot Establish
An MRI is powerful evidence about anatomy. It can identify a disc extrusion, neural compression, or spinal cord signal abnormality. But imaging usually cannot determine the exact age or cause of many degenerative disc findings. A post-accident MRI cannot be read as a timestamp automatically linking every abnormality to the collision. Even a clinically important finding may have predated the event. Conversely, many painful soft-tissue injuries have no dramatic MRI correlate.
The examiner should ask whether earlier imaging exists. A pre-event scan showing no particular disc lesion followed by a clearly new finding may strengthen a temporal argument, although differences in equipment, technique, and reporting still matter. Without an earlier scan, the reasoning must rely on the total clinical record. Discuss other possible contributors, such as age-related changes or previous symptoms, rather than concealing them.
Radiology language must also be used accurately. A disc bulge, protrusion, extrusion, and annular fissure are not interchangeable. A report describing mild foraminal narrowing cannot automatically justify a diagnosis of severe nerve injury. Conversely, clinical signs of nerve compromise deserve appropriate attention even if a static scan appears less impressive than expected. The patient’s history and examination remain essential.
Medical testimony should identify the evidence supporting each anatomical and causal assertion. If the clinician says a collision aggravated a preexisting disc condition, the explanation should describe how the symptoms or findings changed and why that interpretation is more plausible than other supported possibilities. The law demands a sound basis for complex medical claims, not merely the presence of an image in the file (Guevara v. Ferrer, 2007).
Chiropractic Records as Evidence of Functional Change
Chiropractic records can contribute meaningfully to a personal injury case because they often document repeated observations over time. A well-maintained file may include the initial mechanism history, symptom maps, cervical range of motion, neurological examination, functional limitations, treatment plan, patient-reported response, re-evaluation results, and referral decisions. These details may help explain what was present at different recovery points.
The strongest records are not necessarily the longest. Specificity and consistency matter. “Patient better” is less informative than a note documenting that the person now turns the head sufficiently for a particular task, sleeps with fewer interruptions, and has improved a standardized disability score. A significant new complaint should lead to a revised examination or appropriate referral rather than being copied into a repetitive template. Do not invent or exaggerate objective findings.
Careful records also distinguish treatment response from causation. If a patient improves after mobilization and exercise, that may justify continuing a time-limited plan. It does not prove that a specific collision created the underlying disorder. The patient might have improved through natural healing, active rehabilitation, other medical care, or a combination of factors. A transparent clinician explains these limits while still documenting observed progress.
A medical-legal report should also separate facts, patient reports, clinical interpretations, and opinions. For example, a patient can report that a collision occurred at a certain speed. Still, unless the clinician has an appropriate independent basis, the medical report should not present that estimate as an established engineering fact. Accurate source attribution makes the record more trustworthy.
Medical Necessity, Reasonable Care, and Maximum Medical Improvement
Medical necessity asks whether a particular service is appropriate for an identified clinical problem and whether its expected benefit justifies its use. It is distinct from whether the condition was caused by an accident. A patient may have an accident-related injury yet receive a treatment that is not supported by the clinical findings. Another patient may appropriately require treatment for a condition unrelated to the incident being litigated. These questions should not be collapsed into one conclusion.
A reasonable plan states the diagnosis, functional goals, treatment methods, frequency or trial period, expected measurable outcomes, and reassessment schedule. Care may be more frequent when symptoms are highly irritable or function is greatly restricted, then taper as the patient learns a home program. No scientifically defensible universal number of visits applies to every neck injury. When a patient is not improving, repeating the same intervention indefinitely without reconsidering diagnosis or goals is difficult to justify.
Maximum medical improvement, or MMI, commonly refers to a stage of relative medical stabilization, though its formal meaning depends on the legal or administrative context. It should not be confused with complete recovery, absence of pain, or restoration of elite athletic performance. A person may reach MMI while retaining limitations or needing general conditioning. A different person may recover full function before an expected administrative timeline.
Documentation should explain why treatment ends, changes, or shifts to a self-management program. A conclusion that the patient has improved should be supported by symptom trends, functional measurements, examination findings, and the individual’s goals. In court or an insurance review, such explanations are more meaningful than unsupported declarations that every procedure was necessary solely because it was performed.
Treating Clinicians, Expert Witnesses, and the Limits of a Medical Opinion
A treating clinician observes symptoms, performs examinations, makes diagnoses, prescribes or recommends care within the applicable scope, and monitors response. An expert witness may be asked to explain specialized medical questions under legal evidentiary rules. One person may serve both roles in a particular case, but a treatment relationship does not automatically qualify someone to opine on every biomechanical, neurological, economic, or legal subject. Qualifications and the opinion’s foundation matter.
For a straightforward cervical strain, clinical history and examination may be sufficient for many care decisions. A case alleging a highly specific traumatic disc injury, complex nerve damage, permanent disability, or causation after multiple incidents may require a more detailed analysis and specialized expertise. The exact testimony required depends on the claims and governing law. The Texas Supreme Court has repeatedly stressed the distinction between conditions familiar to ordinary experience and complex medical questions that require expert evidence (Guevara v. Ferrer, 2007; JLG Trucking v. Garza, 2015).
A responsible opinion uses appropriately qualified evidence and avoids certainty beyond the record. The clinician may need to say that symptoms are consistent with a collision. Still, the available data cannot definitively distinguish a new disc injury from aggravation of a preexisting condition. Such candor does not undermine the purpose of healthcare. It keeps treatment and documentation trustworthy, regardless of which party requested the report.
For patients, the practical message is that good medical care and good legal documentation overlap, but they are not identical. Health and safety come first. The record should accurately describe the patient. Legal professionals evaluate how that record fits the claims and burdens of proof. This division of responsibilities improves the quality of both clinical and courtroom decisions.
A Hypothetical Rear-End Collision With Delayed Neck Pain
Consider an educational scenario in which a person is stopped at a traffic light, and another vehicle strikes the rear bumper. At the scene, the driver is shaken but reports no significant pain. The following morning, the driver notices cervical stiffness, aching toward the shoulders, and headache. The history is compatible with a possible whiplash-associated disorder, but it does not establish the diagnosis. The first step is to ask about head injury signs, new neurological symptoms, the precise sequence of complaints, and any immediate medical evaluation.
A clinician performs an appropriate physical and neurological examination and decides whether the trauma meets criteria for imaging. If no serious findings are present, a conservative plan may include education, gentle movement, symptom management, and progressive exercise. The patient identifies specific functional goals, such as driving safely, returning to work, and sleeping without repeated awakenings. At re-evaluation, we compare baseline and current measures. If headache symptoms change or arm weakness emerges, we must reconsider the diagnosis and plan.
If a lawsuit follows, the medical record can describe a plausible mechanism, symptoms appearing close to the event, relevant examination findings, and the observed course. It should not imply that delayed symptoms prove a disc tear or that lack of immediate pain excludes trauma. In this hypothetical example, the strength of the causation opinion depends on the total evidence, including prior cervical problems and other possible causes. This is an illustrative scenario, not an actual patient record or a promise about a legal outcome.
A Hypothetical Construction Worker With Preexisting Cervical Degeneration
Imagine a construction worker who previously had occasional neck soreness but completed normal lifting tasks and had not missed work. After a fall, the worker reports a new pattern of arm pain and trouble gripping tools. Imaging reveals degenerative narrowing and a disc abnormality. The challenge is to determine which symptoms and limitations were present beforehand, whether the fall caused a new injury or aggravated an existing disorder, and whether current neurological deficits correlate with the available imaging.
The immediate clinical priority is safety. The clinician examines strength, sensation, reflexes, gait, and possible cord signs. The clinician arranges appropriate imaging or referral when indicated. Rehabilitation is planned around the worker’s demands, progressing from tolerable movement to carrying, reaching, lifting, and job-specific tasks. Care is modified if neurological symptoms worsen. A worker with a persistent neurological deficit should not be returned to hazardous activity merely because resting pain has improved.
From a causation standpoint, the historical record matters. Prior treatments, work ability, absence or presence of arm symptoms, and examinations before the event may help identify an actual change. The clinician can explain that degeneration and trauma may coexist, but should not represent a new MRI as proof that the entire anatomical condition began with the fall. In this way, careful medicine can support an honest analysis without minimizing the worker’s experience.
A Hypothetical Patient With Two Accidents During Recovery
In another educational example, a patient begins care after a collision with documented cervical pain, reduced rotation, and difficulty sleeping. Over several weeks, the person improves substantially and returns to most daily activities. Before complete recovery, a second collision occurs. The patient then reports new arm symptoms and a return of severe headaches. A clinician who assumes that all symptoms belong to the original injury may miss a new problem. A clinician who attributes every complaint to the second event may ignore documented residual deficits from the first.
The appropriate response is a new assessment. We preserve the pre-second-accident records, document the second event and symptom chronology, repeat relevant neurological and functional tests, and decide whether imaging or specialist care is needed. The resulting comparisons may clarify which problems were improving and which appeared or worsened after the new trauma. They may also reveal limitations in what can be apportioned medically.
This scenario reflects the broader clinical lesson illustrated by published observations on El Paso Back Clinic and the legal relevance of later accidents discussed in JLG Trucking v. Garza (2015). Thorough records can help explain change, but they should not manufacture certainty where events overlap. The primary purpose remains appropriate care after each injury.
Building a Sustainable Neck Health Routine After the Acute Phase
Once a clinician has excluded serious pathology and established a suitable plan, recovery increasingly depends on habits patients can control. I encourage a simple, repeatable wellness routine rather than a complicated list of treatments that requires constant supervision. Adjust the routine to symptoms, diagnosis, and occupational or athletic demands. It must not replace medical follow-up for progressive neurological deficits or other red flags.
A reasonable framework may include:
Daily movement variety: Change positions periodically and use comfortable neck and shoulder movements.
Progressive strengthening: Build cervical, scapular, and general muscular capacity with an individualized program.
Aerobic activity: Walk, cycle, or perform another appropriate activity to support conditioning and participation.
Sleep consistency: Address barriers to rest, including pain, medications, and possible sleep disorders.
Workstation adaptation: Arrange equipment to reduce unnecessarily prolonged or awkward exposure without obsessing over perfect posture.
Symptom tracking: Record functional gains and important changes, not only pain fluctuations.
Follow-up when needed: Seek reassessment for new deficits, loss of progress, or failure to meet goals.
In early recovery, the routine may be brief. The person might practice a few comfortable turns, walk for several minutes, and use gentle shoulder exercises. Later, the program may include resistance training, longer walks, work simulation, or sport-specific conditioning. Progression should be based on response, not a calendar alone. The aim is to reduce dependence on recurring passive treatment and build confidence in managing normal symptom variations.
Frequently Asked Questions About Neck Pain and Chiropractic Care
Can neck pain cause headaches?
Neck disorders can contribute to certain headache patterns, including cervicogenic headache, but migraine and other primary headaches can also cause neck discomfort. Location and muscle tenderness alone do not confirm the source. Evaluation is especially important for a new, severe, or unusual headache, or when neurological symptoms accompany it.
Can neck pain cause tingling in the fingers?
Yes, cervical radiculopathy may produce tingling or numbness in an arm or hand. Yet peripheral nerve entrapment, diabetes-associated neuropathy, and other disorders can cause similar symptoms. A focused neurological examination helps determine the next step. Progressive objective weakness warrants prompt medical attention.
Does a normal MRI mean the pain is imaginary?
No. Many painful muscle, ligament, joint, and sensitization-related conditions do not create a dramatic MRI finding. Imaging is one piece of evidence. Interpret a normal or relatively unremarkable scan alongside the patient’s history, examination, and functional limitations. It does not automatically prove or disprove accident-related causation.
Can a chiropractor treat neck pain without making adjustments?
Yes. Chiropractic care can include assessment, education, exercise, low-force mobilization, soft-tissue techniques, and referral coordination. Not every patient needs a thrust adjustment. Treatment selection should consider safety, patient preference, diagnosis, and objective response.
How quickly should neck pain improve after a collision?
There is no universal timeline. Many uncomplicated cases improve over weeks, while some people develop persistent symptoms. Prognosis depends on injury severity, neurological findings, prior health, symptom burden, sleep, psychosocial factors, and participation in rehabilitation. A lack of expected progress should prompt reassessment rather than repeating the same intervention endlessly.
Is chiropractic care safe for every cervical condition?
No. A suspected fracture, instability, spinal cord compromise, vascular disorder, infection, or certain other conditions may make cervical manipulation inappropriate. A clinician must screen for red flags and discuss risks and alternatives. Selecting exercise, low-force care, or referral can be the safest option.
Does improvement after chiropractic care prove the accident caused the injury?
No. Treatment response can show that symptoms or function changed during care, but it does not independently establish the cause of the original condition. A medical causation opinion requires the history, examination, relevant investigations, a plausible mechanism, and consideration of alternatives.
What if neck pain started several days after the accident?
Delayed recognition of symptoms can occur. Document the timing honestly alongside the mechanism, other injuries, activities between the event and onset, and any subsequent medical findings. Delay does not prove or automatically disprove the relationship. Sudden severe or worsening neurological symptoms still demand urgent evaluation.
When is surgery considered for cervical pain?
Surgical assessment may be indicated for significant spinal cord compression, progressive neurological impairment, selected structural disorders, or persistent symptoms that have not responded to appropriate conservative care. A consultation helps compare options. Most uncomplicated mechanical neck pain does not require surgery, while some serious conditions should not be managed conservatively without specialist input.
Can neck pain affect mood, concentration, and sleep?
Yes. Persistent pain can interrupt rest, increase fatigue, reduce concentration, and contribute to anxiety or depressed mood. These effects are real and relevant to treatment. They may also arise from separate medical or psychological conditions, so the assessment should not assume that every symptom has a cervical origin.
What should I document after a personal injury?
Record the event accurately, seek needed medical care, preserve relevant records, and report symptoms and functional changes truthfully. During treatment, standardized measurements, meaningful goals, and clear notes on progress or setbacks can help. Do not invent details or pressure a clinician to assign a diagnosis that the evidence does not support.
Can someone with old degenerative changes still have a new injury?
Yes. Degenerative features and a new traumatic condition may coexist. A collision may also aggravate a previously symptomatic or asymptomatic disorder. The conclusion must rest on a before-and-after comparison, mechanism, examination, imaging when relevant, and alternative explanations, not on the presence of degeneration alone.
Conclusion: Evidence-Based Neck Pain Care That Restores Function and Respects the Facts
Neck pain can influence much more than a small region of the spine. The cervical system helps coordinate movement, sensation, vision, balance, work, recreation, and sleep. Pain may arise from muscles, joints, discs, nerves, or other conditions, and overlapping symptoms require a careful differential diagnosis. The best plan begins with safety, explains the findings in understandable language, and uses measurable goals to guide progress.
Chiropractic care, when properly selected, can contribute to a comprehensive nonsurgical strategy that includes patient education, gentle manual treatment when appropriate, therapeutic exercise, progressive strengthening, and practical lifestyle support. The evidence is strongest for a measured, individualized approach rather than claims that one technique cures every condition. Medical assessment and specialist care remain essential when the diagnosis or the patient’s safety requires them.
At Injury Medical Clinic PA in El Paso, I integrate the chiropractic and rehabilitation perspective with my advanced practice nursing training and the medical oversight of Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. Together with the broader team, we aim to address mechanical, neurological, functional, and medical concerns without confusing association with causation or treatment response with proof of an accident-related injury.
For personal injury patients, an accurate record of the mechanism, baseline function, diagnosis, alternative explanations, treatment response, and changes over time can help explain the injury in a clinically and legally responsible manner. The same commitment to accuracy that protects the patient also makes the evidence more useful in court. The ultimate goal is to help each person regain safe movement, independence, and confidence while remaining candid about the limits of available knowledge.
Blanpied, P. R., Gross, A. R., Elliott, J. M., Devaney, L. L., Clewley, D., Walton, D. M., Sparks, C., & Robertson, E. K. (2017). Neck pain: Revision 2017. Journal of Orthopaedic & Sports Physical Therapy, 47(7), A1-A83.
Chacko, N., Gross, A. R., Miller, J., Santaguida, P. L., Burnie, S. J., Gelley, G. M., Paquin, J. P., Duranai, M. R., Langevin, P., Chopra-Tandon, N., Chak, N. T., Hoving, J. L., & Bobos, P. (2025). Manual therapy with exercise for neck pain. Cochrane Database of Systematic Reviews, 2025(12), CD011225.
neck pain treatment El Paso, cervical spine pain, neck pain symptoms, neck pain comorbidities, chiropractic care for neck pain, integrative chiropractic El Paso, whiplash injury recovery, car accident neck injury, personal injury medical causation, Texas medical causation, cervical radiculopathy, cervical disc injury, cervical myelopathy warning signs, cervicogenic headache, occipital neuralgia, chiropractic rehabilitation, neck pain physical therapy, nonsurgical neck pain treatment, functional medicine and neck pain, cervical spine MRI, medical documentation after car accident, accident related neck pain, Dr Alexander Jimenez, Dr Maria Guadalupe Cardenas, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, El Paso Back Clinic, neurological examination, deep neck flexor exercise, spinal manipulation safety, neck pain and sleep, neck pain and stress, cervical injury causation, Texas personal injury evidence
Persistent Lower Back Pain After a Car Accident: When Is Further Treatment Medically Justified?
Marcus finished his first six weeks of care after a rear-end collision on Loop 375. At rest, his lower back pain had dropped from an 8 out of 10 to a 3 or 4. He could sit through meetings and drive short distances. However, he could not perform the core functions of his job. As a warehouse supervisor in El Paso, he still needed to lift and move 50-pound boxes several times a day. Each time he bent and lifted, a sharp catch radiated across his lower back and into one hip. He paused mid-lift, shifted his weight, and felt the familiar fear that the next box would set him back weeks. His digital range-of-motion measurements remained restricted, and his orthopedic tests stayed positive on the same side the collision loaded.
That gap between “I feel better sitting still” and “I still cannot do my job safely” is common after motor vehicle accidents. It is also the point where further treatment must be medically justified—not by the simple fact that pain continues, but by clear clinical findings that residual traumatic effects are limiting function.
Pain persistence alone does not support unlimited care. Pain is a subjective report. Insurance reviewers, independent medical examiners, and courts look for objective evidence that the injury continues to produce measurable impairment, that prior care produced a meaningful response, and that additional treatment has a reasonable expectation of improving function or preventing further loss. Under the Texas Eggshell Plaintiff rule, a person with pre-existing disc degeneration can still recover for traumatic aggravation, but the file must show the change. Timed digital motion data, positive mechanical tests that match the collision forces, and documented inability to meet job demands provide that evidence. Without them, continued care can appear open-ended.
When Reassessment Is Medically Indicated
Reassessment is appropriate when a patient has completed an initial course of care yet still shows residual mechanical or functional deficits that interfere with prior activities. Common indicators include:
Restricted lumbar range of motion measured digitally that has not returned to expected levels
Persistent positive orthopedic tests (for example, Kemp’s test or straight-leg raise) that reproduce the patient’s familiar pain pattern
Documented difficulty with specific job tasks such as repeated lifting, prolonged standing, or bending under load
Failure to progress as expected after an adequate trial of care, or a pattern in which symptoms improve at rest but flare with the physical demands of work
New or progressive neurological findings that require clarification
In Marcus’s case, the combination of ongoing positive mechanical findings and clear work-related limitations justified a structured reassessment rather than simply extending the same passive treatments. The goal was to determine whether further active rehabilitation and selected conservative interventions could close the remaining functional gap or whether specialist referral and additional diagnostics were needed.
Active Rehabilitation That Targets Real Demands
Once acute inflammation has settled, active rehabilitation becomes the core of further care. Passive treatments alone rarely restore the capacity required for physically demanding work. Progressive programs focus on trunk and hip stability, controlled loading, and job-specific movement patterns. Directional preference exercises (often based on McKenzie principles), graded lifting practice, and endurance work for the core and posterior chain help the patient relearn safe mechanics under load. Clinical guidelines support these approaches, emphasizing early return to activity with modifications rather than prolonged rest.
For a warehouse supervisor, rehabilitation includes practicing the exact lifts required at work—close to the body, with neutral spine, and progressive weight—while monitoring symptom response. Serial functional testing documents whether capacity is improving, plateauing, or limited by residual structural findings. This objective record supports both clinical decision-making and any future-care or work-restriction opinions.
Selected Conservative Interventions Under Dual-Scope Oversight
When residual mechanical findings persist, selected conservative interventions remain appropriate. Spinal manipulative therapy can restore segmental motion. Non-surgical spinal decompression may reduce intradiscal pressure and support disc nutrition in selected patients with disc-related mechanical pain. Electroacupuncture and other neuromodulatory techniques can help modulate pain signals and support recovery without heavy reliance on medication. Class IV laser therapy and targeted soft-tissue work address persistent muscle guarding that limits motion.
These options are not endless by default. They are continued only while objective measures (range of motion, functional tests, and patient-reported work capacity) show benefit, and they are coordinated with the patient’s overall medical picture. At Injury Medical Clinic PA, this coordination occurs under the medical direction of Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine with more than 40 years of experience, working alongside dual-licensed Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP. Dr. Jimenez’s dual credentials allow him to address the structural, soft-tissue, and mechanical aspects of the injury, as well as the broader medical context. This integrated setup is one of the only clinics in El Paso that provides these treatments under true MD/NP and DC collaboration.
When Specialist Referral or Additional Diagnostics Are Needed
Further treatment is also justified when reassessment reveals findings that require more specialized input. Progressive neurological deficits, saddle anesthesia, or bowel/bladder changes demand urgent imaging and specialty referral. Even without red flags, flexion-extension radiographs can quantify alteration of motion segment integrity (AOMSI). For the lumbar spine, translation exceeding roughly 4.5 mm or abnormal angular motion relative to adjacent levels documents ligamentous insufficiency that scar tissue alone may not restore. These measurements support AMA Guides impairment ratings and help isolate traumatic aggravation from longstanding degeneration.
Timed MRI can clarify disc morphology when symptoms persist. High-intensity zones, specific annular findings, and correlation with the mechanism of injury help distinguish acute or subacute changes from purely chronic degeneration. Consider electrodiagnostic studies if radiculopathy remains in question. These diagnostics are not ordered routinely; they are ordered when clinical findings indicate they will change management or strengthen the causation record.
In personal injury cases arising from I-10 or Loop 375 collisions, this level of documentation helps establish both clinical and proximate causation. The mechanics of rapid deceleration and axial loading are linked to the residual mechanical findings and functional deficits. The resulting records support Letters of Protection, special damages, and future-care projections that include necessary rehabilitation or monitoring rather than open-ended passive care.
Bioethical Pillars in Ongoing Care
Three principles guide decisions about further treatment.
Beneficence means the integrated approach—chiropractic mechanical care, targeted rehabilitation, and medical oversight—exists to restore root function rather than simply suppress symptoms. The goal is a safer return to the physical demands of work and daily life.
Non-maleficence means preferring non-invasive, drug-sparing options first. When residual deficits respond to progressive loading and selected conservative interventions, the risks of prolonged opioid use or premature surgical consideration are reduced.
Autonomy means the patient remains the informed decision-maker. Clear explanations of findings, options, and expected outcomes allow the patient to participate in decisions about work modifications, further diagnostics, or specialist referral. Coordination with the patient’s existing primary care physician is maintained so care remains seamless.
Marcus’s residual work limitations were not dismissed as “just pain.” They were measured, linked to residual mechanical findings that matched the collision forces, and addressed with a plan that combined progressive rehabilitation and continued dual-scope oversight. That approach is medically justified because it ties treatment to objective function, not the mere presence of discomfort.
For a deeper look at how objective measurements and dual-licensure documentation establish medical-legal causation after collisions, visit dralexjimenez.com. Related pages on lumbar disc nomenclature, AOMSI and AMA Guides ratings, and functional recovery after injury provide additional context for both patients and the attorneys who represent them.
If you or a client is still limited in physically demanding work after an initial course of care following a car accident, a structured reassessment can clarify whether further treatment is medically indicated. Contact Injury Medical Clinic PA in El Paso to discuss an evaluation focused on residual mechanical findings and functional capacity.
References
American College of Physicians. (2017). Noninvasive treatments for acute, subacute, and chronic low back pain: A clinical practice guideline from the American College of Physicians. Annals of Internal Medicine, 166(7), 514–530. doi.org/10.7326/M16-2367
American Medical Association. (2008). AMA Guides to the evaluation of permanent impairment (6th ed.). American Medical Association. (Classic criteria for alteration of motion segment integrity [AOMSI] and Diagnosis-Related Estimates remain widely referenced in impairment rating; updated editions continue to address motion-segment findings.)
Department of Veterans Affairs & Department of Defense. (2022). VA/DoD clinical practice guideline for the diagnosis and treatment of low back pain (Version 3.0). healthquality.va.gov/guidelines/Pain/lbp
Fardon, D. F., & Milette, P. C. (2001). Nomenclature and classification of lumbar disc pathology: Recommendations of the combined task forces of the North American Spine Society, American Society of Spine Radiology, and American Society of Neuroradiology. Spine, 26(5), E93–E113. doi.org/10.1097/00007632-200103010-00006
State Bar of Texas. (2020). Texas pattern jury charges: General negligence & intentional personal torts (PJC 28.8B & 28.8C). State Bar of Texas. (These charges instruct juries on aggravation of pre-existing conditions under the eggshell-plaintiff principle.)
If Spinal Decompression Relieves Back Pain, Does That Prove a Herniated Disc Caused It?
A patient finishes a course of motorized spinal decompression, stands up, and reports that the familiar ache across the low back has eased. The relief feels clear. It is natural to conclude that the treatment “worked on the disc,” and therefore the disc must have been the structure generating the pain. In personal-injury and clinical settings, this reasoning appears often. It is also incomplete.
Symptomatic improvement during a carefully supervised treatment program is valuable information. It tells clinicians and patients that a non-invasive approach can change symptoms and function. It does not, by itself, identify the single anatomical structure that was producing the pain. Clinicians must read disc pathology, nonspecific low-back pain, examination findings, and imaging findings together. Treatment response is one data point among many, not a diagnostic test that names the pain generator.
Disc Pathology Is Common and Often Silent
Intervertebral discs change with age, load, and prior stress. On MRI, disc bulges, protrusions, and even frank herniations appear in people who have never reported meaningful back or leg pain. Systematic reviews of asymptomatic adults show that disc herniations and degenerative findings are present in a substantial fraction of the population, and the prevalence rises with age (Brinjikji et al., 2015). A herniated disc visible on imaging is therefore a morphological observation. The North American Spine Society nomenclature emphasizes that the terms “herniated disc” or “protrusion” describe location and morphology; they do not, by themselves, establish etiology, symptom correlation, or the need for any particular treatment (Fardon et al., 2014).
Even when a disc herniation is present and the patient has pain, the relationship is not automatic. Chemical irritation from annular fissures, mechanical loading of the facet joints, muscle guarding, and altered movement patterns can all contribute. In many patients, more than one structure is sensitized at the same time. A treatment that reduces intradiscal pressure or unloads the posterior elements may improve symptoms by affecting several of those structures simultaneously. The improvement does not isolate which structure was dominant.
Nonspecific Low-Back Pain Remains the Most Common Presentation
Most episodes of low-back pain are classified as nonspecific. That label means that no single, clearly identifiable pathoanatomical source accounts for the symptoms after a careful history and examination. Large clinical guidelines and evidence reviews consistently note that a specific structural diagnosis is established in only a minority of patients presenting with axial low-back pain (Chou et al., 2007; Maher et al., 2017). Nonspecific pain can still be real, functionally limiting, and responsive to mechanical care.
Spinal decompression therapy creates a controlled reduction in intradiscal pressure and can increase intervertebral height temporarily. Those mechanical effects may reduce load on irritated discs, facet joints, and surrounding soft tissues. Patients often report less pain and better tolerance for standing or walking. The same patients may also improve with targeted exercise, manual therapy, or simple activity modification. When multiple interventions that unload or stabilize the lumbar region produce similar relief, the response supports the idea that mechanical loading is relevant. It does not prove that a particular disc herniation seen on one MRI slice was the sole generator.
What the Examination and Imaging Can and Cannot Show
A thorough examination looks for directional preference, symptom changes with repeated movements, neurological findings, and functional limitations. Digital range-of-motion measurements, straight-leg-raise responses, and segmental motion testing provide objective data that clinicians can track over time. These findings help clinicians decide whether a trial of decompression is reasonable and later document whether function changed.
Imaging adds morphological detail. Flexion-extension radiographs can demonstrate altered motion-segment integrity when translation or angular motion exceeds established thresholds used in impairment systems. MRI can show disc contour, annular high-intensity zones, and nerve-root contact. However, none of these studies reliably identify the pain-generating structure in every patient. Studies comparing imaging findings with clinical outcomes show only modest correlations; many patients with clear disc herniations improve without any change in herniation size, and some patients with modest imaging findings remain symptomatic (Chou et al., 2011). Provocative discography was once used to try to link a disc to pain, yet its diagnostic value is limited by high false-positive rates and the fact that it is an invasive procedure whose results do not automatically dictate treatment.
The Limits of Treatment-Response Reasoning
Reasoning that “the treatment relieved the pain; therefore, the structure the treatment targeted must have been the cause” is a form of post-hoc attribution. It is common in everyday clinical conversations and sometimes appears in medical-legal arguments. Several factors make it unreliable as proof of the original pain generator:
Many lumbar structures share innervation and can respond to the same unloading force.
Natural history and concurrent changes in activity, posture, or inflammation can improve symptoms independently of the treatment.
Placebo and contextual effects are well documented in musculoskeletal care; some improvement occurs even when the mechanical intervention is minimal.
Patients often receive more than one intervention. Without a controlled comparison, you cannot assign improvement after a package of care to a single component.
In a medical-legal file, treatment response is most useful when it is documented alongside objective baseline and follow-up measures—range of motion, functional questionnaires, neurological status, and, when indicated, serial imaging. The response then becomes part of a longitudinal narrative rather than a stand-alone diagnostic claim. Attorneys and clinicians reviewing the file can see that mechanical care produced measurable functional change; they cannot, based on the response alone, conclude that a particular disc herniation was the exclusive cause of the original pain.
An Integrated Approach That Respects These Limits
At Injury Medical Clinic PA in El Paso, we begin evaluating lumbar complaints with a dual-scope assessment. Dr. Alex Jimenez, DC, APRN, FNP-BC, documents soft-tissue and biomechanical findings, including digital range-of-motion and segmental testing. Dr. Maria Guadalupe Cardenas, MD, provides medical direction, reviews comorbidities, and coordinates any indicated laboratory or imaging work-up. When spinal decompression is chosen, it is applied within a broader plan that may include targeted exercise, soft-tissue work, and education on load management. Clinicians record symptom change but form the clinical impression from the full set of findings, not improvement alone.
This approach aligns with three practical principles. Beneficence is served by selecting interventions that address modifiable mechanical and inflammatory contributors without assuming a single structure is responsible. Non-maleficence is served by preferring non-invasive unloading and movement strategies before considering more aggressive options. Autonomy is served by explaining to the patient, in plain language, what the imaging shows, what it does not show, and how treatment response will be interpreted as one piece of information rather than proof of a specific diagnosis.
What makes the clinic distinct in El Paso is the combination of a board-certified internist serving as medical director and a dual-licensed nurse practitioner who specializes in soft-tissue and biomechanical injury. Few clinics in the region integrate these scopes under one roof while also offering advanced mechanical decompression, digital motion analysis, and coordinated medical oversight. The result is documentation that describes both the morphological findings and the functional response without overclaiming that one proves the other.
Patients and attorneys who need a clearer picture of how disc findings, examination data, and treatment response fit into a causation narrative can review related discussions on lumbar disc nomenclature, imaging correlation, and the broader process of establishing medical-legal causation. Those resources appear on the clinic’s educational site and reinforce the same principle: relief is welcome, yet the structure that generated the pain is identified only when history, examination, imaging, and longitudinal function are considered together.
Symptom relief after spinal decompression is a positive clinical outcome. It supports the continued use of non-invasive mechanical care for many patients with lumbar pain. It does not, by itself, prove that a herniated disc was the pain-generating structure. That determination still requires the full clinical picture.
References
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., … Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816.
Chou, R., Qaseem, A., Snow, V., Casey, D., Cross, J. T., Jr., Shekelle, P., & Owens, D. K. (2007). Diagnosis and treatment of low back pain: A joint clinical practice guideline from the American College of Physicians and the American Pain Society. Annals of Internal Medicine, 147(7), 478–491.
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Gabriel Rothman, S. L., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0. The Spine Journal, 14(11), 2525–2545.
Maher, C., Underwood, M., & Buchbinder, R. (2017). Non-specific low back pain. The Lancet, 389(10070), 736–747.
Cervical Muscle and Joint Factors That Amplify Migraine Frequency — and How Structural Care Complements Guideline-Based Prevention
Many people notice their migraines don’t stay confined to the head. The pain often starts or intensifies when the neck feels tight, the base of the skull aches, or turning the head triggers a familiar throb behind the eyes. After a collision or long periods of forward head posture, those neck symptoms can push occasional headaches into a pattern of 15 or more headache days per month. At that point, the condition meets criteria for chronic migraine, and guideline-based prevention such as the PREEMPT injection protocol with onabotulinumtoxinA becomes a medically appropriate option. Structural care that addresses the cervical muscles and joints does not replace that protocol; it reduces the mechanical amplifiers that can keep the frequency high even when preventive injections are used.
Why Neck Tension Amplifies Migraine Frequency
The connection is anatomical and functional. Sensory signals from the upper neck travel through the trigeminocervical complex and converge with pathways that process migraine pain. When certain muscles stay shortened or overloaded, they continuously feed extra input into those shared circuits. Restricted joints add further mechanical irritation. The result is a lower threshold for migraine attacks and more days spent in pain.
Patients commonly describe:
A band of pressure that climbs from the shoulders into the temples
One-sided headache that worsens when looking down at a phone
Increased pain when turning the head while driving on I-10 or Loop 375
Stiffness at the base of the skull that precedes or accompanies the migraine
Key Cervical Muscles That Contribute
Assessment begins with a clear map of the contributing muscles. These same regions appear on the PREEMPT injection map and often respond to structural care.
Occipital and suboccipital muscles
These sit at the base of the skull. They frequently harbor trigger points that refer pain over the top of the head and into the temples.
Cervical paraspinal muscles
These run alongside the spine. After whiplash or prolonged sitting, they often become guarded and contribute to ongoing neck stiffness.
Upper trapezius
This muscle links the shoulder girdle to the neck. It commonly tightens under stress, poor workstation ergonomics, or after-impact injuries.
On the PREEMPT protocol, these muscles receive:
Occipitalis: 30 units across six sites
Trapezius: 30 units across six sites
Cervical paraspinal muscles: 20 units across four sites
Together with other head and neck sites, the full protocol delivers 155 units across 31 sites, repeated every 12 weeks. The injections reduce the release of pain-signaling chemicals from nerve endings in those muscles. When underlying segmental restrictions and muscle imbalances remain unaddressed, however, the mechanical load continues and can limit how far the headache-day count falls.
Digital range-of-motion measurements that document loss of rotation or extension
Segmental restrictions at the atlantoaxial joint or lower cervical levels
Altered disc-height relationships that change load distribution
Soft-tissue findings such as taut bands in the trapezius, shortened suboccipitals, or guarded paraspinals
These findings are recorded alongside the patient’s headache diary so the timeline of neck stiffness and migraine frequency can be compared. This dual documentation supports both clinical decision-making and, when relevant, the medical-legal file by showing how post-injury alignment issues interact with the migraine pattern.
How Structural Care Complements the PREEMPT Protocol
Structural care is sequenced with the preventive protocol rather than replacing it. Typical elements include:
Gentle cervical adjustments that restore segmental motion and reduce aberrant input into the trigeminocervical complex
Soft-tissue techniques that lengthen the occipital, paraspinal, and trapezius groups
Therapeutic exercise that helps the muscles stay lengthened between injection cycles
Patients often notice that neck-related triggers become less potent within the first few weeks of combined care. This can translate into fewer headache days even before the second or third Botox cycle. Because the structural interventions are non-surgical and drug-free, they fit a stepwise approach that prioritizes lower-risk options while still allowing the evidence-based preventive injections to proceed when criteria are met.
Bioethical Principles Guiding Combined Care
Beneficence
Combined structural relief and guideline-based prevention aim to reduce migraine days, improve neck mobility, and increase tolerance for work and driving.
Non-Maleficence
We address mechanical contributors first with non-invasive methods. This reduces the chance that ongoing muscle tension will undermine the preventive treatment or push patients toward more invasive procedures.
Autonomy
Patients learn both the alignment plan—why a specific joint is being mobilized and what home exercises maintain the change—and the injection sites. This shared understanding lets them track how each component contributes to their results and discuss adjustments with the care team.
A Unique Integrated Approach in El Paso
Injury Medical Clinic PA in El Paso is uniquely positioned to deliver this coordinated approach. The clinic’s medical director, Dr. Maria Guadalupe Cardenas, MD, provides internal medicine oversight for complex metabolic and inflammatory factors that can increase headache frequency. Dr. Alex Jimenez, DC, APRN, FNP-BC, specializes in soft-tissue injury and integrates chiropractic structural care with advanced practice nursing. It is the only clinic in El Paso, TX, that provides these treatments under one roof, allowing the same dual-licensed team to document segmental findings, muscle contributions, and the response to both structural care and the PREEMPT protocol in a single continuous record.
Patients who leave with a clear understanding of their neck mechanics and injection map are better able to protect the gains between visits. Simple posture cues, targeted stretches for the upper trapezius and suboccipitals, and consistent headache-day logging become tools they own rather than instructions they merely receive. When they share those daily observations with clinicians, the plan can be refined so structural work continues to support the preventive effect of the injections.
Integrated structural documentation appears in the broader clinical framework at https://dralexjimenez.com. Related discussions of the PREEMPT protocol and integrated migraine care are available in the 2026 Clinical Guide on BOTOX for chronic migraine and the Complete Clinical Guide to Integrated Migraine Treatment. Additional background on cervicogenic contributions and manual approaches is available on the clinic’s pages on cervicogenic headaches associated with neck issues and integrative treatment, including chiropractic care for migraines. Together, these resources help patients and referring providers see how cervical muscle and joint factors are assessed and managed alongside guideline-based prevention.
References
AbbVie. (2026). BOTOX (onabotulinumtoxinA) for injection, for intramuscular use [Prescribing information]. https://www.rxabbvie.com
Aurora, S. K., Winner, P., Freeman, M. C., Spierings, E. L., Heiring, J. O., DeGryse, R. E., VanDenburgh, A. M., Nolan, M. E., & Turkel, C. C. (2011). OnabotulinumtoxinA for treatment of chronic migraine: Pooled analyses of the 56-week PREEMPT clinical program. Headache: The Journal of Head and Face Pain, 51(9), 1358–1373. https://doi.org/10.1111/j.1526-4610.2011.01990.x
Dodick, D. W., Turkel, C. C., DeGryse, R. E., Aurora, S. K., Silberstein, S. D., Lipton, R. B., Diener, H.-C., & Brin, M. F. (2010). OnabotulinumtoxinA for treatment of chronic migraine: Pooled results from the double-blind, randomized, placebo-controlled phases of the PREEMPT clinical program. Headache: The Journal of Head and Face Pain, 50(6), 921–936. https://doi.org/10.1111/j.1526-4610.2010.01678.x
Headache Classification Committee of the International Headache Society (IHS). (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. https://doi.org/10.1177/0333102417738202
Lipton, R. B., Varon, S. F., Grosberg, B., McAllister, P. J., Freitag, F., Aurora, S. K., Dodick, D. W., Silberstein, S. D., Diener, H. C., DeGryse, R. E., Nolan, M. E., & Turkel, C. C. (2011). OnabotulinumtoxinA improves quality of life and reduces impact of chronic migraine. Neurology, 77(15), 1465–1472. https://doi.org/10.1212/WNL.0b013e318232ab65
Potrebic, S., Rizzoli, P., Loder, E., Burch, R., Loder, E., & Burch, R. (2026). 2026 American Academy of Neurology/American Headache Society guideline for the preventive treatment of migraine. Neurology.
Rees, T. A., & others. (2025). Overlapping neurological mechanisms between migraine and neck pain. Cephalalgia or relevant 2025 review as cited in clinical guides.
Before and After the Accident: How Comparing Spine Examinations Helps Explain New Limitations
A car crash does not create a perfectly preserved “before” picture of the patient’s spine.
Most people have never had their lumbar range of motion measured. They have never undergone formal muscle-strength testing. Many may never have needed an MRI. Their medical chart may contain nothing more specific than an old note about occasional back stiffness.
Then an accident happens.
Suddenly, the same person cannot sit through a workday, lift groceries without pain, sleep comfortably, or drive across El Paso without stopping because pain travels into a leg.
For the injured patient, the change may feel obvious.
For the treating clinician—and particularly when a personal injury claim is involved—the challenge is translating that change into a medically defensible timeline.
Comparing pre-accident and post-accident information can be extremely valuable. But meaningful comparison involves far more than putting two MRI scans side by side. A careful evaluation considers historical imaging when it exists, previous symptoms, prior neurological findings, range-of-motion measurements, work abilities, everyday function, the mechanism of trauma, new objective examination findings, and how those findings evolve during recovery.
The central question is simple:
What changed after the accident?
You can often answer that question even without a detailed pre-accident spine examination.
A Hypothetical Patient: Daniel’s Lumbar Spine Before the Collision
Consider Daniel, a fictional 43-year-old El Paso warehouse supervisor.
Before his accident, Daniel occasionally noticed low-back stiffness after long shifts. He mentioned it once during a primary-care visit several years earlier but never had a lumbar MRI. No clinician had measured his lumbar flexion with an inclinometer. There were no documented reflex abnormalities, strength deficits, sensory changes, or radiating leg symptoms.
More importantly, Daniel was functioning.
He worked full duty.
He routinely walked across a large warehouse, climbed stairs, drove to work, lifted moderate loads, maintained his home, slept normally, and played recreational basketball with his teenage son.
No pre-accident MRI declares his spine “normal.”
There does not need to be.
His functional history forms part of his medical baseline.
That distinction becomes important because degenerative spinal findings are remarkably common in people without symptoms. A systematic review of 3,110 asymptomatic individuals found increasing rates of disc degeneration, bulging, protrusion, and other findings with age. For example, disc degeneration was reported in 37% of asymptomatic 20-year-olds and became progressively more common with age (Brinjikji et al., 2015).
Therefore, discovering degeneration on Daniel’s post-accident MRI would not automatically prove that his current pain, neurological symptoms, or functional restrictions existed before the collision.
Visit One: Establishing the Post-Accident Starting Point
Daniel is rear-ended while stopped in traffic.
During the collision, his torso is restrained while rapid acceleration and deceleration transmit forces through his trunk and spine. He does not lose consciousness and is able to leave the scene, but over the next several hours his low back becomes increasingly painful and stiff.
When he presents for evaluation, the clinician does not assume the crash caused every symptom.
The examination begins by documenting the timeline.
Questions include:
What happened during the collision?
Where did the body move?
When did the pain begin?
Did leg pain, numbness, tingling, or weakness develop?
Were similar symptoms present before the accident?
What could the patient do before that he cannot comfortably do now?
Were there previous accidents, back injuries, surgeries, or episodes of sciatica?
Are there warning signs suggesting fracture, cauda equina syndrome, infection, or another urgent condition?
This history creates the first layer of the causation analysis.
Measuring What Can Be Measured
Daniel’s examination then looks for findings that can be documented and compared later.
These may include:
Lumbar flexion, extension, rotation, and side bending
Gait and posture
Muscle strength
Deep-tendon reflexes
Sensory examination
Straight-leg-raise or other nerve-tension testing
Orthopedic testing
Palpation and muscular guarding
Functional movements such as sitting, standing, bending, or transitioning from a chair
Range-of-motion testing can help quantify movement loss, particularly when consistent measurement methods are used. However, restricted motion is not a fingerprint unique to trauma. Pain, guarding, degeneration, fear of movement, neurological disease, and other conditions can also reduce motion.
For that reason, range of motion supports the clinical picture but does not independently prove accident causation.
The same principle applies to neurological testing. Muscle weakness, altered sensation, diminished reflexes, or nerve-tension findings can provide important objective evidence of neurological involvement, but the clinician must still determine whether the findings are new, longstanding, worsening, improving, or attributable to another condition.
Dr. Jimenez’s clinical resource on lumbar radiculopathy discusses the importance of strength, sensation, reflexes, gait, and related neurological examination findings when nerve-root involvement is suspected. Lumbar Radiculopathy and Neurological Examination
Why Daniel Does Not Automatically Receive an MRI on Day One
Patients sometimes assume that a serious collision should automatically result in an MRI.
Current imaging guidance is more selective.
For uncomplicated acute low-back pain without red flags, routine early imaging is generally not recommended because many patients improve with conservative management, and imaging commonly identifies abnormalities unrelated to the patient’s symptoms. When significant trauma, progressive neurological findings, suspected fracture, cauda equina syndrome, or other clinical concerns are present, imaging decisions change accordingly (American College of Radiology, 2021).
This protects the patient from unnecessary testing while preserving access to advanced imaging when the clinical picture warrants it.
The clinic’s educational material similarly emphasizes matching X-ray, CT, or MRI selection to the suspected injury and clinical findings rather than treating imaging as an automatic step after every collision. Spine Trauma Imaging and Diagnostic Evaluation
Visit Two: Six Weeks Later, the Clinical Picture Has Changed
Daniel returns approximately six weeks later.
Some of the generalized muscular soreness has improved. However, his lumbar symptoms have not followed the same course.
He now describes pain extending from the lower back into one leg, intermittent tingling in his foot, and difficulty remaining seated for long periods.
He is still avoiding heavier lifting at work.
The new information matters.
His clinician repeats relevant portions of the examination rather than simply carrying forward the original findings.
Perhaps lumbar motion remains substantially restricted. Straight-leg raising reproduces familiar leg symptoms. The sensory exam identifies a reproducible difference in part of the affected leg. Strength, reflexes, and gait are carefully reassessed.
Now the chart contains something much more useful than two pain scores.
It contains a trajectory.
At the first visit, Daniel had primarily localized back pain and guarding.
By the second visit, persistent symptoms had developed a neurological pattern.
That progression may change the diagnostic question and justify additional evaluation.
When MRI Becomes More Informative
MRI is particularly useful for evaluating discs, nerve-related structures, the spinal canal, and many soft tissues.
If Daniel’s symptoms remain persistent or progressive and his examination suggests lumbar nerve-root involvement, a lumbar MRI may help determine whether a disc protrusion, stenosis, or another structural finding corresponds with the clinical pattern.
ACR criteria identify lumbar MRI without contrast as usually appropriate in selected patients with persistent or progressive symptoms who may be candidates for further intervention after appropriate conservative management.
The key phrase is clinical correlation.
An MRI is evidence.
However, the MRI does not provide a complete causation analysis.
What Happens If the MRI Shows Degeneration?
Suppose Daniel’s MRI identifies degenerative disc changes and an L4-L5 disc protrusion near a nerve root.
An insurer might focus on one word:
Degenerative.
But medically, the interpretation requires more nuance.
Degenerative findings commonly occur in people who have no back pain whatsoever. Brinjikji and colleagues found substantial rates of disc degeneration, bulging, protrusion, annular fissures, and other findings among asymptomatic individuals (Brinjikji et al., 2015).
That means an MRI should not be interpreted in either extreme.
A clinician should not automatically say:
“The degeneration proves the accident had nothing to do with the symptoms.”
Nor should the clinician say:
“Everything visible on this MRI was caused by the accident.”
Both statements may exceed what the evidence can establish.
A more defensible question is:
Does the imaging finding fit the patient’s post-accident symptoms, examination findings, neurological distribution, mechanism of injury, prior history, and clinical progression?
The clinic’s current causation guidance makes precisely this distinction: prior degeneration may be relevant, but it does not automatically explain new neurological findings or post-accident functional losses. Understanding Causation in Chiropractic and Injury Care
What If Daniel Actually Has an Old MRI?
Now imagine a better-than-reconstructed baseline exists.
Daniel underwent an MRI five years earlier after briefly straining his back while moving furniture.
That imaging can be extremely valuable.
A qualified clinician or radiologist may compare:
Previously documented disc degeneration
Disc contour and location
Herniation or protrusion findings
Canal or foraminal narrowing
Vertebral changes
Previous nerve-root involvement
Other structural abnormalities
But even side-by-side imaging has limitations.
Different scanners, imaging sequences, patient positioning, slice thickness, technical quality, interpretation, and the time between examinations can influence what appears on a study. Imaging also does not directly measure pain.
Most importantly, a preexisting structural abnormality can remain anatomically similar while its clinical consequences change.
For example, an old MRI may show an L4-L5 bulge in a patient who previously had no leg symptoms, normal strength, unrestricted work capacity, and no treatment requirements.
After a collision, that patient may develop radiating leg pain, altered sensation, reduced lifting tolerance, and examination findings consistent with nerve irritation.
The causation question is therefore not limited to:
“Was this disc abnormality already there?”
It may instead become:
“Did the traumatic event materially aggravate a previously stable or asymptomatic condition?”
That is a different medical question.
When There Is No Pre-Accident MRI—and Usually There Isn’t
Most personal injury patients do not arrive with a complete pre-collision dataset.
Acknowledge that absence rather than fill it with assumptions.
Clinicians can often reconstruct a reasonable baseline from multiple sources:
Primary-care records
Previous chiropractic or rehabilitation records
Earlier emergency department visits
Prescription history
Prior imaging when available
Previous work restrictions
Employment duties
Sports and exercise participation
Activities of daily living
Previous complaints of back or leg pain
Prior neurological symptoms
Earlier accidents or injuries
The patient’s own consistent history
No single piece establishes the entire baseline.
Together, however, they may answer the practical question of what the patient could do before the collision.
A person who worked unrestricted construction for years before an accident presents a different baseline than someone who was already unable to work because of chronic lumbar radiculopathy.
Thorough medical documentation should preserve that distinction, not erase it.
Visit Three: Recovery Becomes Another Source of Evidence
Daniel returns for another comprehensive re-examination several weeks later.
His lumbar motion has improved. Walking is easier.
He is sleeping longer.
His leg symptoms occur less frequently, and he can sit for longer periods before discomfort develops.
He is not fully recovered, however.
Heavy lifting still reproduces low-back and leg symptoms.
This third examination provides additional information.
Progress examinations allow clinicians to compare:
Visit 1: acute post-traumatic symptoms and measurable movement restriction.
Visit 2: persistent symptoms with new or clarified neurological findings.
That timeline can be more persuasive medically than a chart that simply repeats “back pain 7/10” at every appointment.
The clinic’s documentation guidance recommends following measurable factors such as range of motion, neurological status, sleep, walking or sitting tolerance, lifting capacity, work ability, and activities of daily living across successive re-examinations. Defensible Medical Injury Documentation Best Practices
Functional Baselines Matter Because Injury Is More Than an MRI Finding
For patients, one of the most important concepts is also one of the simplest:
Function matters.
Before the collision, could you:
Work an eight-hour shift?
Drive without needing frequent breaks?
Lift your child?
Exercise?
Sleep through the night?
Bend to put on shoes?
Carry groceries?
Sit through a meeting?
Walk several blocks?
Perform household maintenance?
What can you do now?
A person’s inability to perform an activity does not, by itself, identify the injured tissue. But when functional loss develops immediately after a plausible traumatic mechanism and corresponds with examination findings, neurological changes, imaging, and subsequent clinical progression, it becomes an important component of the overall analysis.
This is why personal injury documentation should capture both anatomy and lived function.
Clinical Causation Is Built From Converging Evidence
A medically supportable causation opinion rarely rests on a single finding.
It becomes stronger when several independent pieces of evidence point in the same direction:
Mechanism: Were the forces capable of loading the involved tissues?
Temporality: Did symptoms begin or materially worsen after the event?
Baseline: What symptoms and limitations existed beforehand?
Objective examination: Are there reproducible orthopedic, neurological, movement, or functional findings?
Imaging: Do clinically indicated studies identify abnormalities that fit the presentation?
Anatomic correlation: Does the location of a structural finding reasonably correspond with the neurological or mechanical pattern?
Alternative explanations: Are degeneration, previous injuries, systemic disease, subsequent accidents, or other factors more persuasive explanations?
Clinical course: Does the patient’s evolution over time make sense for the working diagnosis?
No individual MRI, range-of-motion measurement, orthopedic test, or pain score automatically establishes causation.
What matters is consistency across the entire record.
That distinction matters, especially for attorneys. A healthcare professional can address medical causation and explain whether trauma is medically consistent with a new injury or aggravation. Ultimate legal questions concerning proximate cause, damages, and liability remain matters for counsel and the fact-finder.
Conservative Recovery Should Serve the Patient First
Careful documentation is not merely to create evidence.
It is to guide appropriate treatment.
When serious pathology has been excluded, and conservative care is appropriate, management may incorporate chiropractic care, carefully selected manual or soft-tissue approaches, progressive rehabilitation, mobility work, therapeutic exercise, and other non-invasive modalities based on the patient’s diagnosis and tolerance.
Exercise and movement-based rehabilitation have an established role in many low-back-pain presentations, although treatment should be individualized rather than applying one protocol to every patient (George et al., 2021).
For appropriate patients, an integrated clinic may also consider acupuncture, electroacupuncture, and other supportive modalities as part of a broader plan.
The goal is not simply to lower a pain score.
Meaningful gains include improved mobility, better sleep, greater confidence in movement, increased walking and sitting tolerance, return to work or family activities, and recovery of as much normal function as medically possible.
This reflects beneficence: treatment should serve the patient’s recovery.
It also reflects non-maleficence. When clinically appropriate, conservative and non-invasive strategies may allow recovery without immediately escalating to higher-risk procedures or unnecessary medication exposure.
And it supports autonomy. Patients should understand what their examinations show, what uncertainties remain, why testing is—or is not—being ordered, and what treatment alternatives are available so that they can make informed decisions alongside their existing healthcare team.
What Makes Dr. Jimenez’s Integrated El Paso Clinic Different?
Injury Medical Clinic PA, also known as Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic, uses a multidisciplinary structure designed to address both the mechanical and medical dimensions of injury recovery.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, is dual-licensed as a Doctor of Chiropractic and board-certified Family Nurse Practitioner/Advanced Practice Registered Nurse. His work includes musculoskeletal and soft-tissue injury assessment, neurological screening, diagnostic coordination, chiropractic physical medicine, rehabilitation, and broader medical evaluation within his licensed scope.
Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of clinical experience, serves as medical director and collaborative physician. The clinic lists Texas License #J2933 and NPI #1164426748 for Dr. Cardenas, and Texas APRN/FNP License #1191402 and NPI #1205907805 for Dr. Jimenez.
According to the clinic’s published materials, Injury Medical Clinic PA describes itself as the only El Paso practice combining this board-certified medical-director oversight with Dr. Jimenez’s dual DC/APRN-FNP soft-tissue injury role within its integrated personal-injury model.
For an injured patient, the practical benefit is coordination. A connected clinical framework can consider structural examination, neurological screening, medical risk assessment, imaging decisions, conservative treatment, rehabilitation, and referral decisions as one system rather than unrelated pieces of care.
The Most Important Comparison May Not Be Two MRIs
Daniel’s case shows why “before and after” should mean more than radiology.
There may be no pre-accident MRI.
There may be no old range-of-motion measurement.
Mild degeneration may have existed for years.
None of those facts automatically answers the causation question.
A careful clinician instead reconstructs the best available baseline, documents the post-traumatic presentation, performs repeat examinations when appropriate, investigates evolving neurological findings, orders imaging for a clinical reason, considers alternative explanations, and follows the patient’s recovery over time.
The resulting medical story may look like this:
Before: occasional stiffness, no radicular symptoms, full-duty employment, and normal everyday activity.
Immediately after trauma: new lumbar pain, guarding, movement loss, and reduced function.
Six weeks later: persistent limitations with a developing neurological pattern.
After further evaluation and care: objective and functional improvement, with clearly identified residual limitations.
That is a far more complete picture than saying, “The MRI shows a disc problem.”
For patients, it explains why repeated examinations matter.
For attorneys, it creates a chronological record in which medical reasoning can be examined rather than merely asserted.
And for clinicians, it keeps the most important priority where it belongs: determining what changed, why it changed, and what can safely help the patient recover.
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. Systematic Literature Review of Imaging Features of Spinal Degeneration in Asymptomatic Populations
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. Low Back Pain Clinical Practice Guideline
Educational content only. Individual imaging, treatment, causation, and legal questions require evaluation of the patient’s specific clinical record and circumstances.
Cervical Contributions to Chronic Migraine and How Guideline-Based Botox Complements Structural Care
After a low-speed rear-end collision on Loop 375, Elena noticed her neck stayed tight even after the initial soreness faded. Within weeks, the headaches that once arrived a few times a month now filled most of her calendar. Turning her head to assess a blind spot, sitting through a long meeting, or simply waking with stiff shoulders seemed to launch the next attack. Like many people in El Paso whose migraines intensify after injury or with ongoing neck tension, she discovered that the cervical spine and the upper-shoulder muscles can feed the same pain pathways that drive chronic migraine. Addressing both the structural findings and the preventive injection map used in guideline-based Botox care can reduce the total burden when neither approach is used alone.
Neck pain appears in a large share of people who live with migraine, and the overlap is not random. Sensory nerves from the upper cervical joints, discs, ligaments, and deep muscles converge with trigeminal pathways inside the trigeminocervical complex. Ongoing mechanical irritation or muscle guarding in the neck can therefore add extra input to networks already sensitized in migraine. After trauma—whiplash-type forces, abrupt deceleration, or repeated postural load—the same structures may show restricted motion, segmental stiffness, or altered disc height that keeps the input elevated. Cervical paraspinal muscles, the suboccipital group, and the upper trapezius often carry tender points that patients recognize as where their headaches begin or linger.
The Phase III Research Evaluating Migraine Prophylaxis Therapy (PREEMPT) trials established a fixed-site, fixed-dose injection pattern that remains the FDA-approved framework for onabotulinumtoxinA in chronic migraine (typically defined as 15 or more headache days per month). The full protocol places 155 units across 31 sites in seven muscle groups. Three of those groups sit precisely in the regions Elena and many others describe as sources of tension:
Occipitalis receives six sites (three per side) for 30 units, positioned near the external occipital protuberance.
Cervical paraspinal muscles receive four sites (two per side) for 20 units, placed a short distance below the occipital ridge and lateral to the midline.
Trapezius receives six sites (three per side) for 30 units along the upper portion of the muscle from the base of the neck toward the shoulder.
Optional “follow-the-pain” sites may add up to 40 more units when tenderness is prominent, bringing the total as high as 195 units. These posterior injections do not “freeze” the muscles in a cosmetic sense; they reduce the release of pain-signaling chemicals from peripheral nerve endings, which can lower the drive that reaches the trigeminocervical complex. Because the same muscles and nearby joints are often examined during a structural evaluation, you can review the injection map and cervical findings together rather than in isolation.
A practical assessment begins with the patient’s own timeline: when neck stiffness or reduced turning first appeared relative to the rise in headache days, and whether certain postures or movements reliably precede an attack. Range-of-motion measurements, segmental motion testing, and palpation of the occipitalis, paraspinals, and trapezius identify areas of restriction or tenderness that overlap the PREEMPT landmarks. When imaging or prior records show disc changes or segmental findings at upper or mid-cervical levels, those details are noted so the structural plan can address mobility and load without assuming every radiographic change drives migraine alone. The goal is clarity for the patient: which findings are being treated with alignment and soft-tissue work, which sites will receive the standardized Botox doses, and how the two will be timed across the typical 12-week injection cycle.
Structural care focuses on restoring usable motion and reducing unnecessary muscle guarding. Gentle mobilization or adjustment of restricted segments, soft-tissue work along the paraspinals and trapezius, and progressive loading exercises help the neck tolerate daily positions with less protective tension. Patients often notice smoother head turning and reduced baseline tightness between the shoulder blades. When these changes occur alongside fewer headache days after the first or second Botox cycle, the combined effect supports both fewer attacks and greater confidence in everyday movement. Sleep can improve because the neck no longer forces a guarded posture through the night, and the need for rescue medication may decline as the overall frequency drops.
Beneficence is served when both approaches work toward the same outcome: fewer disabling headache days and a better ability to move, work, and rest. The structural work addresses mechanical contributors that can feed the pain system, while the guideline-based injections dampen peripheral signaling in the exact regions patients identify as tender. Non-maleficence favors starting with these non-surgical options. Careful screening for red flags, precise injection technique, and graded mobility work reduce the chance that a patient will move prematurely toward more invasive procedures or long-term reliance on daily preventive medications. Autonomy is protected when the patient understands both the injection sites—occipitalis, cervical paraspinals, and trapezius—and the concurrent alignment plan. Clear explanations of what each treatment targets, how progress will be measured (headache-day counts, range of motion, and functional tolerance), and how the schedule will be adjusted let the patient remain the decision-maker while coordinating with any existing medical team.
What makes Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic unique is its medical director, Dr. Maria Guadalupe Cardenas, MD, along with a dual-licensed nurse practitioner who specializes in soft-tissue injury. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, evaluates cervical motion, segmental findings, and soft-tissue contributions while coordinating with Dr. Cardenas on overall medical direction. This integrated model is the only clinic in El Paso, Texas, that provides these combined structural and guideline-based preventive treatments under one coordinated team. Patients receive both hands-on assessment of disc and joint factors and the standardized PREEMPT injection pattern without shuttling between separate offices for each element of care.
Further detail on how cervical findings and headache patterns are documented appears in the integrated migraine treatment resources and the causation framework available at dralexjimenez.com. Related discussions of neck pain, whiplash mechanics, and functional recovery after injury appear in the clinic’s guides on cervical contributions to headache and on establishing clear clinical timelines. Integrated structural and preventive documentation appears in the medical-legal causation framework at https://dralexjimenez.com.
When neck tension and chronic migraine travel together, examining the cervical muscles and joints alongside the PREEMPT map gives a practical way to match treatment to the tissues that are actually contributing. Structural work restores motion and reduces guarding; guideline-based Botox lowers the peripheral drive from the same regions. Together, they support fewer headache days, easier daily movement, and a clearer plan the patient can understand and use to guide care.
References
Al-Khazali, H. M., Younis, S., Al-Sayegh, Z., Ashina, S., Ashina, M., & Schytz, H. W. (2022). Prevalence of neck pain in migraine: A systematic review and meta-analysis. Cephalalgia, 42(7), 663–673. https://doi.org/10.1177/03331024211068073
Blumenfeld, A., Silberstein, S. D., Dodick, D. W., Aurora, S. K., Turkel, C. C., & Binder, W. J. (2010). Method of injection of onabotulinumtoxinA for chronic migraine: A safe, well-tolerated, and effective treatment paradigm based on the PREEMPT clinical program. Headache: The Journal of Head and Face Pain, 50(9), 1406–1418. https://doi.org/10.1111/j.1526-4610.2010.01766.x
Headache Classification Committee of the International Headache Society (IHS). (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. https://doi.org/10.1177/0333102417738202
Sterling, M., Jull, G., & Vicenzino, B. (2019). Whiplash-associated disorders and post-traumatic headache. In Textbook of neuromodulation and physical medicine (related clinical reviews on cervical contributions after trauma).
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine