The Server-Rack Crouch: How Mid-Back Stiffness, Hip Restriction, and Awkward Reaching Overload the Lumbar Spine
Abstract: Data center technicians and network engineers crouch behind racks, kneel on hard floors, pull cables, and lift gear in tight aisles. When the mid-back cannot rotate, and the hips cannot flex well, the lumbar spine takes on extra bend, twist, and shear. This article maps that kinetic chain, shows what a structural exam should measure, and outlines alignment, mobility work, mechanical rehab, lifting strategy, and spinal decompression to keep a mechanical problem from becoming a disc or nerve injury.
The job does not look like heavy construction. You slide a switch into a dim rack, kneel to dress fiber, and then stand when a ticket hits. By day three, the low back feels thick and unreliable. Calling that “bad posture” does not tell you what to change.
The real issue is load sharing. The lumbar spine is built to carry compression and resist excess rotation. It is not built to supply the turn your mid-back should provide, or the hip bend your hips should provide, while you also reach and lift. When those neighbors stiffen, the low back becomes the available joint—and available joints get overloaded.
The Kinetic Chain Behind the Rack
Treat the trunk as a three-part system.
The thoracic spine and rib cage should rotate and extend so the arms can reach without dragging the pelvis.
The hips should flex and extend so you can drop or rise without folding the lumbar discs to their end range.
The lumbar spine should stay relatively stable while those two regions move.
When thoracic rotation is limited, the trunk borrows from the lumbar segments. Mobilizing restricted thoracic joints increases thoracic rotation and reduces lumbar rotation during the same turn (Yasuda et al., 2023). Modeling also shows that a stiffer thoracic spine raises lumbar disc stress and L5 pars stress (Morimoto et al., 2024). That is the server-rack crouch: you rotate to see a port, the ribs do not turn, and L4–L5 or L5–S1 supplies the missing degrees.
Hip restriction writes the same story in the sagittal plane. If hip flexion is short, a squat or kneel-to-stand uses extra lumbar flexion. Available hip flexion is linked to how much the lumbar spine flexes during a squat lift (Patterson et al., 2022). People with poorer hip and lumbar mobility also place higher bending stress on the spine during everyday lifts (Dolan & Adams, 1993). On the floor, this means hinging to pick up a box rather than rounding through the belt line.
Awkward reaching multiplies both problems. A reach around a rack post is flexion plus rotation plus a long lever. Confined-space research shows spinal load stays high in restricted height, though kneeling can cut shear compared with stooping because the trunk can stay more upright (Weston et al., 2020). Behind a rack, you often experience the worst mix: a stooped torso, rotated shoulders, and a load at arm’s length, then a sudden stand.
Why This Pattern Progresses
A single shift rarely herniates a disc. The pattern does. Repeated end-range lumbar flexion and rotation under load stress the annulus, facets, and ligaments. Over months, you may notice morning stiffness, a catch when standing from a kneeling position, or buttock pain after a long pull. Those are mechanical warnings. If the segment keeps moving past its useful range while a disc is already irritated, nerve roots can become inflamed. That is a load problem, not “tight muscles.”
What a Structural Assessment Should Measure
A useful exam maps missing motion and excess motion.
Mid-back and rib cage
Seated and quadruped thoracic rotation with the pelvis held still
Thoracic extension, watching for lumbar substitution
Rib and segmental joint play through the levels used in reaching
Hips and pelvis
Hip flexion, extension, and rotation
Hip-hinge quality from standing and from a half-kneel
Pelvic control during sit-to-stand and floor-to-stand
Lumbar spine and nerves
Segmental motion and tenderness
Repeated-movement testing to see whether flexion or extension changes symptoms
Nerve tension signs if pain or tingling travels below the knee
Imaging and a neurologic exam when weakness or progressive numbness appears
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, uses that map with medical screening. Dual licensure lets structural findings sit next to a review of inflammation and medication risk. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, provides collaborative oversight so care stays coordinated with your existing medical team. That is beneficence: the plan exists to protect the disc and the person.
Alignment First: Restore the Joints That Should Move
If the mid-back is locked and the hips are stiff, adjusting only the sore lumbar joints may provide temporary relief, but the improvement often fades by the next session.
Alignment at El Paso Back Clinic restores motion where it belongs:
Thoracic and rib work to return rotation and extension to the cage
Pelvic and hip work so the femur can flex without flattening the lumbar curve
Specific lumbar adjustments after neighboring regions can share load
Patients keep autonomy here. You should know which joint is being treated, why, and how you’ll measure change at the next visit.
Non-maleficence sits in the same step. Skilled, non-invasive adjustments and graded loading can reduce the rush toward long-term medication or surgery while the problem is still mechanical. Surgery has a place for true neurologic emergencies. Most back problems become that case only after the same compensation runs for years.
Mobility Restoration You Can Own
Clinic work does not replace the shift.
Thoracic rotation in a half-kneel, ribs turning, pelvis quiet
Hip-flexor length after long kneeling, so standing does not yank the lumbar spine
Hip-hinge rehearsal so the crease is at the hips, not at the belt
Ankle motion, because a stiff ankle forces an extra lumbar fold when you drop
Short sessions beat heroic stretching after the damage is done. Two minutes before a rack walk and two minutes after is a plan most crews can keep.
Mechanical Rehabilitation and Lifting Strategy
Mobility without strength leaves a new joint unprotected.
Hip-dominant hinges and split-stance pulls so the glutes lift the torso
Anti-rotation holds so the lumbar spine can resist twist while the arms reach
Tall-kneeling and half-kneeling work that mirrors floor-to-stand cable tasks
Gradual loading of lift height and mass so the hips take the extra demand
Lifting rules:
Get the load close before it leaves the floor or the cart
Turn the feet instead of twisting the belt line
Prefer a kneel with an upright trunk over a full stoop when the aisle is low
Split the task: slide, then lift, then turn
Use a partner or lift aid for awkward chassis
Confined work will never be perfect. The goal is fewer cycles at end-range lumbar flexion and twist.
When Spinal Decompression Belongs in the Plan
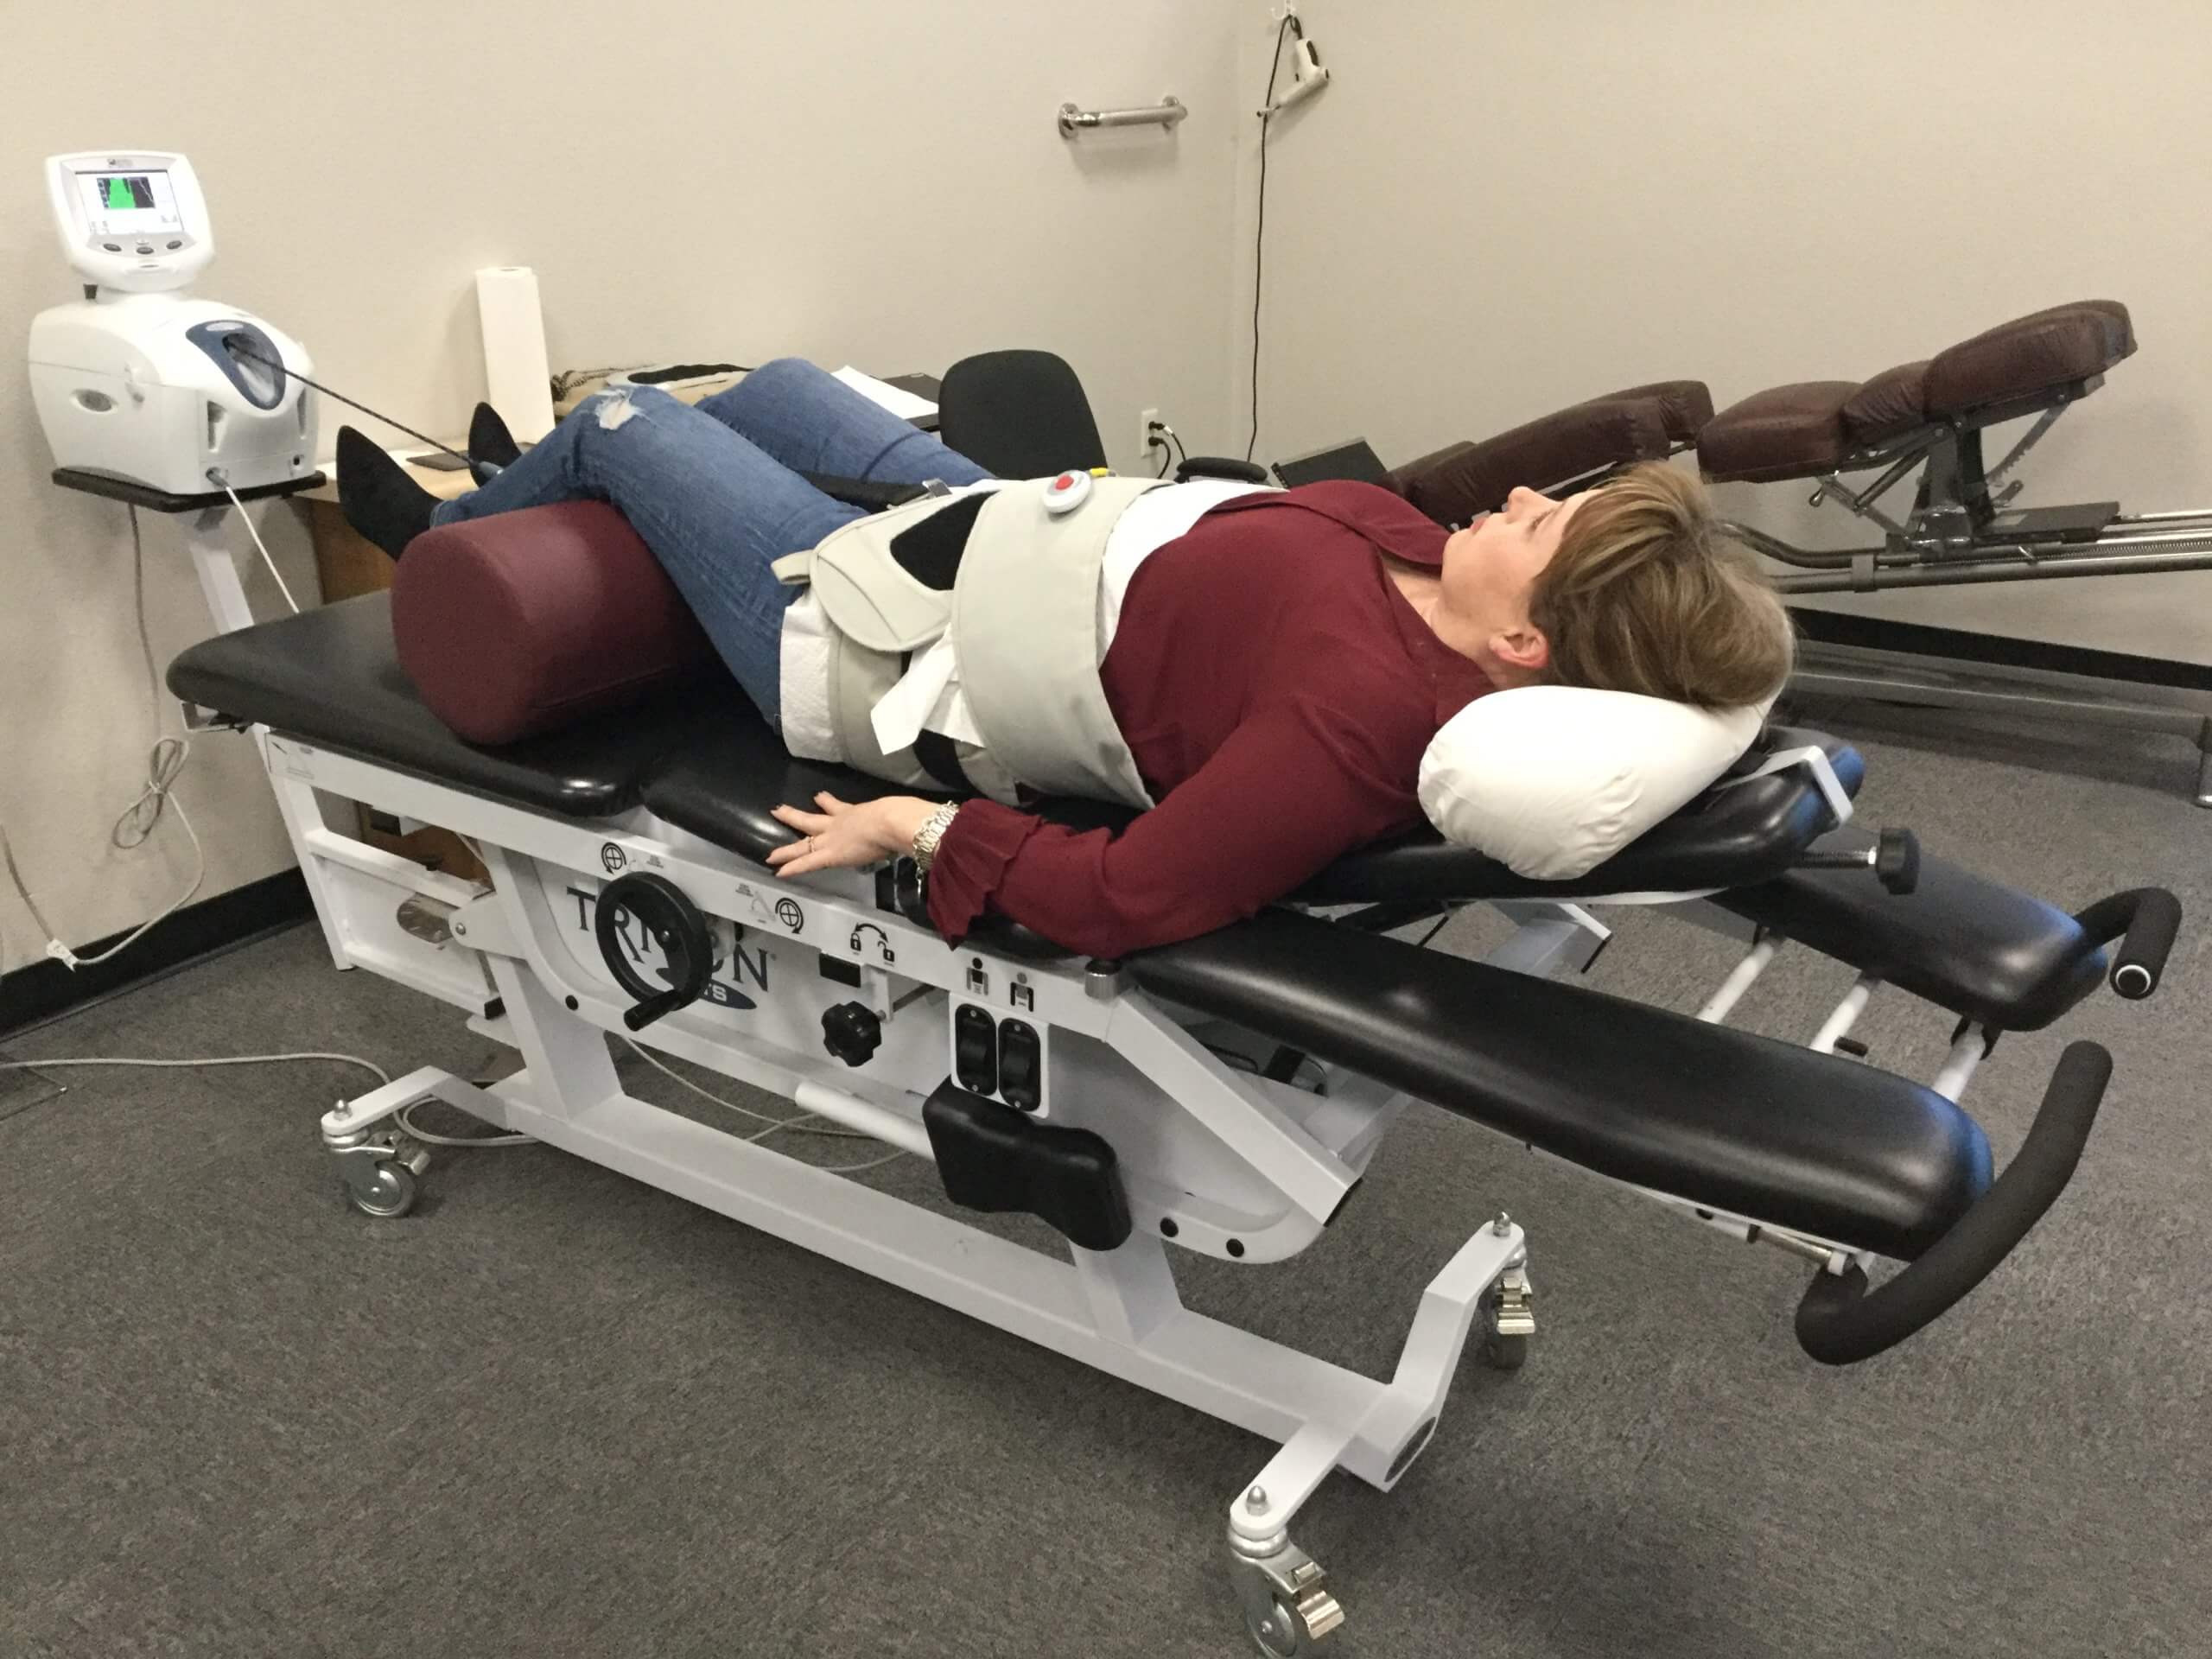
If the disc is already irritated, alignment and exercise may not be enough in the first weeks. Non-surgical spinal decompression uses controlled traction to reduce load on an injured disc while you rebuild the kinetic chain. In lumbar radiculopathy, adding decompression to routine physical therapy improved pain, lumbar motion, endurance, and disability more than therapy alone over four weeks (Amjad et al., 2022).
Decompression is not a substitute for finding the stiff thorax or the restricted hip. It is a tool to calm a loaded segment so those corrections can stick. At Injury Medical Clinic PA in El Paso, decompression is paired with alignment and, when indicated, medical review by Dr. Cardenas so inflammation and nerve status are not ignored.
A Direct Plan for the Next Cutover
If your low back catches when you stand from behind a rack, treat it as a mechanical diagnosis.
Get a structural exam that measures thoracic rotation, hip motion, and lumbar control.
Restore motion to the mid-back and hips, then protect the lumbar segments.
Rebuild hinge strength and anti-rotation capacity for kneeling and reaching.
Change the lift: closer load, feet turn first, upright kneel in a low aisle.
Use decompression when disc or nerve signs are present, under a plan you understand.
You remain the decision-maker. Integrative care at El Paso Back Clinic is designed to work with your current physicians, not around them. The aim is simple: keep the lumbar spine from doing a job it was never meant to do.
Reversing Severe Lumbago and Disc Compression from Amazon Fulfillment Shifts
Abstract: Severe low-back pain after fulfillment work or delivery routes can feel like a one-way road toward surgery. Yet many cases deserve a careful conservative evaluation first. This guide explains how repetitive bending, sorting, vehicle vibration, and lifting can aggravate lumbago and disc-related pain; where mechanical alignment and selected non-surgical decompression may fit; how medical oversight screens red flags; and how Amazon workers can use practical lifting limits to reduce repeat flares.
When a Shift Starts Loading the Lumbar Spine
A warehouse associate may begin a shift feeling stiff. Hours later, repeated low-bin reaches, package twisting, sorting, pallet work, or lifting away from the body can turn stiffness into severe lumbago. Delivery drivers add prolonged sitting, road vibration, repeated cabin exits, carrying, and awkward curbside lifts.
The problem is often cumulative. When the trunk bends and rotates while a load stays away from the body, spinal muscles must generate more force to control movement. Repetition can fatigue those tissues and degrade movement quality. NIOSH treats load weight, reach distance, vertical height, twisting, lifting frequency, duration, and grip quality as factors that change lifting risk (NIOSH, 2024).
That matters because “safe lifting” is not one universal number. A box manageable at waist height may be too demanding on the floor, far from the body, poorly gripped, or lifted repeatedly near the end of a long shift.
Why Pain Can Spike After the Shift
Symptoms may intensify after clocking out because fatigued muscles provide less support, sitting stiffens the hips, and irritated tissues remain sensitive after repeated loading. Delayed soreness doesn’t mean a disc suddenly worsened. Track which movements, loads, positions, and recovery habits consistently increase or decrease symptoms across workdays.
What “Disc Compression” Really Means
Between the lumbar vertebrae, intervertebral discs distribute load and allow movement. A disc is not a jelly doughnut that simply pops out and can be pushed back into place. It is a load-bearing structure with a fibrous outer ring and softer inner region. Repeated flexion, compression, rotation, aging, prior injury, and anatomy can contribute to disc changes.
Pain may come from several overlapping sources:
Irritated lumbar joints or surrounding soft tissues
Protective muscle spasm and reduced hip motion
Disc-related inflammation or mechanical sensitivity
A disc herniation that irritates a nerve root
Deconditioning after repeated pain episodes and activity avoidance
This is why a structural examination matters. The goal is to match symptoms with movement findings, neurologic testing, work demands, and imaging when indicated. Low-back guidelines support exercise, education, and selected manual or mobilization approaches as part of conservative care rather than a single passive treatment (George et al., 2021).
Step One: Restore Motion Without Forcing the Spine
At El Paso Back Clinic, targeted mechanical care begins with a practical question: which movements are limited, painful, unstable, or poorly coordinated?
One worker may have stiff hips that force repeated lumbar bending. Another may have painful lumbar joints that limit extension. A driver can show a different pattern after hours of seated flexion and vibration.
Chiropractic adjustments and non-thrust joint mobilization may improve mobility and reduce pain when the examination supports them. Guidelines report benefit from joint mobilization for many people with chronic low-back pain, including some with leg symptoms (George et al., 2021). Care should pair manual treatment with rehabilitation so improved motion becomes usable strength.
The Functional Target
The patient gains something measurable: easier standing, smoother walking, less guarded bending, better sleep positions, safer transitions from a delivery van, and more confidence handling daily tasks. Those functional gains matter more than trying to make every spinal image look “perfect.”
Step Two: Use Non-Surgical Decompression Carefully
Non-surgical spinal decompression is commonly described as controlled lumbar traction or unloading. The practical aim is to reduce mechanical stress temporarily and create a position in which painful tissues or irritated nerve roots may become less sensitive.
The evidence requires precision. A systematic review found short-term improvements in pain and disability when certain mechanical traction forms were added to treatment for lumbar radiculopathy, but study quality and results varied (Vanti et al., 2021). WHO guidance for chronic primary low-back pain advises against routine traction for most patients, so decompression should not become an automatic protocol for every painful back (World Health Organization, 2023).
For a selected patient, decompression may be one tool within movement retraining, strengthening, work modification, and medical evaluation. It should never be sold as a guaranteed way to “reinflate” a disc or permanently reverse degeneration.
Preventing Unnecessary Surgery Without Delaying Necessary Surgery
Avoiding surgery is valuable when recovery is safe with conservative care. Lumbar discectomy can be appropriate for selected patients, yet it still carries risks such as recurrent herniation, wound complications, dural tears, reoperation, and neurologic complications (Bombieri et al., 2022).
The safer message is not “never have surgery.” It is “earn the decision with the right evaluation.” Recent spine recommendations support surgery when conservative treatment fails and emphasize urgent or early surgery for cauda equina syndrome or progressive severe neurologic deficits (Costa et al., 2024).
Seek urgent assessment for new bowel or bladder dysfunction, saddle-region numbness, rapidly worsening leg weakness, or serious neurologic changes. Fever, major trauma, unexplained weight loss, or concern for infection, fracture, or cancer also deserves prompt review.
This is non-maleficence in practice: use the least invasive reasonable option when it is safe, but never let a desire to avoid surgery delay care for a true emergency.
Step Three: Set Proactive Lifting Limits
For Amazon associates, prevention must survive the workday. “Lift with your legs” is not enough.
Use these rules:
Bring the package close before standing up.
Turn with the feet instead of twisting under load.
Reduce load size when the object starts low, high, or far away.
Use team lifting or mechanical assistance for demanding or awkward items.
Break up repeated lifting when possible with task rotation or brief recovery periods.
Stop treating pain as a test of toughness; a changing neurologic symptom deserves evaluation.
The Revised NIOSH Lifting Equation is useful because it does not assume every worker should lift the same weight in every position. It calculates a recommended weight limit using task conditions and a lifting index that reflects physical demand. NIOSH recommends keeping the lifting index or composite lifting index at or below 1.0 when evaluating two-handed lifting tasks (NIOSH, 2024).
Integrated Oversight: Structure, Medicine, and Patient Choice
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural alignment, mechanical rehabilitation, and advanced medical diagnostics. He holds Texas Advanced Practice Nursing License #1191402, Prescriptive Authority #59628, and NPI #1205907805. His dual licensure lets the clinic coordinate musculoskeletal examination with broader medical assessment and appropriate advanced interventions.
Dr. Maria Guadalupe Cardenas, MD, is Board Certified in Internal Medicine, has more than 40 years of experience, and holds Texas Medical License #J2933 and NPI #1164426748. As Medical Director, Clinical Director, and Collaborative Physician at Injury Medical Clinic PA in El Paso, she provides internal medicine oversight, risk stratification, interpretation of indicated laboratory tests, and comorbidity coordination.
That collaboration supports beneficence: the plan centers on the patient’s best functional outcome. It supports non-maleficence by screening for medical risks before aggressive treatment and using non-invasive, drug-sparing options when appropriate. It also protects autonomy. Patients are taught what the examination shows, what each option can and cannot reasonably do, and when another specialist or their existing medical team should be involved.
A Better Goal Than “Toughing It Out”
Severe lumbago after warehouse or delivery work is not a character test. The goal is to interrupt the overload cycle before pain, guarding, deconditioning, and poor mechanics reinforce one another.
A conservative plan can include targeted joint care, selected decompression, progressive trunk and hip rehabilitation, work-specific lifting education, and medical oversight. The target is direct: more comfortable movement, safer lifting, better sleep, and the ability to work without organizing each day around the next flare.
Multidisciplinary Call to Action
If repeated bending, sorting, driving, or lifting causes severe low-back pain, start with a coordinated evaluation. El Paso Back Clinic can assess mechanical function, neurologic findings, lifting demands, and medical risks, then explain conservative options and when to refer. Bring your imaging, medication list, job demands, and questions. The final decision remains yours, supported by clear information and coordinated chiropractic and medical care.
Severe Low Back Pain in Amazon Fulfillment Workers: Epidural Injections, Spinal Decompression, and the Treatment Window
Abstract: Severe low back pain can turn a 10-hour fulfillment shift into a battle. Repeated low-bin reaching, standing, twisting, and handling can keep an irritated lumbar nerve from settling. This article explains a function-first strategy: “turn down the fire, then address the load.” When true lumbar radiculopathy is present, an appropriately selected epidural injection may reduce acute nerve inflammation enough to create a treatment window for nonsurgical spinal decompression, mechanical chiropractic care, rehabilitation, and safer work habits. The goal is not temporary numbness. It is restoring movement while addressing the forces that keep symptoms returning.
A picker starts the shift moving quickly: scan, reach, bend, pull, pivot, walk, repeat. By hour seven, a familiar ache becomes sharper. By hour ten, standing upright hurts, the leg may burn, and getting into the car feels harder than moving another tote.
NIOSH identifies heavy physical work, lifting, forceful movement, bending, twisting, and static postures as recognized risk factors for low-back musculoskeletal disorders (National Institute for Occupational Safety and Health [NIOSH], 2024). For fulfillment workers, the problem is cumulative exposure. Low bins encourage trunk flexion, rushed reaches add rotation, and long hours on concrete floors magnify fatigue. Once pain changes how you move, compensation can load the hips, pelvis, and opposite side of the back.
The Key Question: Is the Fire in the Back or the Nerve?
Not every severe backache needs an injection. The first step is to identify what is irritated.
Localized lumbar pain may come from muscles, joints, discs, or other structures. Radicular pain is different. It can occur when a lumbar nerve root becomes irritated or compressed and may produce:
Burning or electric pain into the buttock or leg
Numbness or tingling
Pain that travels below the knee
Weakness in the foot or leg
Symptoms that worsen with certain spinal positions, coughing, or straining
A careful examination should assess strength, reflexes, sensation, movement tolerance, nerve tension, gait, and symptom patterns. Imaging may be appropriate when findings suggest significant disc injury, persistent neurologic symptoms, trauma, or when results would change treatment.
New loss of bowel or bladder control, saddle numbness, rapidly worsening weakness, fever with severe back pain, or major trauma requires urgent medical evaluation. These symptoms are not ones you can just “work through.”
Turn Down the Fire, Then Fix the Load
Think of an irritated lumbar nerve like a fire alarm beside a hot engine. If inflammation is high enough, even small movements can trigger intense pain. The worker may stop bending normally, brace every step, sleep poorly, and avoid rehabilitation because almost everything hurts.
That is where the treatment-window concept matters.
For appropriately selected lumbar radiculopathy, an epidural corticosteroid injection can place anti-inflammatory medication near the affected nerve root. A 2025 American Academy of Neurology review found that epidural steroid injections probably reduce short-term pain and disability in radiculopathy, while long-term pain benefit remains uncertain (Armon et al., 2025).
In plain language: the injection is not rebuilding a disc or correcting lifting mechanics. It may turn down the inflammatory “fire” long enough to make useful movement possible.
That window matters when pain blocks progress. A worker who could not tolerate walking, traction, unloading, or stabilization may gain enough control to begin them.
What an Epidural Injection Can—and Cannot—Do
A properly indicated epidural may help:
Reduce acute radicular pain
Improve tolerance for walking and sleep
Make rehabilitation easier to participate in
Allow a graded return to mechanical treatment
Reduce reliance on passive coping alone
It does not guarantee permanent relief, prevent surgery in every case, or address occupational loading patterns on its own. The AAN review found insufficient evidence that epidural steroid injections reduce the eventual need for surgery (Armon et al., 2025).
There are also risks. The FDA notes rare but serious neurologic complications associated with epidural corticosteroid injections and states that corticosteroids are not FDA-approved specifically for epidural administration (U.S. Food and Drug Administration [FDA], 2014). That makes informed consent, patient selection, appropriate image guidance, and medical oversight essential.
Step Two: Use the Window for Nonsurgical Spinal Decompression
Once the fire is quieter, the next question is simple: what mechanical inputs can the spine tolerate now?
Here, “spinal decompression” means nonsurgical mechanical traction or distraction, not surgery. The goal is controlled lumbar unloading while monitoring symptoms and neurologic response.
Research on traction is encouraging for some lumbar disc herniation patients, but it is not one-size-fits-all. A 2025 systematic review found improvements across traction, exercise, and manipulation studies, while also reporting very high variability between protocols and patient groups (Thavarajasingam et al., 2025).
That is why decompression should be treated as a clinical tool, not a magic table.
During the treatment window, the clinician can look for useful signs:
Leg pain centralizes toward the back
Standing and walking tolerance improves
Numbness or tingling decreases
The patient can change positions with less guarding
Basic trunk and hip exercises become tolerable
If symptoms worsen, spread farther down the leg, or neurologic weakness progresses, reassess the plan.
Step Three: Fix the Load With Mechanical Chiropractic Care
Pain relief is valuable, but function is the finish line.
The picker or packer has to return to the same realities: low bins, repetitive handling, long walking routes, awkward reaches, and a clock that does not care whether the lumbar muscles are fatigued. Mechanical chiropractic care should therefore focus on restoring motion and controlling load, not simply chasing pain scores.
Care may include low-force mobilization, selected chiropractic adjustments, hip mobility, trunk endurance, graded lifting, nerve-mobility exercises, and conditioning. Aggressive manipulation is not automatically appropriate during a highly irritable radicular episode; treatment intensity should match neurologic findings and tolerance.
A useful return-to-function plan teaches the worker to:
Hinge through the hips instead of repeatedly rounding the lumbar spine
Bring the load closer before standing
Pivot with the feet instead of twisting while bent
Alternate positions when task design allows
Break large recovery goals into short movement exposures
Report progressive weakness or spreading numbness promptly
These habits support autonomy. The patient should understand what is being treated, why each step is being used, what alternatives exist, and what would change the plan.
Integrated Care: One Plan, Not Three Disconnected Treatments
Severe radicular pain often crosses professional lanes. That is where multidisciplinary care can improve coordination.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines Doctor of Chiropractic care with board-certified family nurse practitioner authority and advanced practice nursing. Under collaborative medical oversight, his scope includes image-guided epidural spinal injections, structural chiropractic care, mechanical rehabilitation, and functional medicine support.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in Internal Medicine, has more than 40 years of experience, and serves as Medical Director and collaborative physician at Injury Medical Clinic PA. Her role includes medical oversight, risk stratification, laboratory interpretation, and coordination of medical conditions that can affect recovery.
The benefit is sequence and communication: calm the nerve when indicated, restore tolerable motion, rebuild capacity, and coordinate with the patient’s existing medical team. That supports beneficence while respecting non-maleficence—using the least invasive reasonable options first when safe, without delaying surgical or emergency referral when neurologic findings demand it.
Your Treatment Window Should Lead Somewhere
An epidural injection should not become permission to ignore the same loading pattern until the pain returns. The window is valuable because it creates opportunity.
Use it to walk more normally.
Use it to sleep.
Use it to tolerate decompression or rehabilitation.
Use it to relearn bending, lifting, and bracing strategies.
Use it to build enough capacity that the next 10-hour shift is not simply another flare waiting to happen.
For an Amazon fulfillment worker with severe low back pain and leg symptoms, the goal is not to choose between “an injection” and “chiropractic.” The better question is whether each tool fits the diagnosis and timing.
Turn down the fire. Then fix the load.
If severe back pain, sciatica, numbness, or weakness is limiting your work or daily function, schedule a multidisciplinary evaluation at El Paso Back Clinic. A coordinated DC/APRN/FNP-BC and MD-guided plan can help determine whether you need urgent referral, an epidural treatment window, nonsurgical decompression, mechanical rehabilitation, or a different path entirely. You remain the informed decision-maker at every step.
Server Rack to Desk Chair: Why Data Center and IT Work Can Trigger Chronic Low-Back Pain—and What You Can Do About It
A shift can change quickly. For one hour, you sit and answer tickets. The next, you are standing on a server-room floor, crouching behind a rack, reaching for cables, or lifting hardware. By day’s end, your low back may feel tight, tired, or familiar.
For El Paso’s IT professionals, data center technicians, and network teams, recurring low-back pain rarely comes down to one “bad posture.” Sitting, standing, bending, twisting, and lifting can contribute to symptoms, but no single exposure consistently explains every case (Swain et al., 2020). The better question is which combined loads, habits, and recovery limits keep your back irritated.
Why Tech Work Can Become a Mechanical Load Problem
Your lumbar spine is built to move and carry load. Problems can appear when tissues face more stress than they comfortably recover from.
Long desk sessions reduce movement variety. Prolonged standing can also become uncomfortable; substantial occupational standing has been associated with more low-back symptoms, though it has not been proven that standing itself causes pain (Coenen et al., 2018). Add crouching, cable work, twisting, and equipment lifting, and the demand changes again.
The goal is not to fear movement. It is to improve how well your body handles it.
Sitting, Hip Stiffness, and the “Locked Up” Feeling
After hours seated, many workers stand feeling stiff through the hips and lower back. It is tempting to blame “tight hip flexors,” but low-back pain is more complex than one muscle group.
Limited hip motion can change how you bend, squat, or reach. The lumbar region may then take on more motion during some tasks. Hip mobility, trunk control, and movement variety can therefore be reasonable rehabilitation targets without claiming that tight hips automatically cause back pain.
Standing on Concrete Is Not Automatically Better Than Sitting
A standing desk may help, but standing all day is not a cure. Technical workspaces may require long periods on firm surfaces while monitoring equipment.
Variation is usually practical: sit, stand, walk, change foot position, and move when the job permits. NIOSH identifies static posture, heavy physical work, lifting, bending, and twisting among contributors to work-related musculoskeletal stress (National Institute for Occupational Safety and Health [NIOSH], 2024a).
Think “best next position,” not “perfect position.”
Crouching, Cable Work, and Rack-Side Repetition
Working behind equipment can place you in deep hip flexion, kneeling, squatting, rotation, or sustained forward bending. None is inherently dangerous. Trouble may develop when exposure is prolonged, repeated, heavily loaded, or performed while fatigued.
Bring tools closer. Raise work when possible. Use a kneeling pad or stable support when appropriate. Alternate sides instead of always rotating one way. Brief movement breaks can reduce unnecessary repetition.
Lifting Hardware: Control the Load, Not Just Your Back
Servers, batteries, monitors, and UPS components can be awkward or hard to grip. Safe lifting is not simply “keep your back straight.” Weight, distance, height, twisting, frequency, grip, and repetition matter. The Revised NIOSH Lifting Equation estimates physical stress from two-handed lifts and supports safer job design (NIOSH, 2024b).
Get close to the load, use a stable stance, avoid rushed twisting, and use team lifts or assistance when appropriate. Lifting limits should reflect the task and your current capacity.
What a Structural Assessment Should Actually Look For
Recurring low-back pain deserves more than a quick label.
At El Paso Back Clinic, a mechanical assessment can consider spinal and pelvic motion, painful patterns, hip mobility, trunk endurance, lifting mechanics, neurological findings, and positions that change symptoms. The goal is not to claim every painful back is “out of alignment,” but to identify modifiable findings and whether conservative care is appropriate.
Imaging is not necessary for every episode. History and examination help determine when testing may be appropriate. New bowel or bladder problems, saddle numbness, progressive leg weakness, major trauma, fever, or systemic symptoms require prompt medical evaluation.
Mechanical Rehabilitation: Build Capacity for Your Real Job
Rehabilitation should prepare you for work, not only help you feel better on a treatment table. Clinical guidelines support exercise and selected manual therapies for many people with acute or chronic low-back pain (George et al., 2021).
For an IT professional, rehabilitation might include hip mobility, trunk endurance, hinging, graded lifting, strength, walking tolerance, and desk-position changes. A data center technician may also need loaded carries, squat tolerance, kneeling transitions, reaching, and controlled rotation.
The plan should progress with your response. Some people need mobility; others need strength, endurance, or confidence with painful movements. Patient autonomy matters: you should understand what is tested, why treatment is suggested, alternatives, and how progress will be measured.
Where Chiropractic Care and Decompression Fit
Chiropractic care may be one part of conservative treatment when examination indicates manual care is appropriate. Guidelines include spinal manipulation among options that may help some people with chronic low-back pain, especially when paired with active care rather than used alone (World Health Organization [WHO], 2023).
“Decompression” requires careful thinking. WHO does not recommend routine traction for chronic primary low-back pain because the supporting evidence is uncertain (WHO, 2023). Decompression should not be sold as a guaranteed disc fix or universal answer.
If decompression is considered, it should follow examination, fit the symptom pattern, have clear goals, and be reassessed. Beneficence means choosing care for your clinical needs—not applying the same protocol to everyone.
Integrated Care When Back Pain Is More Than Mechanical
Persistent pain can be influenced by sleep, stress, metabolic health, medication use, recovery, and other medical factors. An integrated team can help when those issues matter.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care, mechanical rehabilitation, and functional medical assessment. Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, provides medical direction and oversight for complex medical or metabolic concerns and clinically appropriate laboratory evaluation.
Collaboration does not remove your voice. You remain the informed decision-maker.
A Better Back Strategy for El Paso Tech Workers
Whether your day moves from an El Paso desk to a server room, network closet, help-desk station, or equipment floor, your back needs more than perfect posture. It needs movement variety, smart load management, recovery, and enough strength for the work.
Start with small changes: interrupt long sitting, vary standing, improve workstation reach, keep loads close, plan awkward lifts, and build capacity gradually. If pain keeps returning, limits work, radiates into the leg, or changes how you move, seek a qualified evaluation.
At El Paso Back Clinic, our goal is to identify changeable drivers, explain your options clearly, and coordinate structural chiropractic care, mechanical rehabilitation, and medical oversight when indicated. We build the safest plan around your findings, goals, and informed choices. That approach supports safer movement, stronger function, and more confident workdays ahead.
References
Coenen, P., Willenberg, L., Parry, S., Shi, J. W., Romero, L., Blackwood, D. M., Maher, C. G., Healy, G. N., Dunstan, D. W., & Straker, L. M. (2018). Associations of occupational standing with musculoskeletal symptoms: A systematic review with meta-analysis. British Journal of Sports Medicine, 52(3), 176–183. https://doi.org/10.1136/bjsports-2016-096795
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. https://doi.org/10.2519/jospt.2021.0304
Swain, C. T. V., Pan, F., Owen, P. J., Schmidt, H., & Belavy, D. L. (2020). No consensus on causality of spine postures or physical exposure and low back pain: A systematic review of systematic reviews. Journal of Biomechanics, 102, 109312. https://doi.org/10.1016/j.jbiomech.2019.08.006
World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. World Health Organization. https://www.who.int/publications/i/item/9789240081789
Battlefield Acupuncture and Chiropractic Pain Relief
Abstract
Welcome to our educational series. I’m Dr. Alex Jimenez, and today, we’re exploring a powerful, non-pharmacological tool for pain management: Battlefield Acupuncture (BFA). This post will guide you through the principles and applications of this innovative technique, which uses auricular (ear) acupuncture to provide rapid, significant pain relief. We will explore the neurophysiological mechanisms behind BFA, identify key anatomical points on the ear, and explain their connection to the brain’s pain-processing centers. I’ll explain the step-by-step protocol, from patient assessment to needle insertion, and discuss its effectiveness for both acute and chronic pain conditions. As part of our commitment to integrative care at Injury Medical Clinic, we will also explore how Battlefield Acupuncture seamlessly complements our core chiropractic, physical rehabilitation, and functional medicine strategies. By combining these modalities, we can create a comprehensive, patient-centered treatment plan that addresses pain from multiple angles, promotes faster recovery, and restores function while minimizing the need for medication.
An acupuncturist puts needles into the patient’s back, removing inflammation of the muscles
A Modern Approach to Ancient Healing: Understanding Battlefield Acupuncture
As a clinician dedicated to finding the most effective and evidence-based treatments for my patients, I am constantly exploring advancements in integrative medicine. One of the most remarkable techniques I’ve incorporated into my practice is Battlefield Acupuncture (BFA). Developed by Dr. Richard Niemtzow, a retired Air Force physician, this protocol is a specialized form of auricular acupuncture designed for rapid pain relief in diverse settings, from the front lines of combat to our clinical practice here in El Paso.
The name might sound intense, but the technique is precise, minimally invasive, and incredibly effective. It involves placing small, semi-permanent needles, called ASP® needles (Aiguille Semi-Permanente), at specific points on the ear. These are not your typical acupuncture needles; they are tiny, dart-like needles designed to stay in place for several days, providing continuous stimulation to the nervous system. The primary goal is to interrupt pain signals and modulate the body’s own pain-relieving mechanisms.
The Neurological Blueprint of Pain Relief: How BFA Works
To appreciate how placing a tiny needle in the ear can alleviate pain in the lower back or a knee, we must first understand the intricate connection between the ear and the central nervous system. The external ear, or auricle, is one of the most densely innervated parts of the body, with connections to major nerves like the vagus nerve, trigeminal nerve, and cervical plexus.
Ancient acupuncture charts depicted the ear as a “homunculus,” an inverted fetus map where different parts of the body correspond to specific points on the ear. Modern research has validated this concept, showing that stimulating these auricular points sends signals directly to the brain and influences key areas involved in pain perception and processing.
The BFA protocol targets five specific points that correspond to major pain-processing centers in the brain:
Cingulate Gyrus: This is a crucial part of the limbic system, which governs our emotional response to pain. By targeting this point, we can help detach the emotional suffering and anxiety often associated with chronic pain.
Thalamus: Often called the brain’s “relay station,” the thalamus receives sensory signals from the body and directs them to the appropriate cortical areas for processing. Modulating this point helps to filter and reduce the intensity of incoming pain signals before they even reach conscious awareness.
Omega 2: This point is associated with regulating the autonomic nervous system, helping to shift the body from a “fight-or-flight” (sympathetic) state, which often exacerbates pain, to a “rest-and-digest” (parasympathetic) state that promotes healing.
Point Zero: Considered the “autonomic balance” point of the ear, this area helps to bring the entire body back into a state of physiological equilibrium, or homeostasis.
Shen Men (“Spirit Gate”): A master point used in many forms of acupuncture, Shen Men helps to calm the mind, reduce stress, and has a powerful general analgesic (pain-relieving) effect.
When an ASP needle is inserted, it stimulates these nerve endings, sending a signal along neural pathways to the brainstem and higher brain centers. This process is believed to trigger the release of the body’s own natural painkillers—endorphins and enkephalins—and to downregulate the activity in brain regions that process pain, effectively turning down the “volume” of the pain signal.
The Battlefield Acupuncture Protocol: A Step-by-Step Guide
The BFA protocol is systematic and patient-driven. The patient’s feedback on their pain level at each step determines how we proceed. This ensures the treatment is customized in real-time to achieve the best possible outcome.
Initial Assessment and Preparation
Pain Assessment: Before we begin, I ask the patient to rate their pain on a scale of 0 to 10. I also ask them to perform a simple movement that provokes their pain, such as walking, bending, or rotating their neck. This provides us a functional baseline.
Choosing the Starting Ear: For generalized pain or pain on both sides of the body, we typically start with the ear on the patient’s non-dominant side. If the pain is localized to one side (e.g., right-sided sciatica), we start on the contralateral (opposite) ear.
Sanitization: The ear is thoroughly cleaned with an alcohol swab to ensure a sterile field. While some practitioners may not use gloves, I believe it is prudent to wear them to maintain the highest standards of hygiene for patient safety.
Needle Insertion and Reassessment
The magic of BFA lies in its sequential process. We don’t simply insert all five needles at once.
First Point (Cingulate Gyrus): I begin by inserting the first ASP needle into the Cingulate Gyrus point. I hold the needle with a special applicator and, with a quick, firm press, insert it with a small “click.” It’s surprisingly well tolerated, with most patients feeling only a momentary pinch.
Ambulation and Reassessment: After the first needle is in, I ask the patient to stand up and walk around for a minute. I then ask them to rate their pain again. “Has the pain level decreased?” “Does the movement feel easier?”
Decision Point: If the patient reports a significant reduction in pain (e.g., from an 8 down to a 4) with just one needle, we may stop there. The goal is maximum relief with the minimum number of needles.
Progressing the Protocol: If the pain relief is minimal or non-existent, I proceed to the next point in the sequence, the Thalamus. After inserting the second needle, the patient ambulates and reassesses their pain again. We continue this process through the five points, stopping at any point where the patient experiences substantial relief. If we complete all five points in one ear and the pain is still not adequately controlled, we can then move to the other ear and repeat the process.
The ASP needles are designed to stay in the ear for three to seven days. They are covered by a small adhesive patch, and patients can shower and sleep with them in place. They typically fall out on their own as the skin naturally exfoliates. This provides continuous, low-level stimulation that extends the therapeutic benefit long after the patient leaves our clinic.
Integrating BFA with Chiropractic and Rehabilitative Care
At Injury Medical Clinic, our philosophy is rooted in a multidisciplinary, integrative approach. Under the medical direction of our internist, Dr. Maria Cardenas, we blend various disciplines to create a synergistic healing effect. Battlefield Acupuncture is not a standalone cure but a powerful component of a larger, comprehensive treatment plan.
BFA as a Gateway to Movement and Rehabilitation
One of the biggest obstacles in rehabilitating a musculoskeletal injury, such as a herniated disc or severe sciatica, is pain. Pain creates fear of movement (kinesiophobia), leading to muscle guarding, stiffness, and deconditioning. This creates a vicious cycle where pain leads to immobility, and immobility worsens the pain.
This is where BFA shines. By providing rapid and significant pain relief, it creates a crucial “window of opportunity.” A patient who walked in with 8/10 back pain and could barely bend might, after a BFA treatment, experience a drop to 3/10 pain. This newfound comfort allows them to engage more effectively in the other essential parts of their recovery:
Chiropractic Adjustments: When a patient’s muscles are relaxed and they are not in excruciating pain, they are more receptive to spinal adjustments. The chiropractic adjustment, aimed at restoring proper joint mechanics and relieving nerve pressure, can be performed more gently and effectively. BFA helps break the cycle of muscle spasm that often resists manipulation.
Physical Therapy and Functional Exercise: With pain reduced, patients can participate fully in their prescribed therapeutic exercises. They can perform stretches with a greater range of motion and engage in strengthening exercises without the fear of immediate, sharp pain. This is critical for stabilizing the spine, correcting muscular imbalances, and building the resilience needed to prevent re-injury.
Decompression Therapy: For conditions like disc herniation or spinal stenosis, we use non-surgical spinal decompression. This therapy works best when the patient is relaxed. BFA helps calm the nervous system and reduce the reflexive muscle guarding that can interfere with the gentle traction of the decompression table.
In essence, BFA acts as a catalyst for recovery. It doesn’t replace the foundational work of chiropractic and physical rehabilitation; it enables it. By managing the primary symptom of pain, we empower patients to become active participants in their healing journey, accelerating their return to function and daily life. My clinical observations consistently show that patients who receive BFA alongside their regular chiropractic and rehab programs report faster pain reduction and improved functional outcomes compared to those who receive traditional care alone.
A Patient-Centered, Holistic Vision
Our team, guided by the collaborative expertise of Dr. Cardenas and me, looks at each patient through a holistic lens. We understand that pain is a complex experience influenced by physical, biochemical, and emotional factors. Battlefield Acupuncture fits perfectly within this model because it directly addresses the neurological and emotional components of pain, complementing the biomechanical focus of chiropractic care and the functional focus of physical therapy. This integrated system allows us to provide truly comprehensive care for everything from acute personal injuries to chronic, stubborn pain conditions, always keeping the patient’s well-being and long-term health as our ultimate goal.
References
Niemtzow, R. C. (2018). Battlefield acupuncture: An emerging tool for pharmacists to participate in pain management. Hospital Pharmacy, 53(2), 85–86. https://doi.org/10.1177/0018578718761271
Niemtzow, R. C., Burns, S. M., & Zeliadt, S. B. (2020). Battlefield acupuncture for the provider. Medical Acupuncture, 32(4), 196–203. https://doi.org/10.1089/acu.2020.1449
When to Seek a Second Opinion for Complex Spinal Joint and Nerve Pain in El Paso, Texas
Abstract
Complex spinal joint and nerve pain is long-lasting discomfort that comes from more than one spinal structure at the same time. Wear, injury, or pressure can affect the bones, facet joints, discs, and nearby nerve roots at the same time. That overlap is why a single pill, a short course of physical therapy, or one injection often fails to bring lasting relief. This article explains what the condition is, how nerve pain differs from joint pain, and when people in El Paso, Texas, should seek a second opinion. It also shows how integrative chiropractic care can work with medical oversight and combined therapies such as shockwave therapy, MLS laser therapy, IV infusion therapy, PRP, PFP, MFAT, and epidural spinal injections. The goal is a clear path toward better movement and less daily pain.
What Is Complex Spinal Joint and Nerve Pain?
Complex spinal joint and nerve pain is chronic discomfort caused by overlapping damage, wear, or pressure on the vertebrae, facet joints, discs, and surrounding nerve roots in the spine.
The spine is a stack of bones called vertebrae. Between most of those bones sit discs that act like cushions. Small joints on the back of the spine, called facet joints, help you bend and twist. Nerve roots leave the spinal canal through narrow openings and travel into the arms or legs. When more than one of these parts is irritated at the same time, pain can feel mixed, confusing, and hard to treat.
Spine problems often involve the vertebrae, discs, nerves, and nearby muscles together. That mix can cause back or neck pain, stiffness, limited motion, numbness, tingling, or weakness in an arm or leg.
This is not the same as Complex Regional Pain Syndrome (CRPS). CRPS is a separate nerve condition that usually affects a hand, arm, foot, or leg after injury and can include changes in skin color, temperature, and swelling. Complex spinal joint and nerve pain stays centered on the spine and the nerves that exit it.
Why Joint Pain and Nerve Pain Feel So Different
Joint pain and nerve pain do not feel the same, even when they start in the same region of the back or neck.
Joint pain often feels like:
A deep ache in one spot
Stiffness after sitting or first thing in the morning
Pain that worsens when you arch backward or stand for a long time
Soreness that stays close to the spine
Nerve pain often feels like:
Burning, stabbing, or electric-shock sensations
Tingling, numbness, or “pins and needles”
Pain that travels into a shoulder, arm, hip, or leg
Weakness in a muscle group
Kansas Pain Management notes that muscle pain tends to feel dull and tight, nerve pain often shoots or burns, and facet joint pain is more localized and position-based. Oakland Spine explains that nerve pain can start far from where you feel it, while joint pain usually stays in one area unless a swollen joint also presses on a nerve.
When both problems exist together, a person may have a stiff low back and burning pain down the leg. Treating only the joint, or only the nerve, leaves half the problem untouched.
Common Causes of Pressure on Spinal Joints and Nerves
Nerve compression happens when the space around a nerve root becomes smaller. Common causes include:
A bulging or herniated disc
Bone spurs from arthritis
Spinal stenosis (a narrowed spinal canal)
Degenerative disc disease
Injury from a fall, work accident, or car crash
Thickened ligaments
Long-term posture strain
“Radiculopathy” is the medical term for a pinched nerve root. It can cause pain, numbness, tingling, or weakness along the nerve’s path. It is most common in the neck and lower back.
Facet joints can also wear down. When those small joints become inflamed, they can create local spine pain and, in some cases, add extra pressure near a nerve root. That is one reason symptoms overlap.
When to Seek a Second Opinion in El Paso, Texas
A second opinion is not a sign that the first provider failed. It is a smart step when the picture is incomplete.
Consider a second opinion if:
Pain has lasted more than a few weeks and is not clearly improving
You have numbness, tingling, or weakness in an arm or leg
Imaging was done, but no one explained how the findings match your symptoms
You were told “everything looks fine,” yet you still cannot work, sleep, or drive comfortably
Steroid shots or pain medicine helped only for a short time
Surgery was offered as the next step before a full non-surgical plan was tried
You were treated for only one pain source when your symptoms sound mixed
An auto accident, work injury, or old sports injury still bothers you months later
You live in El Paso or elsewhere in West Texas and want a team that can look at both the mechanical and medical sides of the problem
People often seek a new evaluation when traditional care focused on rest, medication, or a single procedure and the pain kept returning. Accurate identification of the pain source—nerve, joint, disc, muscle, or a combination—guides better treatment.
Why One Treatment Often Is Not Enough
A herniated disc on an MRI does not always explain every symptom. Facet arthritis, muscle guarding, inflammation, poor movement patterns, and nerve irritation can all sit at the same spinal level. If care targets only one layer, relief can stall.
Educational videos on spine anatomy and nerve pain show how discs, joints, and nerves sit close together and can fail as a unit rather than as isolated parts. That close relationship is why a combined plan often makes more sense than a single procedure.
Early, complete evaluation also matters because delayed care can allow stiffness, weakness, and guarded movement to become habits. Those habits then keep feeding into the pain cycle.
How Integrative Chiropractic Care Fits Into Treatment
Integrative chiropractic care looks at how the spine moves, how the joints stack, and how nearby muscles and nerves respond. The goal isn’t just to ease pain for a day. The goal is to restore cleaner motion, so nerves have more room and joints share load more evenly.
Chiropractic care can help by:
Improving spinal joint motion with precise adjustments
Reducing mechanical pressure around irritated nerve roots
Pairing care with spinal decompression when discs are compressed
Retraining posture and core support so the spine stays more stable
Coordinating soft-tissue work so muscles stop guarding the injured area
Oakland Spine notes that chiropractic care and physical therapy can help both nerve pain and joint pain when the plan corrects alignment and builds support around the injured structures.
In an integrative clinic, chiropractic care does not stand alone. It is timed with medical evaluation, rehabilitation, and regenerative options so the spine can move better while tissues repair.
Combined Therapies for More Thorough Healing
Complex pain often needs more than one tool. The therapies below are commonly used together, not as competing choices.
Shockwave therapy
Shockwave therapy sends acoustic waves into tight or scarred tissue. Those waves can increase local blood flow, break up dense scar tissue, and help a stalled healing response start again. It is often used before or after regenerative injections so the area is more ready to repair.
MLS laser therapy
MLS laser therapy uses specific light wavelengths to lower inflammation and support cellular energy. It can calm swelling after an adjustment, decompression session, or injection and make it easier to stay consistent with rehab.
IV infusion therapy
IV therapy delivers fluid and selected nutrients into the bloodstream. It does not replace spinal treatment. It may support hydration, recovery, and the broader healing environment while other therapies work on the joints and nerves.
PRP (platelet-rich plasma)
PRP uses a concentrated portion of a person’s own blood platelets. Platelets release growth factors that may support tissue repair in joints, soft tissue, or selected spinal structures when used as part of a larger plan.
PFP (platelet-fibrin plasma / platelet-fibrin products)
PFP is a related blood-based product. Clinics use it when a more fibrin-rich preparation may better support a treatment area. Like PRP, it is a supportive option, not a stand-alone cure.
MFAT (microfragmented adipose tissue)
MFAT uses a small amount of a person’s own fat tissue that is processed into smaller fragments. It may be considered when a more complex injury requires structural or cushioning support.
Epidural spinal injections
An epidural injection places medication near an irritated nerve root to reduce inflammation in the space around that nerve. Conservative care for radiculopathy often includes rehabilitation, medication, and interventional options such as epidural injections. Injections can create a window of lower pain so a person can move, adjust, and strengthen more effectively.
These options work best when they are sequenced. Decompression and adjustments can create space. Shockwave and laser can prepare tissue and control inflammation. Regenerative procedures and selected injections can support biology. Rehabilitation then teaches the spine how to hold the new motion.
The Collaborative Team in El Paso
At Injury Medical Clinic PA in El Paso, Texas, care is built as a team model rather than a one-provider visit.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides chiropractic care, functional medicine, personal injury evaluation, and rehabilitation planning. His clinical observations, shared on dralexjimenez.com and his LinkedIn profile, emphasize finding both the mechanical problem and the metabolic or inflammatory factors that keep pain going. He often notes that patients improve more when alignment, soft-tissue health, nutrition, and cellular support are addressed together.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine. Her NPI is #1164426749, and her Texas medical license is #J2933. With more than 40 years of experience as an internist, she serves as medical director and collaborative physician at Injury Medical Clinic PA. This MD–DC partnership is common in integrative and injury-care clinics. The medical director provides medical oversight while the chiropractic and rehabilitation team addresses spinal mechanics, movement, and recovery.
Together, the team can coordinate:
Chiropractic and spinal decompression
Functional medicine and nutrition support
Personal injury documentation and rehabilitation
Shockwave and MLS laser therapy
Regenerative options such as IV infusion therapy, PRP, PFP, and MFAT
Medical decision-making around injections and co-existing health issues
That structure matters in El Paso, Texas, where patients may travel from across El Paso, the Upper Valley, or nearby desert communities and want one coordinated plan instead of disconnected referrals.
What a Second-Opinion Visit Should Cover
A useful second opinion should do more than repeat the last MRI report. It should connect your story to a clear exam.
A thorough visit often includes:
A detailed history of how the pain started and what makes it travel
A movement exam of the neck or low back
Nerve testing for strength, sensation, and reflex changes
Review of prior imaging and whether it matches the exam
Screening for joint pain versus nerve pain versus mixed pain
A discussion of non-surgical options before any new procedure
A staged plan that may combine chiropractic care, rehab, laser or shockwave therapy, and selected regenerative or injection options
If you have personal injury, veteran, or work-related documentation needs, those records should be part of the same conversation so care and paperwork stay aligned.
A Clear Next Step for El Paso, Texas Patients
Complex spinal joint and nerve pain is particularly challenging because it is rarely “just a disc” or “just arthritis.” It is often both, plus muscle guarding and nerve irritation. That is why people feel stuck after standard care.
A second opinion is worth seeking when pain is mixed, persistent, or poorly explained. Integrative chiropractic care can restore motion and reduce mechanical pressure. Medical oversight can keep the plan safe and complete. Combined therapies such as shockwave therapy, MLS laser therapy, IV infusion therapy, PRP, PFP, MFAT, and epidural spinal injections can support healing from more than one angle.
If you live in El Paso or elsewhere in West Texas and your current plan has not given you a clear path forward, a multidisciplinary evaluation can help you see which structures are driving the pain and which combination of care is most likely to help you move again.
Faster Injury Recovery in El Paso: Pairing IV Infusion Therapy with Spinal Adjustments
IV infusion therapy and spinal adjustments can work together to help the body heal from injuries faster. This article explains what each treatment does, why they work together, and how they relax tense muscles, reduce joint inflammation, and speed tissue repair. You will also see how integrative chiropractic care belongs in the plan, how the El Paso medical and chiropractic team works, and what a personal recovery path can look like.
What IV Infusion Therapy Does
IV infusion therapy sends fluids, vitamins, minerals, and other nutrients straight into the bloodstream through a small vein. Because the nutrients skip the stomach and intestines, the body can use nearly all of them right away. This is often called 100 percent bioavailability.
A typical recovery mix includes fluids for hydration, magnesium to help muscles relax, B vitamins for energy and nerve support, vitamin C to fight inflammation and help build collagen, and sometimes antioxidants. These ingredients reach cells quickly. The result is better hydration at the cellular level, less oxidative stress, and faster new tissue building.
People often notice less muscle tightness and more energy within hours. The session itself usually lasts 30 to 45 minutes and is done in a comfortable clinic setting under medical supervision.
How Spinal Adjustments Support Healing
Spinal adjustments, also called chiropractic manipulations, gently restore proper alignment to the spine and other joints. When bones sit in the right place, nerves can send clearer signals, muscles can fire more evenly, and blood flow improves around injured areas.
Misalignment from a car accident, sports strain, or everyday wear can keep muscles in a protective spasm and limit the nutrients that reach damaged tissue. An adjustment reduces that mechanical stress. It also helps the nervous system settle, which can lower the body’s overall pain response.
Integrative chiropractic care looks at the whole person. It does not stop at the adjustment. It includes movement exercises, posture work, and coordination with other therapies so the structural change lasts.
Why the Two Treatments Work Better Together
IV infusion therapy complements spinal adjustments by delivering 100 percent bioavailable fluids, magnesium, and vitamins directly into the bloodstream. This rapid cellular hydration and nutrient delivery, bypassing the digestive system, relaxes tense muscles, reduces joint inflammation, and speeds tissue repair, optimizing the body for structural healing.
Think of the adjustment as resetting the frame of a house and the IV as delivering the right building materials and water to every room at once. Once the spine is better aligned, circulation and nerve signals improve. The nutrients from the IV can then travel more easily to the exact spots that need repair. Spinal adjustments combined with IV infusion therapy help the body recover faster by treating structural misalignment while delivering nutrients directly to cells to fight inflammation. This integrated approach improves nutrient bioavailability and accelerates tissue repair, reducing the chronic pain associated with musculoskeletal injuries. If you’re in El Paso and want a full, tailored recovery plan, contact Injury Medical & Chiropractic Clinic.
Magnesium in the IV mix helps muscles release extra tension after an adjustment. Vitamin C and antioxidants help quiet the inflammatory chemicals that often linger after a sprain, strain, or disc injury. Better hydration also keeps joints moving more freely, so the benefits of the adjustment last longer.
Key Benefits for Musculoskeletal Injuries
Patients with back pain, neck pain, whiplash, sports injuries, or post-accident stiffness often see these improvements when the two therapies are used together:
Faster drop in muscle spasm and stiffness
Less swelling around joints and soft tissue
Quicker return of energy and daily function
Better collagen formation for ligaments and tendons
Reduced need for extra pain medication in many cases
Support for the immune system so healing is not delayed by extra stress
These effects are especially helpful after auto accidents or when recovery has stalled. Direct nutrient delivery can reach areas that have limited blood flow, such as some tendons and spinal discs.
How Integrative Chiropractic Care Fits the Picture
Integrative chiropractic care is more than a single adjustment. It includes a full assessment of posture, movement patterns, and how the injury affects the rest of the body. The chiropractor addresses the structural side, while the IV provides biochemical support.
This combination is common in clinics that treat personal-injury cases and chronic musculoskeletal problems. The adjustment improves joint motion and nerve function. The IV then gives the cells the raw materials they need to rebuild. Functional medicine principles—looking at nutrition, inflammation, and lifestyle—tie the two together so the plan is personalized.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, has observed that patients recover more completely when structural care and cellular nutrition are addressed at the same time. His clinical work in El Paso focuses on non-invasive, root-cause approaches that restore function after trauma rather than just masking symptoms.
The Team at Injury Medical Clinic PA
Injury Medical Clinic PA in El Paso uses a multidisciplinary model. Dr. Alex Jimenez provides chiropractic and functional medicine expertise. Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), serves as medical director and collaborative physician. She has more than 40 years of experience as an internist.
This setup is typical in integrative injury-care clinics. The MD oversees medical safety, reviews lab work when needed, and ensures IV therapies are appropriate. The chiropractor handles spinal and musculoskeletal alignment. Together, they also coordinate rehabilitation, personal-injury documentation, and functional-medicine testing.
The team treats auto-accident injuries, sports strains, work-related pain, and chronic conditions such as sciatica or disc problems. Patients receive a plan that can include adjustments, targeted IV infusions, movement therapy, and nutrition guidance—all under one roof.
What a Typical Recovery Journey Looks Like
A first visit usually starts with a history and exam. Imaging or labs may be ordered if needed. The doctors then decide which IV formula (hydration, Myers’-style cocktail, or recovery blend) matches the injury and which adjustment techniques will help most.
Treatments are often scheduled close together at first—sometimes the same day or within 24–48 hours—so the nutrients and the alignment change can reinforce each other. Follow-up visits track pain levels, range of motion, and energy. Frequency is adjusted as healing progresses.
Safety is a priority. Trained staff administers IVs in a sterile setting. Patients are screened for any conditions that would make an infusion unsuitable.
Taking the Next Step in El Paso
If you are dealing with lingering pain, slow healing after an injury, or muscle tightness that will not ease, the combination of IV infusion therapy and spinal adjustments offers a practical, evidence-informed option. The goal isn’t just short-term relief, but a body that can repair itself more efficiently.
If you’re in El Paso and want a full, tailored recovery plan, contact Injury Medical & Chiropractic Clinic. The team can review your history, explain the options, and design a program that fits your needs.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine