Back Clinic Power & Strength Training. These types of conditioning programs are for both athletes and the general population. They can reach higher levels of personal power and strength, making them capable of achieving their personal fitness goals. Power is defined as the ability to generate as much force as fast as possible. It’s needed for athletic movements such as workouts (clean & jerk), swinging a bat, golf club, tennis racket, and running through a tackle.
Power requires strength and speed to develop force. Strength is the amount of force muscle/s can exert against an external load. One rep maximum test is performed where individuals assess the greatest weight they can lift while maintaining proper form. The movement’s speed is not important in a strength test. Dr. Alex Jimenez offers insight into various stretches and exercises and explains the possible risks of injury on strength training through his numerous article archives.
Why Repeated Small Bends Can Bother Your Back More Than One Heavy Lift
Abstract
Repeated small bends for packages, cables, laundry, or drawers can irritate the lower back more than one controlled heavy lift. This article explains cumulative spinal loading, how fatigue and reach distance change forces on the discs and ligaments, and why limited hip mobility and trunk endurance shift more work onto the lumbar spine. It outlines a chiropractic assessment process, progressive hip and trunk conditioning, practical task changes, and a plan to build bending tolerance safely rather than avoid spinal flexion. The goal is better function for Amazon associates, data center technicians, parents, warehouse workers, and desk professionals.
Maria finishes her Amazon shift without a single heavy box. She reaches into totes and bends for packages dozens of times an hour. By the time she gets home, her low back feels tight. At home, she loads the washer and picks up toys. One controlled lift earlier never bothered her as much. The pattern shows up in data center technicians, parents, warehouse workers, and desk professionals who repeatedly bend for cables, laundry, tools, or drawers.
The idea that only heavy objects matter misses how the spine handles repeated work. A single well-executed lift is one event. One hundred lighter bends spread the work across tired muscles, changing angles, and longer reaches. The tissues never fully recover between cycles, so the result can feel different—and sometimes worse.
The Myth of the Heavy Object
Advice to “lift with your legs” and “never bend your back” protects against sudden overload. It does not fully describe repeated bending for hours. Research shows both the size of each force and the number of cycles matter. High-frequency moderate loads still contribute substantially to total spinal stress (Coenen et al., 2012).
A controlled heavy lift usually uses a planned technique and finishes before fatigue sets in. Repeated light bends are hurried, done at the end of a reach, and performed after the trunk muscles have already worked. The spine sees a different pattern of compression, shear, and bending moment.
What Cumulative Loading Means for Your Spine
Each bend compresses and bends the lumbar discs and ligaments. When erector spinae muscles fatigue, they allow more lumbar flexion. Volunteers who lifted a 10 kg weight 100 times showed increased peak lumbar flexion and a 36 percent rise in estimated bending moment by the end of the task (Dolan & Adams, 1998).
Fatigue failure studies reinforce the point. Motion segments cyclically loaded to simulate lifting a 9 kg weight failed after far fewer cycles as torso flexion increased. Neutral posture allowed thousands of cycles; 45 degrees of flexion reduced survival to a few hundred cycles on average (Gallagher et al., 2005). Spinal posture during bending changes tissue tolerance.
Fatigue and Creep
As back muscles tire, the spine relies more on passive tissues. Repeated flexion produces creep—a slow increase in flexibility. After 20 minutes of sustained flexion, peak flexion rose by about 5.5 degrees, and full stiffness recovery took longer than the loading period (McGill & Brown, 1992). Short rests do not always fully reset the tissues. Residual creep can leave the spine more flexible for the next cycle.
Reach Distance and the Moment Arm
How far the hands are from the body matters as much as the weight. Holding a package at arm’s length multiplies the lumbar bending moment even if the package is light. Reaching into a rack, tote, or across a bed lengthens the lever arm. Bringing the object closer or raising the work surface shortens that distance and reduces demand.
How Hips and Trunk Endurance Share the Work
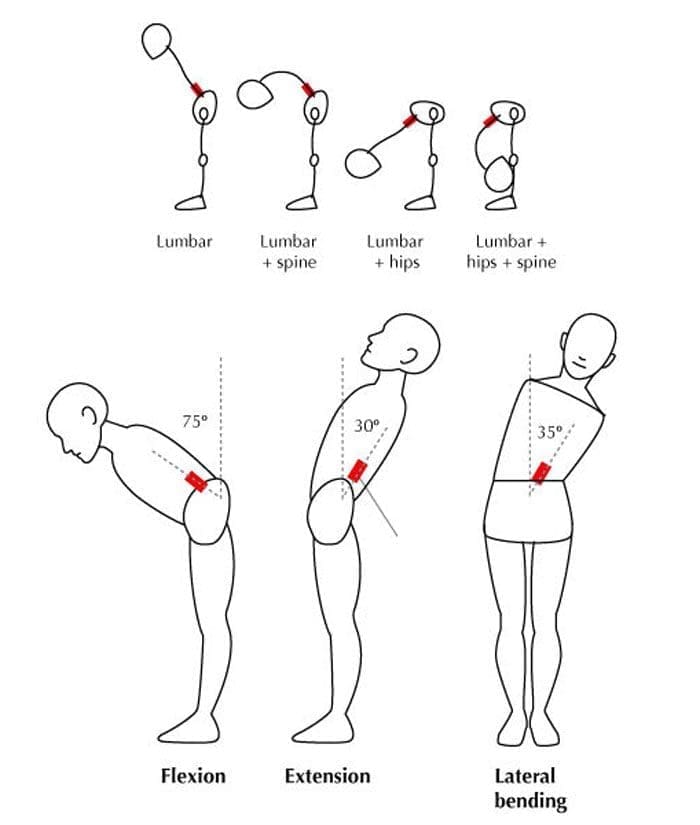
The lumbar spine favors stability; the hips handle large ranges of flexion. Limited hip mobility forces earlier and deeper lumbar flexion. Over dozens of bends, this shifts cumulative load onto the discs and ligaments.
Trunk endurance matters as much as peak strength. Someone who can deadlift once may still fatigue during 40 minutes of light bending if deep stabilizers and hip extensors lack endurance. Building that capacity protects the spine later in the shift.
Chiropractic Assessment: Finding the Real Pattern
A thorough evaluation at El Paso Back Clinic looks beyond the single heavy lift. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, and the team examine how the patient moves during the tasks that bother them. Assessment covers lumbar and hip range of motion, hip-hinge ability with a relatively neutral lumbar spine, trunk and hip endurance, control during repeated bending, and postural habits. The evaluation promptly identifies red-flag signs that require imaging or referral.
The evaluation identifies limited hip mobility, poor trunk endurance, excessive reach distance, residual stiffness, or a combination. Medical Director Dr. Maria Guadalupe Cardenas, MD, provides collaborative oversight, interpreting structural findings alongside medical factors when needed. Accurate diagnosis lets treatment address the real pattern. Beneficence guides the process: coordinated care improves safety, function, and recovery.
Building Bending Tolerance Instead of Avoiding Flexion
Fear of spinal flexion can create its own problems. Avoiding all bending leads to deconditioning. The tissues that are never loaded gradually lose capacity. A better approach is to restore control and then gradually reintroduce bending under conditions the spine can tolerate.
Chiropractic care restores restricted joint motion and reduces protective guarding. Adjustments and soft-tissue work free the hips and thoracic spine so the lumbar spine compensates less. Once motion improves, focus shifts to endurance work that matches real tasks:
Hip-hinge practice with light loads held close to the body
Controlled step-ups or partial squats that train the hips to share work
Timed trunk endurance holds in positions that match the job
Progressive increases in the number of bends per set, starting well below the threshold that produces next-day stiffness
The plan matches the job. An Amazon associate who bends 200 times per shift needs a different progression from a parent who bends mainly after a desk day. Progress is measured by how the back feels during and after the real task. Non-invasive options reduce risks of surgical complications or heavy medication dependence.
Practical Task Modifications for Daily Work and Home
While capacity builds, small changes reduce the total load the spine sees each day:
Bring packages, cables, or laundry closer before lifting or lowering them.
Use a low stool or kneel for tasks that would otherwise require deep lumbar flexion.
Alternate sides and change stance so one pattern does not dominate.
Take brief standing or walking breaks after longer periods of repeated bending.
Raise frequently used items so the average bend is shallower.
For parents, place a sturdy surface at hip height for folding or packing.
These changes reduce peak moments and high-flexion cycles while improving capacity. Patients remain the informed decision-makers, choosing modifications that fit their shift and family schedule.
The Multidisciplinary Path Forward
Integrative care at Injury Medical Clinic PA combines chiropractic structural work with medical oversight from Dr. Cardenas. Dr. Jimenez’s dual licensure supports coordinated attention to mechanical alignment and contributing factors. The emphasis remains on non-invasive strategies that restore function and reduce the need for surgery. Many patients with excellent group insurance coverage find coordinated care covered when it addresses documented functional limits.
If repeated bending has become the part of your day you dread, a focused assessment can clarify the drivers and how to rebuild tolerance safely. Call 915-850-0900 or visit the clinic in El Paso. The aim is to keep the spine working for the tasks you actually do.
Why the First Heavy Lift of the Shift Can Feel Worse Than the Twentieth
Abstract
The first demanding lift after sitting or standing still can feel stiff or surprisingly heavy. That does not automatically mean the back is damaged. It often reflects a rapid transition from inactivity to loaded movement. This article explains how temperature, coordination, readiness, fatigue, and conditioning shape that transition—and how workers can prepare without fearing lifting.
You badge in, reach your station, and the first real task is a heavy tote, server component, tool case, cable spool, or awkward package. The weight is familiar, yet your hips feel slow, and your back feels tight.
Twenty lifts later, the job may feel smoother. That difference can be unsettling, especially if you’ve had lower back pain before. But the body does not move identically from the first repetition to the twentieth. The goal is not to fear the early lift. It is to prepare for the demand.
The Body Has to Change Gears
A commute or computer session requires less force than lifting, carrying equipment, or pulling inventory. When demand rises quickly, muscles and joints must coordinate faster.
Warm-up research helps explain part of this effect. Higher muscle temperature is associated with improved rate-dependent muscle function, including faster force production and power, although not necessarily greater maximum strength (Wilson et al., 2025). Appropriate warm-ups can also improve physical performance (Fradkin et al., 2010).
A “cold” muscle is not automatically unsafe. Progressive movement can help the body reach the speed and coordination the job requires.
Why Sitting Before Work Can Matter
Many workers begin physical work after a commute, meeting, or computer task.
After inactivity, the first deep hip bend or loaded reach may simply feel unfamiliar. The hips flex, the trunk controls the load, the feet create a stable base, and the upper body manages the object. Problems are more likely when demand suddenly exceeds what the worker can comfortably coordinate or tolerate that day.
Readiness also changes with sleep, soreness, injury, stress, and object shape. Good preparation, therefore, needs more than one lifting slogan.
There Is No Single Perfect Lift
Workers are often told to “lift with the legs” and never bend the back. That sounds simple, but research shows that technique training alone does not reliably prevent lower back pain in material-handling workers (Verbeek et al., 2012).
Technique still matters—in context. Useful principles can include:
bringing the load closer when practical;
creating a stable stance before pulling or lifting;
using the hips and knees when the task allows;
avoiding sudden twisting with a demanding load;
using team lifting or mechanical help when needed;
changing strategy when space, fatigue, or object shape changes.
Lifting is a skill, not one perfect pose. The best strategy is controlled, repeatable, and adaptable.
Warm-Up Effects and Fatigue Are Different
Feeling better by the twentieth lift does not mean endless repetitions are protective. Early in a shift, increasing temperature and repeated practice may improve movement efficiency. Later, fatigue can reduce control, slow reactions, and make familiar loads feel harder.
Think of the shift as a curve: preparation early, efficiency in the middle, and smarter pacing or assistance later.
“I loosen up after a few lifts” should not become “I should ignore pain.” Progressive readiness is useful; sharp pain, increasing numbness, weakness, or loss of coordination deserves clinical attention.
A Five-Minute Work-Readiness Sequence
A practical warm-up should resemble the work ahead.
1. Walk and breathe
Walk briskly for one or two minutes to transition out of inactivity.
2. Move the hips and trunk
Perform several comfortable hip hinges, shallow squats, or controlled reaches without forcing range.
3. Add light load
Practice a few lifts with a light object and focus on smooth control.
4. Rehearse the task
If work involves carrying, pulling, stepping, or lifting from knee height, rehearse that pattern at lower effort.
5. Build toward harder work
When workflow allows, use a few graded repetitions before the heaviest or most awkward task.
When the First Lift Repeatedly Hurts
If the first heavy lift repeatedly causes back pain, evaluation should go beyond “stretch more.” Assessment can examine spinal and hip motion, neurological findings, strength, tolerance, previous injury, and triggering work demands.
For persistent lower back pain, exercise is supported as part of conservative care and can improve pain and function for many patients (Hayden et al., 2021). The World Health Organization also includes structured exercise and spinal manipulative therapy as options within person-centered care for chronic primary lower back pain (World Health Organization, 2023).
At El Paso Back Clinic, chiropractic care should not teach patients that their spine is fragile. The aim is to improve comfortable movement and pair hands-on care with strength, mobility, and work-specific rehabilitation.
Building Capacity Beats Avoiding Work
Workers who lift, carry, kneel, reach, or handle equipment need the capacity to do those tasks. Long-term progress may include hip strength, trunk endurance, leg strength, grip, loaded carries, squats, hinges, step-ups, and graded exposure to realistic work demands.
The practical target is simple: enough mobility to reach the task, enough strength to control it, and enough endurance to repeat it without unnecessary guarding or fear.
Progress the load rather than fear it. Exercise therapy has evidence for chronic lower back pain, but programs should match the individual rather than treating every painful back the same way (Hayden et al., 2021).
This supports beneficence by restoring function, non-maleficence by emphasizing non-invasive care before unnecessary procedures when appropriate, and autonomy by helping patients understand options and coordinate decisions with their medical team.
Integrated Care When Stiffness Is Not the Whole Story
Radiating pain, numbness, weakness, recurrent injury, or stalled recovery may require broader evaluation.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines chiropractic and advanced practice nursing perspectives. Dr. Maria Guadalupe Cardenas, MD, provides internal medicine oversight for complex medical factors and coordinated care. Depending on findings, care may include chiropractic treatment, rehabilitation, diagnostic testing, acupuncture, electroacupuncture, or other appropriate options. Advanced therapies should follow a clear diagnosis and should not replace strength and movement capacity.
Start the Shift Ready, Not Afraid
The first heavy lift may feel worse because your body has not transitioned from stillness to demanding movement. That doesn’t mean lifting is dangerous.
Give your body time to adjust. Build strength for your actual work. Adjust strategy as load or fatigue changes. If pain keeps coming back, get assessed instead of guessing.
The goal is not to avoid lifting. The goal is to be better prepared to lift, carry, bend, and work with confidence.
Multidisciplinary Call to Action
If lower back pain is limiting your lifts or full shift, schedule an evaluation with the El Paso Back Clinic team. A chiropractic assessment, rehabilitation, and medical oversight can build a plan focused on function, capacity, and independence.
Why Standing Still Can Hurt Your Back More Than Walking
Abstract: Many workers are surprised that walking through a warehouse, data center, retail floor, or job site can feel easier than standing still. The reason is often not that walking is “better posture,” but that movement changes how the back, hips, and legs share load. This article explains static loading, muscular endurance, hard-floor fatigue, posture variability, and how chiropractic assessment plus progressive conditioning can improve standing tolerance.
A shift can create a strange pattern: your back feels fine while you are moving, but it starts aching when you stop at a workstation, security station, register, rack, or packing area. The key difference is simple: walking keeps the load changing; standing still holds it in one place.
That distinction matters in jobs. A technician may walk between racks comfortably, then ache while troubleshooting one cabinet. A warehouse employee may tolerate picking orders but be hurt at a fixed packing station. The activity is not necessarily harder; the body simply has fewer chances to redistribute effort.
Static Loading: Why “Not Moving” Still Requires Work
Standing may look restful, but it still requires active work. Your trunk, hips, legs, and feet make small, continuous corrections to keep you upright. When you stay in nearly the same position, the same tissues can be asked to work for a long time with little variation.
Research has linked substantial occupational standing to higher odds of low-back symptoms, although individual responses vary and not every worker develops pain (Coenen et al., 2018). Laboratory research also shows prolonged standing can provoke low-back discomfort even when spinal loads are relatively low, suggesting posture strategy and individual sensitivity matter (Gregory & Callaghan, 2008).
That is why “stand up straight” is not a complete solution. Holding a perfect posture too long can still become uncomfortable.
Walking Changes the Mechanical Conversation
Walking creates repeated motion through the hips, pelvis, lumbar spine, knees, ankles, and feet. Muscles contract and relax in cycles instead of holding one continuous position. Weight shifts from side to side. The pelvis and spine keep moving.
That variability may explain why a worker can walk several aisles with less discomfort than standing at one station for twenty minutes.
In one laboratory study, five-minute walking breaks inserted every twenty-five minutes reduced the number of participants who developed low-back pain during a two-hour standing period. The walking periods also increased lumbar movement compared with standing still (Gallagher et al., 2019). The lesson is not to follow an exact timer; periodic movement changes the mechanical demand.
Endurance Matters More Than People Realize
Back pain while standing doesn't always mean something is “out of place.” Endurance may be the limiting factor.
Imagine holding a light grocery bag at your side. The bag may not be heavy, but if you hold it long enough without changing position, your shoulder and forearm eventually fatigue. Static standing can create a similar challenge for the trunk and hips.
Workers may notice:
aching across the beltline after standing in one location;
tightness in the low back or gluteal muscles;
shifting repeatedly from one leg to the other;
leaning on a counter, cart, rack, or desk for relief;
feeling better after walking a short distance;
leg or foot fatigue that seems to “travel upward.”
The Hips and Legs Share the Job
The lumbar spine does not work alone. Hip strength, gluteal endurance, calf capacity, ankle mobility, and foot comfort all influence how long standing feels tolerable.
If the hips fatigue quickly, a worker may begin hanging on one hip, locking the knees, or leaning the trunk. If the ankles are stiff, the body may compensate higher up. If the feet become sore, a person may change stance repeatedly in ways that increase back tension.
Hard work surfaces also matter. Evidence suggests cushioned materials such as softer flooring, mats, or insoles can reduce discomfort or fatigue during prolonged standing, although they are not a cure for back pain and results vary among workers (Speed et al., 2018). Concrete does not automatically “damage” the spine, but hard surfaces may add to foot and leg fatigue.
Posture Variability Beats Chasing One Perfect Position
People often blame pain on “bad posture,” but that idea is too simple.
A more useful goal is posture variability. Instead of freezing your body in one ideal alignment, change positions before fatigue sets in.
Practical options include:
alternate between sitting, standing, and walking when the job allows
place one foot briefly on a low support, then switch sides
take a short walking loop during natural work transitions
avoid locking the knees for long periods
change stance width periodically
use supportive footwear appropriate for the job and floor
avoid leaning on one hip for long stretches
These are load-management strategies, not rigid rules
What a Chiropractic Assessment Should Look For
For standing-related back pain, an examination should do more than ask, “Where does it hurt?”
A useful assessment may include lumbar range of motion, hip motion, neurological screening, gait, balance, trunk endurance, hip strength, symptom reproduction, and the positions that increase or reduce discomfort. Work demands matter too; a server rack differs from a register, packing station, or tool bench.
Chiropractic care may be appropriate when joint stiffness, restricted movement, or mechanical pain contributes to symptoms. Current guidelines support staying active, therapeutic exercise, and, for selected patients, spinal manipulation as part of broader care (Zhou et al., 2024; World Health Organization [WHO], 2023).
The goal is not simply to make the back feel looser for an hour. The goal is to increase what the body can tolerate.
Build Capacity: Trunk, Hips, Walking, and Load Management
Progressive conditioning gives the body more reserve for long workdays.
A clinician may start with low-demand exercises and gradually increase time, resistance, and complexity:
controlled sit-to-stand or squat patterns;
bridges and hip-extension exercises;
split-stance or step-up work;
trunk endurance exercises;
loaded carries with appropriate technique;
calf and ankle conditioning;
progressive walking.
Exercise supports chronic nonspecific low-back pain, though no single style works for everyone. Trunk-focused programs can improve pain, disability, and trunk performance (Prat-Luri et al., 2023). A 2024 network meta-analysis found that exercise dose and type influence outcomes, but evidence certainty varies, supporting individualized progression (Liang et al., 2024).
Walking tolerance deserves special attention because walking is both exercise and a practical work skill. If five minutes feels acceptable but twenty minutes flares symptoms, the plan may progress gradually instead of jumping immediately to long distances.
When Back Pain Needs More Than Ergonomic Changes
Not every backache from standing is simply fatigue. Seek medical evaluation promptly for new bowel or bladder changes, saddle numbness, progressive leg weakness, major trauma, fever with back pain, unexplained weight loss, or severe symptoms that do not behave like ordinary mechanical pain.
Persistent pain that disrupts sleep, work, or walking also warrants evaluation.
At Injury Medical Clinic PA in El Paso, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines chiropractic care with advanced-practice clinical assessment, rehabilitation, and functional medicine. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than forty years of experience, provides medical direction and collaborative oversight when metabolic, neurological, or systemic issues need broader evaluation.
That coordinated model supports beneficence by aiming to identify the real driver of symptoms, non-maleficence by emphasizing conservative and non-invasive options when appropriate, and autonomy by helping patients understand choices and coordinate care with their existing medical team.
The Takeaway: Move More, Then Build More Capacity
If walking feels easier than standing still, your body may be telling you that movement variability helps while static endurance is limited.
The answer is usually not to avoid standing forever. Instead, understand what limits tolerance, change positions before fatigue becomes pain, build trunk and hip capacity, manage footwear and work surfaces, and progressively rebuild the ability to stand and move through a full shift.
For many workers, the most useful question is not, “What is the perfect posture?” It is, “How can I keep changing position and build enough capacity so that my back no longer runs out of endurance before my workday ends?”
Schedule a coordinated chiropractic, rehabilitation, and medical evaluation to turn that question into a practical plan.
Why Twisting to Reach Behind a Server Rack Can Hurt More Than Lifting Straight Ahead
A straight lift keeps the load close to your body’s center. A reach behind a server rack, into an engine bay, or around a pallet adds a turn, a one-handed pull, and often a bent trunk. This article explains why that mix can stress the low back more than a heavier square lift, how stiff hips and a stiff mid-back push the turn into the lumbar spine, and how assessment, mobility, strength, and positioning help workers keep the job.
The cable was not heavy. That is what bothers most technicians later. The same grab shows up across jobs:
A data center tech can carry a battery module square to the body, then grab sharply while reaching behind a live rack for a loose fiber run.
A network installer feels it as he pulls a bundle from a wall cavity.
A mechanic feels it leaning across an engine bay.
A warehouse worker feels it as they turn a carton off a pallet without a step.
The object was lighter than the morning lift. The position was not.
Straight Ahead Is a Different Task
A square lift is simpler. Three things keep the load moment smaller:
The hands stay near the midline.
The hips and knees bend.
The trunk stays stacked.
A reach behind a rack breaks that setup at once:
The hands move off to the side or behind the hip, so the weight sits farther from the spine.
The trunk bends and turns together.
One hand often does the work, which adds a side bend.
The feet cannot always step, because a rack, a liftgate, or a frame is in the way.
The pull starts and stops quickly when a connector sticks.
The revised NIOSH lifting equation includes an asymmetry multiplier for this reason. At a 90-degree turn, the recommended limit drops by roughly 29 percent before accounting for height, distance, and frequency (Waters et al., 1993). In industrial studies, five factors separated higher-risk jobs from lower-risk jobs with an odds ratio of 10.7: lifting frequency, load moment, sideways trunk speed, twisting speed, and forward bend (Marras et al., 1993).
What Rotation Under Load Means
Rotation under load means the spine is compressed while also being asked to twist. Compression is the squeeze from body weight, the object, and the bracing muscles. Twist is the turn. Separately, each can be tolerable. Together, they ask discs, facets, and ligaments to manage shear while the muscles are already working.
Asymmetric lifting raises paraspinal muscle activity and intradiscal pressure (McGill, 1991; Wilke et al., 2001). People with low back pain can load the spine more during the same controlled lifts. In one comparison, moment-adjusted compression was about 26 percent higher and front-to-back shear about 70 percent higher than in people without pain (Marras et al., 2004). One reach does not automatically herniate a disc. The tissues simply have less margin when the turn, the bend, and the tug arrive together.
Why the Low Back Borrows the Turn
Each lumbar segment can rotate only a few degrees. Most of a healthy turn should come from the hips and the thoracic spine, the mid-back between the shoulder blades. Confined work steals those contributions.
A stiff mid-back is common in people who reach forward or brace one arm overhead. If the rib cage cannot rotate, the low back is next.
Stiff hips show up after long stands, kneeling, and hours in a vehicle. If the pelvis cannot turn, the lumbar segments turn instead.
Tired trunk muscles still fire, but the timing that keeps shear in check gets sloppier late in the shift.
A one-handed pull adds side bend, so the opposite back muscles brace harder.
Cable Pulls, Bays, and the Last Row
A slow two-handed turn with free feet doesn’t expose you to the same risk as a stuck connector at shoulder height in a narrow aisle. Higher-demand versions share traits:
The load starts far from the body.
The feet stay planted.
The pull is one-handed.
The release is sudden.
The same motion repeats after fatigue has set in.
Turning a carton onto a conveyor without a step is a different task from a square lift. The grab often arrives on the last row.
What the Exam Should Sort Out
A useful visit does not stop at the sore side. At Injury Medical Clinic PA, we ask where the turn comes from and whether the low back is covering for a hip, a mid-back, or a brace that faded with fatigue.
The exam checks thoracic and hip rotation on each side within a range that does not provoke leg pain. It checks whether bending forward, bending back, or the turn reproduces the work symptom. The task account matters too: one hand or two, height, how often, and early or late in the shift.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges that structural exam with nursing-level review when the story needs it. Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine, provides collaborative oversight for medical risk and imaging decisions. A drug-free plan of adjustment, mobility, and strength avoids the tradeoffs of long-term opioids and keeps surgery as a later option. Autonomy means the worker hears the findings and chooses the pace.
A Plan That Does Not Ban the Twist
The job includes turning. A plan that pretends otherwise fails on the first shift back. The sequence is assessment, restoring the missing motion, building controlled rotational strength, and then rehearsing the work position.
Use adjustment when joints aren’t moving, and that restriction feeds lumbar compensation. Mobility follows the exam. A stiff mid-back may need pain-free open-book rotation. Stiff hips may need rotation and hinge practice before cable work. Strength starts with control. Anti-rotation holds, such as a Pallof-style press, teach the trunk to resist rotation before it happens. Slow chops come next, inside a range that does not light up the leg. Speed and load wait until the hips clearly share the motion.
Electroacupuncture is an adjunct, not the default. If pain blocks sleep or blocks the exercise that would change the pattern, precise needling with microcurrent can settle the guarding so training can start. Non-surgical decompression enters when leg-dominant symptoms point to disc loading and simpler care has not opened a window.
Positioning for the Next Shift
Move the feet before the shoulders when the aisle allows. A small step often removes more twist than a longer warm-up.
Bring the connector, carton, or part closer before the turn. Distance is the hidden weight.
Use two hands when the object allows. A one-hand pull is sometimes required. It should not be the default.
Break a large reach into two smaller turns.
Slide on rails or a cart when the equipment is designed to slide.
Reset before the last row if the same pull has already grabbed once.
New bowel or bladder changes, saddle numbness, rapidly worsening leg weakness, or pain after a major fall need emergency care, not a mobility drill.
Using the Group Plan
Many data center, warehouse, field service, and mechanic group plans include chiropractic evaluation. Benefits differ for decompression, acupuncture, and other add-ons. Excellent group insurance helps only if the worker knows it can cover a mechanical exam, not just a later surgical consult.
An image-guided epidural, when appropriate, is a rehab window under collaborative medical direction. It is not the first answer to a stiff hip.
The worker remains the decision-maker. The clinic explains what the turn costs, what can be trained, and what belongs with a surgeon or a work restriction. If that affects your shift, sleep, or the drive home, start with a full exam beyond the sore side. Call Injury Medical Clinic PA at (915) 850-0900 or visit El Paso Back Clinic at https://www.elpasobackclinic.com. The office is at 11860 Vista del Sol Dr, Suite 128, El Paso, TX 79936.
Author: Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP — Texas APRN License #1191402, Prescriptive Authority #59628, NPI 1205907805 — in collaborative practice with Dr. Maria Guadalupe Cardenas, MD, Texas Medical License #J2933, NPI 1164426748, Medical Director at Injury Medical Clinic PA, El Paso.
This article is for education. It is not a diagnosis, a work restriction, or a promise of coverage. Have new or worsening symptoms evaluated in person.
Reversing Severe Lumbago and Disc Compression from Amazon Fulfillment Shifts
Abstract: Severe low-back pain after fulfillment work or delivery routes can feel like a one-way road toward surgery. Yet many cases deserve a careful conservative evaluation first. This guide explains how repetitive bending, sorting, vehicle vibration, and lifting can aggravate lumbago and disc-related pain; where mechanical alignment and selected non-surgical decompression may fit; how medical oversight screens red flags; and how Amazon workers can use practical lifting limits to reduce repeat flares.
When a Shift Starts Loading the Lumbar Spine
A warehouse associate may begin a shift feeling stiff. Hours later, repeated low-bin reaches, package twisting, sorting, pallet work, or lifting away from the body can turn stiffness into severe lumbago. Delivery drivers add prolonged sitting, road vibration, repeated cabin exits, carrying, and awkward curbside lifts.
The problem is often cumulative. When the trunk bends and rotates while a load stays away from the body, spinal muscles must generate more force to control movement. Repetition can fatigue those tissues and degrade movement quality. NIOSH treats load weight, reach distance, vertical height, twisting, lifting frequency, duration, and grip quality as factors that change lifting risk (NIOSH, 2024).
That matters because “safe lifting” is not one universal number. A box manageable at waist height may be too demanding on the floor, far from the body, poorly gripped, or lifted repeatedly near the end of a long shift.
Why Pain Can Spike After the Shift
Symptoms may intensify after clocking out because fatigued muscles provide less support, sitting stiffens the hips, and irritated tissues remain sensitive after repeated loading. Delayed soreness doesn’t mean a disc suddenly worsened. Track which movements, loads, positions, and recovery habits consistently increase or decrease symptoms across workdays.
What “Disc Compression” Really Means
Between the lumbar vertebrae, intervertebral discs distribute load and allow movement. A disc is not a jelly doughnut that simply pops out and can be pushed back into place. It is a load-bearing structure with a fibrous outer ring and softer inner region. Repeated flexion, compression, rotation, aging, prior injury, and anatomy can contribute to disc changes.
Pain may come from several overlapping sources:
Irritated lumbar joints or surrounding soft tissues
Protective muscle spasm and reduced hip motion
Disc-related inflammation or mechanical sensitivity
A disc herniation that irritates a nerve root
Deconditioning after repeated pain episodes and activity avoidance
This is why a structural examination matters. The goal is to match symptoms with movement findings, neurologic testing, work demands, and imaging when indicated. Low-back guidelines support exercise, education, and selected manual or mobilization approaches as part of conservative care rather than a single passive treatment (George et al., 2021).
Step One: Restore Motion Without Forcing the Spine
At El Paso Back Clinic, targeted mechanical care begins with a practical question: which movements are limited, painful, unstable, or poorly coordinated?
One worker may have stiff hips that force repeated lumbar bending. Another may have painful lumbar joints that limit extension. A driver can show a different pattern after hours of seated flexion and vibration.
Chiropractic adjustments and non-thrust joint mobilization may improve mobility and reduce pain when the examination supports them. Guidelines report benefit from joint mobilization for many people with chronic low-back pain, including some with leg symptoms (George et al., 2021). Care should pair manual treatment with rehabilitation so improved motion becomes usable strength.
The Functional Target
The patient gains something measurable: easier standing, smoother walking, less guarded bending, better sleep positions, safer transitions from a delivery van, and more confidence handling daily tasks. Those functional gains matter more than trying to make every spinal image look “perfect.”
Step Two: Use Non-Surgical Decompression Carefully
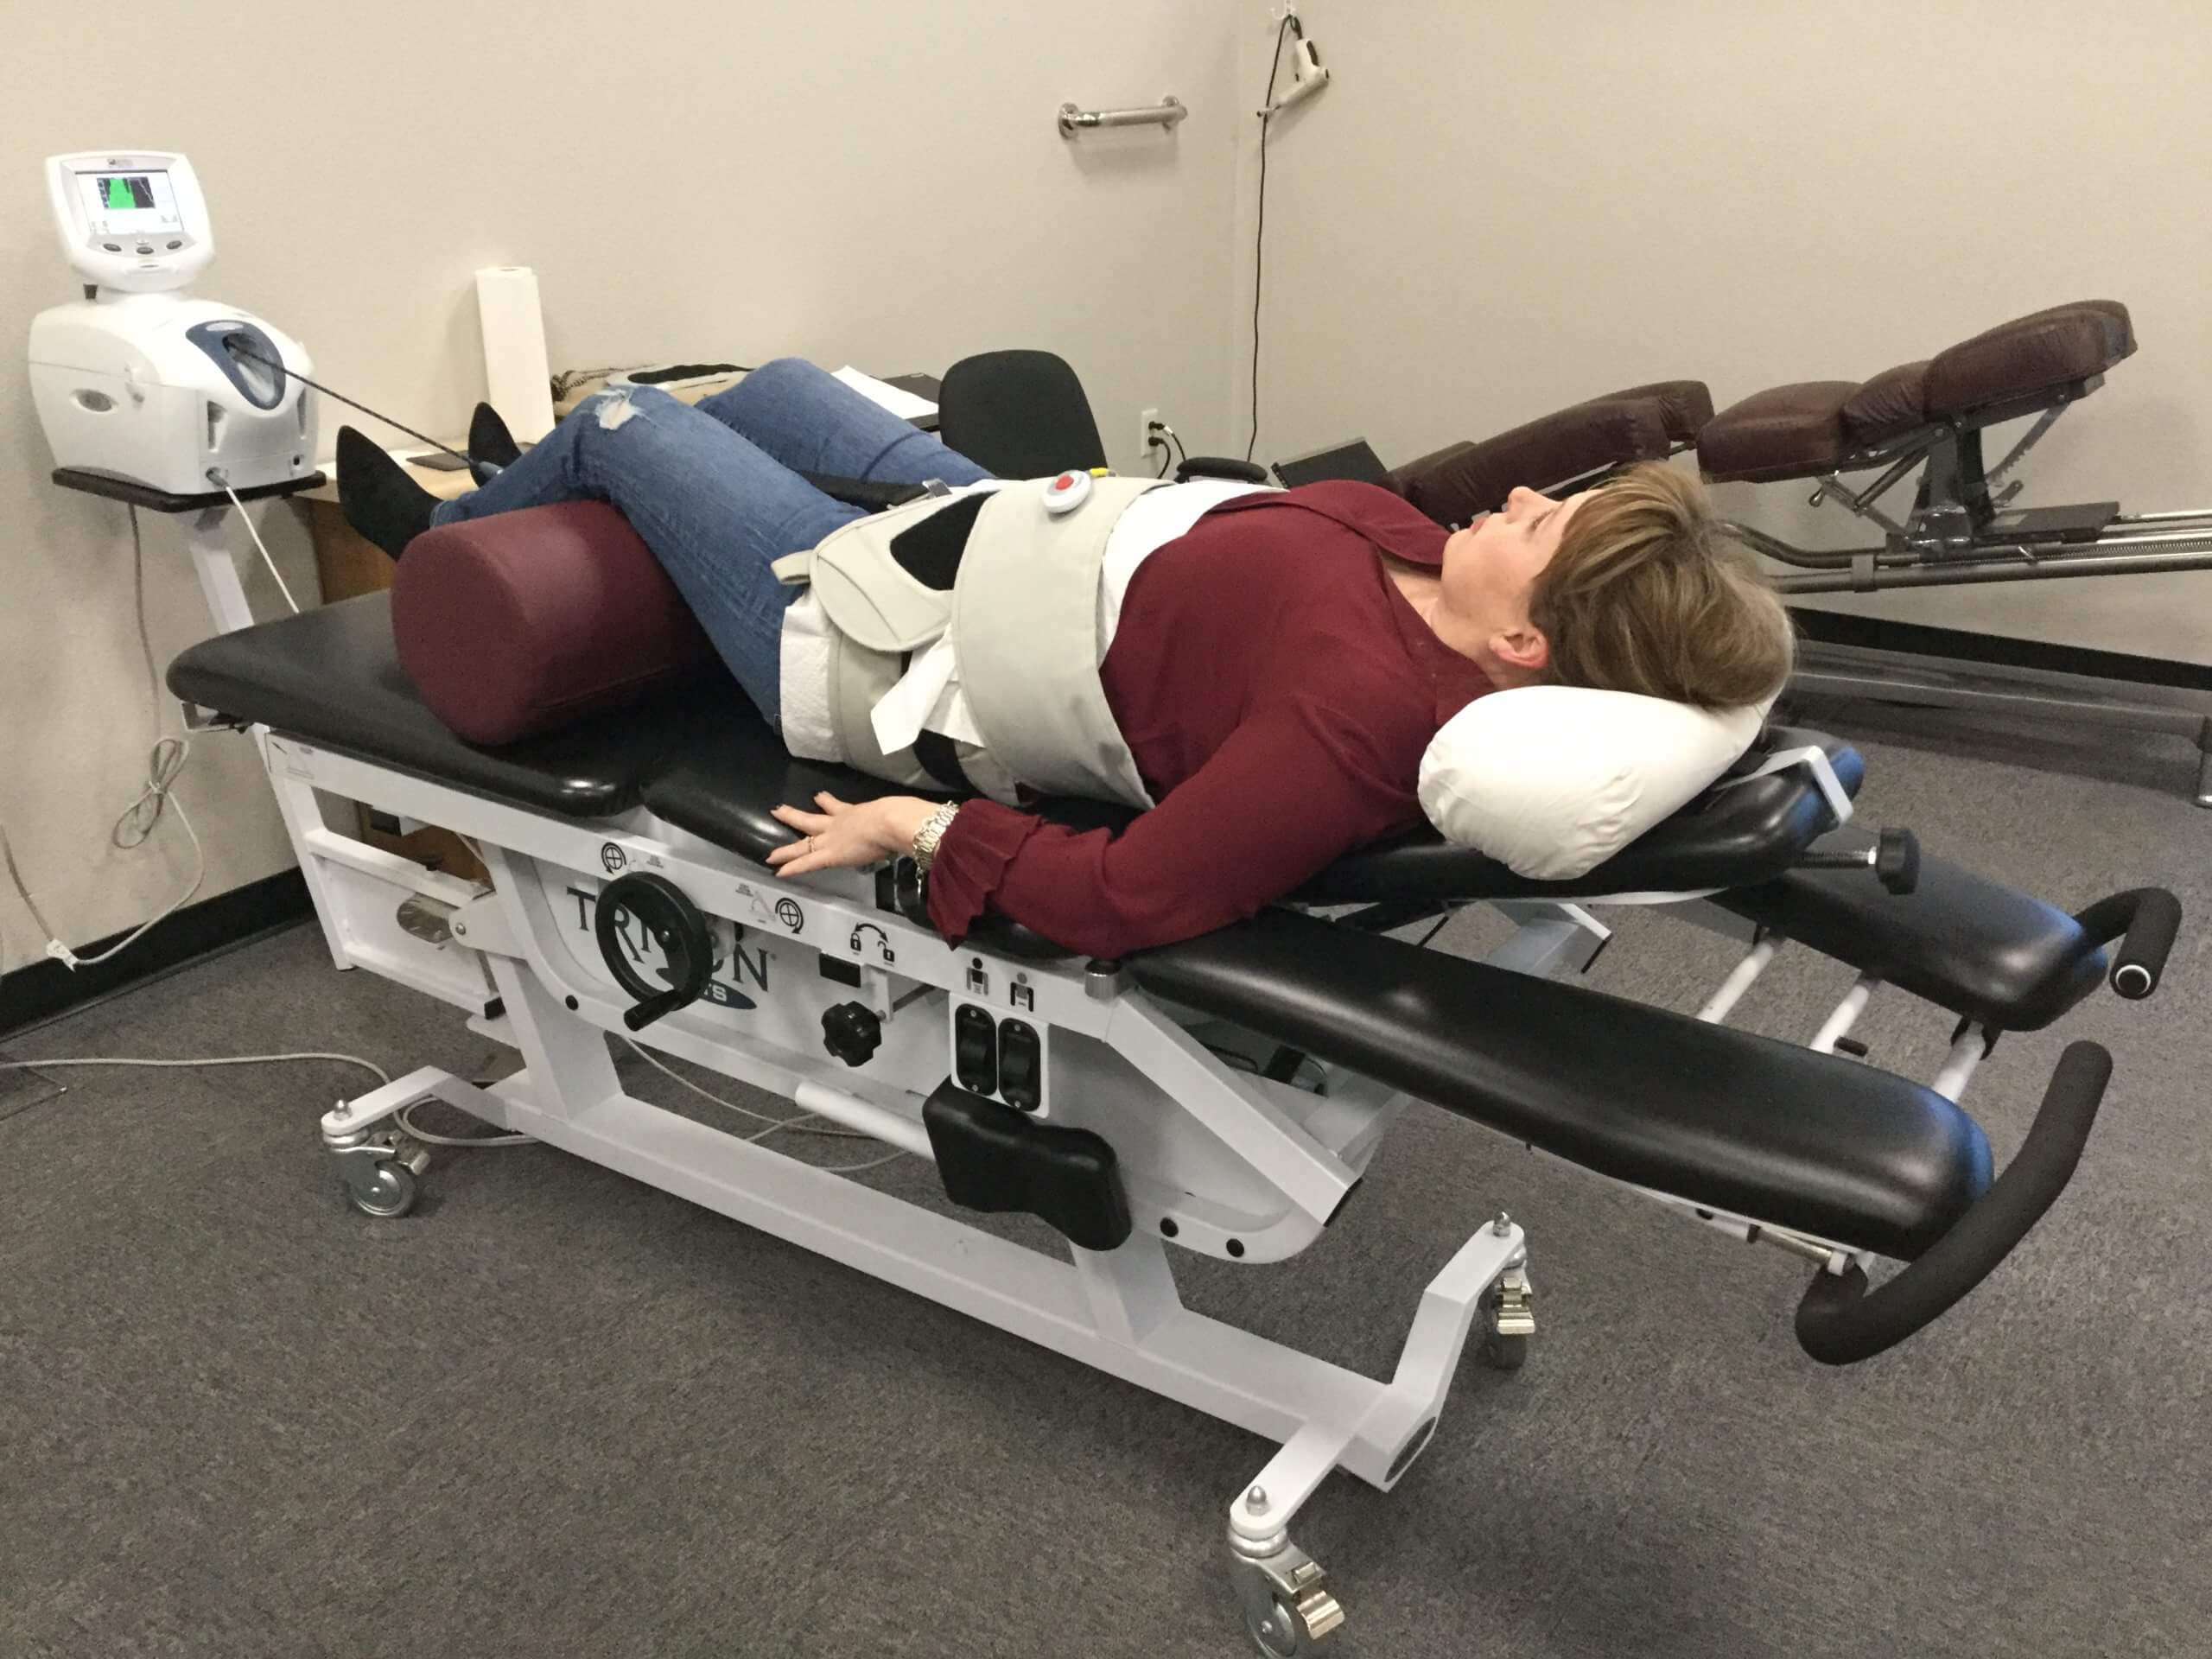
Non-surgical spinal decompression is commonly described as controlled lumbar traction or unloading. The practical aim is to reduce mechanical stress temporarily and create a position in which painful tissues or irritated nerve roots may become less sensitive.
The evidence requires precision. A systematic review found short-term improvements in pain and disability when certain mechanical traction forms were added to treatment for lumbar radiculopathy, but study quality and results varied (Vanti et al., 2021). WHO guidance for chronic primary low-back pain advises against routine traction for most patients, so decompression should not become an automatic protocol for every painful back (World Health Organization, 2023).
For a selected patient, decompression may be one tool within movement retraining, strengthening, work modification, and medical evaluation. It should never be sold as a guaranteed way to “reinflate” a disc or permanently reverse degeneration.
Preventing Unnecessary Surgery Without Delaying Necessary Surgery
Avoiding surgery is valuable when recovery is safe with conservative care. Lumbar discectomy can be appropriate for selected patients, yet it still carries risks such as recurrent herniation, wound complications, dural tears, reoperation, and neurologic complications (Bombieri et al., 2022).
The safer message is not “never have surgery.” It is “earn the decision with the right evaluation.” Recent spine recommendations support surgery when conservative treatment fails and emphasize urgent or early surgery for cauda equina syndrome or progressive severe neurologic deficits (Costa et al., 2024).
Seek urgent assessment for new bowel or bladder dysfunction, saddle-region numbness, rapidly worsening leg weakness, or serious neurologic changes. Fever, major trauma, unexplained weight loss, or concern for infection, fracture, or cancer also deserves prompt review.
This is non-maleficence in practice: use the least invasive reasonable option when it is safe, but never let a desire to avoid surgery delay care for a true emergency.
Step Three: Set Proactive Lifting Limits
For Amazon associates, prevention must survive the workday. “Lift with your legs” is not enough.
Use these rules:
Bring the package close before standing up.
Turn with the feet instead of twisting under load.
Reduce load size when the object starts low, high, or far away.
Use team lifting or mechanical assistance for demanding or awkward items.
Break up repeated lifting when possible with task rotation or brief recovery periods.
Stop treating pain as a test of toughness; a changing neurologic symptom deserves evaluation.
The Revised NIOSH Lifting Equation is useful because it does not assume every worker should lift the same weight in every position. It calculates a recommended weight limit using task conditions and a lifting index that reflects physical demand. NIOSH recommends keeping the lifting index or composite lifting index at or below 1.0 when evaluating two-handed lifting tasks (NIOSH, 2024).
Integrated Oversight: Structure, Medicine, and Patient Choice
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural alignment, mechanical rehabilitation, and advanced medical diagnostics. He holds Texas Advanced Practice Nursing License #1191402, Prescriptive Authority #59628, and NPI #1205907805. His dual licensure lets the clinic coordinate musculoskeletal examination with broader medical assessment and appropriate advanced interventions.
Dr. Maria Guadalupe Cardenas, MD, is Board Certified in Internal Medicine, has more than 40 years of experience, and holds Texas Medical License #J2933 and NPI #1164426748. As Medical Director, Clinical Director, and Collaborative Physician at Injury Medical Clinic PA in El Paso, she provides internal medicine oversight, risk stratification, interpretation of indicated laboratory tests, and comorbidity coordination.
That collaboration supports beneficence: the plan centers on the patient’s best functional outcome. It supports non-maleficence by screening for medical risks before aggressive treatment and using non-invasive, drug-sparing options when appropriate. It also protects autonomy. Patients are taught what the examination shows, what each option can and cannot reasonably do, and when another specialist or their existing medical team should be involved.
A Better Goal Than “Toughing It Out”
Severe lumbago after warehouse or delivery work is not a character test. The goal is to interrupt the overload cycle before pain, guarding, deconditioning, and poor mechanics reinforce one another.
A conservative plan can include targeted joint care, selected decompression, progressive trunk and hip rehabilitation, work-specific lifting education, and medical oversight. The target is direct: more comfortable movement, safer lifting, better sleep, and the ability to work without organizing each day around the next flare.
Multidisciplinary Call to Action
If repeated bending, sorting, driving, or lifting causes severe low-back pain, start with a coordinated evaluation. El Paso Back Clinic can assess mechanical function, neurologic findings, lifting demands, and medical risks, then explain conservative options and when to refer. Bring your imaging, medication list, job demands, and questions. The final decision remains yours, supported by clear information and coordinated chiropractic and medical care.
Server Rack to Desk Chair: Why Data Center and IT Work Can Trigger Chronic Low-Back Pain—and What You Can Do About It
A shift can change quickly. For one hour, you sit and answer tickets. The next, you are standing on a server-room floor, crouching behind a rack, reaching for cables, or lifting hardware. By day’s end, your low back may feel tight, tired, or familiar.
For El Paso’s IT professionals, data center technicians, and network teams, recurring low-back pain rarely comes down to one “bad posture.” Sitting, standing, bending, twisting, and lifting can contribute to symptoms, but no single exposure consistently explains every case (Swain et al., 2020). The better question is which combined loads, habits, and recovery limits keep your back irritated.
Why Tech Work Can Become a Mechanical Load Problem
Your lumbar spine is built to move and carry load. Problems can appear when tissues face more stress than they comfortably recover from.
Long desk sessions reduce movement variety. Prolonged standing can also become uncomfortable; substantial occupational standing has been associated with more low-back symptoms, though it has not been proven that standing itself causes pain (Coenen et al., 2018). Add crouching, cable work, twisting, and equipment lifting, and the demand changes again.
The goal is not to fear movement. It is to improve how well your body handles it.
Sitting, Hip Stiffness, and the “Locked Up” Feeling
After hours seated, many workers stand feeling stiff through the hips and lower back. It is tempting to blame “tight hip flexors,” but low-back pain is more complex than one muscle group.
Limited hip motion can change how you bend, squat, or reach. The lumbar region may then take on more motion during some tasks. Hip mobility, trunk control, and movement variety can therefore be reasonable rehabilitation targets without claiming that tight hips automatically cause back pain.
Standing on Concrete Is Not Automatically Better Than Sitting
A standing desk may help, but standing all day is not a cure. Technical workspaces may require long periods on firm surfaces while monitoring equipment.
Variation is usually practical: sit, stand, walk, change foot position, and move when the job permits. NIOSH identifies static posture, heavy physical work, lifting, bending, and twisting among contributors to work-related musculoskeletal stress (National Institute for Occupational Safety and Health [NIOSH], 2024a).
Think “best next position,” not “perfect position.”
Crouching, Cable Work, and Rack-Side Repetition
Working behind equipment can place you in deep hip flexion, kneeling, squatting, rotation, or sustained forward bending. None is inherently dangerous. Trouble may develop when exposure is prolonged, repeated, heavily loaded, or performed while fatigued.
Bring tools closer. Raise work when possible. Use a kneeling pad or stable support when appropriate. Alternate sides instead of always rotating one way. Brief movement breaks can reduce unnecessary repetition.
Lifting Hardware: Control the Load, Not Just Your Back
Servers, batteries, monitors, and UPS components can be awkward or hard to grip. Safe lifting is not simply “keep your back straight.” Weight, distance, height, twisting, frequency, grip, and repetition matter. The Revised NIOSH Lifting Equation estimates physical stress from two-handed lifts and supports safer job design (NIOSH, 2024b).
Get close to the load, use a stable stance, avoid rushed twisting, and use team lifts or assistance when appropriate. Lifting limits should reflect the task and your current capacity.
What a Structural Assessment Should Actually Look For
Recurring low-back pain deserves more than a quick label.
At El Paso Back Clinic, a mechanical assessment can consider spinal and pelvic motion, painful patterns, hip mobility, trunk endurance, lifting mechanics, neurological findings, and positions that change symptoms. The goal is not to claim every painful back is “out of alignment,” but to identify modifiable findings and whether conservative care is appropriate.
Imaging is not necessary for every episode. History and examination help determine when testing may be appropriate. New bowel or bladder problems, saddle numbness, progressive leg weakness, major trauma, fever, or systemic symptoms require prompt medical evaluation.
Mechanical Rehabilitation: Build Capacity for Your Real Job
Rehabilitation should prepare you for work, not only help you feel better on a treatment table. Clinical guidelines support exercise and selected manual therapies for many people with acute or chronic low-back pain (George et al., 2021).
For an IT professional, rehabilitation might include hip mobility, trunk endurance, hinging, graded lifting, strength, walking tolerance, and desk-position changes. A data center technician may also need loaded carries, squat tolerance, kneeling transitions, reaching, and controlled rotation.
The plan should progress with your response. Some people need mobility; others need strength, endurance, or confidence with painful movements. Patient autonomy matters: you should understand what is tested, why treatment is suggested, alternatives, and how progress will be measured.
Where Chiropractic Care and Decompression Fit
Chiropractic care may be one part of conservative treatment when examination indicates manual care is appropriate. Guidelines include spinal manipulation among options that may help some people with chronic low-back pain, especially when paired with active care rather than used alone (World Health Organization [WHO], 2023).
“Decompression” requires careful thinking. WHO does not recommend routine traction for chronic primary low-back pain because the supporting evidence is uncertain (WHO, 2023). Decompression should not be sold as a guaranteed disc fix or universal answer.
If decompression is considered, it should follow examination, fit the symptom pattern, have clear goals, and be reassessed. Beneficence means choosing care for your clinical needs—not applying the same protocol to everyone.
Integrated Care When Back Pain Is More Than Mechanical
Persistent pain can be influenced by sleep, stress, metabolic health, medication use, recovery, and other medical factors. An integrated team can help when those issues matter.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care, mechanical rehabilitation, and functional medical assessment. Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, provides medical direction and oversight for complex medical or metabolic concerns and clinically appropriate laboratory evaluation.
Collaboration does not remove your voice. You remain the informed decision-maker.
A Better Back Strategy for El Paso Tech Workers
Whether your day moves from an El Paso desk to a server room, network closet, help-desk station, or equipment floor, your back needs more than perfect posture. It needs movement variety, smart load management, recovery, and enough strength for the work.
Start with small changes: interrupt long sitting, vary standing, improve workstation reach, keep loads close, plan awkward lifts, and build capacity gradually. If pain keeps returning, limits work, radiates into the leg, or changes how you move, seek a qualified evaluation.
At El Paso Back Clinic, our goal is to identify changeable drivers, explain your options clearly, and coordinate structural chiropractic care, mechanical rehabilitation, and medical oversight when indicated. We build the safest plan around your findings, goals, and informed choices. That approach supports safer movement, stronger function, and more confident workdays ahead.
References
Coenen, P., Willenberg, L., Parry, S., Shi, J. W., Romero, L., Blackwood, D. M., Maher, C. G., Healy, G. N., Dunstan, D. W., & Straker, L. M. (2018). Associations of occupational standing with musculoskeletal symptoms: A systematic review with meta-analysis. British Journal of Sports Medicine, 52(3), 176–183. https://doi.org/10.1136/bjsports-2016-096795
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. https://doi.org/10.2519/jospt.2021.0304
Swain, C. T. V., Pan, F., Owen, P. J., Schmidt, H., & Belavy, D. L. (2020). No consensus on causality of spine postures or physical exposure and low back pain: A systematic review of systematic reviews. Journal of Biomechanics, 102, 109312. https://doi.org/10.1016/j.jbiomech.2019.08.006
World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. World Health Organization. https://www.who.int/publications/i/item/9789240081789
Regenerative Chiropractic Therapy for Better Recovery
Many people live with joint pain, soft tissue injuries, or spine problems that do not fully improve with rest or basic care. Regenerative medicine and integrative chiropractic therapy function together by integrating cellular tissue healing with mechanical alignment of the spine. PRP (platelet-rich plasma), PFP (platelet-fibrin products), MFAT (microfragmented adipose tissue), and epidural injections are aimed at inflammation and rebuilding of weak soft tissues. At the same time, chiropractic therapy restores correct joint motion and unloads strained structures. This partnership creates a more complete path to recovery.
The combination is useful for sports injuries, personal injury cases, and long-term wear on joints and soft tissues. It supports the body’s natural healing processes instead of only covering up symptoms.
Regenerative Treatments That Target Inflammation and Rebuild Tissue
Regenerative medicine uses materials from a person’s own body to support repair at the cellular level. These treatments deliver concentrated growth factors or signaling cells to injured areas. The goal is to calm chronic inflammation and encourage healthier tissue to form.
Platelet-rich plasma (PRP) starts with a simple blood draw. The blood is spun to concentrate the platelets. These platelets release growth factors that help form new blood vessels, support collagen production, and shift the area from long-term inflammation toward active healing. Athletes and active people often use PRP for tendon problems, ligament sprains, muscle strains, and mild joint wear because it can improve tissue quality without surgery (Nortex Spine and Joint, n.d.; OrthoRepair, n.d.).
Platelet-fibrin products (PFP) work similarly. They create a natural fibrin scaffold that holds growth factors in place longer. This slower release can help tissues that heal slowly, such as certain ligaments or spinal structures.
Microfragmented adipose tissue (MFAT) comes from a small sample of the patient’s own fat. The fat is processed into tiny fragments that keep regenerative cells and their supporting environment intact. MFAT provides both cushioning and biological signals. It is often chosen for more advanced joint issues, partial tears, or areas that need structural support along with repair (Form Health PDX, 2025).
Epidural injections place anti-inflammatory or regenerative material into the space around spinal nerves. These can reduce irritation from disc problems or stenosis. Regenerative versions may include platelet products to support longer calming of nerves and better participation in rehabilitation (El Paso Chiropractor Blog, 2026).
These options focus on the biological side. They help rebuild weak soft tissues and lower the inflammation that keeps pain going.
How Chiropractic Therapy Restores Motion and Unloads Strain
Chiropractic therapy addresses the mechanical side of the problem. Joints that do not move correctly create extra stress on nearby muscles, ligaments, and discs. Over time, this stress can slow healing or cause new issues.
Precise adjustments restore correct joint motion. Soft-tissue techniques reduce muscle tension. Spinal decompression and posture training help unload compressed or strained structures. Movement retraining and simple exercises teach the body better patterns so the same injury is less likely to return.
When joints move freely again, the regenerative treatments have a better environment in which to work. Healthy alignment means less repeated strain on the tissues that are trying to heal (NewRegen Ortho, 2021).
Why the Two Approaches Work Better Together
One side of care rebuilds tissue at the cellular level. The other restores healthy joint mechanics and reduces load on damaged areas. Supporting literature and clinical experience show that biologics alone are rarely enough. Structured rehabilitation and mechanical correction improve long-term results. When growth factors reach tissues that are no longer under constant abnormal stress, recovery tends to be more complete and lasting (Nortex Spine and Joint, n.d.; The Osteo Center, n.d.).
This layered approach is especially beneficial after personal injury. Auto accidents often create both soft-tissue damage and joint dysfunction. Treating only one side leaves the other problem unaddressed. Combining the two helps patients regain strength, reduce medication needs, and return to daily activities with more confidence (Health Coach Clinic, n.d.).
A Multidisciplinary Team in El Paso
At Injury Medical Clinic PA in El Paso, Texas, this integrated model is put into practice every day. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides chiropractic care, functional medicine insights, rehabilitation guidance, and personal injury documentation. His clinical observations, shared through his practice sites, emphasize that mechanical alignment prepares the body for biological repair and that both must be addressed for lasting results (Jimenez, n.d.).
Working alongside him is Dr. Maria Guadalupe Cardenas, MD. She is board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933) and brings more than 40 years of experience as an internist. Dr. Cardenas serves as medical director and collaborative physician. She provides medical oversight, reviews complex health histories, and helps ensure safety protocols are followed. This partnership is common in integrative injury clinics: the chiropractor handles musculoskeletal and functional care while the medical director supplies internal-medicine expertise and collaborative guidance.
The clinic also weaves in functional medicine. This looks at nutrition, sleep, inflammation, gut health, hormones, and metabolic factors that influence how well tissues heal. Rehabilitation services, personal injury care coordination, and related therapies round out the plan. Patients receive detailed evaluations and personalized steps that move from reducing inflammation to rebuilding tissue to restoring full function.
Practical Benefits Patients Notice
People who use this combined approach often report several advantages:
Faster progress in reducing pain and swelling
Improved joint motion that feels more stable
Better ability to take part in physical therapy
Lower chance of the same injury returning
Clearer documentation for injury claims when needed
Athletes appreciate the support for return-to-activity timelines when regenerative treatments are paired with proper loading and alignment work. People with chronic joint or spine problems value the chance to avoid repeated steroid injections or surgery when appropriate (OrthoRepair, n.d.; Form Health PDX, 2025).
What to Expect on the Care Journey
Care usually begins with a thorough exam, imaging when needed, and a clear discussion of goals. Regenerative injections are performed with guidance such as ultrasound for accuracy. Chiropractic sessions focus on restoring motion and reducing mechanical stress. Functional medicine recommendations may include nutrition and lifestyle steps that support healing from the inside. Rehabilitation progresses from gentle movement to strength and activity-specific tasks.
Results build over weeks rather than overnight. Early progress often shows as less pain and better daily function. Longer-term gains include stronger tissue and more reliable joint performance.
Moving Forward with a Complete Plan
Regenerative medicine and integrative chiropractic therapy form a practical partnership. One side targets inflammation and rebuilds weak soft tissues at the cellular level. The other restores correct joint motion and unloads strained structures. When guided by an experienced multidisciplinary team—like the collaboration between Dr. Alexander Jimenez and Dr. Maria Guadalupe Cardenas at Injury Medical Clinic PA—patients receive coordinated support that addresses both biology and biomechanics.
This approach offers a clear path for those seeking lasting recovery. It respects the body’s ability to heal while giving it the right conditions to do so. Anyone dealing with soft-tissue injuries, joint problems, or personal-injury recovery can explore whether this combined model fits their needs through a careful evaluation with a qualified team.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine