Med-Legal Corner
Back Clinic Med-Legal Corner. Medical law is a branch of law that concerns the prerogatives and responsibilities of medical professionals and the rights of the patient. It should not be confused with medical jurisprudence, which is a branch of medicine, rather than a branch of law. The main branches of medical law are the law of torts (most notably medical malpractice) and criminal law in relation to medical practice and treatment. Ethics and medical practice are a growing field.
After working in chiropractic for 30+ years, especially in personal and work injuries. In the Med-legal corner, Dr. Jimenez knows the ins and out’s of what goes into personal and work injury claims. Receiving chiropractic care from a personal injury doctor after suffering an injury can be a lifesaver. As a personal injury chiropractor has attended post-graduate training in accident injury evaluation and treatment which can guarantee a more effective diagnosis and care.
An added bonus is that the chiropractor can do depositions and testify in court. A personal injury doctor works closely with multiple attorneys. The best chiropractors maintain a list of attorneys they know can deliver quality results to their patients in a car accident and personal injury cases. A doctor that has connections with more than one attorney offers a wide variety of experienced personal injury claim professionals to choose from, who can better accommodate you to solve your specific case after an accident. For answers to any questions you may have please call Dr. Jimenez at 915-850-0900

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Chiropractic Examination, Imaging & Diagnostics, Injury Care, Lower Back Pain, Med-Legal Corner, Personal Injury, Spine Care
Why Changing Back Pain Diagnoses During Rehabilitation May Reflect Better Clinical Understanding
After a collision on I-10, Carlos, a 42-year-old warehouse supervisor from El Paso, walked into the clinic with intense low-back pain that made sitting, bending, and even standing long enough to finish a shift feel impossible. Two days after the rear-end impact, his lumbar muscles were locked in protective spasm, swelling limited his ability to twist or extend, and every movement provoked sharp local pain. The first examination pointed to an acute lumbar strain with facet joint irritation—an understandable starting point when inflammation still masks deeper findings. By the second visit, the picture had already begun to shift. By the third, objective imaging and clearer symptoms allowed a more precise diagnosis of a traumatically aggravated lumbar disc injury. Far from signaling inconsistency, these evolving impressions demonstrated careful clinical reasoning that ultimately strengthened both his recovery path and the medical-legal record.

Initial findings in acute spinal trauma are often provisional by necessity. In the first 48–72 hours, inflammatory chemicals flood the injured tissues, producing swelling, muscle guarding, and reduced range of motion that can obscure the full extent of disc, ligament, or nerve involvement. Guidelines and clinical observation confirm that many patients present with nonspecific low-back pain until the acute inflammatory stage begins to resolve. As swelling decreases, patients can better describe the character and radiation of their symptoms, orthopedic tests become more reliable, and clinicians can distinguish simple muscular strain from patterns that suggest disc or nerve-root irritation. When symptoms persist or change in quality, imaging is appropriately obtained and interpreted in the context of the mechanism of injury, the timeline, and serial examinations. Alternative explanations—pre-existing degeneration, subsequent activity, or unrelated conditions—are systematically considered and either ruled out or incorporated. This refinement process is a hallmark of good care, not a sign of error.
Visit One: The Acute Phase and a Provisional Working Diagnosis
Carlos arrived two days after the collision. His history matched the mechanics of rapid deceleration: seat-belt restraint, torso thrust, and immediate low-back pain. Examination showed limited lumbar flexion and extension, tenderness over the paraspinal muscles and lower facets, and a negative straight-leg raise limited by back pain alone. Swelling and spasm made precise segmental testing difficult. The working diagnosis recorded that day was acute lumbar sprain/strain with possible facet irritation secondary to the motor-vehicle collision. Treatment focused on reducing inflammation, restoring gentle motion, and protecting the tissues while they began to settle. Chiropractic adjustments were deferred until guarding decreased; instead, soft-tissue work, gentle mobilization, and education on activity modification helped him manage pain and maintain as much function as possible. Objective measures, including a baseline Oswestry Disability Index, documented the functional impact so that later changes could be compared against a clear starting point.
Visit Two: Swelling Subsides and Symptoms Clarify
Ten days later, the protective muscle spasm had eased. Carlos could now describe a deep, aching low-back pain that occasionally traveled into the buttock and the back of the thigh when he sat for more than twenty minutes or lifted a light box at work. Kemp’s test and repeated extension reproduced familiar symptoms; the straight-leg raise remained limited but now produced mild buttock referral. These findings raised the possibility of disc involvement masked by early swelling. The clinical note explicitly recorded the reasoning: “Initial acute inflammatory presentation limited differential. With reduced edema, radicular-pattern symptoms and provocative testing now support consideration of intervertebral disc injury at the lower lumbar levels. MRI ordered to correlate clinical findings and rule out alternative structural causes.” This documentation is essential. It shows the diagnosis was not arbitrarily changed but updated based on new, objective information. Serial functional scores and range-of-motion measurements further demonstrated that the clinical picture was evolving in a biologically plausible way.
Visit Three: Imaging Confirms, and the Diagnosis Is Refined
MRI obtained in the fourth week revealed a moderate protrusion at L4–5 with annular fissuring, consistent with the timing of the collision and the emerging leg symptoms. Mild pre-existing disc desiccation was noted, yet the acute morphology and symptom correlation supported traumatic aggravation of the disc rather than purely degenerative change. The updated diagnosis—lumbar intervertebral disc protrusion with mild radicular component, traumatically aggravated by the collision—was accompanied by a clear narrative of clinical reasoning: mechanism of injury, temporal relationship, progressive findings once swelling subsided, exclusion of red-flag alternatives, and correlation with imaging. Treatment shifted toward targeted disc decompression, directional preference exercises, and progressive core stabilization while medical oversight addressed any metabolic factors that could slow healing. Patients gain measurable benefits from this approach: reduced nerve irritation, improved sitting and lifting tolerance, better sleep, and a clearer path back to work without reliance on prolonged medication or early surgery.
Documenting the Clinical Reasoning
behind each diagnostic shift protects both the patient and the legal record. In personal-injury cases, defense experts frequently argue that changing diagnoses indicate uncertainty or exaggeration. Thorough notes that explain why new information warranted an updated impression neutralize that argument. They establish the proximate link between the collision forces and the objective injury, support Letters of Protection, and demonstrate that the care plan remained evidence-based as the clinical picture clarified. Tools such as the Oswestry Disability Index, digital range-of-motion measurements, and consistent orthopedic testing provide the objective anchors that allow these evolving impressions to withstand scrutiny. Readers seeking a deeper understanding of how mechanism, timeline, and serial findings establish causation can review the clinic’s detailed discussion of medical-legal causation principles.
Careful Documentation also Serves the Three Bioethical Pillars that Guide Care
Beneficence is realized when the multidisciplinary team—chiropractic biomechanical assessment, nurse-practitioner soft-tissue and functional evaluation, and internal-medicine oversight—works together to identify the true source of pain and address it at its root rather than merely masking symptoms. Non-maleficence is honored by favoring non-invasive options such as chiropractic adjustment, electroacupuncture, and targeted rehabilitation that reduce the risks associated with opioid dependency or premature surgery. Autonomy is strengthened when patients receive clear explanations of why their diagnosis may evolve, what each new finding means, and how they remain active partners in decisions about imaging, activity, and treatment goals. Coordination with the patient’s existing medical providers further supports informed choice.
What makes Injury Medical Chiropractic and Functional Medicine Clinic unique is its integrated structure, which makes this level of precision possible. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than forty years of experience, directs the clinic and provides medical direction, advanced laboratory interpretation, and risk stratification. Working alongside her is Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, a dual-licensed chiropractor and board-certified family nurse practitioner who specializes in soft-tissue injury, structural alignment, and the objective documentation required for personal-injury cases. This dual-licensure model—medical director plus nurse practitioner specializing in soft-tissue injury—is the only integrated arrangement of its kind in El Paso, Texas, allowing the same clinical team to generate both the biomechanical findings and the medical reasoning that appear in a single, coherent causation file.
Readers who wish to explore related topics will find practical guidance on the stages of healing from neck or back injuries, the proper nomenclature for lumbar disc findings, and auto-accident management strategies for sciatica and herniated discs. Each of these resources reinforces the same principle illustrated by Carlos’s three visits: better clinical understanding is not a fixed label applied on day one but a progressive process of observation, testing, and documented reasoning that ultimately produces a clearer diagnosis, more effective treatment, and a more defensible medical-legal record.
References
Brumitt, J., & Cuddeford, T. (2015). Current concepts of muscle and tendon adaptation to strength and conditioning. International Journal of Sports Physical Therapy, 10(6), 748–759. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4637912/
Duchesne, E., Dufresne, S. S., & Dumont, N. A. (2017). Impact of inflammation and anti-inflammatory modalities on skeletal muscle healing: From fundamental research to the clinic. Physical Therapy, 97(8), 807–817. https://doi.org/10.1093/ptj/pzx056
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Gabriel Rothman, S. L., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology, and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Johnsen, L. G., Hellum, C., Nygaard, Ø. P., Storheim, K., Brox, J. I., Rossvoll, I., Leivseth, G., & Grotle, M. (2013). Comparison of the SF6D, the EQ5D, and the Oswestry Disability Index in patients with chronic low back pain and degenerative disc disease. BMC Musculoskeletal Disorders, 14, Article 148. https://doi.org/10.1186/1471-2474-14-148
Wu, Y. S., & Chen, S. N. (2014). Apoptotic cell: Linkage of inflammation and wound healing. Frontiers in Pharmacology, 5, Article 1. https://doi.org/10.3389/fphar.2014.00001

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Herniated Disc, Imaging & Diagnostics, Med-Legal Corner, Personal Injury
What a Lumbar Spine MRI Can and Cannot Tell a Jury About an Accident-Related Disc Injury
A lumbar spine MRI provides one of the clearest pictures medicine can give a jury of what is happening inside the low back after a crash, fall, or workplace impact. It shows the discs, the nerves, and the surrounding structures in high detail. Yet the same scan that reveals a herniation or compressed nerve root often leaves the most important legal questions unanswered: When did this finding appear, and was the accident the cause?
Defense experts frequently point to the MRI and call every abnormality “pre-existing degeneration.” That argument succeeds when the imaging is presented in isolation. It weakens when the MRI is viewed alongside the patient’s history, the collision mechanics, the examination findings, and serial clinical notes. Understanding what the scan can and cannot prove helps patients, clinicians, and attorneys interpret the evidence correctly.
How MRI Shows Lumbar Disc Herniations and Nerve Root Compression
The intervertebral disc has a soft, gel-like center (nucleus pulposus) surrounded by a tough outer ring (annulus fibrosus). On a T2-weighted MRI, the healthy nucleus appears bright because it holds water. When the annulus tears and nuclear material pushes outward, the MRI shows the displaced material as a protrusion, extrusion, or sequestration.
A herniation is called focal when it involves less than 25 percent of the disc circumference. Posterolateral herniations are the most common pattern after trauma because the posterior longitudinal ligament is thinner on the sides. When herniated material compresses a nerve root in the lateral recess or foramen, MRI can show the root flattened or displaced. Surrounding soft-tissue edema or a high-intensity zone (HIZ)—a bright spot on T2 images within the posterior annulus—further signals an acute or subacute annular tear.
Nerve-root compression is not always dramatic. Mild contact may still produce radicular pain through chemical inflammation from the herniated material rather than pure mechanical pressure. Clinical correlation remains essential: the side and level of the imaging finding must match the patient’s leg pain, numbness, or reflex changes. Digital range-of-motion measurements and electrodiagnostic studies (when indicated) help confirm that the compressed root, not an incidental finding, is causing the symptoms.
Degenerative Findings That Commonly Appear on MRI
Disc desiccation (darkening of the nucleus), multilevel bulging, small osteophytes, and mild facet arthropathy appear on MRI scans of many adults who have never been in a crash and who have no pain. Large population studies show that roughly one-third of asymptomatic people in their twenties already have disc bulges or protrusions; by the seventies and eighties the rate approaches 90 percent. These age-related changes do not automatically mean a patient’s current pain is unrelated to trauma.
The key distinction is between symmetric, multilevel, slowly progressive degeneration and a focal, asymmetric finding that matches the biomechanics of the accident and the patient’s new symptoms. An annular high-intensity zone that is bright, a few millimeters of unilateral disc-height loss, or a new extrusion at the level and side of impact is far more suggestive of traumatic aggravation than uniform drying across five levels.
MRI nomenclature follows standardized terms. A bulge is a broad-based extension greater than 25 percent of the circumference, usually from annular redundancy as the disc loses height. A protrusion remains contained by outer annular fibers; an extrusion has broken through them. These distinctions matter for both treatment planning and for explaining the finding to a jury, but the nomenclature itself does not assign cause or date. The official lumbar disc nomenclature notes that dating a herniation from images alone is unreliable; bright signal and surrounding inflammation suggest relative acuteness, yet those changes can persist for months.
Why the MRI Alone Does Not Establish Age or Cause
An MRI is a snapshot. It doesn’t carry a time stamp saying, “This herniation occurred on the day of the collision.” Even an acute-appearing high-intensity zone can remain bright for many months. Without prior imaging, the radiologist cannot know whether a disc protrusion existed silently before the crash. That is why defense experts correctly state that the presence of a herniation on MRI does not, by itself, prove the accident caused it.
Causation is established by linking several elements:
- The patient had no comparable radicular symptoms before the event.
- The mechanism (axial compression plus flexion or lateral shear typical of rear-end or side-impact collisions) is capable of tearing the annulus and forcing nuclear material posterolaterally.
- Symptoms began or dramatically increased shortly after the impact.
- The MRI finding matches the level, side, and clinical examination.
- Serial notes document ongoing functional limitations that track the imaging abnormality.
When these elements are present, the MRI becomes powerful objective evidence of traumatic aggravation under the Texas Eggshell Plaintiff rule. A pre-existing, asymptomatic disc that is torn and made symptomatic by the crash is still a compensable injury. The clinic’s records capture this linkage in plain language so that the attorney and the jury can follow the chain from collision forces to specific MRI morphology.
The Role of Clinical Correlation and Multidisciplinary Documentation
Radiology reports describe anatomy; they do not decide legal causation. The treating clinician must integrate the images with the history, the physical examination, and the functional status. Digital range-of-motion testing, postural analysis, and response to conservative care provide additional objective data that MRI alone cannot.
At Injury Medical Clinic PA, the dual-licensed team coordinates these pieces. Dr. Alex Jimenez, DC, APRN, FNP-BC, documents soft-tissue and structural findings, correlates them with the mechanism of injury and MRI, and tracks the response to non-invasive care. Dr. Maria Guadalupe Cardenas, MD, provides medical direction, reviews metabolic and inflammatory factors that affect disc healing, and ensures the overall clinical picture is medically coherent. The result is a continuous, Colossus-compliant record that withstands cross-examination far better than isolated imaging reports.
Patients benefit from this approach through clearer understanding of their condition, safer non-drug options such as targeted chiropractic care, spinal decompression, and electroacupuncture, and better coordination with any outside physicians. Attorneys receive the objective linkage needed for Letters of Protection and trial. Clinicians outside the clinic can rely on the same transparent interpretation when they review the records.
What Makes the Clinic Unique
- Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is the only practice in El Paso, Texas, that integrates a board-certified internal medicine medical director with a dual-licensed chiropractor and nurse practitioner who specializes in soft-tissue and disc injury.
- Dr. Maria Guadalupe Cardenas, MD, provides medical direction and advanced laboratory oversight for patients with metabolic conditions that affect recovery.
- Dr. Alex Jimenez, DC, APRN, FNP-BC, focuses on the structural and soft-tissue consequences of trauma, using precise imaging correlation, digital functional testing, and non-invasive therapies. This single-clinic model produces unified documentation rather than fragmented records from separate providers, giving both patients and attorneys a clearer, more defensible account of how the accident affected the lumbar spine.
For deeper discussion of how imaging findings are tied to causation, see the detailed review of advanced spinal MRI interpretation for attorneys at dralexjimenez.com and the explanation of why abnormal MRI findings do not automatically establish injury age. The standardized lumbar disc nomenclature used in these reports is also available for reference.
An MRI is indispensable, but it is only one piece of the story. Read in context with the mechanism, history, and clinical course, it becomes courtroom-ready evidence of traumatic disc injury rather than an ambiguous picture the defense can relabel as ordinary aging.
Feeling Better Than Ever After a Semi-Truck Accident | El Paso, TX
References
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. https://doi.org/10.3174/ajnr.A4173
Fardon, D. F., & Milette, P. C. (2001). Nomenclature and classification of lumbar disc pathology: Recommendations of the combined task forces of the North American Spine Society, American Society of Spine Radiology, and American Society of Neuroradiology. Spine, 26(5), E93–E113. https://doi.org/10.1097/00007632-200103010-00006
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Gabriel Rothman, S. L., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Aprill, C., & Bogduk, N. (1992). High-intensity zone: A diagnostic sign of painful lumbar disc on magnetic resonance imaging. British Journal of Radiology, 65(773), 361–369. https://doi.org/10.1259/0007-1285-65-773-361
Boden, S. D., Davis, D. O., Dina, T. S., Patronas, N. J., & Wiesel, S. W. (1990). Abnormal magnetic-resonance scans of the lumbar spine in asymptomatic subjects. A prospective investigation. Journal of Bone and Joint Surgery, 72(3), 403–408. https://doi.org/10.2106/00004623-199072030-00013
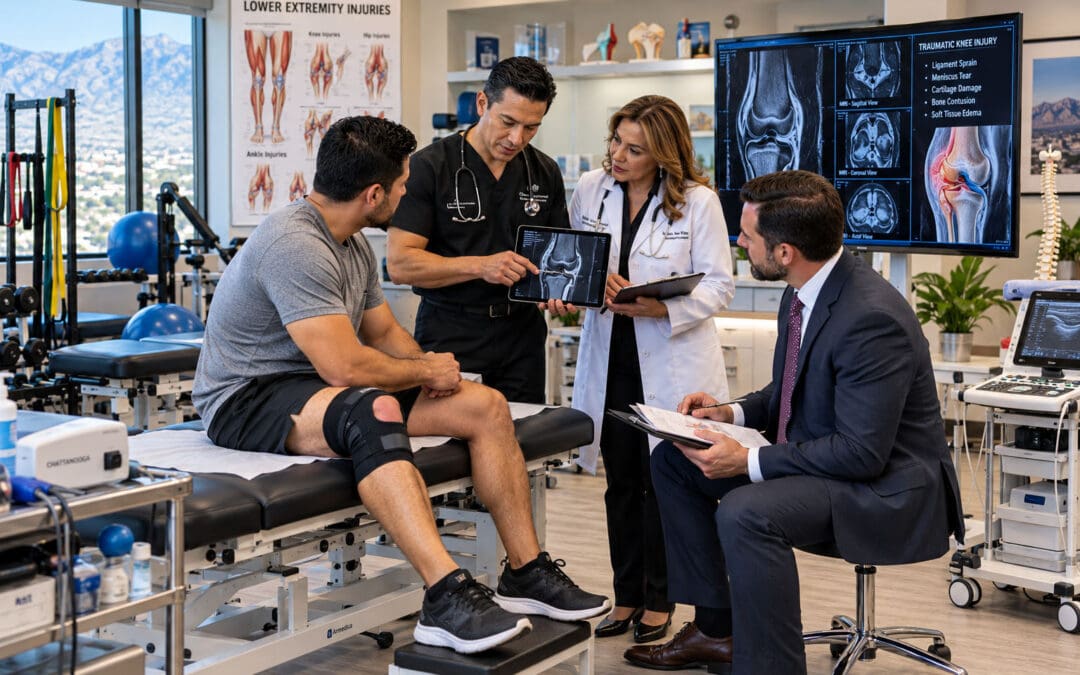
by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Chiropractic Examination, Imaging & Diagnostics, Lower Back Pain, Med-Legal Corner
Why the Location of Back Pain Matters When an Accident Injury Is Disputed
After a car crash, slip-and-fall, or workplace accident, a patient may tell a doctor, “My back hurts.” Clinically, that statement is only the beginning.
Where does the pain begin? Does it stay in the center of the lower back? Is it stronger on one side? Does it spread into the buttock, thigh, calf, or foot? Is there numbness, tingling, weakness, or a change in walking?

Those details matter because the location and distribution of back pain can help clinicians determine whether a patient’s symptoms fit a proposed structural or neurological diagnosis. They become even more important when an insurance company, defense expert, or opposing attorney disputes whether an accident caused the condition.
Pain location does not prove causation by itself. Instead, clinicians look for agreement among the patient’s history, spinal examination, neurological findings, functional limitations, diagnostic imaging, and accident mechanism.
Back Pain Is a Symptom, Not a Diagnosis
Back pain can arise from many structures. Muscles, ligaments, spinal joints, intervertebral discs, nerve roots, and the sacroiliac region can all produce pain in or around the lower back. Conditions outside the spine can sometimes produce similar symptoms.
That is why clinicians begin by defining the pattern.
Pain centered across the lumbar region may be associated with muscular, joint, or disc-related problems. One-sided pain around the lower back or buttock can originate from several musculoskeletal structures. Pain that travels from the back or buttock down a leg raises additional questions about nerve involvement, particularly when it occurs with numbness, tingling, weakness, or altered reflexes.
Clinical research supports evaluating lumbosacral radicular pain through a combination of symptom history, pain distribution, examination findings, and additional testing when appropriate—not through one symptom in isolation (Peene et al., 2024).
Patients wanting a deeper explanation of radiating symptoms can review Dr. Jimenez’s discussion of radiculopathy and sciatica.
Why the Location of Back Pain Matters
Imagine two people with lower-back pain after similar rear-end collisions.
The first person has soreness mainly in the lumbar muscles and stiffness when bending.
The second has lower-back pain that travels through one buttock, down the outside of the leg, and toward the foot. That patient also reports tingling and difficulty walking on the heel.
Both patients have back pain, but their clinical presentations are different.
The second pattern raises more concern for possible nerve-root involvement. A clinician would therefore pay particular attention to sensation, muscle strength, reflexes, gait, and neural tension during the examination.
Research has found that findings such as sensory disturbance, myotomal weakness, decreased reflexes, focal muscle changes, and certain neural tension findings can support a diagnosis of radiculopathy when interpreted together (Bateman et al., 2025).
Pain Patterns Are Helpful—but They Are Not Perfect Maps
Clinicians sometimes compare radiating pain to dermatomes, areas of skin associated with particular spinal nerve roots.
However, the human nervous system doesn’t always follow a textbook diagram.
Studies of patients with confirmed lumbar nerve-root problems have found substantial overlap between pain distributions. Therefore, a patient does not need to trace a perfect line on a dermatome chart for a nerve problem to be possible.
This distinction is especially important in personal injury cases. Pain distribution can support a diagnosis, but it shouldn’t be used alone to claim a particular disc or nerve root caused the symptoms.
The stronger question is:
Does the complete neurological and biomechanical pattern make sense?
What a Spinal Examination Looks For
When accident-related back pain is disputed, a thorough examination provides information that a pain rating alone cannot.
A clinician may compare both sides of the body and evaluate how the patient moves, walks, bends, sits, and responds to specific tests. Common examination components can include:
- Lumbar range of motion and movement tolerance
- Palpation for tenderness, muscle guarding, or spasm
- Orthopedic and neurological provocation testing
- Straight-leg raise or related neural tension procedures
- Lower-extremity muscle strength
- Sensory testing
- Patellar and Achilles reflexes
- Heel and toe walking
- Gait and balance
- Functional tolerance for sitting, standing, bending, lifting, and walking
No single examination maneuver proves a spinal diagnosis.
Newer research has made that point even clearer. A 2026 systematic review found that the straight-leg raise and crossed straight-leg raise tests, by themselves, generally produced only limited changes in the probability of lumbosacral radicular pain. The practical lesson is that clinicians should combine tests rather than diagnose based on one positive maneuver (Nee et al., 2026).
Do the Symptoms Match the Structural Diagnosis?
Suppose an MRI identifies a lumbar disc herniation.
That finding matters, but another question immediately follows:
Does the disc finding explain this patient’s symptoms?
A stronger clinical match includes a disc abnormality that can affect a particular nerve root, pain and sensory complaints in a reasonably compatible area, corresponding strength or reflex changes, and functional limitations consistent with the involved nerve.
Current WFNS Spine Committee recommendations emphasize history, pain localization, muscle strength, sensory testing, sphincter function, and appropriate neurological testing when evaluating suspected lumbar disc herniation. MRI is the preferred imaging study to confirm a suspected disc herniation when advanced imaging is clinically warranted (Pojskic et al., 2024).
Dr. Jimenez provides additional patient education about lumbar herniated discs and sciatica.
An MRI Finding Is Not Automatically Proof of Accident Causation
This distinction is critical for both patients and attorneys.
An MRI can show anatomy. It may demonstrate a disc protrusion, herniation, stenosis, degeneration, or another abnormality. But the image alone usually cannot tell an attorney exactly when that abnormality developed or whether a specific collision made it symptomatic.
Some spinal abnormalities can exist before an accident without producing significant symptoms.
That is why clinicians correlate imaging with the history and examination rather than simply pointing to an MRI and declaring causation.
Current recommendations also discourage routine imaging for uncomplicated acute low-back pain. Imaging becomes more appropriate when red flags are present, radicular symptoms persist, neurological deficits progress, or another clinical reason warrants further investigation (Gushcha et al., 2024).
What If the Pain Pattern Does Not Fit?
A careful clinician should not try to force every symptom into a spinal diagnosis.
Hip disorders, tendon injuries, muscle problems, peripheral nerve disorders, neuropathy, vascular conditions, and other musculoskeletal conditions can sometimes resemble lumbar radiculopathy. Some can even coexist with a spinal injury.
A recent review emphasized the importance of distinguishing true lumbosacral radiculopathy from musculoskeletal conditions that can produce similar radiating pain or weakness (Bateman et al., 2025).
This differential diagnosis becomes especially valuable when an injury claim is challenged.
A medically defensible causation opinion should identify reasonable competing explanations, evaluate them, and explain why the available evidence supports or does not support each possibility.
Connecting the Accident Mechanism to the Symptoms
The next step is to ask whether the accident mechanism is compatible with the proposed injury.
Motor-vehicle crashes can expose the spine and surrounding soft tissues to rapid acceleration, deceleration, compression, rotation, or combined forces. Depending on the circumstances, those forces may affect muscles, ligaments, joints, discs, or neural structures. Dr. Jimenez discusses these mechanisms further in his resource on spinal injuries following motor-vehicle collisions.
Consider a patient who had no meaningful radiating leg symptoms before a crash but soon afterward developed unilateral low-back pain extending into the leg. The examination then identifies compatible sensory loss, weakness, or reflex changes, and clinically appropriate imaging demonstrates a corresponding structural abnormality.
That sequence provides a more coherent causation analysis than simply saying, “The MRI showed a disc problem.”
Clinicians also review prior injuries, previous imaging, medical conditions, treatment history, subsequent accidents, and other possible causes. Injury Medical Clinic’s current medical-legal guidance similarly emphasizes evaluating symptom timing, prior history, neurological findings, imaging, functional limitations, and alternative causes rather than relying on one test.
Attorneys can review that discussion in Medical-Legal Causation Opinions for Attorneys Explained.
Functional Limitations Add Another Layer of Evidence
Pain tells clinicians what the patient feels. Function shows what the condition prevents the patient from doing.
An accident victim may have difficulty sitting through a workday, getting out of a vehicle, lifting a child, climbing stairs, carrying groceries, sleeping comfortably, exercising, or walking for extended periods.
Documenting those limitations helps connect the diagnosis to real-world impairment.
Repeated examinations are also valuable. If strength, range of motion, walking tolerance, and everyday function improve as the patient recovers, clinicians can compare those objective and functional changes over time.
That creates a more complete clinical record than repeatedly documenting only “pain 7/10.”
What Makes Injury Medical Chiropractic and Functional Medicine Clinic Different?
Injury Medical Chiropractic and Functional Medicine Clinic in El Paso uses a multidisciplinary structure that brings structural, neurological, functional, and medical evaluations together.
The Natural Way to Heal: Non-Surgical Chiropractic Care for Pain Relief | El Paso, TX
Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of experience, serves as Medical Director and Collaborative Physician. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, is dual-licensed as a Doctor of Chiropractic and board-certified Family Nurse Practitioner. This allows the clinic to coordinate chiropractic biomechanics and soft-tissue injury evaluation with advanced-practice nursing assessment and medical oversight. The clinic website confirms Dr. Cardenas’s medical-director role and Dr. Jimenez’s dual clinical credentials.
The clinic describes this coordinated combination of chiropractic care, medical oversight, soft-tissue injury evaluation, rehabilitation, diagnostic assessment, acupuncture/electroacupuncture, and advanced treatment options as a unique model in El Paso. Rather than requiring every patient to follow the same protocol, the multidisciplinary approach matches treatment and referrals to examination findings, medical risk, patient preferences, and existing healthcare relationships.
That approach also supports three important principles: helping patients recover function and reduce pain, choosing conservative and non-invasive options when appropriate, and giving patients enough information to participate meaningfully in decisions about their care.
When Back Pain Needs More Urgent Evaluation
Conservative spine care may help appropriate patients improve pain, mobility, sleep, and physical function. Clinicians may incorporate chiropractic care, rehabilitation, mobility work, acupuncture, and electroacupuncture when clinically appropriate.
But treatment should always follow the diagnosis.
New bowel or bladder dysfunction, saddle-area numbness, rapidly progressive leg weakness, significant neurological deterioration, or other signs of serious neural compression require urgent medical assessment rather than routine musculoskeletal treatment. Guidelines specifically identify progressive neurological deficits and bowel or bladder dysfunction as reasons for further investigation.
The Bottom Line: Location Helps Build the Clinical Story
When an accident-related back injury is disputed, where the pain occurs matters—but it’s only the beginning of the analysis.
Strong clinical reasoning looks for agreement among the accident mechanism, symptom timing, pain distribution, spinal examination, neurological findings, imaging, medical history, competing explanations, and functional limitations.
For patients, the lesson is simple: describe your symptoms precisely. Tell your clinician where the pain starts, where it travels, whether you experience numbness or weakness, which movements make it worse, and what you can no longer do comfortably.
For attorneys, the lesson is equally important: don’t evaluate a spinal injury claim based on a single MRI phrase or pain score. Look at whether the complete clinical record demonstrates a coherent relationship between the mechanism of trauma, the patient’s symptoms, objective findings, diagnosis, and resulting functional impairment.
A well-documented examination does more than attach a diagnostic label to back pain.
It explains why the diagnosis fits—or does not fit—the patient standing in front of the clinician.
References
Bateman, E. A., Fortin, C. D., & Guo, M. (2025). Musculoskeletal mimics of lumbosacral radiculopathy. Muscle & Nerve, 71(5), 816–832. PubMed record
Gushcha, A. O., Sharif, S., Zileli, M., Oertel, J., Zygourakis, C. C., & Yusupova, A. R. (2024). Acute back pain: Clinical and radiologic diagnosis: WFNS Spine Committee recommendations. World Neurosurgery: X, 22, 100278. PubMed record
Nee, R. J., Boyd, B. S., Sierra-Silvestre, E., & Coppieters, M. W. (2026). Diagnostic accuracy of the straight leg raise test for lumbosacral radicular pain: A systematic review with meta-analysis. Musculoskeletal Science and Practice, 86, 103666. PubMed record
Peene, L., Cohen, S. P., Kallewaard, J. W., Wolff, A., Huygen, F., van de Gaag, A., Monique, S., Vissers, K., Gilligan, C., Van Zundert, J., & Van Boxem, K. (2024). Lumbosacral radicular pain. Pain Practice, 24(3), 525–552. PubMed record
Pojskic, M., Bisson, E., Oertel, J., Takami, T., Zygourakis, C., & Costa, F. (2024). Lumbar disc herniation: Epidemiology, clinical and radiologic diagnosis—WFNS Spine Committee recommendations. World Neurosurgery: X, 22, 100279. PubMed record

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Herniated Disc, Med-Legal Corner, Personal Injury, Spinal Decompression Treatments
Why Mechanism-to-MRI Linkage of Disc Injury Is Required to Justify Lumbar Causation at Trial
Abstract
Defense counsel routinely labels annular tears and modest disc-height loss as “pre-existing degeneration.” A precise mechanism-to-MRI linkage—correlating specific highway force vectors (axial compression, lateral shear, rotation) to the level, side, and morphology of the imaging findings—is required to establish clinical and proximate causation under Texas law and to support special damages for future non-surgical care. This article shows attorneys how structural MRI, timed to the collision and interpreted against the Texas Eggshell Plaintiff framework, neutralizes those challenges while future-care projections for extracorporeal shockwave therapy (ESWT) and spinal decompression document ongoing structural needs.
Imagine the defense expert in an El Paso courtroom pointing at a lumbar MRI and stating, “The annular fissure and 2 mm height loss are age-related.” Without a clear biomechanical bridge from the crash forces to those exact findings, the jury is left with competing medical opinions, and the claim is vulnerable. Mechanism-to-MRI linkage supplies that bridge. It converts a radiologic observation into courtroom-ready evidence of traumatic aggravation.
The Trial Reality of Annular Tears and Disc-Height Challenges
Annular tears (more precisely termed annular fissures in NASS nomenclature) and measured disc-height loss are the two findings most often attacked as pre-existing. Defense radiologists emphasize that high-intensity zones on T2-weighted images can appear in asymptomatic individuals and that modest height loss is common after age 40 (Fardon et al., 2014). Attorneys therefore need more than the finding’s mere presence; they must show that the morphology, laterality, and timing match the collision’s known force vectors and differ from multilevel, symmetric baseline degeneration.
Texas law does not require a perfectly healthy spine. Under the Eggshell Plaintiff doctrine (PJC 28.8 series), the defendant takes the plaintiff as found. If the collision created a new fissure, extended a pre-existing one, or accelerated previously asymptomatic height loss, the resulting functional impairment and future care are compensable (Texas Pattern Jury Charges). The clinical task is to document that acceleration with objective imaging and a reasoned causation narrative.
Correlating Highway Force Vectors to Structural MRI
A high-speed impact on an El Paso corridor transmits forces in milliseconds. Pure axial compression from a rear-end or frontal collision loads the disc vertically, increasing intradiscal pressure and stressing the annulus. Lateral or oblique impacts (common on Loop 375 and similar highways) add shear and rotational components that preferentially load the posterolateral fibers—the anatomically weakest region of the annulus (NCBI StatPearls, 2023). When those forces exceed tissue tolerance, a radial or transverse fissure forms, nuclear material migrates or dehydrates, and measurable height loss appears at the loaded level.
Key imaging correlates that support causation include:
- Single- or dominant-level abnormality matching the predicted segment (commonly L4–L5 or L5–S1 after low-lumbar loading).
- Asymmetric high-intensity zone or height reduction greater on the side of the force vector.
- Temporal relationship: symptoms beginning immediately or within days, with MRI performed after the collision and compared, when available, to any pre-accident imaging.
- Distinction from baseline: the traumatic pattern is focal and asymmetric, while degenerative change is typically multilevel and symmetric.
Clinic notes at Injury Medical Clinic PA capture this linkage in plain language: “The left posterolateral L4–L5 annular high-intensity zone and 2 mm asymmetric disc-height reduction are morphologically and temporally consistent with the lateral shear and rotational forces of the collision. These findings differ from the mild, symmetric multilevel desiccation representing age-related baseline change.” Such statements survive Colossus review and deposition because they rest on biomechanics, not advocacy.
For deeper discussion of how chiropractic and medical records establish causation elements (mechanism, temporal association, biological plausibility, and exclusion of alternatives), see Causation: Understanding Its Role With Chiropractic Care. Attorneys preparing expert reports will also find practical guidance in Medical Legal Causation Opinions for Attorneys Explained.
Future-Care Projections That Support Special Damages
Once the mechanism-to-MRI link is established, the same objective findings justify future non-surgical interventions that restore disc hydration and height. Spinal decompression reduces intradiscal pressure, promotes nutrient inflow, and has been shown to improve height and pain in selected lumbar disc cases (Choi et al., 2017). Extracorporeal shockwave therapy (ESWT) stimulates neovascularization and extracellular-matrix remodeling; recent laboratory and clinical observations indicate it can attenuate endplate degeneration under compressive stress and facilitate resorption of herniated material (Frontiers in Bioengineering and Biotechnology, 2026; Orthopedic Reviews case report, 2026).
These modalities are not speculative. When serial MRI or functional testing demonstrates persistent height loss or annular signal that correlates with ongoing symptoms, a future-care spreadsheet listing a defined course of decompression and ESWT is supported by the same causation evidence that proves the injury. The resulting impairment evidence is packaged inside medical-legal causation documentation standards at https://dralexjimenez.com.
Bioethical Integration of Care
Beneficence is realized when chiropractic spinal adjustments, decompression, and ESWT are combined with MD/NP-directed laboratory and imaging oversight to restore structural integrity at the disc level rather than merely mask symptoms.
Non-maleficence is achieved by prioritizing these non-invasive, drug-free options, thereby delaying or avoiding the risks of surgery or prolonged opioid exposure.
Autonomy places the patient in control of the imaging timeline and treatment decisions. The clinic orders serial MRI scans when clinically indicated, explains results in plain language, and lets the patient coordinate care with any existing medical team.
What Makes the Clinic Unique
- Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is the only practice in El Paso, Texas, that integrates a board-certified internal medicine medical director with a dual-licensed chiropractor/nurse practitioner specializing in soft-tissue and disc injury.
- Dr. Maria Guadalupe Cardenas, MD (Texas License #J2933, NPI 1164426748), provides medical direction, advanced laboratory panels, and risk stratification for complex metabolic comorbidities that influence disc healing.
- Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP (Texas License #1191402, Prescriptive Authority #59628, NPI 1205907805), delivers structural and regenerative interventions—chiropractic adjustments, spinal decompression, ESWT, and electroacupuncture—while maintaining complete collaborative notes that meet clinical and legal standards. This dual-credentialed, single-clinic model eliminates fragmented records and supplies the continuous, objective documentation attorneys require for Letters of Protection and trial.
From Injury to Recovery (with Chiropractic Care) | El Paso, TX
Practical Documentation Checklist for Counsel
- Accident reconstruction or black-box data establishing direction and approximate magnitude of force.
- Immediate or near-immediate symptom onset recorded in emergency or early clinical notes.
- MRI protocol that includes T2 sagittal and axial images with measurements of height loss and description of annular signal laterality.
- Comparison to any pre-accident imaging or, in its absence, clear language distinguishing focal traumatic morphology from multilevel degenerative baseline.
- Functional testing (range of motion, neurologic exam, patient-reported outcome scores) timed to imaging.
- Future-care cost projections tied to the same structural findings that support causation.
When these elements are present, annular tears and disc-height loss stop being defense talking points and become the foundation of special damages. Patients regain mobility and sleep quality through non-invasive care, while attorneys get courtroom-ready proof that the collision—not ordinary aging—caused measurable structural change.
Schedule a comprehensive evaluation at Injury Medical Clinic PA. The team will map the collision’s force vectors to current MRI findings, design a plan to restore disc hydration and height, and prepare the objective documentation needed for trial or settlement.
References
Choi, J., Lee, S., & Hwangbo, G. (2017). Influences of spinal decompression therapy and general traction therapy on the pain, disability, and straight leg raising of patients with intervertebral disc herniation. Journal of Physical Therapy Science, 29(4), 697–699. https://doi.org/10.1589/jpts.29.697
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Rothman, S. L. G., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology, and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Frontiers in Bioengineering and Biotechnology. (2026). ESWT attenuates compressive stress-induced cartilaginous endplate degeneration via modulation of the SOST/Wnt/β-catenin signaling pathway. Frontiers in Bioengineering and Biotechnology, 14, Article 1769920. https://doi.org/10.3389/fbioe.2026.1769920
StatPearls. (2023). Annular disc tear. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK459235/
Texas Pattern Jury Charges—General Negligence, Intentional Personal Torts & Workers’ Compensation. (2024). Committee on Pattern Jury Charges, State Bar of Texas.

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Collision & Injury Dynamics, Med-Legal Corner, Personal Injury, Spinal Decompression Treatments
Annular Tear and Disc Height Loss After Loop 375 Lateral Impact: Mechanism-to-MRI Linkage
A high-speed side impact on El Paso’s Loop 375 can transmit focused lateral shear, axial compression, and rotational forces through the lumbar or cervical spine in a fraction of a second. When those force vectors exceed the tensile strength of the annulus fibrosus—particularly its relatively weaker posterolateral fibers—an acute annular tear can form, allowing nuclear material to migrate and producing measurable disc height loss visible on MRI. At Injury Medical Clinic PA in El Paso, the multidisciplinary team of Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP (Texas License #1191402, Prescriptive Authority #59628, NPI 1205907805) and Medical Director Dr. Maria Guadalupe Cardenas, MD (Board Certified Internal Medicine, Texas License #J2933, NPI 1164426748), systematically links these biomechanical mechanisms to objective imaging so that clinical and proximate causation are clear for patients and attorneys.
How a Loop 375 Lateral Impact Generates Disc Injury
Loop 375 (Joe Battle Boulevard and related segments) is a high-volume corridor where lane changes, side-swipes, and T-bone or angle collisions are common. In a pure lateral impact, the striking vehicle imparts a force vector roughly perpendicular to the struck vehicle’s longitudinal axis. Occupants experience rapid lateral torso acceleration while the pelvis and lower extremities lag or rotate, creating shear across the intervertebral discs and facet joints. At the same time, the sudden change in velocity produces axial compression and, often, a twisting moment as the body rebounds against the seatbelt or door.
The annulus fibrosus consists of concentric lamellae whose fiber orientation alternates for strength; however, the posterolateral region contains a higher proportion of vertically oriented fibers and is a known site of relative weakness (StatPearls, 2023). When lateral shear and rotation are superimposed on compression, these fibers can separate, producing a radial or transverse annular tear. Nuclear material may then extrude or lose hydration and volume, resulting in a measurable reduction in disc height at the affected level. Because the forces are asymmetric, the tear and height loss are often unilateral or more pronounced on the side of impact—an important morphologic clue when compared with the more uniform, multilevel pattern of ordinary age-related degeneration.
MRI Linkage: Reading the Images Through the Force Vectors
On T2-weighted MRI, an acute annular tear typically appears as a high-intensity zone (HIZ)—a focal bright signal within the normally dark annulus caused by increased water content and inflammatory fluid (StatPearls, 2023; Teraguchi et al., 2022). Supporting signs of acute traumatic change, as opposed to a chronic degenerative baseline, include:
- A single or dominant level of abnormality that matches the predicted biomechanics of the impact (for example, L4-L5 or L5-S1 after a low lumbar lateral load, or mid-cervical levels after a higher side-impact).
- Asymmetric height loss or annular signal that is greater on the side of the force vector.
- Associated soft-tissue findings such as ligamentous edema, facet fluid, or paraspinal muscle signal change at the same or adjacent levels.
- Higher T2 hyperintensity and involvement of the outer third of the annulus are more consistent with traumatic disruption than the lower-intensity, inner-two-thirds fissures typical of slow degenerative breakdown (Khurana et al., 2025).
Degenerative disc disease is extremely common and increases with age; imaging studies of asymptomatic volunteers show annular fissures in roughly 19–29% of adults depending on the decade (Brinjikji et al., as cited in clinical radiology reviews). The clinic therefore never equates the mere presence of an HIZ or reduced disc height with trauma. Instead, the team correlates the precise morphology, laterality, and associated acute soft-tissue changes with the documented mechanism, the patient’s immediate post-collision symptoms, and serial clinical examinations. When pre-existing degeneration is present, the records explicitly separate the baseline findings from the new traumatic aggravation—language that prevents defense arguments that “the MRI only shows wear and tear.”
Distinguishing Acute Traumatic Change from Degenerative Baseline
Clear, plain-language documentation is essential. An example of phrasing used in clinic notes and narrative reports reads: “The left posterolateral L4-L5 annular high-intensity zone and 2 mm asymmetric disc-height reduction are morphologically and temporally consistent with the lateral shear and rotational forces of the 14 July Loop 375 side-impact collision. These findings differ from the mild, symmetric multilevel disc desiccation and small inner annular fissures that represent age-related baseline change.” Such statements rest on the mechanism-to-MRI linkage rather than on the radiologist’s impression alone. Digital imaging, functional testing (range-of-motion, neurologic, and strength measures), and Colossus-compliant electronic records further corroborate that the structural changes produce the patient’s objective functional deficits.
Future-Care Modeling with ESWT and Non-Surgical Decompression
Once causation is established, the clinic models evidence-based future care to address both the annular tear and height loss. Non-surgical spinal decompression creates controlled negative intradiscal pressure that can increase disc height and reduce pain; one retrospective cohort demonstrated a statistically significant correlation between restored disc height and decreased low-back pain scores (Apfel et al., 2010). Additional studies confirm improvements in radicular pain and disc morphology after motorized decompression protocols (Choi et al., 2022; Egyptian Rheumatology and Rehabilitation, 2019).
Extracorporeal shock-wave therapy (ESWT) supplies a complementary biologic stimulus. In laboratory models, low-energy ESWT combined with low-tension traction has been shown to restore disc height, improve rehydration, and reduce matrix-degrading enzymes (MMP-3, MMP-13, ADAMTS-4), thereby reshaping the microenvironment for repair (Spine Journal, 2021). Clinical series report pain reduction and facilitation of herniation resorption when ESWT is integrated into staged conservative care (Orthopedic Reviews, 2026; Rehabilitation Medicine, 2024). Because both modalities are non-invasive and drug-free, they align with non-maleficence: they lower the risk of progression to surgery or long-term opioid dependence while still delivering measurable structural and symptomatic benefit.
Unlocking Pain Relief: How We Assess Motion to Alleviate Pain | El Paso, TX
In the future-care cost spreadsheet these interventions appear as a defined course of decompression sessions (typically 20–30 over 6–8 weeks) plus a series of ESWT treatments, accompanied by supportive chiropractic adjustments, neurofunctional acupuncture or electroacupuncture, and functional-medicine laboratory monitoring directed by Dr. Cardenas. The combination targets root-cause healing—restoring disc height and annular integrity where possible, reducing inflammatory cytokines, and improving segmental stability—rather than merely masking pain (beneficence). Patients receive clear education about expected timelines, self-care strategies, and how the plan coordinates with any outside specialists they already see, preserving autonomy and informed decision-making.
Documentation That Withstands Scrutiny
Every element—mechanism narrative, MRI description distinguishing acute from baseline change, functional deficits, and itemized future-care costs—is recorded in a manner suitable for letters of protection and deposition. The dual-licensed perspective of Dr. Jimenez (structural alignment plus advanced practice medical diagnostics), together with Dr. Cardenas’s internal-medicine oversight, supplies both the biomechanical and medical foundation attorneys require. The result is a transparent, mechanism-linked record that supports the patient’s recovery while meeting El Paso personal-injury litigation evidentiary standards.
Patients and counsel seeking this level of integrated causation analysis and future-care planning may contact Injury Medical Clinic PA for a coordinated evaluation.
References
Apfel, C. C., Cakmakkaya, O. S., Martin, W., Richmond, C., Macario, A., George, E., Schaefer, M., & Pergolizzi, J. V. (2010). Restoration of disk height through non-surgical spinal decompression is associated with decreased discogenic low back pain: A retrospective cohort study. BMC Musculoskeletal Disorders, 11, Article 155. https://doi.org/10.1186/1471-2474-11-155
Choi, E., Gil, H. Y., Ju, J., Han, W. K., Nahm, F. S., & Lee, P. B. (2022). Effect of nonsurgical spinal decompression on intensity of pain and herniated disc volume in subacute lumbar herniated disc. International Journal of Clinical Practice, 2022, Article 6343837. https://doi.org/10.1155/2022/6343837
Khurana, B., Khorasani, M., & et al. (2025). Lumbar disc annular tear versus annular fissure: Distinguishing traumatic from degenerative findings on MRI. [PDF]. https://img1.wsimg.com/blobby/go/b1a39d28-bc5a-416f-9f65-e6d871130b13/downloads/f8cc02aa-ed0e-4623-a8fc-400307687027/Khurana%20et%20al%2C%2C%202025%20-%20Lumbar%20disc%20annular%20tea.pdf
National Center for Biotechnology Information. (2023). Annular disc tear. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK459235/
Orthopedic Reviews. (2026). Spontaneous resorption of prolapsed lumbar disc herniation facilitated by extracorporeal shock wave therapy: A case report. Orthopedic Reviews, 17(1). https://orthopedicreviews.openmedicalpublishing.org/article/172374-spontaneous-resorption-of-prolapsed-lumbar-disc-herniation-facilitated-by-extracorporeal-shock-wave-therapy-a-case-report
Rehabilitation Medicine. (2024). Effect of extracorporeal shock wave therapy on different types of lumbar disc herniation. Rehabilitation Medicine, 34(1), 84–89.
Spine Journal. (2021). Low energy extracorporeal shock wave therapy combined with low tension traction can better reshape the microenvironment in degenerated intervertebral disc regeneration and repair. The Spine Journal, 21(1), 160–177. https://doi.org/10.1016/j.spinee.2020.08.012
Teraguchi, M., Cheung, J. P. Y., & Samartzis, D. (2022). High-intensity zones and annular tears. In Spine phenotypes (pp. 187–201). Academic Press. https://doi.org/10.1016/B978-0-12-822778-7.00016-X
El-Sayed, A. M., et al. (2019). Spinal decompression therapy as an alternative modality for management of low back pain and radicular pain caused by lumbar disc herniation or protrusion. Egyptian Rheumatology and Rehabilitation, 46, 161–168. https://doi.org/10.4103/err.err_34_18
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. https://doi.org/10.3174/ajnr.A4173

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Back Pain, Herniated Disc, Imaging & Diagnostics, Lawyers, Med-Legal Corner, Spinal Decompression Treatments
Segmental Disc Compression Patterns Generated by Loop 375 Lateral Impacts
Abstract
Loop 375 lateral impacts in El Paso generate rapid, side-directed force vectors that compress lumbar segments, tear the annulus, and accelerate disc height loss visible on structural MRI. These patterns create clear mechanism-to-injury linkages that support clinical and proximate causation for lumbar claims. At Injury Medical Clinic PA, the dual-licensed team of Dr. Alex Jimenez, DC, APRN, FNP-BC, and collaborating medical director Dr. Maria Guadalupe Cardenas, MD, documents these objective findings with Colossus-compliant notes, functional testing, and imaging timelines. Non-invasive care—chiropractic decompression and ESWT—restores disc hydration and height, reduces surgical risk, and keeps patients in control of their recovery decisions. The resulting impairment ratings are packaged inside the medical-legal causation documentation framework at https://dralexjimenez.com.

Highway-side impacts on El Paso’s Loop 375 do more than crumple doors. They deliver concentrated lateral force vectors that simultaneously load lumbar discs in compression, shear, and side-bending. The result is a recognizable pattern of segmental disc compression: annular fissures, progressive height loss, and altered load-sharing that shows up clearly on structural MRI. For personal-injury attorneys and patients, this pattern clearly links crash mechanics to documented objective injury.
How Lateral Force Vectors Create Segmental Compression
In a typical Loop 375 side-impact or side-swipe, the struck vehicle’s occupant experiences a rapid lateral acceleration. The lumbar spine, already bearing axial load, is forced into lateral bending while the upper body lags. Finite-element and cadaver studies show that axial compression plus lateral bending produces peak stresses along the posterolateral annulus—the same region where clinical annular tears most often appear.
The outer annulus, whose fibers run nearly vertical in the posterolateral quadrant, is mechanically weakest in this direction. Once a tear begins, nuclear material can migrate, and the disc loses height. Sequential MRI demonstrates the progression: an initially bright T2 fissure evolves into a broader annular disruption accompanied by measurable reduction in disc height at the involved segment (commonly L4–L5 or L5–S1).
MRI Correlation That Withstands Scrutiny
Structural MRI is the cornerstone of objective documentation. High-resolution T2 sequences reveal hyperintense annular fissures; sagittal and axial measurements quantify disc-height loss relative to adjacent normal levels. When these imaging findings are correlated with the known crash kinematics—ΔV, principal direction of force, and seat-belt usage—the clinical causation statement becomes precise: the lateral impact produced the observed segmental compression pattern and annular disruption.
Digital diagnostic imaging, functional range-of-motion and strength testing, and detailed electronic notes are packaged so they align with Colossus valuation factors. These records also support Letters of Protection and provide a clear timeline that patients and counsel can share.
Beneficence: Restoring Disc Hydration and Height
The clinical goal is root-cause recovery, not symptom suppression. Non-surgical spinal decompression creates negative intradiscal pressure that draws nuclear material centrally and allows water and nutrients to re-enter the disc. When low-energy extracorporeal shockwave therapy (ESWT) is combined with controlled traction, animal and clinical data show improved disc height, rehydration, and favorable remodeling of the annular matrix.
At the clinic, Dr. Jimenez (DC, APRN, FNP-BC, CFMP, IFMCP; Texas License #1191402, Prescriptive Authority #59628, NPI 1205907805) integrates these mechanical therapies with targeted regenerative options under the medical direction of Dr. Cardenas, MD (Board Certified Internal Medicine, Texas License #J2933, NPI 1164426748). The combination addresses both the structural compression and any concurrent metabolic or inflammatory factors that slow healing.
Non-Maleficence: Delaying or Avoiding Surgery
Invasive procedures carry risks of infection, hardware, and adjacent-segment disease. By restoring disc height and reducing annular stress through decompression and ESWT, many patients experience durable pain relief and improved mobility without immediate surgical intervention. This approach minimizes iatrogenic harm while still producing the objective measurements insurers and defense counsel expect.
Autonomy: Patient-Owned Imaging and Decision Making
Patients retain full access to their imaging timeline and functional data. They review the mechanism-to-injury linkage with both the clinical team and their attorney, then choose the care pathway that fits their goals. Coordination with existing medical providers remains seamless; the clinic’s dual-licensure model keeps chiropractic, acupuncture/electroacupuncture, and advanced medical diagnostics within one coordinated plan.
Future-Care Projections That Drive Case Value
Documented residual disc-height loss and annular disruption support projections for ongoing decompression sessions, periodic ESWT, and monitoring MRI. These future-care items are stated in plain language and tied directly to the original lateral-impact mechanism, so they withstand Colossus review and support appropriate impairment ratings.
The resulting impairment ratings are packaged inside the medical-legal causation documentation framework at https://dralexjimenez.com.
Detailed Biomechanics of Loop 375 Lateral Impacts
Loop 375’s high-speed corridors and frequent lane-change geometry produce a distinctive set of force vectors. When a vehicle is struck broadside or sideswiped, the occupant’s torso is accelerated laterally while the pelvis remains partially restrained by the seat. The resulting moment arm loads the lumbar spine in combined compression, lateral bending, and shear.
Peak annular stresses concentrate at the posterolateral annulus of L4–L5 and L5–S1. In vitro studies using complex loading protocols that include lateral bending demonstrate endplate junction failures and isolated outer-annulus disruptions—exactly the lesions seen clinically after side impacts.
These mechanics explain why patients present with segmental rather than diffuse disc changes. The MRI shows focal height loss and annular high-intensity zones at the levels that experienced the greatest lateral moment. Correlating the police report’s principal direction of force with these segmental findings supplies the proximate-causation statement required for both medical and legal purposes.
Structural MRI Protocols and Quantification
Standard lumbar MRI protocols are augmented with thin-slice T2 sequences and precise mid-sagittal height measurements. Disc height is compared with the adjacent normal disc and with published normative data. We grade annular tears by radial extent and T2 signal intensity. When serial imaging is available, the timeline shows progressive height loss beginning after the documented impact rather than from age-related change alone.
These measurements are entered into the electronic record in a Colossus-ready format: diagnosis codes, objective findings, and functional limitations appear in structured fields. The same images are released to counsel so the patient retains ownership of the visual evidence.
Clinical Examination and Functional Correlates
The physical examination maps MRI findings to clinical signs: restricted lateral flexion, positive straight-leg or femoral-nerve tension, and segmental motion restriction. Instrumented strength and range-of-motion testing quantifies the deficit. These functional data corroborate imaging and show that segmental compression produces real activity limitations—information that directly influences impairment ratings and future care needs.
Multidisciplinary Treatment: Decompression and ESWT
Chiropractic decompression tables apply computer-controlled distraction forces that cycle between hold and rest phases, generating negative intradiscal pressures sufficient to retract nuclear material and promote rehydration. ESWT delivers acoustic energy that, when combined with traction, down-regulates matrix-degrading enzymes and stimulates annular repair.
Sessions are scheduled according to the severity of height loss and annular disruption. We track progress with clinical scores and, when indicated, follow-up MRI. The dual-licensed model allows Dr. Jimenez to integrate these mechanical therapies with medical oversight from Dr. Cardenas, ensuring concurrent management of any metabolic factors.
Spinal Decompression in Depth | El Paso, TX
Bioethical Framework in Practice
Beneficence is realized when disc height and hydration improve and patients regain mobility and sleep. Non-maleficence is served by prioritizing non-invasive options that delay or eliminate the need for fusion or discectomy. Autonomy is preserved because every patient receives a clear explanation of the mechanism, imaging findings, and expected outcomes of each treatment choice; the patient retains possession of the imaging timeline and shares it with counsel at the patient’s direction.
Documentation That Survives Defense Scrutiny
Every encounter generates Colossus-compliant electronic notes that link the original crash kinematics to current objective findings. Digital imaging is archived with measurement annotations. Functional testing results are dated and signed. The complete package supports both the Letter of Protection and the impairment rating that is later incorporated into the medical-legal causation report hosted at https://dralexjimenez.com.
Impairment Ratings and Future-Care Projections
Residual disc-height loss and annular disruption are translated into AMA Guides impairment percentages when appropriate. Future-care projections specify the number and frequency of decompression and ESWT sessions needed to maintain restored height and prevent further annular progression. These projections are written in plain language and tied explicitly to the Loop 375 lateral-impact mechanism.
Coordination with Legal Counsel and Existing Providers
The clinic supplies counsel with a concise mechanism-to-injury summary, annotated imaging, and the functional data set. When a patient already has a primary-care or specialty physician, the dual-licensure team coordinates with that relationship rather than replacing it, preserving continuity while adding the structural and regenerative expertise needed for the injury claim.
Multidisciplinary Call to Action and Reference List
Patients injured in Loop 375 lateral impacts and their attorneys can obtain a coordinated evaluation that links crash mechanics to MRI-documented segmental disc compression, restores disc height non-surgically through decompression and ESWT, and packages the entire record for legal use.
Call to Action
Schedule a comprehensive evaluation at Injury Medical Clinic PA in El Paso. Dr. Alex Jimenez, DC, APRN, FNP-BC, and Dr. Maria Guadalupe Cardenas, MD, will map the force vectors of your collision to your current MRI findings, design a drug-free plan to restore disc hydration and height, and prepare the objective documentation your counsel needs. Contact the clinic or visit https://dralexjimenez.com to begin.
References
- Che, Y.-J., Guo, J.-B., Wang, Y.-F., Zhu, L.-M., Zhou, C.-X., & Liu, Y.-L. (2021). Low energy extracorporeal shock wave therapy combined with low tension traction can better reshape the microenvironment in degenerated intervertebral disc regeneration and repair. The Spine Journal, 21(1), 91–102. https://doi.org/10.1016/j.spinee.2020.08.004
- Ghavam, K., & Standring, S. (2023). Annular disc tear. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK459235/
- Disc injury and spine loads in low-to-moderate-severity frontal impacts. (2025). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC12457475/
- Stress evaluation along the posterior annular circumferential tears on the L5-S1 spinal unit as an index of tear progression. (2025). ScienceDirect. https://www.sciencedirect.com/science/article/pii/S0972978X25000261
- Influence of complex loading conditions on intervertebral disc failure. (2016). PubMed. https://pubmed.ncbi.nlm.nih.gov/27187053/
- Posttraumatic changes of the intervertebral disc. (2017). In Wheeless’ Textbook of Orthopaedics. https://www.wheelessonline.com/ISSLS/section-17-chapter-7-posttraumatic-changes-of-the-intervertebral-disc/
- Regional variations of mechanical responses of IVD to 7 different motions: An in vivo study combined with FEA and DFIS. (2024). ScienceDirect. https://www.sciencedirect.com/science/article/abs/pii/S175161612400417X
- Effect of extracorporeal shock wave therapy on different types of lumbar disc herniation. (2024). ResearchGate. https://www.researchgate.net/publication/385851112

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Adrenal Fatigue (AF), Anti Aging, Chiropractic, Conditions Treated, El Paso Chiropractic News, Functional Medicine, Health, Health News El Paso, Heart Health, Hormone Balance, Lawyers, Med-Legal Corner, Physical Rehabilitation, Screening Tests, Seniors, Weight Loss, Wellness
Legal Peptides and Integrative Chiropractic Care: A Clear Guide
Abstract
This article explains legal peptide use in plain language. Legal peptide use means giving, making, or prescribing certain short chains of amino acids that regulatory bodies such as the Food and Drug Administration (FDA) have officially approved for medical use. Readers will learn how approved drugs differ from compounded products and research-only chemicals. The article then reviews the New Mexico Board of Nursing’s September 2026 peptide FAQs. It covers a valid patient-provider relationship, telehealth, advertising, nutrition, and muscle care. The last sections show how integrative chiropractors and nurse practitioners work together, and how Dr. Alexander Jimenez, DC, APRN, FNP-BC, and Dr. Maria Guadalupe Cardenas, MD, run that model at Injury Medical Clinic PA in El Paso.

What Legal Peptide Use Means
Peptides are short chains of amino acids. The body already makes many of them. They act like small messages that can change appetite, hormone release, inflammation, and tissue repair (Findlay, 2026; Vibrant Health of Colorado, 2026).
Legal peptide use means giving, making, or prescribing certain short chains of amino acids that regulatory bodies such as the Food and Drug Administration (FDA) have officially approved for medical use (Findlay, 2026; Peptide Laws, n.d.). In everyday terms, a peptide plan is safer when:
- A regulator has officially approved that product for medical use.
- A licensed clinician examines the patient and writes a prescription.
- Any compounded version follows federal compounding law and state pharmacy rules.
- The chart shows a reason, informed consent, and follow-up (ByrdAdatto, n.d.; LumaLex Law, n.d.).
Insulin, semaglutide, tirzepatide, tesamorelin, and bremelanotide (PT-141) are examples of peptides with FDA-approved products for specific conditions (Findlay, 2026; DJ Holt Law, 2026). Approval covers a product and its use. It does not make every similar vial on the internet legal.
Approved, Compounded, or Research-Only
FDA-approved medicines have finished clinical trials and manufacturing review. A clinician may use an approved drug off-label when science and judgment support that choice, but the product itself is still an approved drug (DJ Holt Law, 2026; ByrdAdatto, n.d.).
Compounded peptides are custom medicines made for one named patient when the law allows it. They are not FDA-approved. They may differ in formula, stability, and oversight (New Mexico Board of Nursing, 2026). After branded GLP-1 shortages eased, federal policy tightened around copies of those products (DJ Holt Law, 2026; Peptide Laws, n.d.).
Research-only chemicals are often sold as “not for human use.” Popular names include BPC-157, TB-500, and several growth-hormone secretagogues. That label does not make clinical use legal. The FDA treats marketing for human treatment as a drug claim (Findlay, 2026; LumaLex Law, n.d.). Status can also change as compounding committees review bulk substances (DJ Holt Law, 2026).
State boards rarely ban peptides as a whole class. They do ask whether the prescriber stayed in scope, did a real exam, and used a lawful pharmacy (Peptide Journal, 2026; ByrdAdatto, n.d.).
What the New Mexico Board of Nursing Said
In September 2026, the New Mexico Board of Nursing published clinical-practice FAQs on peptide therapies. The Board said the page is guidance, not a legal opinion, and it does not change the Nursing Practice Act (New Mexico Board of Nursing, 2026). The answers still give a clear map.
Key points include:
- APRNs may prescribe compounded medicines within their population focus and prescriptive authority if they have the education and judgment to do so. The Board uses LACE: licensure, accreditation, certification, and education.
- GLP-1 medicines are among the most watched peptides because they help and they carry risk.
- A valid patient-provider relationship must exist before prescribing.
- A compounded GLP-1 vial must stay patient-specific. It cannot be shared.
- Pharmacies should be licensed and able to share sterility testing.
- Patients must be told when a product is compounded rather than a brand-name FDA-approved drug.
- Reckless prescribing—not peptide use alone—invites discipline (New Mexico Board of Nursing, 2026).
New Mexico grants nurse practitioners full practice authority. Texas generally requires a collaborating physician (Peptide Journal, 2026). The clinical standard still looks the same: exam, reason, consent, monitoring, and a clean pharmacy.
The Exam, Telehealth, and Honest Ads
The Board listed what should happen before GLP-1 or related peptide care starts (New Mexico Board of Nursing, 2026):
- A health history and a review of current medicines
- A check for higher-risk problems, such as family medullary thyroid cancer or MEN-2, pancreatitis, gallbladder disease, kidney disease, pregnancy plans, eating disorders, or frailty
- A physical exam and baseline labs when they are needed
- Consent that covers benefits, common side effects, serious risks, other options, how long care may last, lifestyle changes, and weight regain after stopping
- A written plan and later checks of weight, nutrition, tolerance, and dose
Telehealth can be used when the standard of care is still met. A questionnaire alone is not enough. The prescriber must also be licensed in the state where the patient is located (New Mexico Board of Nursing, 2026). Ads must be truthful. Claims of guaranteed weight loss do not meet professional standards. The Federal Trade Commission watches those claims (New Mexico Board of Nursing, 2026). A med-spa name does not change the duty of the person who evaluates and prescribes.
Food and Muscle Still Come First
The Board was clear: medicine is not the whole treatment. Providers should counsel patients on protein, resistance exercise, lean-mass protection, vitamins, and long-term habits. Skipping that work can lead to muscle loss, frailty, and poor results after the drug stops (New Mexico Board of Nursing, 2026). Integrative clinics make the same point. Peptides work best when you address food, sleep, and movement (Nourish House Calls, n.d.; Evolution Integrative Medicine, n.d.).
How Integrative Chiropractic Care Fits
Teams of integrative chiropractors and nurse practitioners (NPs) work together in integrative medical offices. Most of the time, chiropractors do the manual therapies, biomechanics, and structural rehabilitation. Nurse practitioners, on the other hand, conduct clinical evaluations and have the medical authority to prescribe and oversee therapies (ProCredits, n.d.; Jimenez, 2026a). That split protects both the patient and the license.
Chiropractic care links to peptide treatment by making muscles and bones stronger:
- Adjustments and mobilization restore joint motion and lower mechanical stress on nerves and soft tissue.
- Better motion lets a person load a tendon, hip, or spine pattern with less guarding.
- Rehab—easy isometrics, then controlled loading—tells muscle, tendon, and bone to remodel.
- Protein-forward eating provides the building blocks those tissues need.
- A legal metabolic peptide, when indicated, may help appetite, blood sugar, and body composition so rehab is easier to finish.
- Any tissue-support peptide is an add-on to loading, not a replacement for it (El Paso Back Clinic, n.d.; Gruber Chiropractic, n.d.).
Dr. Jimenez has written that peptides should not be sold as a shortcut to grow cartilage, discs, or ligaments. Food cannot unlock a stuck joint. An adjustment cannot replace protein. Each tool has a job (Jimenez, 2026a).
The El Paso Team: Dr. Jimenez and Dr. Cardenas
Injury Medical Clinic PA in El Paso shows how those roles work in daily care. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, is a dual-licensed chiropractor and board-certified family nurse practitioner. He leads conservative care, rehabilitation, functional medicine, and personal-injury documentation (Jimenez, n.d.).
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine (NPI #1164426749; Texas MD License #J2933). With more than 40 years of experience as an internist, she serves as medical director and collaborative physician. This multidisciplinary setup is common in integrative or injury clinics, where an MD provides medical direction alongside a chiropractor. The team integrates chiropractic care from Dr. Jimenez with medical oversight by Dr. Cardenas, plus functional medicine, personal injury care, rehabilitation, and related services (Jimenez, n.d.; El Paso Back Clinic, n.d.).
A simple path for crash, sports, or chronic back pain recovery looks like this:
- Map the problem with history, exam, and movement testing.
- Restore motion with chiropractic and soft-tissue care.
- Rebuild muscle and bone loading with graded rehab.
- Address nutrition and metabolic gaps.
- Add a legal, patient-specific peptide only after the reason, labs, and consent are on the chart.
Clinical Observations on Strength and Recovery
Clinical observations shared by Dr. Jimenez describe peptides as possible signaling helpers, not magic. Progress often looks better when spinal care is paired with inflammation control, body-weight support, protein intake, and sleep (Jimenez, 2026a; El Paso Back Clinic, n.d.). Other clinics describe peptides for recovery, metabolism, gut integrity, sleep, and connective tissue (New Life Physicians, n.d.; RevitalIV, n.d.). Those descriptions are not the same as FDA approval. Patients should ask which product is approved, which is compounded for them alone, and which is still experimental.
Questions to Ask Before Starting
Before any peptide begins, ask four plain questions:
- Is this an FDA-approved product or a compounded one?
- Who is the licensed prescriber, and which state does the patient live in?
- What exam, labs, and follow-up will I receive?
- How will chiropractic care, exercise, and nutrition work with the medicine?
Boards expect those answers in the record (New Mexico Board of Nursing, 2026; ByrdAdatto, n.d.). Legal peptide use is a medical act. Integrative chiropractic care is a movement and strength act. When a clinic keeps both lines clear, patients build stronger muscles and bones—and, when appropriate, receive carefully chosen peptide support without a gray-market detour.
References
ByrdAdatto. (n.d.). How state laws impact peptides.
DJ Holt Law. (2026). What peptides are legal in the U.S.? Understanding FDA approval, compounding, and the legal gray areas.
El Paso Back Clinic. (n.d.). Integrative peptide science and chiropractic innovations.
El Paso Chiropractic. (n.d.). Peptide chiropractic wellness guide in El Paso.
Evolution Integrative Medicine. (n.d.). Why integrative medicine practitioners are turning to peptide therapy.
Findlay, S. (2026, July 30). Are peptides legal? Everything you want to know. Healthline.
Gruber Chiropractic. (n.d.). Peptide therapy.
Jimenez, A. (n.d.). Injury specialists. Injury Medical Clinic PA.
Jimenez, A. (n.d.). Dr. Alexander Jimenez [LinkedIn profile].
Jimenez, A. (2026a). Peptide therapy, nutrition, and chiropractic care explained. Dr. Alex Jimenez.
LumaLex Law. (n.d.). Peptides.
New Life Physicians. (n.d.). Commonly used peptides.
New Mexico Board of Nursing. (2026, September). Peptide therapies: Clinical practice frequently asked questions.
Nourish House Calls. (n.d.). How functional medicine uses peptides.
Peptide Journal. (2026). Are peptides legal? State-by-state guide.
Peptide Laws. (n.d.). United States peptide laws.
ProCredits. (n.d.). Peptide therapy for chiropractors: Tissue repair and metabolic health.
RevitalIV. (n.d.). Top 5 most popular peptides: What they do.
Vibrant Health of Colorado. (2026, January 23). Peptide therapy: A functional medicine guide.










