Unlocking Cellular Healing: The Power of Advanced Laser Therapy in Integrative Care
Abstract
As a clinician with a diverse background spanning chiropractic, advanced practice nursing, and functional medicine, my primary goal is to offer patients the most effective, evidence-based treatments available. In this educational post, I will take you on a journey into the world of Multiwave Locked System (MLS) Laser Therapy, a cutting-edge technology that is transforming how we manage pain and inflammation. We will explore the science behind this therapy, moving beyond surface-level explanations to understand its profound effects on cellular biology, including its impact on mitochondria and the inflammatory cascade. I will share insights from leading researchers and demonstrate how we apply this technology in clinical settings, particularly for conditions such as low back pain and joint issues. Furthermore, I will explain how MLS Laser Therapy integrates seamlessly into a comprehensive care model like ours at Injury Medical Clinic, where we combine chiropractic adjustments, physical rehabilitation, and advanced medical oversight from our Medical Director, Dr. Maria Guadalupe Cardenas, MD, to optimize patient outcomes. This post will detail specific treatment protocols, the importance of energy density, and how this therapy can augment other regenerative treatments, such as Platelet-Rich Plasma (PRP), offering a multifaceted approach to true healing.
A New Frontier in Healing at Injury Medical Clinic
Hello, I’m Dr. Alex Jimenez. With my credentials as a Doctor of Chiropractic (DC) and Advanced Practice Registered Nurse (APRN), and my certifications in functional and integrative medicine (CFMP, IFMCP), my passion has always been to bridge gaps between healing disciplines. At Injury Medical Clinic PA, we have built a practice on this very principle: a truly integrative approach to patient wellness.
A cornerstone of our collaborative model is my partnership with Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is Board Certified in Internal Medicine and serves as our esteemed Medical Director and Collaborative Physician. With over 40 years of invaluable experience, she provides essential medical oversight, ensuring our patients receive safe, comprehensive, and well-rounded care. This multidisciplinary structure allows us to blend the best of chiropractic and physical rehabilitation with the diagnostic and medical expertise of internal medicine. Our team works in synergy, designing treatment plans that address not just the symptoms but the underlying physiological dysfunction. Whether a patient is recovering from a personal injury, managing a chronic condition, or seeking to optimize their overall health, our integrated team provides a holistic, evidence-based pathway to recovery.
Navigating Low Back Pain with MLS Laser Therapy
One of the most common ailments we see is chronic low back pain. Today, we have a patient, John, who is experiencing persistent joint pain and stiffness in his lumbar spine, specifically around the L4-L5 facet joints, with some discomfort radiating down his right side. This is a classic presentation that responds exceptionally well to a targeted, multimodal approach.
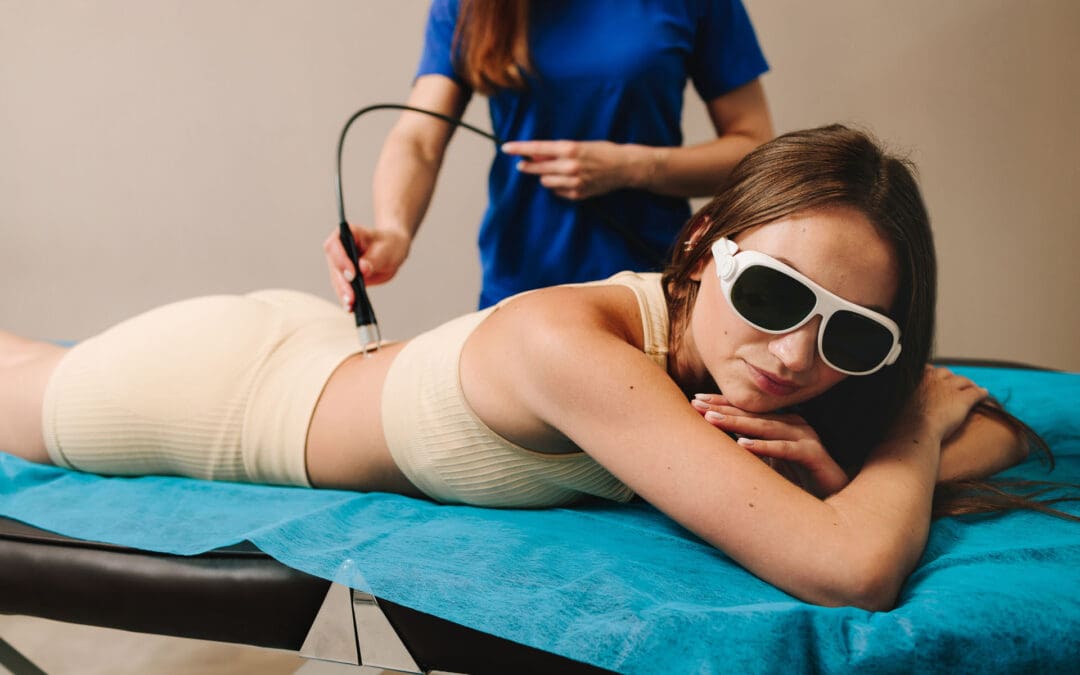
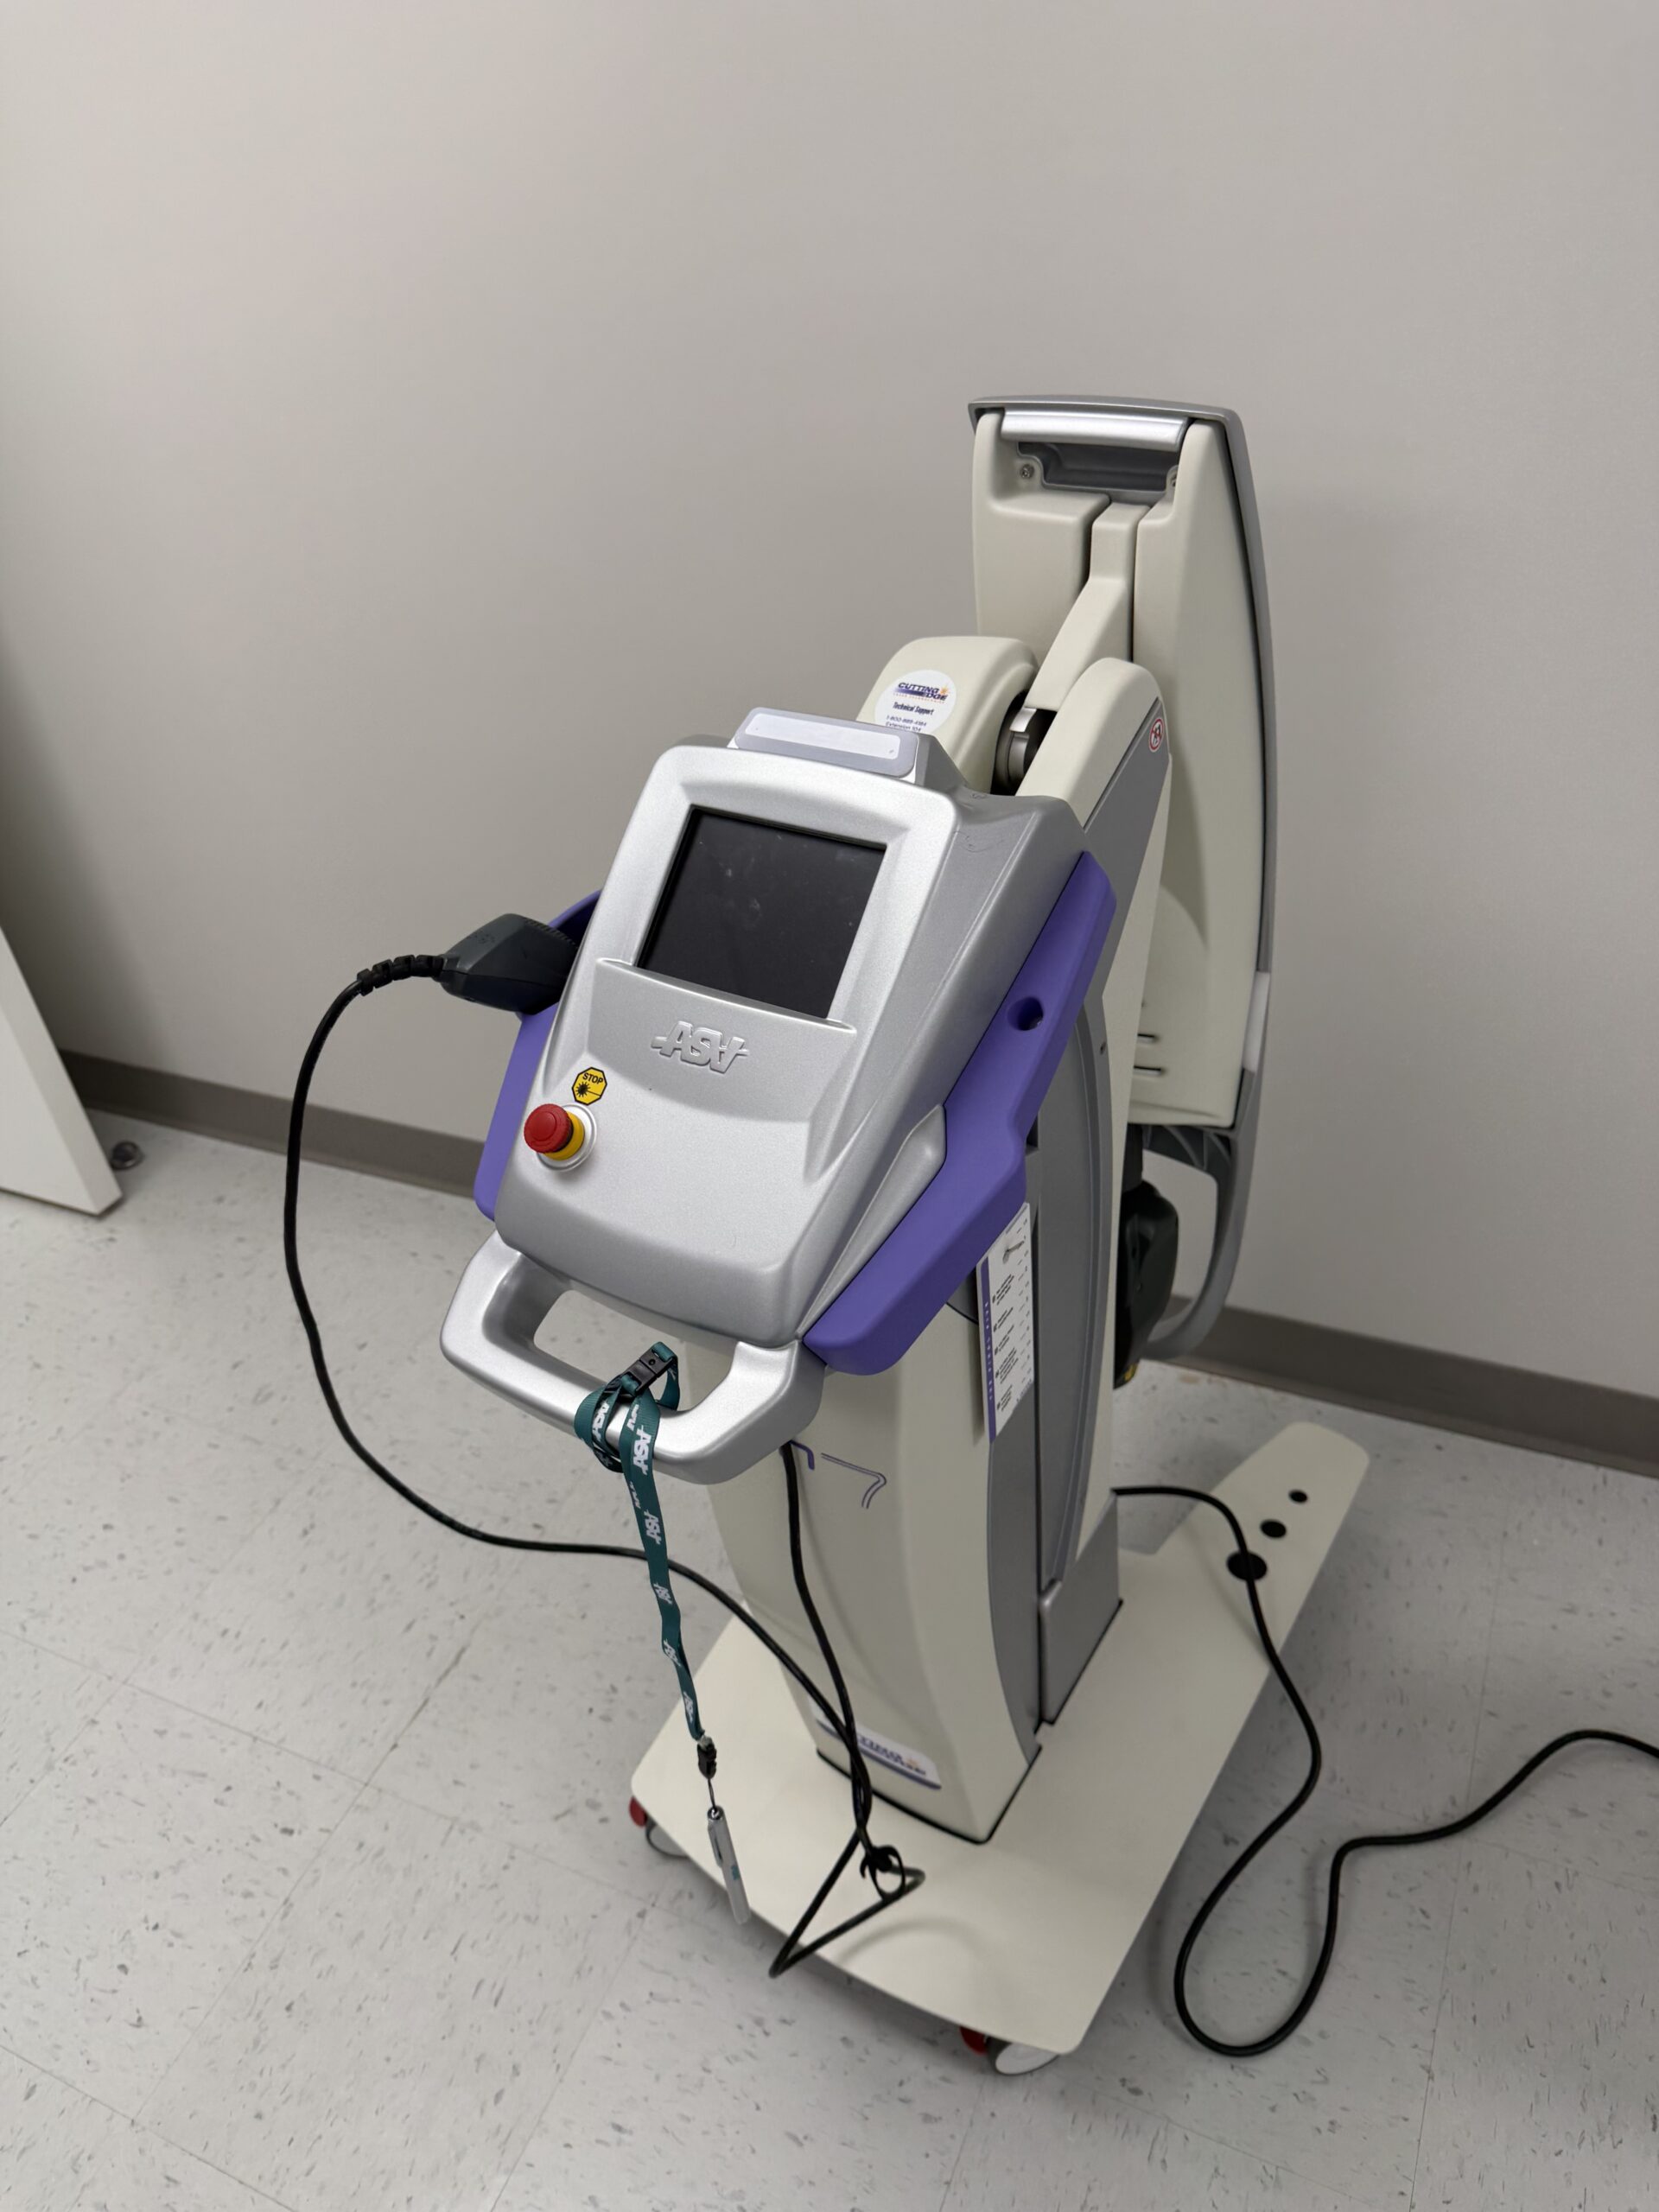
For John, we are utilizing the M6 Robotic MLS Laser. The first priority is always patient comfort. When using a robotic system, it’s critical that the patient remains still, as the laser is programmed to treat a precise area. We position the patient face down to allow direct access to the skin over the lumbar spine, as the laser energy must be delivered without the barrier of clothing.
The Clinical Multimodal Approach: More Than Just the “Spot of Pain”
Once John is comfortable, we begin the setup. The robotic laser interface is remarkably sophisticated yet user-friendly.
Targeting the Ailment: I select the “Joint Pain and Stiffness” protocol for the back.
Centering the Treatment: I zero out the X and Y axes on the control panel. This temporarily stops the robotic arm’s movement, allowing me to manually position the guiding red light directly over the primary source of John’s discomfort—the L4-L5 region he indicated.
Expanding the Field: This is where our clinical multimodal approach comes into play. Instead of just treating the single spot of pain, I expand the treatment area using the X and Y controls. This creates a larger therapeutic field that covers not only the symptomatic facet joints but also the surrounding connective tissue, muscles, and nerve roots. We aren’t just chasing pain; we are treating the entire functional unit to address the source of the dysfunction and support the interconnected biological systems.
The laser head is positioned at a precise distance from the skin—about six inches—using a provided ruler. This is crucial because the MLS laser beam is collimated, meaning the light rays are parallel. The focal point is engineered to be most effective at this distance, ensuring the therapeutic energy penetrates deep into the tissues rather than dissipating at the surface.
The Science of Healing: How MLS Laser Therapy Works
With the treatment underway—an eight-minute session for John’s low back—let’s dive into what’s happening at a cellular level. It’s common for patients to ask if they will feel anything. Most feel nothing at all, though some may notice a gentle warmth or tingling. This lack of intense heat is a hallmark of the MLS system’s advanced design.
The device combines two specific wavelengths of light: an 808-nanometer (nm) continuous-wave and a 905-nanometer (nm) pulsed-wave.
The 808 nm wavelength works more superficially to reduce inflammation and edema. It enhances blood circulation to the area, which helps clear out inflammatory byproducts and deliver oxygen and nutrients.
The 905 nm wavelength, delivered in powerful, short pulses, penetrates much deeper, reaching tissues such as muscle, nerve, and even the joint capsule. This pulsed energy is what provides the powerful analgesic (pain-relieving) effect.
These two wavelengths are synchronized, creating the patented “MLS pulse.” This enables delivery of very high peak power (up to 50 watts) in extremely short bursts (nanoseconds). This high-intensity “punch” of energy stimulates the cells without generating heat. A period of rest follows each pulse, allowing the tissue to absorb the energy efficiently. If a laser produces significant heat at the skin’s surface, it often means the energy isn’t being absorbed properly by the target tissues. The MLS system maintains tissue temperature at a constant level, ensuring optimal therapeutic delivery.
Seeing the Invisible: A Window into the Treatment
A fascinating demonstration of this technology involves using a smartphone camera. While the red aiming light is visible to the naked eye, the therapeutic infrared laser light is not. However, a camera’s sensor can detect it. If you were to look at John’s back through a phone camera during treatment, you would see a distinct triangle of light—this is the 808 nm wavelength at work, covering a significant area and illustrating how comprehensively we are treating the region.
Energy Density: The Key to Effective Dosing
A critical concept in laser therapy is energy density, measured in joules per centimeter squared (J/cm²). This is more important than the total number of joules delivered. Think of it like watering a plant: you need to provide the right amount of water for the pot’s size. Too little has no effect; too much drowns it. Similarly, our goal is to deliver a precise dose of light energy to the target tissue.
The World Association for Laser Therapy (WALT) and a large body of research support an optimal therapeutic window of 4-10 J/cm².
For John’s condition, the protocol is set to deliver approximately 6 J/cm². The laser’s software automatically calculates the treatment time required to achieve this density over the selected area. If I were to make the treatment area smaller or larger, the software would instantly recalibrate the time to ensure the correct dose is delivered.
This concept also relates to the Arndt-Schultz Law, a pharmacological principle stating that low doses stimulate, moderate doses inhibit, and high doses are toxic. With laser therapy, if you “overcook” an area with too much energy, you risk a bioinhibitory effect, in which the treatment becomes less effective or even counterproductive. The body’s cells can only absorb so much energy at once. This is why our protocols focus on precise energy density and, if more treatment is needed, we target different areas (e.g., an anterior and posterior approach for a knee) rather than just increasing the time on one spot.
Integrating Modalities for Superior Results
While the robotic laser treats the broader lumbar region, I can simultaneously use a handheld MLS laser applicator. This handpiece allows for more focused treatment on specific points, such as trigger points or “knots” in the muscle. I often use the “cooked meat” versus “raw meat” analogy that a physical therapist once taught me. Healthy, relaxed muscle feels like raw meat, while a tight, knotted trigger point feels firm, like cooked meat. The handheld applicator is perfect for treating these punctual spots.
The robot and the handpiece operate on two separate channels, allowing us to perform this dual treatment. This is a perfect example of our integrative philosophy in action:
Chiropractic Care: Before or after the laser session, I can perform specific chiropractic adjustments to restore proper motion to the L4-L5 facet joints and relieve mechanical stress.
Physical Rehabilitation: Our team can guide John through exercises to strengthen his core musculature and improve spinal stability.
MLS Laser Therapy: The laser works at the cellular level to reduce pain and inflammation that may be hindering his ability to engage in rehabilitation, thereby accelerating healing.
This combination addresses the structural, functional, and biochemical aspects of his condition simultaneously.
Advanced Applications: Augmenting Regenerative Medicine
The conversation around healing is increasingly turning toward orthobiologics, such as Platelet-Rich Plasma (PRP) injections. This is where MLS Laser Therapy shows even more remarkable potential. A common question arises: if PRP induces a beneficial pro-inflammatory phase to kickstart healing, won’t an anti-inflammatory laser treatment counteract it?
The answer is no. In fact, the laser augments the process. The data and our clinical observations show that using laser therapy in conjunction with PRP can improve outcomes by an estimated 15-20%.
Here is the progressive protocol we often recommend:
Pre-Injection Priming (2-3 treatments): In the weeks leading up to the PRP injection, we use the laser to “prepare the soil.” These sessions are designed to increase local blood circulation, reduce baseline chronic inflammation, and optimize the cellular environment, making the tissue more receptive to the growth factors in the PRP.
Day of Injection (1 treatment): A treatment on the day of the procedure can further enhance the effects.
Post-Injection Support (6+ treatments): Following the injection, a series of laser treatments helps manage pain and supports the regenerative cascade initiated by the PRP. The laser enhances mitochondrial function, which is critical for providing the cellular energy (ATP) needed for tissue repair.
The Cascade of Healing: From Acute Relief to Chronic Repair
How does a single modality address both acute pain and chronic conditions? The effects occur in a cascade.
Immediate Effect (Acute Phase): The initial pain relief often comes from the laser’s effect on small, unmyelinated nerve fibers (C-fibers) that transmit pain signals. The energy can temporarily block these signals, providing rapid relief. This is the analgesic effect.
Subsequent Effect (Inflammatory Modulation): Over the next few hours and days, the anti-inflammatory effect takes hold. The laser energy modulates the immune response, reducing pro-inflammatory cytokines and promoting the resolution of inflammation and edema.
Long-Term Effect (Biostimulation and Chronic Repair): With a series of treatments, we get to the core of cellular repair. Light energy is absorbed by cytochrome c oxidase in the mitochondria, the powerhouses of our cells. This significantly increases ATP (adenosine triphosphate) production, the body’s primary energy currency. This surge in available energy fuels all cellular repair processes, from protein synthesis to cell replication, promoting true, long-term tissue healing.
This mitochondrial boost is especially relevant in today’s world, where many common medications, such as statins, can impair mitochondrial function. By enhancing mitochondrial biogenesis and efficiency, laser therapy can help overcome these hurdles and optimize the body’s innate healing capacity. This is why we also discuss nutritional and lifestyle factors—such as CoQ10 supplementation to support mitochondrial function—as part of a truly comprehensive functional medicine approach.
Treatment Frequency and The Cumulative Effect
Healing is a process, not an event. The effects of MLS Laser Therapy are cumulative. We recommend a series of treatments to achieve lasting results.
Acute Conditions: Typically, a course of 6 treatments is effective.
Chronic Conditions: A more intensive course of 12 treatments is often needed.
Ideally, treatments are scheduled close together (e.g., Monday, Wednesday, Friday) to build therapeutic momentum. It is crucial for patients to complete the full course. Many start feeling significantly better after just 3-4 sessions and are tempted to stop. However, completing the entire protocol ensures deeper cellular repair, leading to more durable outcomes.
At Injury Medical Clinic, our mission is to empower your body’s own ability to heal. By integrating the best of chiropractic, medical oversight, and groundbreaking technologies like MLS Laser Therapy, we offer a path to recovery that is not only faster but also more complete.
World Association for Laser Therapy. (n.d.). WALT Recommended Treatment Doses for LLLT. WALT. Retrieved from https://waltza.co.za/wp-content/uploads/2012/08/Dose_table_780-860nm_for_Low_Level_Laser_Therapy_WALT-2010.pdf
Welcome to our exploration of photobiomodulation therapy (PBMT), a revolutionary approach that harnesses the power of light to stimulate cellular healing. In this educational post, I will guide you through the intricate biological processes that make PBMT so effective. We will explore how specific wavelengths of light can penetrate tissues to activate mitochondria, modulate the immune response, and accelerate recovery. This journey will cover the fundamental science behind PBMT, from its effects on ATP production and cytokine modulation to its role in promoting angiogenesis and neurogenesis. Furthermore, we will examine the synergistic potential of combining PBMT with orthobiologics, such as Platelet-Rich Plasma (PRP), and demonstrate how this integrated approach can enhance healing outcomes. Drawing on the latest research, including fascinating studies from the veterinary world and our laboratory findings on tenocyte proliferation, we’ll demonstrate why light is not just a modality but a cornerstone of modern regenerative medicine. At Injury Medical Clinic, we integrate these advanced therapies within a collaborative framework, combining my expertise in chiropractic and functional medicine with the medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD, to provide comprehensive, evidence-based care for our patients.
About Our Integrated Practice: A Collaborative Approach to Wellness
I, Dr. Alex Jimenez, am honored to share my passion for integrative and regenerative medicine with you. With a diverse background as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), board-certified Family Nurse Practitioner (FNP-BC), and certifications in Functional Medicine (CFMP, IFMCP), Applied Traumatology (ATN), and Cranial Spinal Integration (CCST), my goal has always been to find the most effective, evidence-based paths to healing.
Here at Injury Medical Clinic PA in El Paso, Texas, we have built a unique, multidisciplinary practice. We believe that the best patient outcomes are achieved through a collaborative team approach. I am privileged to work alongside Dr. Maria Guadalupe Cardenas, MD, who serves as our Medical Director and Collaborative Physician. Dr. Cardenas is a highly respected, board-certified Internist with over 40 years of experience (NPI #1164426749, Texas MD License #J2933). Her extensive medical knowledge provides invaluable oversight and complements our services, ensuring our patients receive safe, comprehensive, and well-rounded care.
Our clinic integrates:
Advanced Chiropractic Care: Focused on spinal health, biomechanics, and nervous system function.
Physical Therapy & Rehabilitation: Tailored programs to restore movement, strength, and function.
Medical Oversight: Guided by Dr. Cardenas to ensure clinical safety and efficacy.
Functional Medicine: Investigating the root causes of chronic conditions.
Personal Injury Care: Specialized treatment for injuries sustained in accidents.
This model allows us to address health from multiple angles. While our core focus at elpasobackclinic.com is chiropractic and physical rehabilitation, we incorporate advanced modalities such as photobiomodulation to enhance the body’s innate healing capabilities, with all treatments guided by a solid medical and scientific foundation.
The Awakening: From Skepticism to Cellular Biology
I have been on this journey for nearly a decade, and for the first five years, discussing “laser” therapy in medical circles often felt like an uphill battle. It was a path paved with skepticism, much like the initial reception many of you in the biologics field have likely experienced. But today, I am thrilled to see the conversation shifting as the science catches up with the clinical results.
My evolution as a clinician mirrors this shift. For the first two decades of my career, I was a “mechanic,” using established tools to address specific conditions. Over the last ten years, however, I have become a “biologist,” focused on understanding and facilitating the body’s own healing processes at a cellular level. This is why I am so excited to share the science of photobiomodulation (PBMT) with you. It represents a profound shift from treating symptoms to enabling cellular recovery.
Understanding Photobiomodulation: The Science of Light and Life
The concept is beautifully simple, rooted in a phenomenon we all accept: photosynthesis. The sun’s light fuels life on Earth, and as a species that has evolved under this light for hundreds of thousands of years, our cells have developed a deep, genetic sensitivity to it. We readily accept that sunlight is necessary for Vitamin D synthesis, yet a significant gap remains in medical education regarding the broader therapeutic applications of light.
Photobiomodulation breaks down as:
Photo: Light
Bio: Life
Modulation: To affect or change
Light is energy, delivered in units called photons. These photons can transfer their energy to our cells, triggering a cascade of biological responses. This is the essence of PBMT.
The Cellular Engine: How PBMT Activates Mitochondria
The primary target of photobiomodulation within the cell is the mitochondria, our cellular powerhouses. Specifically, an enzyme in the mitochondrial respiratory chain, cytochrome c oxidase, acts as a photoacceptor. This means it is designed to absorb photons of light.
Here is the cascade of events that follows:
Activation: When light photons of the correct wavelength strike cytochrome C oxidase, the enzyme becomes more active.
Increased ATP Production: This heightened activity accelerates the Krebs cycle, leading to more efficient production of adenosine triphosphate (ATP), the primary energy currency of the cell. More ATP means more energy available for cellular repair, replication, and function.
Signaling Cascade: This process also triggers the release of key signaling molecules, including nitric oxide and reactive oxygen species (ROS) in controlled, beneficial amounts.
Gene Transcription: These signaling molecules then travel to the cell’s nucleus, initiating gene transcription. This is where the cell is instructed to produce specific proteins, including cytokines, which orchestrate the healing process.
Modulating the Immune Response: From Inflammation to Repair
When an injury occurs, the body initiates an inflammatory response characterized by the production of pro-inflammatory cytokines. PBMT helps guide the body out of this chronic or stalled inflammatory phase and into a reparative one by modulating the cytokine profile.
Anti-Inflammatory Effects: Research has clearly shown that PBMT, when used at the right wavelengths, can increase the production of interleukin-10 (IL-10), a potent anti-inflammatory cytokine.
Pro-Inflammatory Reduction: It has also been shown to reduce levels of pro-inflammatory cytokines, such as interleukin-6 (IL-6).
This shift moves the cellular environment from a state of chronic inflammation—such as that seen in a thickened, bulbous Achilles tendon—toward active healing and regeneration.
Building the Foundation for Healing: Angiogenesis, Neurogenesis, and Muscle Recovery
The benefits of PBMT extend beyond simple control of inflammation. The cellular signaling it initiates promotes the foundational elements of tissue repair.
Enhanced Blood Flow (Angiogenesis): PBMT has been shown to promote angiogenesis by stimulating the production of cytokines such as galectin-1. This improved microcirculation is crucial for delivering oxygen and nutrients to injured tissue and removing waste products. For anyone focused on healing, whether through chiropractic adjustments or post-surgical recovery, enhanced blood flow is paramount.
Nerve Repair (Neurogenesis): We can also document the repair of nerve cells. PBMT stimulates the production of proteins that encourage axonal growth, helping to repair damaged neurons. This is particularly relevant in our practice for treating neuropathies and nerve entrapment syndromes like carpal tunnel.
Muscle and Tissue Recovery: Electron microscopy studies have provided clear evidence that PBMT improves muscle cell development and increases myoglobin production, which enhances oxygenation. It also activates fibroblasts, the cells responsible for producing collagen and building the structural framework for new tissue.
In essence, PBMT orchestrates a symphony of healing: it modulates the immune system, increases blood flow, repairs nerves, and rebuilds tissue.
The Therapeutic Window: Why Wavelength Matters
Not all light is created equal. The electromagnetic spectrum ranges from deadly short-wavelength gamma rays to long-wavelength radio waves that pass harmlessly through us. The therapeutic potential of light lies within a specific “therapeutic window,” approximately from 600 nanometers (red light) to 1200 nanometers (near-infrared light).
The primary challenge is getting the photons to the target tissue. Three main obstacles absorb light energy before it can penetrate deeply:
Skin (Melanin)
Blood (Hemoglobin)
Water
While red light is effective for superficial tissues (penetrating 3-4 millimeters), treating deeper musculoskeletal structures requires wavelengths in the near-infrared spectrum, which can penetrate more effectively.
In my practice, we leverage this science daily. For acute injuries, such as those our Division 1 athletes sustain, PBMT significantly reduces recovery time. Post-operatively, it minimizes swelling and bruising and improves incision healing. And for the chronic inflammatory conditions we see so often, it provides the cellular energy needed to break the cycle of pain and dysfunction.
Synergy in Action: Combining PBMT and Orthobiologics
This is where the conversation becomes truly exciting. We know that orthobiologics, such as Platelet-Rich Plasma (PRP), deliver a potent cocktail of growth factors and anti-inflammatory proteins. They are essentially sending a “message” to the cells, instructing them to heal.
Now, imagine providing the “fuel” for that message.
By combining PRP with PBMT, we are doing just that. The PRP provides the blueprint for repair, and the PBMT provides the cellular energy (ATP) needed to carry out those instructions. We turn on the mitochondrial engine, allowing the cells to fully utilize the growth factors and signaling proteins delivered by the biologic treatment. We are creating a synergistic effect where the whole is greater than the sum of its parts.
Evidence from Our Four-Legged Friends: A Canine Study
When exploring emerging therapies, I often look to veterinary medicine. Animals, particularly dogs, do not have confounding factors such as secondary gain or placebo effects associated with complex human emotions. A treatment either works or it does not.
An outstanding randomized controlled trial on canines with knee osteoarthritis provides compelling evidence for this synergy.
Study Design: Each dog served as its own control. The dogs first received PBMT alone. After a washout period, they received a PRP injection alone. Finally, after another washout period, they received a combination of PRP and PBMT.
Results: The outcomes, measured by owner-reported functional improvements (like climbing stairs or getting into a car), were significantly better with the combined therapy than with either treatment alone.
This study strongly suggests that combining light energy with biologics creates a more robust and effective healing response.
Our Own Research: Proving Cellular Proliferation
To further validate these concepts, we embarked on our own research. My son, Zachary, led a study at the Mass General Brigham Enable BioSkills Lab to investigate the direct effects of PBMT on human tendon cells.
We treated human tenocytes (tendon cells) with our laser therapy. The results were remarkable: we demonstrated a 20% dose-dependent increase in tenocyte proliferation with PBMT alone. We were able to literally watch the cells multiply under the influence of light.
We are now conducting additional qPCR and ELISA testing to analyze gene expression and protein levels, which will give us an even deeper understanding of the pathways being activated. This work confirms that PBMT is not a passive modality; it is an active biological stimulus that directly promotes cellular regeneration.
The Future of Medicine is Biology
We are moving away from an era of purely symptomatic treatments and toward a future of true disease modification. The goal is to intervene earlier and more effectively, harnessing the body’s innate biological wisdom to heal from within. Photobiomodulation is a cornerstone of this new paradigm. It has been validated by major health organizations, including its mention in the CDC’s revised opioid guidelines as a non-pharmacological option for pain.
I have seen the profound impact of this therapy in my clinic and in the research lab. It works. The synergy between photobiomodulation and other regenerative therapies, all within an integrated care model that prioritizes chiropractic and physical rehabilitation, represents the future of orthopedic and musculoskeletal health. It has been a pleasure to share this journey with you.
As a Doctor of Chiropractic, Advanced Practice Registered Nurse, and certified functional medicine practitioner, I am constantly exploring the leading edge of musculoskeletal health. In this educational post, I will share key insights from the forefront of orthobiologics, a revolutionary field that harnesses your body’s own substances to heal injuries and manage chronic conditions such as osteoarthritis (OA). We will delve into the nuances of Platelet-Rich Plasma (PRP), discussing the critical importance of understanding its cellular composition—specifically, the roles of platelets versus pro-inflammatory neutrophils. We will also explore advanced techniques, such as micro-fragmented adipose tissue (MFAT) and subchondral bone injections, and examine the latest research and clinical applications. Throughout this discussion, I will explain how our multidisciplinary practice integrates these advanced biological treatments with our foundational principles of integrative chiropractic care, physical rehabilitation, and functional medicine. Our goal is to provide a comprehensive, patient-centered approach that not only addresses symptoms but also corrects the underlying biomechanical and physiological imbalances that contribute to joint degeneration, all under the expert medical direction of Dr. Maria Guadalupe Cardenas, MD.
Our Collaborative Care Model: The Synergy of Chiropractic and Medicine
At Injury Medical Clinic, our strength lies in our multidisciplinary team approach. I, Dr. Alex Jimenez (DC, APRN, FNP-BC, CFMP), work in close collaboration with our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a board-certified Internist with over 40 years of invaluable experience (NPI #1164426749, Texas MD License #J2933). This integrative model, common in advanced injury and wellness clinics, allows us to blend the best of different disciplines for superior patient outcomes.
Dr. Jimenez’s Role: I focus on the biomechanical, functional, and structural aspects of health. Through chiropractic adjustments, I address spinal and joint misalignments that create abnormal stress on the body. My expertise in functional medicine allows me to investigate and correct underlying metabolic and inflammatory issues. My role as a Family Nurse Practitioner enables me to bridge the gap between conservative care and medical interventions.
Dr. Cardenas’s Role: As the Medical Director, Dr. Cardenas provides essential medical oversight, ensuring all treatments are safe, appropriate, and aligned with the highest standards of medical care. Her deep knowledge of internal medicine is crucial for managing complex patient cases, especially those with comorbidities that could impact treatment outcomes. She collaborates on patient diagnoses, reviews treatment plans, and provides the necessary medical supervision for procedures that fall under the practice of medicine.
This partnership ensures that when we discuss and implement advanced therapies such as orthobiologics, we do so within a framework of comprehensive care. We can offer a spectrum of services from chiropractic adjustments and physical therapy to medically supervised regenerative procedures, all under one roof. This allows us to create truly personalized treatment plans that address the patient as a whole person, not just a symptom or a single joint.
The PRP Puzzle: Why Not All Platelet-Rich Plasma Is Created Equal
One of the most exciting and debated topics in orthobiologics is Platelet-Rich Plasma (PRP). The fundamental idea is simple: we concentrate the platelets from your blood and inject them into an injured area to stimulate healing. However, the details are crucial, and the clinical outcomes can vary dramatically based on the specific composition of the PRP.
It’s fascinating to look at the differences in preparation methods. For instance, European studies often describe manual preparation methods, which can yield a very different product from that of automated centrifuge systems commonly used in the United States. A key point of confusion in the literature and among practitioners concerns the white blood cell content of PRP, specifically the presence of neutrophils.
Leukocyte-Rich vs. Leukocyte-Poor PRP: The Neutrophil Question
When PRP was first being described, “leukocyte-rich” often implied it was rich in neutrophils. These are powerful immune cells that are excellent at fighting infection but are also highly pro-inflammatory. When injected into the sensitive, contained environment of a joint like the knee, a high concentration of neutrophils can trigger a significant inflammatory flare-up, leading to pain, swelling, and potentially even cartilage damage—an outcome we desperately want to avoid.
Many modern PRP systems in the U.S. are marketed as producing “leukocyte-poor” PRP. However, this term can be misleading. While these systems effectively reduce neutrophil counts, they often concentrate other white blood cell types, such as lymphocytes and monocytes. The total white blood cell count might remain the same or even increase, but the cell type has shifted.
My clinical takeaway for both patients and practitioners is this: Be meticulous.
Know Your System: If you are considering PRP, it’s crucial to understand what kind of preparation is being used. Ask the provider or the system manufacturer for data on the cellular composition. What is the typical platelet concentration? What are the final counts of neutrophils, lymphocytes, and monocytes?
The Differential is Key: The most important factor is the white blood cell differential. We generally want a preparation with a high concentration of platelets and monocytes (which can signal tissue repair) but a very low concentration of neutrophils. Injecting neutrophil-rich PRP into a joint with osteoarthritis is not a sound strategy and can lead to unhappy patients with increased pain and inflammation.
The future of this field may involve real-time analysis. I envision a time where we can aspirate fluid from a swollen knee, analyze its specific inflammatory profile in a lab, and then custom-tailor a biologic injection—be it a specific PRP formulation or another orthobiologic—to precisely counteract that patient’s unique inflammatory signature. Until then, diligence and a deep understanding of the product being used are paramount.
The Role of Integrative Chiropractic Care with PRP Therapy
When a patient receives PRP for a condition like knee osteoarthritis, the treatment doesn’t end with the injection. In our clinic, integrative chiropractic care is essential to maximizing the success of the biologic intervention.
Biomechanical Optimization: A degenerating knee is often the victim of poor biomechanics. There may be a pelvic tilt, a functional leg length discrepancy, or spinal misalignments that cause uneven weight distribution, placing excessive stress on one side of the joint. Through chiropractic adjustments, we can help restore proper alignment of the pelvis and spine, ensuring that forces are distributed more evenly through the lower extremities. This off-loading of the treated joint is critical; it creates a more favorable mechanical environment for the new tissue to regenerate and reduces the repetitive strain that caused the problem in the first place.
Neuromuscular Re-education: Our physical rehabilitation team works to strengthen weak muscles (such as the quadriceps and glutes) and release tight ones (such as the hamstrings). This corrects muscular imbalances that contribute to poor joint tracking and stability. Proper muscle function is vital for protecting the joint as it heals.
Reducing Systemic Inflammation: My functional medicine training enables me to address sources of systemic inflammation that can hinder healing. We may use dietary modifications, targeted nutritional supplements, and lifestyle coaching to lower the body’s overall inflammatory load, giving the PRP a better physiological environment in which to work its magic.
By combining the targeted regenerative power of PRP with a comprehensive plan to correct the underlying biomechanical and physiological dysfunctions, we give our patients the best possible chance for long-term success.
Micro-Fragmented Adipose Tissue (MFAT): A Powerful Second-Line Therapy
What happens when a patient has tried everything—physical therapy, bracing, cortisone shots, even PRP—and still suffers from persistent joint pain and swelling? For these individuals, who are often trying to delay or avoid a total knee replacement, we may consider a more advanced orthobiologic: micro-fragmented adipose tissue (MFAT), also known as a fat graft.
This procedure involves harvesting a small amount of fat, typically from the flank or abdomen, through a minimally invasive liposuction process. The fat is then specifically processed to create a micro-fragmented injectate rich in reparative cells, including mesenchymal stem cells (MSCs), which are contained within the fat tissue’s supportive structural matrix. This matrix, called the stromal vascular fraction (SVF), provides a natural scaffold and signaling environment for the cells.
Who Is a Candidate for MFAT?
We typically reserve MFAT as a second-line therapy for specific cases:
Patients with Osteoarthritis and Persistent Effusions (Swelling): These are individuals whose knees remain swollen and painful despite other treatments.
Post-Surgical Patients: Some patients elect to have an MFAT injection following an orthopedic surgery to provide a biologic boost to the healing process.
Patients Seeking to Avoid Joint Replacement: These are often individuals who have exhausted other non-surgical options and are seeking a more powerful intervention to preserve their native joint.
I have been pleasantly surprised by the number of patients who have responded favorably to MFAT after failing to respond to other biologics. This suggests that the cellular and structural components of adipose tissue confer a unique and potent capacity for healing. Does it work for everyone? No, just like any other medical procedure. But for the right patient, it can be a game-changing option.
The harvesting procedure itself is very well-tolerated. Interestingly, data from the plastic surgery field show that liposuction performed on an awake patient (using local anesthetic) is significantly safer than when performed under general anesthesia. We perform this procedure in a specialized treatment room in our clinic. We use a tumescent solution—a mixture of saline and local anesthetic—which is infused into the harvest area. A critical pearl of this process is time. We let the solution sit for 20-30 minutes. This not only numbs the area completely but also makes the fat tissue easier to harvest. It’s a comfortable and safe in-office procedure.
Decompressing the Bone: The Subchondral Injection Approach
For many years, the focus of osteoarthritis treatment has been on the cartilage. But we now understand that OA is a disease of the whole joint, including the subchondral bone—the layer of bone just beneath the cartilage. In advanced OA, this bone can become stressed, leading to bone marrow lesions (which appear as bruises on MRI), increased intraosseous pressure, and sclerotic changes. This “sick bone” is a major source of pain and contributes to the progression of cartilage breakdown.
This understanding has led to the development of subchondral bone injections. The procedure involves using fluoroscopic (X-ray) guidance to precisely place a needle into the area of diseased subchondral bone and decompress it. This act of creating a channel into the bone may itself be therapeutic by relieving the high pressure that causes pain.
What Do We Inject?
Once decompression is achieved, a biologic agent can be injected. Studies have explored using various substances, including:
Bone Marrow Aspirate Concentrate (BMAC): Rich in stem cells and growth factors to stimulate bone healing.
Calcium Phosphate Cement: A synthetic bone graft substitute that provides structural support.
A significant body of literature, including a notable French paper, has shown impressive results, with some studies reporting that up to 80-95% of patients avoided joint replacement for many years after the procedure. However, a consistent finding across most subchondral injection studies is a failure rate of about 20%. This tells us that while it is a powerful intervention for about 80% of patients, it’s not a silver bullet.
Maximizing Success: It’s All About the Environment
The key to improving that 80% success rate lies in what we do after the needle comes out. We must change the environment that made the bone sick in the first place.
This is where the principles of integrative and functional care are non-negotiable.
Offloading the Joint: From an orthopedic perspective, this might mean a surgical osteotomy to realign the bone. From a non-surgical and chiropractic perspective, it means using an offloading brace, correcting biomechanics through chiropractic adjustments, and, most importantly, weight loss. Every pound of body weight lost reduces the force on the knee by four pounds.
Treating the Biomechanics: As my surgical colleagues often point out, you can’t ignore the “roof collapsing on the foundation.” If a patient has poor core stability, weak quadriceps, and valgus collapse (knock-knees) during movement, they are constantly putting compressive stress on that joint. No biologic injection can fix that. This is why our physical rehabilitation programs are so vital. We must rebuild the functional foundation to protect the biological repair.
Patients who fail these advanced procedures are often those whose underlying biomechanical and metabolic issues are not addressed. The more variables we can modify—from spinal alignment and muscle function to body weight and systemic inflammation—the greater the patient’s chance of long-term success. It’s a testament to the fact that true healing is never about a single magic injection; it’s about a comprehensive, integrated strategy.
References
Hernigou, P., Auregan, J. C., Dubory, A., Flouzat-Lachaniette, C. H., Chevallier, N., & Rouard, H. (2018). Subchondral bone or intra-articular injection of bone marrow concentrate: what is the best treatment for knee osteoarthritis? International Orthopaedics, 42(10), 2265–2272. https://doi.org/10.1007/s00264-018-3926-5
Laudy, S., Boughedda, R., Musquer, N., & Verdot, F. (2020). Efficacy of autologous platelet-rich plasma to treat knee osteoarthritis: a systematic review. International Orthopaedics, 44(9), 1711–1725. https://doi.org/10.1007/s00264-020-04664-8
Pak, J., Lee, J. H., & Lee, S. H. (2013). A novel biological therapy for knee osteoarthritis: A combination of intra-articular and intraosseous injections of autologous adipose tissue-derived stromal cells. Journal of Medical and Biological Engineering, 33(5), 554-561. https://doi.org/10.5405/jmbe.1394
Sánchez, M., Delgado, D., Anitua, E., & Orive, G. (2019). The inflammatory paradox of platelet-rich plasma. Seminars in Thrombosis and Hemostasis, 45(6), 577-588. https://doi.org/10.1055/s-0039-1693444
In this educational post, I will take you on a journey through the cutting-edge landscape of regenerative and integrative medicine for treating common musculoskeletal conditions. Drawing on the latest evidence-based research and my clinical experience, we will explore which injuries respond best to advanced orthobiologic therapies such as Platelet-Rich Plasma (PRP) and microfragmented adipose tissue. We will explore a systematic, algorithm-based approach for patient selection, focusing on conditions such as partial rotator cuff tears, tendinopathies like tennis elbow, and mild-to-moderate osteoarthritis. Furthermore, I will introduce a groundbreaking study that uses machine learning to identify key biomarkers—such as uric acid and lipoprotein(a)—that predict patients’ treatment response. Finally, I will explain how our unique multidisciplinary practice in El Paso, Texas, integrates advanced medical oversight with chiropractic care, physical therapy, and functional medicine to create a comprehensive and personalized healing environment for our patients.
A New Era of Collaboration in Patient Care
I am thrilled to announce a significant enhancement to our patient care model here at Injury Medical Clinic. We are honored to welcome Dr. Maria Guadalupe Cardenas, MD, to our team as our Medical Director and Collaborative Physician. Dr. Cardenas is a highly respected, board-certified Internist with over four decades of clinical experience (NPI #1164426749, Texas MD License #J2933).
This collaboration represents a powerful fusion of expertise. Our clinic has always been at the forefront of providing exceptional chiropractic care, physical therapy, and rehabilitation, particularly for those suffering from personal injuries. With Dr. Cardenas providing medical oversight, we can now offer an even more robust and integrated treatment paradigm. This multidisciplinary setup allows us to manage complex cases by combining my expertise in chiropractic, functional, and regenerative medicine with her profound knowledge of internal medicine. This ensures that every aspect of a patient’s health—from musculoskeletal alignment and function to underlying systemic factors—is addressed, creating a truly holistic path to recovery.
The Foundation of Our Approach: Evidence-Based Integrative Care
When I established my practice in El Paso, TX, this environment ingrained in me the necessity of grounding every clinical decision in solid, evidence-based research. We developed a structured protocol to identify which conditions were most appropriate for orthobiologic treatments. This required a deep dive into the scientific literature to ensure we were offering therapies with proven efficacy.
This commitment to evidence is the cornerstone of our practice in El Paso. We specialize in treatments that bridge the gap between conservative care and invasive surgery. Our focus is on harnessing the body’s innate healing capabilities, supported by advanced diagnostics and targeted interventions.
Identifying the Right Conditions for Orthobiologic Therapies
Through rigorous review of studies and extensive clinical experience, we have identified a specific cohort of conditions that respond well to integrative and regenerative treatments. It is crucial to be precise in our diagnosis and patient selection to achieve the best possible outcomes.
Here are some of the primary conditions we treat:
Shoulder: Low-grade, partial-thickness rotator cuff tears and mild-to-moderate glenohumeral arthritis. For arthritis, it is vital to consider the Walsh classification (e.g., A1, A2, B1) to ensure that the joint architecture is stable and that the “golf ball” (humeral head) isn’t falling off the “tee” (glenoid).
Elbow: Lateral epicondylitis (tennis elbow) and medial epicondylitis (golfer’s elbow), as well as proximal partial tears of the ulnar collateral ligament (UCL).
Hand/Wrist: Mild-to-moderate carpometacarpal (CMC) arthritis. A landmark study from my professor at the Mayo Clinic validated the use of biologics for this condition.
Hip: Femoroacetabular Impingement (FAI) of grade two or less, where the labrum is not shredded, and there are no large pincer or cam deformities. We also achieve great results with gluteus medius and hamstring tendinopathy, especially focal mid-portion tears.
Foot/Ankle: Plantar fasciitis.
Knee: Classically, mild-to-moderate knee osteoarthritis and very small meniscal tears.
Interestingly, recent literature has shown promise in the use of PRP post-operatively. Some forward-thinking surgeons now refer patients for a PRP injection between 0 and 6 weeks after a rotator cuff repair to potentially enhance healing.
A Deeper Look at Tendinopathy: Diagnosis and Treatment Strategy
Let’s examine a common case: tennis elbow, or a partial-thickness tear of the common extensor tendon. Using musculoskeletal ultrasound, we can visualize the injury with incredible detail. I look at the tendon in both long-axis and short-axis views to measure the tear’s precise length and width.
A key to my treatment success has been the technique of tenotomy with fenestration. This involves using a needle to meticulously break up the scarred, degenerative tissue throughout the entire length and width of the tear. Many practitioners might inject only into one spot, but I have found that ensuring the biologic agent is delivered throughout the full extent of the damaged area significantly improves results. We are essentially creating micro-trauma to stimulate a new, robust healing cascade and delivering the growth factors right where they are needed most. The study by Gosens et al. (2011) provides strong support for using PRP to treat chronic tennis elbow, and it is a paper I often share with my colleagues to explain the rationale for this approach.
Consider the case of a 31-year-old weightlifter with patellar tendinopathy. His ultrasound revealed a complex picture: early-stage arthritis with a knee effusion (fluid), a large partial-thickness tear of the patellar tendon, heterogeneous echogenicity changes (indicating tendinosis), and even a large calcium deposit. The critical question becomes: what is the primary pain generator? Is it the joint cartilage, the degenerated tendon, or the calcification?
After a thorough discussion about the risks and benefits, and correlating his physical exam findings with the imaging, I decided to treat the tendon tear with PRP. My decision was influenced by research, such as the work of Jason Dragoo, who demonstrated the efficacy of leukocyte-rich PRP for tendinopathy. For a tear of this significant size, PRP provides a powerful concentration of growth factors to orchestrate cellular repair and tissue regeneration. In these challenging cases, pinpointing the source of pain is paramount.
The Nuances of Treating Rotator Cuff Tears
Rotator cuff tears present another layer of complexity. An MRI might show a partial-thickness tear (less than 50% of the tendon’s thickness) and also an interstitial tear (a split within the tendon fibers), along with surrounding edema (fluid). My approach is often to treat both. I will perform a guided injection into the subacromial bursa to reduce inflammation and another directly into the interstitial tear itself.
Using ultrasound guidance is non-negotiable. I can watch the needle in real-time as it passes through the deltoid muscle and subacromial bursa to precisely target the tear on the superficial facet of the greater tuberosity. I use a small amount of fluid to hydrodissect the tissue planes, which confirms I am in the correct location and helps distribute the biologic throughout the length of the tear.
It’s important to clarify terminology. A partial-thickness tear involves only a portion of the tendon’s depth. A full-thickness tear goes all the way through, but this can be a partial-width tear (affecting only part of the tendon’s footprint) or a full-thickness, full-width tear (a complete rupture). Orthobiologics are most effective for partial-thickness and full-thickness, partial-width tears, not complete ruptures, which typically require surgery.
Choosing the Right Tool: PRP vs. Adipose Tissue
When a patient presents with a more severe injury, we must consider more robust therapies. This is where my treatment algorithm helps guide the decision-making process.
For low-grade partial-thickness tears (less than 50%): I will consider PRP, sometimes augmented with dextrose prolotherapy (P2G), to stimulate a healing response.
For high-grade partial-thickness tears (greater than 50%): I will consider using microfragmented adipose tissue.
Why adipose? Adipose tissue is not just fat; it is a rich source of mesenchymal stem cells (MSCs) and other perivascular cells that create a biological scaffold. This scaffold provides a structural framework and a sustained-release reservoir of signaling molecules that guide tissue repair over a longer period. This is particularly beneficial in larger defects where a simple injection of PRP might not be sufficient to bridge the gap. For moderate-to-severe arthritis (Kellgren-Lawrence grade 3-4), I also lean towards adipose tissue or bone marrow aspirate concentrate (BMAC) for their more potent anti-inflammatory and regenerative capabilities.
For patients with neuralgia or nerve entrapment, I have found that hydrodissection—using fluid to carefully separate the nerve from surrounding fibrotic tissue—can provide significant relief by freeing the nerve and reducing compression.
An Algorithmic Approach to Treating Knee Osteoarthritis
To standardize care and optimize outcomes, I have developed a treatment algorithm for patients with knee osteoarthritis (OA). This systematic process ensures we address all contributing factors:
Assess Systemic Health: First, I investigate for underlying systemic diseases (like autoimmune conditions) or factors that impair healing. We must address the whole person, not just the knee.
Evaluate Functional Markers: Next, I consider a functional medicine workup. What are their hormone levels? Is there evidence of gut dysbiosis or microbiome imbalance? These factors create the systemic environment in which the knee must heal.
Grade the Arthritis: Using X-rays and MRIs, I determine the severity. Is it grade 3 or 4 arthritis? Is there significant subchondral bone edema (a sign of stress and inflammation in the bone beneath the cartilage)?
Select the Treatment:
If the patient has mild-to-moderate OA (grade 1-2) without the above complicating factors, PRP is my first-line orthobiologic treatment.
If they have severe OA (grade 3-4) or significant bone edema, I will discuss microfragmented adipose tissue or BMAC.
Monitor and Adjust: Healing is a process. PRP typically causes increased soreness for about three days, with functional improvements beginning around weeks three to six. By twelve weeks, we should have a clear indication if we are on the right track. If the patient has achieved at least 60% improvement, we continue with our supportive care plan. If not, we re-evaluate and adjust the strategy.
The Future is Now: Machine Learning and Personalized Medicine
A groundbreaking study published in April 2026 in BMC Musculoskeletal Disorders is already changing how I think about patient selection. Researchers in China used a machine learning algorithm to predict clinical response to PRP for knee osteoarthritis. They analyzed a vast dataset including patient demographics, BMI, lab markers, and pain scores.
The algorithm aimed to identify the factors that were most predictive of a high response rate (defined as increasing the success rate from 65% to 85%). The results were fascinating. While we often focus on the “special recipe” of the PRP itself, the study found that three biomarkers were most important in predicting success:
Osmotic Pressure (Joint Swelling): This was self-explanatory. My clinical experience confirms that patients with recurrent, large effusions do not respond as well. The inflammatory environment dilutes the biologic and impedes healing.
Lipoprotein(a) [Lp(a)]: A marker for cardiovascular risk, elevated Lp(a) is also strongly associated with inflammation.
Uric Acid: Commonly known for its role in gout, high uric acid is a powerful pro-inflammatory marker.
This study reinforces the critical link between systemic metabolic health and local musculoskeletal healing. It’s making me consider routinely checking uric acid and Lp(a) levels in my patients. Perhaps by addressing these metabolic imbalances first—through diet, lifestyle, and targeted supplementation, a core principle of functional medicine—we can turn potential non-responders into high-responders. It highlights the importance of our integrative model, in which chiropractic adjustments and physical therapy optimize biomechanics, while functional and internal medicine address the underlying biochemistry.
This is the future of medicine: personalized, predictive, and integrative. By combining advanced orthobiologics, sophisticated diagnostics, and a deep understanding of the body as an interconnected system, we can offer our patients in El Paso a truly transformative level of care.
References
Gosens, T., Peerbooms, J. C., van Laar, W., & den Oudsten, B. L. (2011). Ongoing positive effect of platelet-rich plasma versus corticosteroid injection in lateral epicondylitis: a double-blind randomized controlled trial with 2-year follow-up. The American Journal of Sports Medicine, 39(6), 1200–1208. https://doi.org/10.1177/0363546510397173
Functional Orthopedics for Spine and Joint Health: The Unit Approach to Integrative Care
Abstract
Hello, I’m Dr. Alex Jimenez. In this educational post, we will journey beyond traditional pain management to explore a comprehensive, patient-centered model for treating musculoskeletal conditions. I will introduce the concept of Interventional and Functional Orthopedics, a philosophy that goes beyond simply treating a “pain generator” to address the body’s entire functional unit. We will delve into the latest evidence-based research from leading experts, examining how treating intra-articular (inside the joint), extra-articular (outside the joint), and even intraosseous (inside the bone) structures can lead to superior, long-term outcomes. This discussion will highlight the critical interplay between structure and function, from the microscopic level of cellular health in the subchondral bone to the macroscopic mechanics of how your hip and ankle affect your knee. I’ll also explain how our unique, multidisciplinary practice at Injury Medical Clinic PA integrates cutting-edge chiropractic care, advanced rehabilitation, and medical oversight to restore not just comfort, but true, lasting function.
Our Integrated Approach: A Collaboration for Your Health
At Injury Medical Clinic PA, we believe that the future of healthcare lies in collaboration. That’s why I am proud to announce a significant development for our practice and our community here in El Paso, Texas. I, Dr. Alex Jimenez, am thrilled to be working alongside Dr. Maria Guadalupe Cardenas, MD, who has joined our team as the Medical Director and Collaborative Physician.
Dr. Cardenas is a highly respected internist, Board Certified in Internal Medicine, with an impressive career spanning over 40 years (NPI #1164426749, Texas MD License #J2933). Her extensive experience and deep understanding of internal medicine provide an invaluable layer of medical oversight and diagnostic expertise to our practice.
This multidisciplinary setup allows us to offer a truly integrative model of care. Here’s how our team works together for you:
Medical Direction (Dr. Cardenas): Provides comprehensive medical evaluations, oversees patient care plans, and manages any underlying medical conditions that could be contributing to musculoskeletal pain. While our focus remains on non-surgical solutions, her expertise ensures that all aspects of your health are considered.
Chiropractic & Functional Neurology (Dr. Jimenez): I focus on the body’s biomechanical and neurological integrity. Through precise chiropractic adjustments, spinal decompression, and advanced soft tissue therapies, we correct structural misalignments that are often the root cause of pain and dysfunction.
Functional Medicine & Rehabilitation: We dive deep to understand the “why” behind your condition. This includes advanced diagnostics, nutritional counseling, and personalized rehabilitation programs designed to strengthen weaknesses, improve mobility, and restore proper movement patterns.
Personal Injury Care: Our integrated team is uniquely equipped to manage the complex needs of patients injured in accidents, providing comprehensive documentation and a coordinated treatment plan that addresses everything from acute spinal injury to long-term rehabilitation.
By combining the structural focus of chiropractic care with the medical oversight of an experienced internist, we ensure a safe, effective, and holistic journey back to health. Our focus at elpasobackclinic.com remains centered on chiropractic and physical rehabilitation, but this collaboration allows us to address the whole person in a way that sets a new standard for patient care.
Beyond the Pain Point: Understanding Interventional Orthopedics
For years, the standard approach to joint pain was to identify the single “thing” causing the pain and treat it. This might mean an injection into a knee joint or therapy focused solely on a sore shoulder. But I ask, is that enough? What if the pain is just a symptom of a much larger, more complex issue?
This is where the concept of Interventional Orthopedics comes in. It’s a philosophy that shifts our focus from just treating the pain to understanding and treating the entire system. It means we’re not just “chasing the pain.” Instead, we use advanced imaging guidance, such as musculoskeletal ultrasound and fluoroscopy, to precisely target and treat the specific anatomical structures involved in a person’s unique condition. We look at the whole picture.
But how do we know what to target? How do we build a treatment plan that goes beyond the obvious? This brings us to a philosophy I’ve developed based on my background and clinical experience: Functional Orthopedics.
Functional Orthopedics: The “Why” Behind the “What”
You likely haven’t heard the term Functional Orthopedics before, because it’s a concept I’ve coined to describe my approach. However, the principles behind it are timeless and deeply rooted in well-established medical philosophies. It draws heavily from my training as an osteopathic physician and my background in Physical Medicine and Rehabilitation (PM&R).
The core tenets are:
The Body is a Unit: No part of the body works in isolation. The foot is connected to the knee, the knee to the hip, the hip to the spine. A problem in one area will inevitably affect others.
Structure and Function are Interrelated: The way your body is built (structure) dictates how it moves (function), and vice versa. Poor movement patterns can lead to structural damage, and structural problems will compromise function.
The Body Has Self-Healing Mechanisms: Our bodies possess an incredible, innate ability to heal. Our role as clinicians is to identify and remove the barriers to this process and provide the necessary support to facilitate it.
Rational Treatment is Based on These Principles: A truly effective treatment plan must honor these truths.
Functional Orthopedics applies these principles by looking for the root causes of a condition. Imagine a tree. The leaves and branches might be the symptoms—the knee pain, the back ache—but the real problem may lie in the roots and the soil. We need to examine all factors that may be involved in optimizing the patient’s biological environment for healing. A crucial part of this is the Functional Unit Approach.
The Functional Unit Approach: Treating the System, Not Just the Joint
The idea of a “functional unit” originated in the surgical literature, specifically in the context of the functional spinal unit. Surgeons recognized that when dealing with the spine, you couldn’t just look at a single vertebra or disc. You had to consider the adjacent vertebrae, the disc between them, the ligaments holding them together, the facet joints that guide their movement, and the muscles that power them. All these components work together as a single unit.
We are now applying this powerful concept to the world of orthopedics and regenerative medicine. Recent research is validating this comprehensive approach.
Studies on the Spine: Pioneering research has investigated the use of orthobiologics such as Platelet-Rich Plasma (PRP) and Bone Marrow Aspirate Concentrate (BMAC) in the spine. Instead of just injecting one area, researchers treated the entire functional unit: the epidural space, facet joints, stabilizing ligaments, and paraspinal muscles. The results showed more significant and longer-lasting benefits compared to single-target treatments.
Expanding to the Knee: This principle isn’t limited to the spine. A landmark study looked at patients with knee osteoarthritis. One group received a standard intra-articular (inside the joint) injection. The other group received injections both intra-articularly and into the extra-articular structures—the surrounding ligaments and tendons that stabilize and support the knee. While both groups improved, the group that received the comprehensive treatment reported significantly better outcomes.
This marks a major paradigm shift. For conditions like knee osteoarthritis, we should not just be injecting the joint space. We must also assess and treat the supporting cast of characters—the ligaments, tendons, and muscles that make up the knee’s functional unit. But does it stop there?
The Critical Role of Subchondral Bone: Digging Deeper
For decades, we were taught—and we taught our patients—that osteoarthritis is a disease of cartilage. You’ve likely heard someone say, “My cartilage is gone,” as if that’s the end of the story. While cartilage loss is a feature of osteoarthritis, we now recognize that it does not always equate to pain. The plot thickens when the damage goes deeper.
When cartilage wears away, the underlying bone, known as the subchondral bone, becomes exposed to abnormal stress. This bone is not a dead, inert scaffold; it is a living, dynamic tissue rich with blood vessels, nerves, and even a reservoir of stem cells (pericytes) crucial for healing.
Dr. Philippe Hernigou, a true pioneer in regenerative medicine, conducted groundbreaking research comparing the stem cell populations in bone marrow. He found that as knee osteoarthritis worsens with age, the concentration of healing cells in the subchondral bone of the knee declines dramatically, whereas the concentration at a distant site, such as the pelvis (PSIS), remains relatively stable. This tells us that the local healing environment within the arthritic joint becomes depleted. The bone itself is sick.
This has led to a revolutionary treatment strategy: intraosseous injections, or injections directly into the subchondral bone.
Evidence for Intraosseous PRP: A recent meta-analysis and a consensus statement we just published for the American Academy of Physical Medicine and Rehabilitation (AAPM&R) have recognized the significant merit of injecting PRP directly into the bone for knee osteoarthritis, particularly in more advanced cases.
Compelling Data on Bone Marrow: The most robust data, in my opinion, comes from two sister studies on intraosseous bone marrow aspirate concentrate (BMAC).
In the first study, patients had one knee that had already been replaced and a second knee with severe osteoarthritis. The arthritic knee was treated with an intraosseous BMAC injection. With an average follow-up of 15 years, an astounding 80% of these patients avoided a knee replacement on the treated side. Furthermore, they overwhelmingly preferred their “bone marrow knee” to their artificial one.
The second study involved patients with severe osteoarthritis in both knees who wanted to avoid surgery. One knee received an intra-articular BMAC injection, while the other received an intraosseous BMAC injection. While both knees improved, the knees treated with the intraosseous injection had a significantly lower rate of eventually needing a knee replacement.
The message is clear: for moderate-to-severe osteoarthritis, the most effective approach must address the entire functional unit—the intra-articular space, the extra-articular soft tissues, and the underlying subchondral bone.
The Art of Diagnosis: How We Decide What to Treat
So, how do we put this all together in the clinic? How do we analyze the complex interplay of forces and decide which structures to treat? This is where a thorough physical examination and a deep understanding of biomechanics become indispensable. It is not just a matter of “poking to see where it hurts.”
Let’s use the knee as an example:
Varus Stress (Bow-Legged): If a patient presents with a bow-legged posture, the medial (inner) part of their knee is under compressive stress. This might lead to medial knee osteoarthritis or a medial meniscus tear. In addition to treating these compressed structures, we must ask: what is happening on the other side? The lateral collateral ligament (LCL) on the outside of the knee is likely being chronically stretched and weakened. To restore stability to the entire functional unit, we must also address this laxity in the LCL.
Valgus Stress (Knock-Knees): Conversely, in a patient with knock-knees, the lateral (outer) part of the joint is compressed. But we also need to examine the medial structures, such as the medial collateral ligament (MCL), which may be overstretched and require support.
Patellofemoral Maltracking: If the kneecap (patella) is being pulled laterally (to the outside), causing pain and cartilage wear, it’s not enough to just treat the cartilage. We must investigate why it’s maltracking. Often, the medial patellofemoral ligament (MPFL), which acts as a tether to prevent lateral movement, becomes lax. Treating and tightening this ligament is key to correcting the underlying mechanical problem.
Looking Proximal and Distal: The Buck Doesn’t Stop at the Knee
Here is the final piece of the puzzle, and it’s one I implore every patient and clinician to consider. If someone develops knee pain, like a meniscus tear or patellofemoral pain, without a specific traumatic injury, does the problem really originate in the knee?
Or should we be looking elsewhere?
The Hip and Glutes: The gluteal muscles, particularly the gluteus medius, are critical for pelvic and knee stability. Weakness in these muscles is a very common driver of knee pain and faulty movement patterns. As a clinician, I always strength-test these muscles.
The Ankle and Foot: How a person’s foot strikes the ground reverberates up the entire kinetic chain. Poor foot mechanics, such as overpronation, can cause the tibia to rotate internally, placing abnormal stress on the knee.
The Lumbar Spine: Is there a subclinical radiculopathy? A subtle nerve irritation in the lower back could be causing weakness in the muscles that control the leg, leading to instability and pain downstream at the knee. We must test for this.
True, long-term success comes not from just treating the joint itself but from identifying and correcting these dysfunctions throughout the kinetic chain. This is what it means to look at the patient as a whole. This is the essence of integrative chiropractic care and functional rehabilitation. By correcting spinal and pelvic alignment, restoring proper nerve function, and strengthening weak links in the chain, we don’t just put a bandage on the problem—we rebuild the foundation for lasting health.
This journey back to our roots in physical diagnosis, combined with the exciting advancements in orthobiologics, allows us to provide truly transformative care. It’s about creating not just a “pain generator” treatment plan, but a “health and function generator” plan for life.
Platelet-Rich Plasma and Chiropractic Joint Healing
Abstract
This educational post explores the sophisticated science behind regenerative medicine, with a particular focus on Platelet-Rich Plasma (PRP) therapy for joint and soft-tissue conditions. We will navigate the evolving understanding of PRP composition, moving beyond the older concepts of “leukocyte-rich” versus “leukocyte-poor” to a more nuanced, dose-dependent perspective. Drawing on the latest research, I will explain why the total number of platelets delivered to a target tissue is now considered a primary driver of clinical success. We will discuss the specific roles of white blood cell types (leukocytes), such as granulocytes, lymphocytes, and monocytes, in orchestrating the healing cascade. Crucially, this post will detail how integrative chiropractic care is essential for optimizing the outcomes of these advanced biological treatments. By combining regenerative injections with targeted chiropractic adjustments, advanced physical therapy, and functional medicine, we can create a synergistic healing environment that addresses both the biological and biomechanical aspects of an injury, ensuring a more complete and lasting recovery for my patients at El Paso Back Clinic.
As a practitioner dedicated to the principles of functional and integrative medicine, my mission has always been to seek out and apply the most effective, evidence-based treatments for my patients. Over the years, I’ve seen the field of regenerative medicine undergo a remarkable evolution. One of the most exciting areas is the use of Platelet-Rich Plasma (PRP), a therapy that harnesses a patient’s own biological material to stimulate healing. Today, I want to take you on a journey into the intricate world of PRP, sharing the latest findings from leading researchers and explaining how we apply this science in our clinic to help patients recover from chronic pain and injury. We’ll move past some older terminology and dive deep into what truly matters for successful outcomes: platelet dosing and the synergistic role of specific cell types.
The Critical Role of Platelet Concentration in PRP Therapy
A common question I receive from both patients and colleagues is about the specifics of the PRP preparations we use. They often ask, “What was the concentration you used?” and want to know about the composition, particularly the debate between “leukocyte-rich” versus “leukocyte-poor” PRP.
This is an excellent question, and the answer is more detailed than a simple choice between two options. To illustrate with a clinical example, in a recent case, we achieved a platelet concentration factor of approximately 7.5 times the patient’s baseline blood level. It’s important to understand that this concentration isn’t a fixed number; it varies from patient to patient based on their unique physiology. In my clinical experience over nearly four years of using advanced PRP processing systems, I’ve consistently observed concentrations in the 6x to 10x range.
The key takeaway here is that the processing method is paramount. Modern systems allow us to be incredibly precise. In our clinic, we use a system that isolates the buffy coat—a thin layer in centrifuged blood that is densely packed with platelets and leukocytes (white blood cells). This method ensures we capture the vast majority of available platelets. By maximizing this platelet capture, we are focusing on what recent research has identified as a crucial factor for success: the total platelet dose.
Beyond a Simple Dichotomy: Re-evaluating Leukocytes in Healing
For many years, the regenerative medicine community categorized PRP into two main types:
Leukocyte-Rich (LR-PRP): Containing a high concentration of white blood cells.
Leukocyte-Poor (LP-PRP): Containing a low concentration of white blood cells.
This framework emerged around 2011-2012 and provided a useful way to conceptualize what was being injected into a joint or tendon. It was a simple “yes or no” system that allowed us to start differentiating preparations. The prevailing thought was that, for certain conditions, such as tendon injuries, the pro-inflammatory nature of LR-PRP might be beneficial, whereas for others, such as joint arthritis, the less inflammatory LP-PRP might be superior.
However, scientific understanding is not static; it evolves. In a significant development around 2022, the very same researchers who first proposed this “rich versus poor” classification published a new paper. Their updated findings, specifically regarding joint arthritis, suggested that in the long run, the distinction between leukocyte-rich and leukocyte-poor PRP did not significantly impact outcomes (Driban et al., 2022). The focus began to shift from the cell ratio to the absolute number of healing cells delivered. The new paradigm became centered on platelet dosing—how many total platelets are we successfully delivering to the site of injury?
This makes intuitive sense. Platelets are the primary drivers of tissue repair, releasing a symphony of growth factors that orchestrate the healing process. It stands to reason that delivering a higher, more potent dose of these signaling molecules would lead to a more robust clinical response. Retrospectively, it appears that many of the early studies showing better results with “leukocyte-rich” systems may have been observing a confounding variable: those systems also yielded higher total platelet counts. The success was likely due to the higher platelet dose, not necessarily the presence of leukocytes alone.
The Specialized Roles of Leukocytes: Not All White Blood Cells Are the Same
This shift in understanding doesn’t mean leukocytes are unimportant. On the contrary, we now appreciate their roles with greater nuance. Instead of viewing them as a monolithic group that is either “good” or “bad,” we now recognize that different types of leukocytes have distinct and vital functions in the healing cascade.
Our advanced PRP processing system allows for this nuanced approach. While the buffy coat contains the bulk of the platelets, we also strategically capture a small portion of the red cell layer just below it. This zone, once feared for being overly inflammatory, is actually rich in specific leukocyte types that are highly beneficial.
Let’s break down the key players:
Granulocytes: These are a type of white blood cell often associated with the initial, acute inflammatory response. While a massive, uncontrolled influx can be detrimental, their presence in controlled numbers is part of the natural healing process. They are the “first responders” that help clear debris from the injury site.
Lymphocytes and Monocytes: These are the real stars of the secondary healing phase. Our preparation method is designed to maximize the inclusion of these specific cells. Monocytes, in particular, are critical. When they migrate from the bloodstream into the tissue, they differentiate into macrophages. These macrophages are essential for modulating inflammation and directing the regenerative process. The presence of lymphocytes and other signaling molecules in the PRP helps guide these monocytes toward a pro-healing, anti-inflammatory “M2 macrophage” phenotype, which is crucial for long-term tissue repair and remodeling.
So, to summarize, our goal is not simply to create a “leukocyte-rich” PRP. It is to create a biologically optimized PRP that contains:
A high dose of platelets to deliver a powerful payload of growth factors.
A beneficial concentration of monocytes and lymphocytes to help orchestrate the subsequent phases of tissue repair and inflammation resolution.
This sophisticated approach ensures we are not just initiating inflammation but guiding the body through the entire healing process, from cleanup to rebuilding.
Integrative Chiropractic Care: The Essential Framework for Regenerative Success
Here is where the worlds of advanced regenerative medicine and foundational chiropractic care merge. Injecting a high-quality PRP preparation is a powerful tool, but it is only one piece of the puzzle. At El Paso Back Clinic, we understand that for healing to be successful and durable, we must address the entire functional unit—not just the damaged tissue. This is the core philosophy of integrative chiropractic care.
1. Correcting Biomechanical Imbalances
Imagine we are treating a patient’s arthritic knee with PRP. The injection can do wonders in reducing inflammation and stimulating cartilage repair. However, if that patient has a misaligned pelvis, a functional leg-length discrepancy, or poor foot mechanics, abnormal stress will continue to be placed on the knee joint. This constant, improper loading can undermine the healing process initiated by the PRP and lead to a recurrence of symptoms.
This is why a thorough chiropractic and biomechanical assessment is the first step. Through specific chiropractic adjustments, we can:
Restore proper joint alignment in the spine, pelvis, and extremities.
Improve nervous system function to ensure the brain can communicate with and control the muscles that support the joint.
Correct postural distortions that place undue stress on injured tissues.
By optimizing the body’s biomechanics, we create an environment where the PRP-stimulated healing can occur without being constantly disrupted by mechanical dysfunction. We are ensuring the “house” is built on a solid foundation.
2. Advanced Physical Therapy for Functional Restoration
Once the PRP injection has initiated the biological repair process and chiropractic adjustments have corrected the structural framework, the next step is to rebuild functional strength and stability. This is accomplished through a customized physical therapy and rehabilitation program.
Our approach goes beyond simple exercises. We focus on:
Neuromuscular Re-education: Retraining the brain and muscles to work together in proper movement patterns. After an injury, the body often develops compensatory strategies that are inefficient and can lead to further problems. We work to overwrite these faulty patterns.
Proprioceptive Training: Enhancing the body’s sense of position and movement. This is crucial for joint stability and preventing re-injury.
Targeted Strengthening and Flexibility: Building strength in the specific muscles that support and protect the healing joint while improving the flexibility of tight, restricted tissues.
This active rehabilitation is critical. The mechanical loading from therapeutic exercise provides the necessary signals to the healing tissues, guiding the new collagen fibers to align properly and form strong, resilient tissue. It turns the healing potential created by PRP into actual, functional strength.
3. Functional Medicine: Supporting Healing from the Inside Out
Finally, we look at the patient’s overall health through the lens of functional medicine. A successful regenerative outcome depends on the body’s systemic ability to heal. We assess and optimize factors such as:
Nutritional Status: Ensuring the patient has the necessary building blocks (amino acids, vitamins, minerals) for tissue repair.
Inflammatory Balance: Using diet and targeted supplements to manage systemic inflammation, which can otherwise hinder local healing.
Hormonal Health: While we keep this in the background, we are aware that hormones like testosterone and growth hormone play roles in tissue regeneration. We support the body’s natural balance to create an optimal internal healing environment.
By integrating these three pillars—precise regenerative injections, foundational chiropractic care, and functional rehabilitation—we create a powerful, synergistic effect. We are not just treating a symptom; we are treating the whole person and addressing the root causes of their condition from every angle. This comprehensive model is the future of musculoskeletal care and how we achieve lasting results for our patients at El Paso Back Clinic.
References
Driban, J. B., McCulloch, P. C., & Rodeo, S. A. (2022). Do leukocytes in platelet-rich plasma really matter for the treatment of osteoarthritis? Moving from the “leukocyte-rich” versus “leukocyte-poor” dichotomy. The American Journal of Sports Medicine, 50(14), 3981–3986. https://doi.org/10.1177/03635465221128362
Jimenez, A. (n.d.). About Dr. Alex Jimenez. El Paso Back Clinic. Retrieved May 2, 2026, from https://elpasobackclinic.com/
Jimenez, A. (n.d.). Alex Jimenez DC, APRN, FNP-BC. LinkedIn. Retrieved May 2, 2026, from https://www.linkedin.com/in/dralexjimenez/
Chiropractic and Regenerative Joint Pain Care: An Evidence-Based Approach
Abstract
Welcome to our educational series. I’m Dr. Alexander Jimenez, and today, we’ll explore the sophisticated world of regenerative medicine, specifically focusing on platelet-rich plasma (PRP) and its applications in managing joint pain, particularly osteoarthritis. This post translates complex clinical research into practical insights, exploring patient selection, treatment protocols, and the crucial role of integrative care. We will discuss the science behind PRP, including platelet concentration, the debate between leukocyte-rich versus leukocyte-poor preparations, and how these factors influence patient outcomes. Furthermore, we’ll examine how we integrate these advanced biologic treatments with our foundational chiropractic and physical therapy principles to create a comprehensive, patient-centered journey toward healing and restored function. We’ll navigate the nuances of post-injection care, the timing of treatments relative to other interventions, such as cortisone shots, and the latest evidence-based strategies to optimize results. Our goal is to empower you with a clear understanding of how these modern therapies work synergistically with established musculoskeletal care, not just to alleviate pain but to foster true, long-term healing.
Hello, I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. It’s a privilege to share insights from the forefront of musculoskeletal and regenerative medicine. In my practice, we are dedicated to merging the latest scientific advancements with a holistic, patient-first philosophy. Today, I want to guide you through a fascinating and rapidly evolving area: the use of platelet-rich plasma (PRP) for joint conditions like osteoarthritis. We will explore how we, as integrative practitioners, make clinical decisions based on cutting-edge research and how these decisions fit within a broader chiropractic and physical therapy framework to optimize your recovery.
Optimizing Patient Selection for Regenerative Therapies: Who is the Ideal Candidate?
A common and critical question I encounter is, “Am I a suitable candidate for PRP?” Patients often wonder if there are strict cutoffs based on age, body mass index (BMI), or the severity of their arthritis.
Based on the latest evidence and my clinical experience, the answer is more nuanced than simple metrics. While there can be a subtle bias against higher BMI, the primary predictor of a successful response to PRP is the nature of the patient’s symptoms, not their demographic profile.
Ideal Candidates: Patients who describe their pain as a broad, achy, and inflammatory sensation tend to respond remarkably well. This type of pain often signals an underlying inflammatory process that PRP is uniquely equipped to modulate. In these cases, age and the degree of arthritis seen on an X-ray are less critical factors. We have seen patients in their nineties achieve significant relief.
Less Predictable Candidates: Conversely, individuals who experience sharp, stabbing, or mechanical pressure-type pain often have a more complex clinical picture. This type of pain can indicate issues beyond simple inflammation, such as bone marrow lesions, significant meniscal tears, or other “pain generators” that create mechanical blocks or instability. While these patients may still benefit from PRP, our treatment algorithm must be expanded to address concurrent issues, often through targeted physical therapy and chiropractic adjustments.
It is a matter of managing expectations. For a patient with severe arthritis who is exploring alternatives to knee replacement, we might discuss the potential for a 30-60% improvement over several months. I am always transparent: no treatment is 100% effective. Our approach is to create a personalized, evidence-informed plan that maximizes your chances of success.
The Science of PRP: Leukocyte-Rich vs. Leukocyte-Poor
The conversation around PRP often involves technical terms like leukocyte-rich (LR-PRP) and leukocyte-poor (LP-PRP). Leukocytes are white blood cells, and their presence in the PRP injectate is a subject of significant debate.
A preparation is generally considered “leukocyte-rich” if the concentration of white blood cells exceeds that in the patient’s baseline whole blood. Most commercial PRP systems produce a leukocyte-rich product. The key distinction lies in the types of leukocytes present. The current focus in research is on reducing pro-inflammatory neutrophils while preserving monocytes, which are crucial for tissue remodeling and healing.
Leukocyte-Poor (LP-PRP): This is often preferred for injections near sensitive structures, such as nerves or the spine, where minimizing the initial inflammatory response is paramount.
Leukocyte-Rich (LR-PRP): For most joint and soft tissue applications, a degree of inflammation is not only acceptable but beneficial. This initial inflammatory flare, driven by the leukocytes and platelets, is what kickstarts the healing cascade. Patients receiving LR-PRP might experience more swelling and soreness for a day or two, but this is a sign that the body’s regenerative engine is firing up.
At our clinic, we recognize that the most critical factor in treating conditions like osteoarthritis is the total platelet dose delivered to the joint. Research overwhelmingly supports that a higher platelet count correlates with better clinical outcomes. While we can fine-tune the leukocyte profile, we never want to sacrifice the platelet dose to do so.
The Cornerstone of Recovery: Integrating Chiropractic and Physical Therapy
Regenerative injections like PRP are powerful tools, but they are not a “magic bullet.” True and lasting healing requires a comprehensive approach that addresses the root cause of the joint dysfunction. This is where integrative chiropractic care and physical therapy become indispensable.
The human body is an intricate system of levers and pulleys. If a joint is in pain, it’s often due to improper biomechanics, muscular imbalances, or postural deficits that place abnormal stress on the joint. Injecting PRP can reduce inflammation and stimulate tissue repair, but if the underlying mechanical problems aren’t corrected, the joint will remain under duress, and the pain will likely return.
This is why our protocol is built on a foundation of musculoskeletal care:
Chiropractic Adjustments: We use precise adjustments to restore proper joint alignment and mobility. For a knee, this involves assessing and correcting mechanics not just in the knee itself but also in the hips, ankles, and spine. A misaligned pelvis or a collapsed arch in the foot can profoundly alter the forces acting through the knee joint. By correcting these issues, we ensure that the healing environment stimulated by PRP is not compromised by ongoing mechanical stress.
Targeted Physical Therapy: Our physical therapy programs are designed to complement both chiropractic adjustments and regenerative injections. The goals are to:
Strengthen Supporting Musculature: We build strength in the muscles around the affected joint (e.g., quadriceps, hamstrings, and glutes for the knee) to provide dynamic stability.
Improve Flexibility and Range of Motion: Gentle stretching and mobility exercises help prevent stiffness and ensure the joint can move through its full, healthy range of motion.
Neuromuscular Re-education: We retrain the body to move correctly, correcting faulty movement patterns that contributed to the initial injury. This is crucial for long-term prevention.
This synergistic approach ensures that we are not just treating the symptom (pain) but are fundamentally rebuilding the joint’s functional capacity. The PRP provides the biological “scaffolding” and signaling for repair, while chiropractic and physical therapy provide the mechanical and functional framework for that repair to be successful and durable.
Clinical Protocols and Timing: Maximizing Therapeutic Benefit
The timing and technique of regenerative treatments are critical. Many patients come to us having had previous cortisone injections. Corticosteroids are potent anti-inflammatories, but they are also catabolic, meaning they can break down tissue and suppress the very cellular activity that PRP aims to stimulate.
Therefore, we adhere to a strict washout period. Based on studies of steroid residency in joint spaces, we typically wait a minimum of 30 to 35 days after an intra-articular cortisone injection before administering PRP. This allows the steroid’s suppressive effects to dissipate, ensuring the joint environment is receptive to regenerative signals from platelets.
Dose and Volume: Customizing the Injection
A guiding principle in regenerative medicine is the delivery of an adequate platelet dose. The larger the joint and the more severe the condition, the more platelets are needed. This has led to innovative techniques for maximizing the therapeutic payload.
For a large joint like the knee, we might first draw off the most concentrated fraction after preparing the PRP. For example, if we process a blood draw and obtain 4-5 cc of PRP, the final 1-2 cc at the bottom of the syringe (closest to the red blood cell layer) will have the highest platelet concentration. In a patient with severe arthritis who can tolerate more volume, I might:
Inject the most potent, platelet-dense fraction first.
Follow this with the next-most concentrated layer.
Finally, inject the remaining platelet-poor plasma (PPP), which contains valuable proteins and growth factors that help modulate inflammation.
This layering technique allows us to deliver a very high total number of platelets and other beneficial biological factors, essentially “hyper-dosing” the joint to maximize the healing response. For a large knee, we might inject up to 15 cc of total volume if the patient can comfortably accommodate it.
The research is detailed: dose matters. My clinical observations confirm that achieving a higher platelet count, especially in moderate-to-severe osteoarthritis, yields a more robust and lasting clinical improvement (Everhart et al., 2019).
The Role of Peptides and Other Biologics
The field of regenerative medicine is constantly exploring synergistic therapies. One area of growing interest is the combination of PRP with peptides like BPC-157. BPC-157 is a peptide chain known for its ability to promote angiogenesis (the formation of new blood vessels), which is fundamental to tissue healing.
While human data is still emerging, animal studies suggest that combining PRP with BPC-157 could enhance the healing response. The logic is compelling: PRP initiates the inflammatory and repair cascade, while BPC-157 may accelerate the development of a rich blood supply needed to fuel that repair process. This is an exciting frontier, and as more robust data becomes available, we will continue to integrate evidence-based combination therapies into our protocols.
As we continue this journey together, remember that our mission is to provide you with the most advanced, evidence-based, and personalized care possible. By integrating the biological power of regenerative medicine with the foundational principles of chiropractic and physical therapy, we can move beyond merely managing symptoms and guide you toward true, functional recovery.
References
Everhart, J. S., Cavendish, P. A., & Flanigan, D. C. (2019). Platelet-Rich Plasma Preparation and Composition. In D. C. Flanigan (Ed.), Platelet-Rich Plasma in Orthopaedics and Sports Medicine (pp. 11-20). Springer. https://link.springer.com/chapter/10.1007/978-3-030-01919-3_2
LaPrade, R. F., Dragoo, J. L., Rodeo, S. A., & Chu, C. R. (2021). The Orthobiologic Classification System: A Data-Driven Approach for the Standardization of Orthobiologic Reporting. The American Journal of Sports Medicine, 49(12), 3121–3129. https://doi.org/10.1177/03635465211029519
Meheux, C. J., McCulloch, P. C., Lintner, D. M., Varner, K. E., & Harris, J. D. (2016). Efficacy of intra-articular platelet-rich plasma injections in knee osteoarthritis: A systematic review. Arthroscopy: The Journal of Arthroscopic & Related Surgery, 32(3), 495-505. https://doi.org/10.1016/j.arthro.2015.08.005
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine