Reversing Severe Lumbago and Disc Compression from Amazon Fulfillment Shifts
Abstract: Severe low-back pain after fulfillment work or delivery routes can feel like a one-way road toward surgery. Yet many cases deserve a careful conservative evaluation first. This guide explains how repetitive bending, sorting, vehicle vibration, and lifting can aggravate lumbago and disc-related pain; where mechanical alignment and selected non-surgical decompression may fit; how medical oversight screens red flags; and how Amazon workers can use practical lifting limits to reduce repeat flares.
When a Shift Starts Loading the Lumbar Spine
A warehouse associate may begin a shift feeling stiff. Hours later, repeated low-bin reaches, package twisting, sorting, pallet work, or lifting away from the body can turn stiffness into severe lumbago. Delivery drivers add prolonged sitting, road vibration, repeated cabin exits, carrying, and awkward curbside lifts.
The problem is often cumulative. When the trunk bends and rotates while a load stays away from the body, spinal muscles must generate more force to control movement. Repetition can fatigue those tissues and degrade movement quality. NIOSH treats load weight, reach distance, vertical height, twisting, lifting frequency, duration, and grip quality as factors that change lifting risk (NIOSH, 2024).
That matters because “safe lifting” is not one universal number. A box manageable at waist height may be too demanding on the floor, far from the body, poorly gripped, or lifted repeatedly near the end of a long shift.
Why Pain Can Spike After the Shift
Symptoms may intensify after clocking out because fatigued muscles provide less support, sitting stiffens the hips, and irritated tissues remain sensitive after repeated loading. Delayed soreness doesn’t mean a disc suddenly worsened. Track which movements, loads, positions, and recovery habits consistently increase or decrease symptoms across workdays.
What “Disc Compression” Really Means
Between the lumbar vertebrae, intervertebral discs distribute load and allow movement. A disc is not a jelly doughnut that simply pops out and can be pushed back into place. It is a load-bearing structure with a fibrous outer ring and softer inner region. Repeated flexion, compression, rotation, aging, prior injury, and anatomy can contribute to disc changes.
Pain may come from several overlapping sources:
Irritated lumbar joints or surrounding soft tissues
Protective muscle spasm and reduced hip motion
Disc-related inflammation or mechanical sensitivity
A disc herniation that irritates a nerve root
Deconditioning after repeated pain episodes and activity avoidance
This is why a structural examination matters. The goal is to match symptoms with movement findings, neurologic testing, work demands, and imaging when indicated. Low-back guidelines support exercise, education, and selected manual or mobilization approaches as part of conservative care rather than a single passive treatment (George et al., 2021).
Step One: Restore Motion Without Forcing the Spine
At El Paso Back Clinic, targeted mechanical care begins with a practical question: which movements are limited, painful, unstable, or poorly coordinated?
One worker may have stiff hips that force repeated lumbar bending. Another may have painful lumbar joints that limit extension. A driver can show a different pattern after hours of seated flexion and vibration.
Chiropractic adjustments and non-thrust joint mobilization may improve mobility and reduce pain when the examination supports them. Guidelines report benefit from joint mobilization for many people with chronic low-back pain, including some with leg symptoms (George et al., 2021). Care should pair manual treatment with rehabilitation so improved motion becomes usable strength.
The Functional Target
The patient gains something measurable: easier standing, smoother walking, less guarded bending, better sleep positions, safer transitions from a delivery van, and more confidence handling daily tasks. Those functional gains matter more than trying to make every spinal image look “perfect.”
Step Two: Use Non-Surgical Decompression Carefully
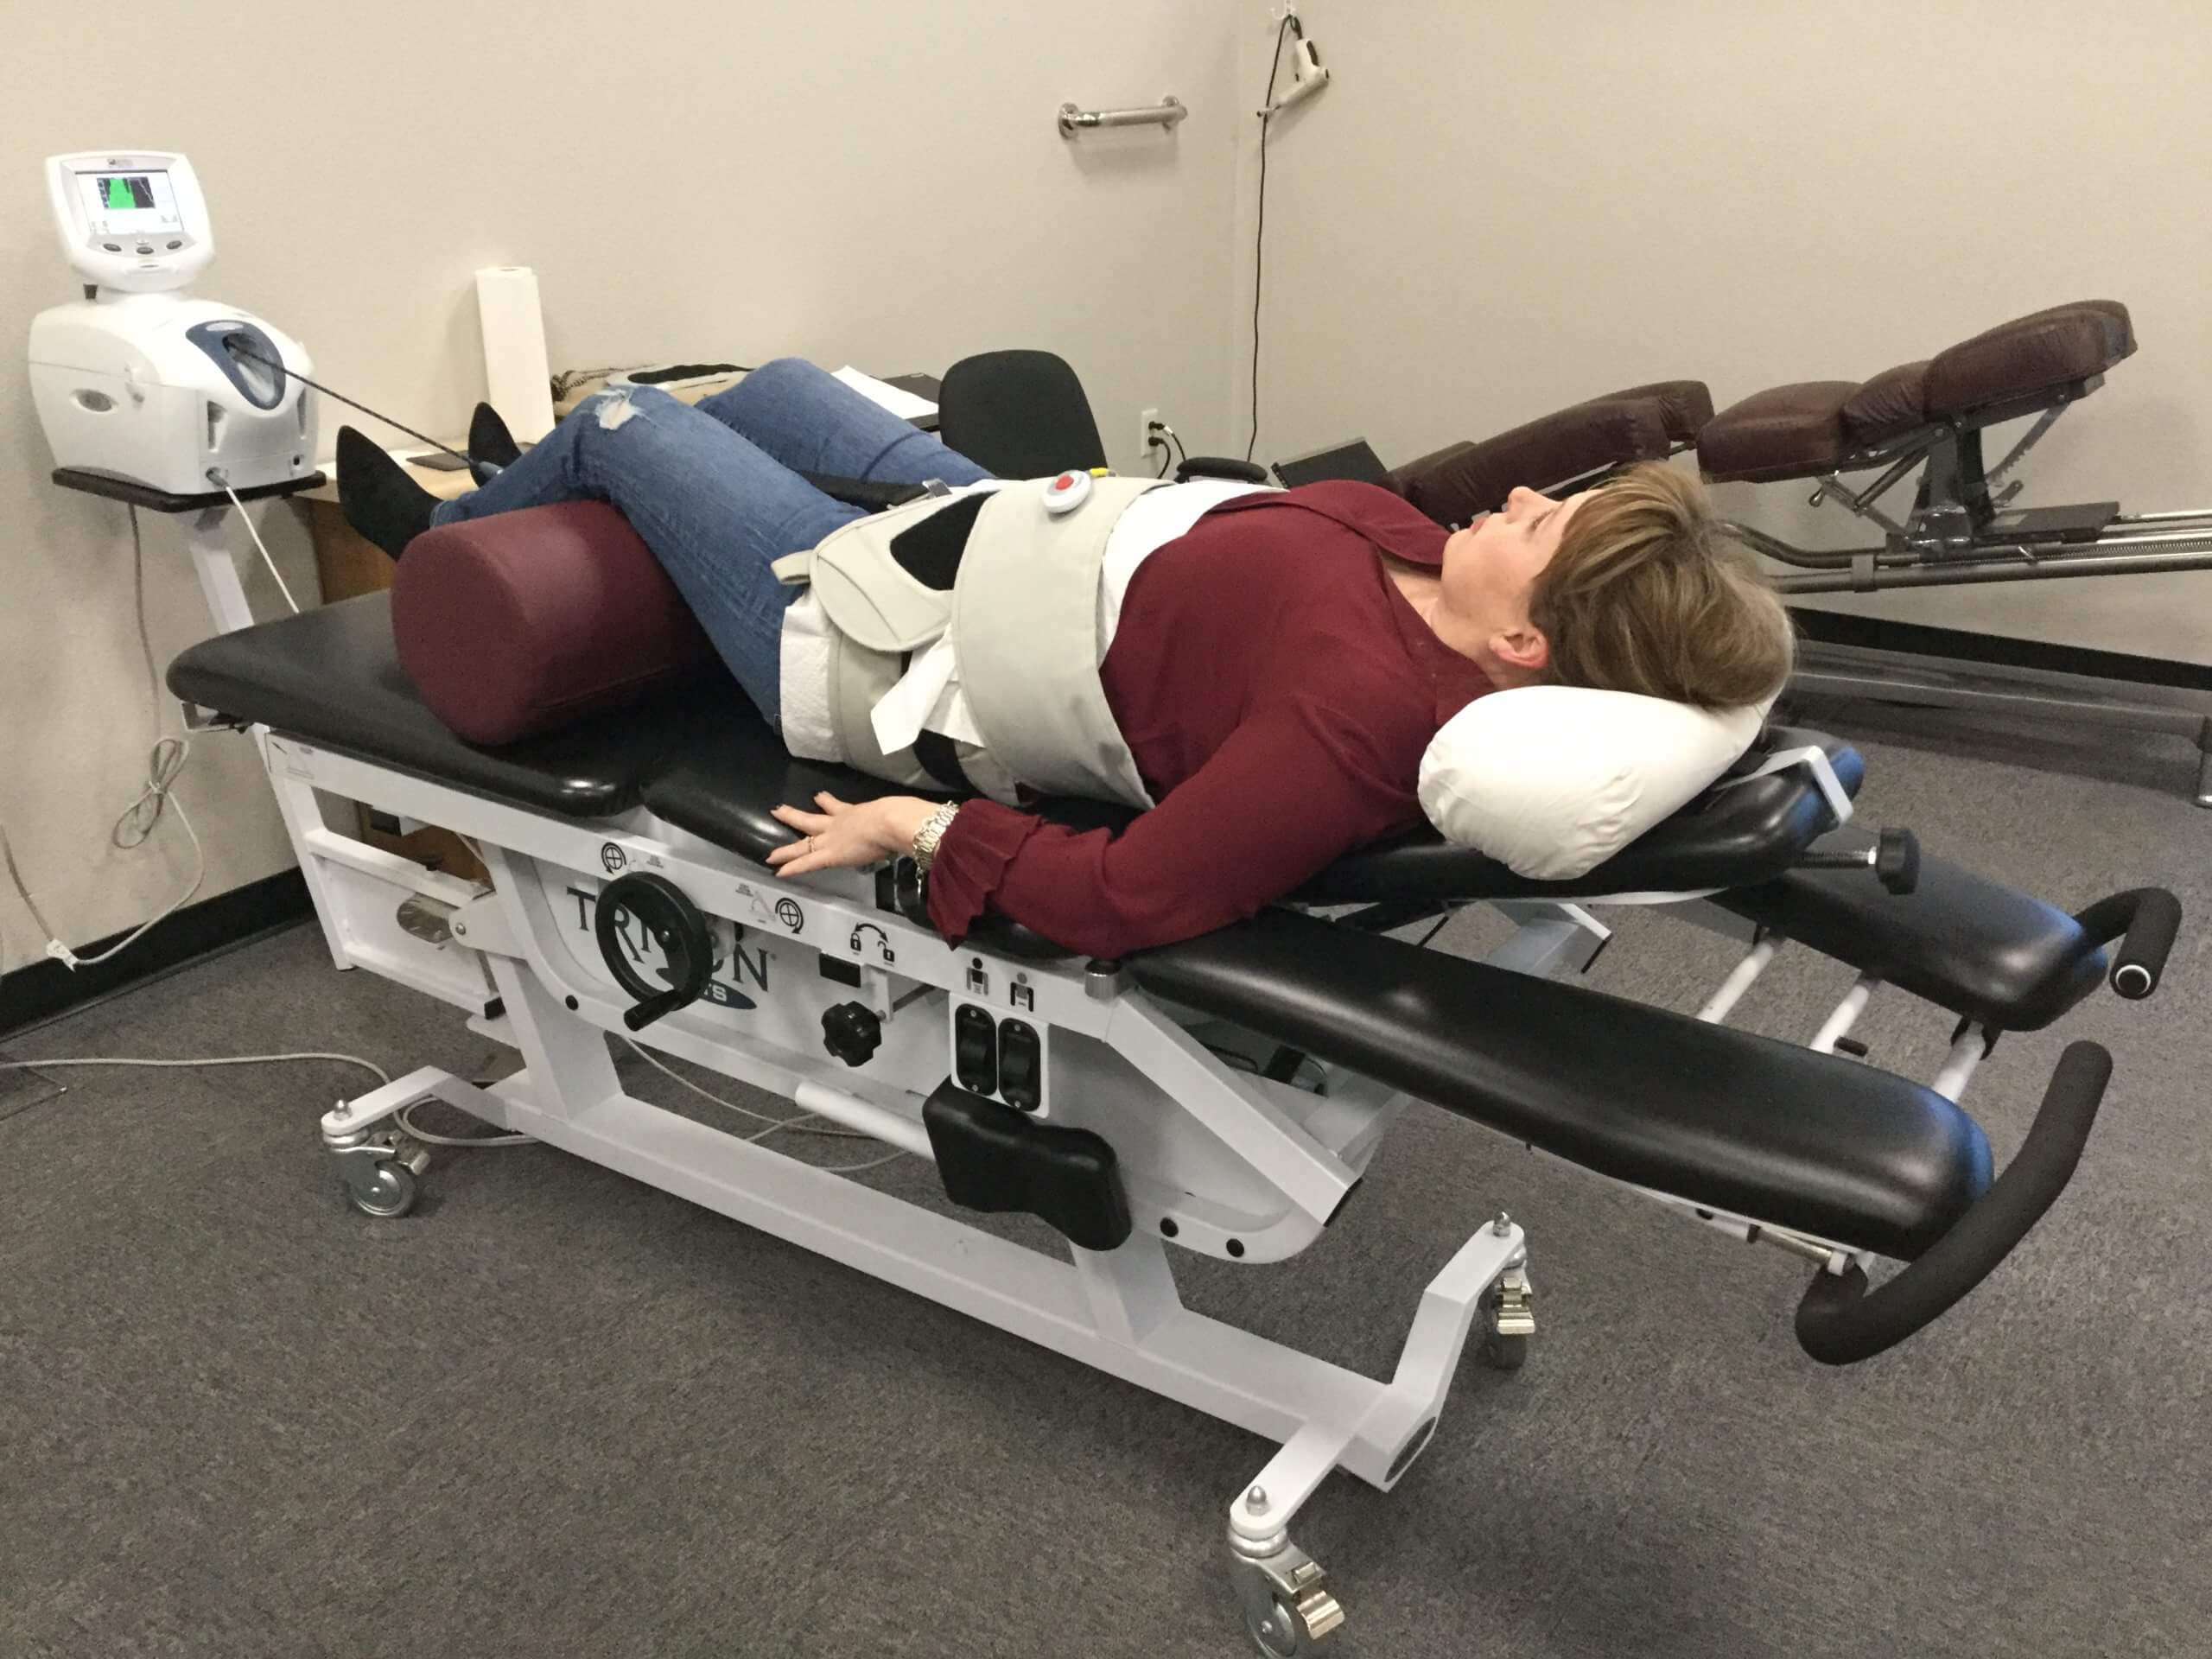
Non-surgical spinal decompression is commonly described as controlled lumbar traction or unloading. The practical aim is to reduce mechanical stress temporarily and create a position in which painful tissues or irritated nerve roots may become less sensitive.
The evidence requires precision. A systematic review found short-term improvements in pain and disability when certain mechanical traction forms were added to treatment for lumbar radiculopathy, but study quality and results varied (Vanti et al., 2021). WHO guidance for chronic primary low-back pain advises against routine traction for most patients, so decompression should not become an automatic protocol for every painful back (World Health Organization, 2023).
For a selected patient, decompression may be one tool within movement retraining, strengthening, work modification, and medical evaluation. It should never be sold as a guaranteed way to “reinflate” a disc or permanently reverse degeneration.
Preventing Unnecessary Surgery Without Delaying Necessary Surgery
Avoiding surgery is valuable when recovery is safe with conservative care. Lumbar discectomy can be appropriate for selected patients, yet it still carries risks such as recurrent herniation, wound complications, dural tears, reoperation, and neurologic complications (Bombieri et al., 2022).
The safer message is not “never have surgery.” It is “earn the decision with the right evaluation.” Recent spine recommendations support surgery when conservative treatment fails and emphasize urgent or early surgery for cauda equina syndrome or progressive severe neurologic deficits (Costa et al., 2024).
Seek urgent assessment for new bowel or bladder dysfunction, saddle-region numbness, rapidly worsening leg weakness, or serious neurologic changes. Fever, major trauma, unexplained weight loss, or concern for infection, fracture, or cancer also deserves prompt review.
This is non-maleficence in practice: use the least invasive reasonable option when it is safe, but never let a desire to avoid surgery delay care for a true emergency.
Step Three: Set Proactive Lifting Limits
For Amazon associates, prevention must survive the workday. “Lift with your legs” is not enough.
Use these rules:
Bring the package close before standing up.
Turn with the feet instead of twisting under load.
Reduce load size when the object starts low, high, or far away.
Use team lifting or mechanical assistance for demanding or awkward items.
Break up repeated lifting when possible with task rotation or brief recovery periods.
Stop treating pain as a test of toughness; a changing neurologic symptom deserves evaluation.
The Revised NIOSH Lifting Equation is useful because it does not assume every worker should lift the same weight in every position. It calculates a recommended weight limit using task conditions and a lifting index that reflects physical demand. NIOSH recommends keeping the lifting index or composite lifting index at or below 1.0 when evaluating two-handed lifting tasks (NIOSH, 2024).
Integrated Oversight: Structure, Medicine, and Patient Choice
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural alignment, mechanical rehabilitation, and advanced medical diagnostics. He holds Texas Advanced Practice Nursing License #1191402, Prescriptive Authority #59628, and NPI #1205907805. His dual licensure lets the clinic coordinate musculoskeletal examination with broader medical assessment and appropriate advanced interventions.
Dr. Maria Guadalupe Cardenas, MD, is Board Certified in Internal Medicine, has more than 40 years of experience, and holds Texas Medical License #J2933 and NPI #1164426748. As Medical Director, Clinical Director, and Collaborative Physician at Injury Medical Clinic PA in El Paso, she provides internal medicine oversight, risk stratification, interpretation of indicated laboratory tests, and comorbidity coordination.
That collaboration supports beneficence: the plan centers on the patient’s best functional outcome. It supports non-maleficence by screening for medical risks before aggressive treatment and using non-invasive, drug-sparing options when appropriate. It also protects autonomy. Patients are taught what the examination shows, what each option can and cannot reasonably do, and when another specialist or their existing medical team should be involved.
A Better Goal Than “Toughing It Out”
Severe lumbago after warehouse or delivery work is not a character test. The goal is to interrupt the overload cycle before pain, guarding, deconditioning, and poor mechanics reinforce one another.
A conservative plan can include targeted joint care, selected decompression, progressive trunk and hip rehabilitation, work-specific lifting education, and medical oversight. The target is direct: more comfortable movement, safer lifting, better sleep, and the ability to work without organizing each day around the next flare.
Multidisciplinary Call to Action
If repeated bending, sorting, driving, or lifting causes severe low-back pain, start with a coordinated evaluation. El Paso Back Clinic can assess mechanical function, neurologic findings, lifting demands, and medical risks, then explain conservative options and when to refer. Bring your imaging, medication list, job demands, and questions. The final decision remains yours, supported by clear information and coordinated chiropractic and medical care.
Severe Low Back Pain in Amazon Fulfillment Workers: Epidural Injections, Spinal Decompression, and the Treatment Window
Abstract: Severe low back pain can turn a 10-hour fulfillment shift into a battle. Repeated low-bin reaching, standing, twisting, and handling can keep an irritated lumbar nerve from settling. This article explains a function-first strategy: “turn down the fire, then address the load.” When true lumbar radiculopathy is present, an appropriately selected epidural injection may reduce acute nerve inflammation enough to create a treatment window for nonsurgical spinal decompression, mechanical chiropractic care, rehabilitation, and safer work habits. The goal is not temporary numbness. It is restoring movement while addressing the forces that keep symptoms returning.
A picker starts the shift moving quickly: scan, reach, bend, pull, pivot, walk, repeat. By hour seven, a familiar ache becomes sharper. By hour ten, standing upright hurts, the leg may burn, and getting into the car feels harder than moving another tote.
NIOSH identifies heavy physical work, lifting, forceful movement, bending, twisting, and static postures as recognized risk factors for low-back musculoskeletal disorders (National Institute for Occupational Safety and Health [NIOSH], 2024). For fulfillment workers, the problem is cumulative exposure. Low bins encourage trunk flexion, rushed reaches add rotation, and long hours on concrete floors magnify fatigue. Once pain changes how you move, compensation can load the hips, pelvis, and opposite side of the back.
The Key Question: Is the Fire in the Back or the Nerve?
Not every severe backache needs an injection. The first step is to identify what is irritated.
Localized lumbar pain may come from muscles, joints, discs, or other structures. Radicular pain is different. It can occur when a lumbar nerve root becomes irritated or compressed and may produce:
Burning or electric pain into the buttock or leg
Numbness or tingling
Pain that travels below the knee
Weakness in the foot or leg
Symptoms that worsen with certain spinal positions, coughing, or straining
A careful examination should assess strength, reflexes, sensation, movement tolerance, nerve tension, gait, and symptom patterns. Imaging may be appropriate when findings suggest significant disc injury, persistent neurologic symptoms, trauma, or when results would change treatment.
New loss of bowel or bladder control, saddle numbness, rapidly worsening weakness, fever with severe back pain, or major trauma requires urgent medical evaluation. These symptoms are not ones you can just “work through.”
Turn Down the Fire, Then Fix the Load
Think of an irritated lumbar nerve like a fire alarm beside a hot engine. If inflammation is high enough, even small movements can trigger intense pain. The worker may stop bending normally, brace every step, sleep poorly, and avoid rehabilitation because almost everything hurts.
That is where the treatment-window concept matters.
For appropriately selected lumbar radiculopathy, an epidural corticosteroid injection can place anti-inflammatory medication near the affected nerve root. A 2025 American Academy of Neurology review found that epidural steroid injections probably reduce short-term pain and disability in radiculopathy, while long-term pain benefit remains uncertain (Armon et al., 2025).
In plain language: the injection is not rebuilding a disc or correcting lifting mechanics. It may turn down the inflammatory “fire” long enough to make useful movement possible.
That window matters when pain blocks progress. A worker who could not tolerate walking, traction, unloading, or stabilization may gain enough control to begin them.
What an Epidural Injection Can—and Cannot—Do
A properly indicated epidural may help:
Reduce acute radicular pain
Improve tolerance for walking and sleep
Make rehabilitation easier to participate in
Allow a graded return to mechanical treatment
Reduce reliance on passive coping alone
It does not guarantee permanent relief, prevent surgery in every case, or address occupational loading patterns on its own. The AAN review found insufficient evidence that epidural steroid injections reduce the eventual need for surgery (Armon et al., 2025).
There are also risks. The FDA notes rare but serious neurologic complications associated with epidural corticosteroid injections and states that corticosteroids are not FDA-approved specifically for epidural administration (U.S. Food and Drug Administration [FDA], 2014). That makes informed consent, patient selection, appropriate image guidance, and medical oversight essential.
Step Two: Use the Window for Nonsurgical Spinal Decompression
Once the fire is quieter, the next question is simple: what mechanical inputs can the spine tolerate now?
Here, “spinal decompression” means nonsurgical mechanical traction or distraction, not surgery. The goal is controlled lumbar unloading while monitoring symptoms and neurologic response.
Research on traction is encouraging for some lumbar disc herniation patients, but it is not one-size-fits-all. A 2025 systematic review found improvements across traction, exercise, and manipulation studies, while also reporting very high variability between protocols and patient groups (Thavarajasingam et al., 2025).
That is why decompression should be treated as a clinical tool, not a magic table.
During the treatment window, the clinician can look for useful signs:
Leg pain centralizes toward the back
Standing and walking tolerance improves
Numbness or tingling decreases
The patient can change positions with less guarding
Basic trunk and hip exercises become tolerable
If symptoms worsen, spread farther down the leg, or neurologic weakness progresses, reassess the plan.
Step Three: Fix the Load With Mechanical Chiropractic Care
Pain relief is valuable, but function is the finish line.
The picker or packer has to return to the same realities: low bins, repetitive handling, long walking routes, awkward reaches, and a clock that does not care whether the lumbar muscles are fatigued. Mechanical chiropractic care should therefore focus on restoring motion and controlling load, not simply chasing pain scores.
Care may include low-force mobilization, selected chiropractic adjustments, hip mobility, trunk endurance, graded lifting, nerve-mobility exercises, and conditioning. Aggressive manipulation is not automatically appropriate during a highly irritable radicular episode; treatment intensity should match neurologic findings and tolerance.
A useful return-to-function plan teaches the worker to:
Hinge through the hips instead of repeatedly rounding the lumbar spine
Bring the load closer before standing
Pivot with the feet instead of twisting while bent
Alternate positions when task design allows
Break large recovery goals into short movement exposures
Report progressive weakness or spreading numbness promptly
These habits support autonomy. The patient should understand what is being treated, why each step is being used, what alternatives exist, and what would change the plan.
Integrated Care: One Plan, Not Three Disconnected Treatments
Severe radicular pain often crosses professional lanes. That is where multidisciplinary care can improve coordination.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines Doctor of Chiropractic care with board-certified family nurse practitioner authority and advanced practice nursing. Under collaborative medical oversight, his scope includes image-guided epidural spinal injections, structural chiropractic care, mechanical rehabilitation, and functional medicine support.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in Internal Medicine, has more than 40 years of experience, and serves as Medical Director and collaborative physician at Injury Medical Clinic PA. Her role includes medical oversight, risk stratification, laboratory interpretation, and coordination of medical conditions that can affect recovery.
The benefit is sequence and communication: calm the nerve when indicated, restore tolerable motion, rebuild capacity, and coordinate with the patient’s existing medical team. That supports beneficence while respecting non-maleficence—using the least invasive reasonable options first when safe, without delaying surgical or emergency referral when neurologic findings demand it.
Your Treatment Window Should Lead Somewhere
An epidural injection should not become permission to ignore the same loading pattern until the pain returns. The window is valuable because it creates opportunity.
Use it to walk more normally.
Use it to sleep.
Use it to tolerate decompression or rehabilitation.
Use it to relearn bending, lifting, and bracing strategies.
Use it to build enough capacity that the next 10-hour shift is not simply another flare waiting to happen.
For an Amazon fulfillment worker with severe low back pain and leg symptoms, the goal is not to choose between “an injection” and “chiropractic.” The better question is whether each tool fits the diagnosis and timing.
Turn down the fire. Then fix the load.
If severe back pain, sciatica, numbness, or weakness is limiting your work or daily function, schedule a multidisciplinary evaluation at El Paso Back Clinic. A coordinated DC/APRN/FNP-BC and MD-guided plan can help determine whether you need urgent referral, an epidural treatment window, nonsurgical decompression, mechanical rehabilitation, or a different path entirely. You remain the informed decision-maker at every step.
Server Rack to Desk Chair: Why Data Center and IT Work Can Trigger Chronic Low-Back Pain—and What You Can Do About It
A shift can change quickly. For one hour, you sit and answer tickets. The next, you are standing on a server-room floor, crouching behind a rack, reaching for cables, or lifting hardware. By day’s end, your low back may feel tight, tired, or familiar.
For El Paso’s IT professionals, data center technicians, and network teams, recurring low-back pain rarely comes down to one “bad posture.” Sitting, standing, bending, twisting, and lifting can contribute to symptoms, but no single exposure consistently explains every case (Swain et al., 2020). The better question is which combined loads, habits, and recovery limits keep your back irritated.
Why Tech Work Can Become a Mechanical Load Problem
Your lumbar spine is built to move and carry load. Problems can appear when tissues face more stress than they comfortably recover from.
Long desk sessions reduce movement variety. Prolonged standing can also become uncomfortable; substantial occupational standing has been associated with more low-back symptoms, though it has not been proven that standing itself causes pain (Coenen et al., 2018). Add crouching, cable work, twisting, and equipment lifting, and the demand changes again.
The goal is not to fear movement. It is to improve how well your body handles it.
Sitting, Hip Stiffness, and the “Locked Up” Feeling
After hours seated, many workers stand feeling stiff through the hips and lower back. It is tempting to blame “tight hip flexors,” but low-back pain is more complex than one muscle group.
Limited hip motion can change how you bend, squat, or reach. The lumbar region may then take on more motion during some tasks. Hip mobility, trunk control, and movement variety can therefore be reasonable rehabilitation targets without claiming that tight hips automatically cause back pain.
Standing on Concrete Is Not Automatically Better Than Sitting
A standing desk may help, but standing all day is not a cure. Technical workspaces may require long periods on firm surfaces while monitoring equipment.
Variation is usually practical: sit, stand, walk, change foot position, and move when the job permits. NIOSH identifies static posture, heavy physical work, lifting, bending, and twisting among contributors to work-related musculoskeletal stress (National Institute for Occupational Safety and Health [NIOSH], 2024a).
Think “best next position,” not “perfect position.”
Crouching, Cable Work, and Rack-Side Repetition
Working behind equipment can place you in deep hip flexion, kneeling, squatting, rotation, or sustained forward bending. None is inherently dangerous. Trouble may develop when exposure is prolonged, repeated, heavily loaded, or performed while fatigued.
Bring tools closer. Raise work when possible. Use a kneeling pad or stable support when appropriate. Alternate sides instead of always rotating one way. Brief movement breaks can reduce unnecessary repetition.
Lifting Hardware: Control the Load, Not Just Your Back
Servers, batteries, monitors, and UPS components can be awkward or hard to grip. Safe lifting is not simply “keep your back straight.” Weight, distance, height, twisting, frequency, grip, and repetition matter. The Revised NIOSH Lifting Equation estimates physical stress from two-handed lifts and supports safer job design (NIOSH, 2024b).
Get close to the load, use a stable stance, avoid rushed twisting, and use team lifts or assistance when appropriate. Lifting limits should reflect the task and your current capacity.
What a Structural Assessment Should Actually Look For
Recurring low-back pain deserves more than a quick label.
At El Paso Back Clinic, a mechanical assessment can consider spinal and pelvic motion, painful patterns, hip mobility, trunk endurance, lifting mechanics, neurological findings, and positions that change symptoms. The goal is not to claim every painful back is “out of alignment,” but to identify modifiable findings and whether conservative care is appropriate.
Imaging is not necessary for every episode. History and examination help determine when testing may be appropriate. New bowel or bladder problems, saddle numbness, progressive leg weakness, major trauma, fever, or systemic symptoms require prompt medical evaluation.
Mechanical Rehabilitation: Build Capacity for Your Real Job
Rehabilitation should prepare you for work, not only help you feel better on a treatment table. Clinical guidelines support exercise and selected manual therapies for many people with acute or chronic low-back pain (George et al., 2021).
For an IT professional, rehabilitation might include hip mobility, trunk endurance, hinging, graded lifting, strength, walking tolerance, and desk-position changes. A data center technician may also need loaded carries, squat tolerance, kneeling transitions, reaching, and controlled rotation.
The plan should progress with your response. Some people need mobility; others need strength, endurance, or confidence with painful movements. Patient autonomy matters: you should understand what is tested, why treatment is suggested, alternatives, and how progress will be measured.
Where Chiropractic Care and Decompression Fit
Chiropractic care may be one part of conservative treatment when examination indicates manual care is appropriate. Guidelines include spinal manipulation among options that may help some people with chronic low-back pain, especially when paired with active care rather than used alone (World Health Organization [WHO], 2023).
“Decompression” requires careful thinking. WHO does not recommend routine traction for chronic primary low-back pain because the supporting evidence is uncertain (WHO, 2023). Decompression should not be sold as a guaranteed disc fix or universal answer.
If decompression is considered, it should follow examination, fit the symptom pattern, have clear goals, and be reassessed. Beneficence means choosing care for your clinical needs—not applying the same protocol to everyone.
Integrated Care When Back Pain Is More Than Mechanical
Persistent pain can be influenced by sleep, stress, metabolic health, medication use, recovery, and other medical factors. An integrated team can help when those issues matter.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care, mechanical rehabilitation, and functional medical assessment. Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, provides medical direction and oversight for complex medical or metabolic concerns and clinically appropriate laboratory evaluation.
Collaboration does not remove your voice. You remain the informed decision-maker.
A Better Back Strategy for El Paso Tech Workers
Whether your day moves from an El Paso desk to a server room, network closet, help-desk station, or equipment floor, your back needs more than perfect posture. It needs movement variety, smart load management, recovery, and enough strength for the work.
Start with small changes: interrupt long sitting, vary standing, improve workstation reach, keep loads close, plan awkward lifts, and build capacity gradually. If pain keeps returning, limits work, radiates into the leg, or changes how you move, seek a qualified evaluation.
At El Paso Back Clinic, our goal is to identify changeable drivers, explain your options clearly, and coordinate structural chiropractic care, mechanical rehabilitation, and medical oversight when indicated. We build the safest plan around your findings, goals, and informed choices. That approach supports safer movement, stronger function, and more confident workdays ahead.
References
Coenen, P., Willenberg, L., Parry, S., Shi, J. W., Romero, L., Blackwood, D. M., Maher, C. G., Healy, G. N., Dunstan, D. W., & Straker, L. M. (2018). Associations of occupational standing with musculoskeletal symptoms: A systematic review with meta-analysis. British Journal of Sports Medicine, 52(3), 176–183. https://doi.org/10.1136/bjsports-2016-096795
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. https://doi.org/10.2519/jospt.2021.0304
Swain, C. T. V., Pan, F., Owen, P. J., Schmidt, H., & Belavy, D. L. (2020). No consensus on causality of spine postures or physical exposure and low back pain: A systematic review of systematic reviews. Journal of Biomechanics, 102, 109312. https://doi.org/10.1016/j.jbiomech.2019.08.006
World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. World Health Organization. https://www.who.int/publications/i/item/9789240081789
Unlocking Relief: A Closer Look at Occipital Nerve Blocks for Head and Neck Pain
Abstract
This educational guide offers an in-depth, first-person look at managing head and neck pain, focusing on conditions like occipital neuralgia and cervicogenic headaches. I will walk you through the diagnostic process. Additionally, I explain how occipital nerve block injections help diagnose and treat this type of debilitating pain.
We will explore the underlying anatomy and physiology, detailing how irritation of the occipital nerves can lead to widespread symptoms. This post explains the rationale behind using a combination of a local anesthetic (lidocaine) and a corticosteroid (cortisone) to provide immediate relief. It also shows how this combination helps reduce inflammation over the long term.
We will also discuss how this intervention is a crucial part of our integrative care model at Injury Medical Clinic. This model combines medical oversight from Dr. Maria Guadalupe Cardenas, MD, with chiropractic care, functional medicine, and comprehensive rehabilitation. Together, these approaches address the root causes of pain, restore function, and promote lasting wellness.
By the end of this article, you will understand how we diagnose, treat, and holistically manage complex head and neck pain syndromes.
The Journey to Diagnosing Complex Head and Neck Pain
Hello, I’m Dr. Alex Jimenez. At our clinic, we frequently see patients who have been suffering from persistent, often debilitating, head and neck pain for months or even years. They come to us describing symptoms that can range from a dull, constant ache at the base of their skull to sharp, shooting, or electrical-shock-like sensations. These sensations may travel up the back of their head. Sometimes they even reach behind their eyes. These symptoms are characteristic of occipital neuralgia.
Occipital neuralgia occurs when the greater or lesser occipital nerves, which emerge from the upper cervical spine (neck) and run up through the scalp, become inflamed or irritated. This irritation can be caused by various factors, including:
Muscle Tension and Spasms: Chronic tension in the suboccipital muscles at the base of the skull is a primary culprit. These muscles can tighten from poor posture (like “text neck”), stress, or previous injury, compressing the nerves that pass through them.
Trauma: Injuries such as whiplash from a car accident can directly damage these nerves or cause inflammation and muscle guarding that entraps them.
Spinal Misalignments: Structural issues in the cervical spine, particularly the upper vertebrae (C1/Atlas and C2/Axis), can impinge on the nerve roots that form the occipital nerves.
Degenerative Changes: Conditions like osteoarthritis in the cervical spine can lead to bone spurs that narrow the spaces through which the nerves travel.
The journey to an accurate diagnosis begins with a thorough history and a detailed physical examination. For a patient presenting with these symptoms, I focus my evaluation on the suboccipital region. This area is located at the junction where the neck meets the skull. My goal is to reproduce the patient’s familiar pain through careful palpation.
Pinpointing the Source: A Hands-On Approach
In a recent case, I was working with a patient who had been experiencing significant posterior head pain. As I gently but firmly applied pressure to specific points along the occipital ridge, I asked for feedback. “Is that hurting right there?” I inquired. The patient’s immediate, affirmative response—”That’s it”—is a crucial diagnostic clue. This process, known as provocative testing, helps us confirm that the occipital nerves are indeed the source of the pain.
Once I identify the point of maximum tenderness, I need to mark it for the next step. This can be tricky, especially in the hairline, where traditional ink marks can be hard to see. To ensure precision, I use a two-step method. First, I use the tip of a capped ballpoint pen to create a small, temporary indentation in the skin directly over the tender spot. This provides me with a tactile landmark. Then, just below it, I place a small ink mark as a visual guide. I repeat this process to identify a second tender spot, as multiple points along the nerve’s path are often irritated.
The Occipital Nerve Block: A Targeted Intervention
After identifying and marking the precise locations of nerve irritation, the next step is to perform an occipital nerve block. This procedure serves a dual purpose: diagnostic and therapeutic.
Diagnostic Purpose: If injecting a local anesthetic provides immediate and significant pain relief, it confirms our diagnosis that the occipital nerve is the primary pain generator.
Therapeutic Purpose: The injection delivers medication directly to the site of inflammation, providing both short-term and potentially long-term relief.
Preparing for the Procedure
Before any injection, patient safety and comfort are paramount. I begin by thoroughly cleaning the marked areas with alcohol swabs to minimize the risk of infection. While a stronger antiseptic like Betadine is often used for other procedures, its application in the hairline can be messy and less practical. Given the small needle size and the superficial nature of the injection, rigorous cleaning with alcohol is sufficient.
The medication I use is a carefully measured mixture of two key components:
Lidocaine: A fast-acting local anesthetic. Its primary role is to block the sodium channels in the nerve fibers. By preventing sodium ion influx, lidocaine stops the nerve from transmitting pain signals to the brain. This is why patients often experience relief within minutes of the injection. The immediate feedback is invaluable—if the pain disappears, we know we’ve targeted the right spot.
Cortisone: This is a type of corticosteroid, a powerful anti-inflammatory agent. While lidocaine provides immediate relief, its effects are temporary. The cortisone addresses the underlying physiological problem: inflammation. It works at a cellular level to suppress the inflammatory cascade, reducing swelling, irritation, and pressure on the nerve. The therapeutic effects of cortisone develop over the coming days and can provide relief for several weeks or even months.
For this procedure, I use a thin, 1-inch, 25-gauge needle to minimize discomfort. In many cases, I would use a topical freeze spray (ethyl chloride) to numb the skin before the injection. However, in the scalp and hairline, the spray can run down into the patient’s face, eyes, or ears, which is uncomfortable and potentially hazardous. So I proceed without it. Instead, I rely on a quick, precise technique. I always communicate this to the patient: “You’re going to feel a little bit of a stick here. Is that all right?” Informed consent and clear communication help alleviate patient anxiety.
The Injection Technique: Precision and Safety
With the patient ready, I locate the first marked spot. I brace my hand and, on a count of three, gently insert the needle. The goal is to advance the needle until I feel it make contact with the surface of the occipital bone. This provides a safe and solid backstop, ensuring I don’t inject too deeply.
Before injecting the medication, I perform a critical safety assessment called aspiration. I gently pull back on the syringe plunger to see if any blood enters the syringe. If it does, the needle tip is in a blood vessel. Injecting the medication, especially the corticosteroid, directly into the bloodstream can cause systemic side effects and would not be effective locally. Seeing “nothing on aspiration” confirms the needle is in the correct tissue plane—the perineural space around the nerve.
Satisfied with the needle’s position, I slowly inject half of the medication from the syringe, bathing the inflamed nerve and surrounding tissues. I then withdraw the needle. Next, I repeat the exact same process at the second marked location, injecting the remaining half of the mixture.
Immediate Feedback and Post-Procedure Care
Immediately after the injections, I gently massage the areas. This helps spread the medication throughout the suboccipital tissues. This helps ensure the medication reaches all irritated nerve branches. This also helps alleviate some of the initial post-injection soreness.
The final and most rewarding step is to re-evaluate the patient’s pain. I apply firm pressure to the same spots that were excruciatingly tender just moments before. “Does that hurt right there?” I asked the patient. Their response changed from a pained wince to a simple “Pressure.” When I asked if it was better, they replied, “Feels better.” We checked the second spot, which had also improved significantly.
This immediate pain reduction confirms the block’s success. The lidocaine is already at work, silencing the overactive pain signals. The patient leaves the room with hope and immediate relief, while the cortisone begins its slower, more sustained work of healing the inflammation.
The Power of Integrative Care: Beyond the Injection
An occipital nerve block is a powerful tool, but it is rarely a standalone cure. At Injury Medical Clinic, we view it as one critical piece of a much larger, comprehensive puzzle. As a Family Nurse Practitioner (APRN, FNP-BC), I am qualified to perform these procedures. In addition, my foundation as a Doctor of Chiropractic (DC) and my advanced certifications in Functional Medicine (CFMP, IFMCP) provide the framework for a truly holistic approach. This is all done under the medical direction and collaboration of our esteemed internist, Dr. Maria Guadalupe Cardenas, MD. Her decades of experience provide invaluable medical oversight.
Our philosophy is that true healing requires addressing the root cause, not just masking the symptoms. The nerve block provides a crucial window of opportunity. By significantly reducing the patient’s pain, it allows us to implement other therapies effectively. These are treatments that were previously too painful to perform.
Integrating Chiropractic and Rehabilitation
This is where my expertise as a chiropractor becomes essential. With the patient’s pain under control, I can begin to address the underlying biomechanical dysfunctions. Our integrated approach includes:
Chiropractic Adjustments: Gentle, precise adjustments to the cervical spine, particularly the C1 and C2 vertebrae, can relieve mechanical pressure on the nerve roots and improve overall spinal alignment. This restores proper motion and reduces the structural stress that may have been compressing the occipital nerves.
Myofascial Release and Soft Tissue Therapy: The nerve block calms the nerve, but it doesn’t release the chronically tight muscles that are strangling it. I use advanced soft tissue techniques to break down adhesions and trigger points in the suboccipital, trapezius, and other neck muscles. This improves blood flow, reduces muscular tension, and creates more space for the nerve to function without compression.
Corrective Exercises and Rehabilitation: We provide a personalized rehabilitation program. This includes specific stretches to maintain flexibility in the neck and shoulders, along with strengthening exercises to improve postural endurance. The goal is to correct poor postural habits (like forward head posture) that often contribute to occipital neuralgia and prevent recurrence.
By combining the immediate relief of the medical injection with the long-term structural correction of chiropractic care and rehabilitation, we create a synergistic effect. The injection breaks the pain-inflammation cycle. Moreover, rehabilitative therapies address the underlying cause, supporting sustainable recovery. This multidisciplinary model—where medical, chiropractic, and functional medicine professionals work hand in hand—is the future of effective pain management and injury care.
References
Choi, H. J., & Oh, I. H. (2021). The effect of greater occipital nerve block on pulseless disease (Takayasu arteritis) with occipital neuralgia. The Korean Journal of Pain, 34(1), 126–129. https://doi.org/10.3344/kjp.2021.34.1.126
Dach, F., & Eckeli, A. L. (2021). Occipital nerve block for cervicogenic headache: A systematic review. Cephalalgia: An International Journal of Headache, 41(14), 1476–1489. https://doi.org/10.1177/03331024211027464
Naja, Z. M., El-Rajab, M. A., Al-Tannir, M. A., Faysal, W. M., & Ziade, F. M. (2006). Occipital nerve blockade for cervicogenic headache: A double-blind, randomized, controlled clinical trial. Pain Practice, 6(2), 89–95. https://doi.org/10.1111/j.1533-2500.2006.00068.x
A concussion or whiplash injury can do more than strain the neck. It can interrupt the three-way loop among the gut, the brain, and the spine. When that loop breaks, inflammation rises, digestion changes, and healing slows. This article explains the gut-brain-spine connection in plain language. It then covers protein-forward meals, supplement advice, lifestyle changes, integrative chiropractic care, and regenerative therapies that support neuro-recovery. You will also see how Injury Medical Clinic PA in El Paso combines chiropractic care, functional medicine, and medical direction to treat root causes rather than symptoms alone.
A Trilateral Network That Works as One Loop
The gut-brain-spine connection is a trilateral communication network in functional medicine and integrative chiropractic therapy. Disruption in one region can cause dysfunction in the others. The gut and brain talk through nerves, immune signals, hormones, and the microbes that live in the digestive tract. The main nerve highway is the vagus nerve. It runs from the brainstem, through the neck, and down to the organs of digestion. The gut also has its own large nerve network, often called a “second brain.” Gut microbes help make chemical messengers that affect mood, sleep, and pain.
The spine physically supports this conversation. Nerves leaving the neck and mid-back carry rest-and-digest signals and fight-or-flight signals to the gut. When cervical joints move well, those signals travel more clearly. When joints lock after an injury, the message becomes noisy. That is why a neck problem can show up as nausea or bloating, and why gut inflammation can keep neck muscles tight.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, has described this as a loop rather than a one-way path. Clinical observation in his El Paso practice supports that view: leaky-gut inflammation can signal the brain, and brain or trauma stress can worsen gut-barrier function. Patients typically arrive with more than just a neck or a stomach. They arrive with a cluster.
How Head and Neck Injury Breaks the Cycle
This complete cycle is broken whenever damage to the head or neck happens, like a whiplash or concussion. After a concussion or mild traumatic brain injury, the gut lining can become more permeable. Bacteria can shift. Whole-body inflammation can rise. Those changes may add to brain fog, headaches, low mood, and poor sleep.
Whiplash adds a mechanical problem. A fast stretch of neck ligaments, joints, and muscles can irritate pathways that travel with the vagus nerve and the sympathetic chain. The result is often a mix of stiffness, dizziness, gut upset, and a nervous system that will not settle.
The injured brain also uses more energy to repair membranes and restore chemical balance. If food intake drops, protein is low, or the gut cannot absorb nutrients well, healing stalls. Functional nutrition speeds healing by restoring the intestinal barrier, systematically reducing systemic inflammation, and supplying the nutrients needed for structural and neurological repair.
Protein-Forward Nutrition for Neuro-Recovery
Protein is the building material for tissue, enzymes, and many brain chemicals. After a head or neck injury, calorie and protein needs often rise. Research on early mild traumatic brain injury has linked meeting calorie and protein needs with better recovery markers.
A practical rule is simple: include a protein source at every meal and snack. Do not save all protein for dinner.
Helpful protein-forward choices include:
Eggs, which also provide choline for nerve-signal chemicals
Fatty fish such as salmon, sardines, and mackerel
Poultry or lean red meat in modest portions
Greek yogurt or cottage cheese if dairy is tolerated
Beans, lentils, and chickpeas
Nuts and seeds, especially walnuts and pumpkin seeds
Pair protein with colorful plants. Berries, leafy greens, peppers, and herbs bring antioxidants that help the body handle oxidative stress after impact. Add turmeric and ginger to meals for extra anti-inflammatory support.
Foods that often slow recovery include ultra-processed snacks, sugary drinks, and large amounts of refined starches. These can fuel inflammation and worsen blood-sugar swings. Many people feel fatigue, irritability, and more severe headaches.
A simple plate pattern works well:
Half the plate: vegetables and some fruit
One quarter: quality protein
One quarter: slow carbs such as oats, quinoa, potatoes, or beans
A source of healthy fat: olive oil, avocado, or fatty fish
Do not crash-diet during recovery. The injured nervous system needs steady fuel. From a nurse practitioner and functional medicine view, this is metabolic care: give the body enough amino acids and energy, so repair can happen.
Supplement Advice: Fill Gaps With Clinical Oversight
Food comes first. Supplements can help when labs, symptoms, or diet show a need. They should be chosen with a licensed clinician, especially after a brain or neck injury, and especially if you take blood thinners or have kidney, bleeding, or absorption issues.
Nutrients often discussed in concussion and neuro-recovery care include:
Omega-3 fats (DHA and EPA). These support cell membranes and help balance inflammation. The best food sources are fatty fish. Algal oil is an option for people who do not eat fish.
Magnesium. It supports nerve signaling, muscle relaxation, sleep, and headache control. Greens, seeds, nuts, and legumes are food sources.
Vitamin D. Low levels are common and may affect immune tone, mood, and recovery. Testing guides dosing.
Antioxidant patterns. Vitamin C, polyphenols from berries and cocoa, and curcumin from turmeric help the body handle oxidative stress.
Creatine. Some research looks at creatine for brain energy after injury. It is not for everyone and should be reviewed by a professional.
Gut-supportive tools. Fiber-rich plants, fermented foods if tolerated, and clinician-guided probiotics or other gut-repair nutrients may help restore the barrier and calm immune signaling.
A systematic review of nutritional care in early mild traumatic brain injury found that meeting calorie and protein needs, plus targeted supports such as omega-3s, vitamin D, and magnesium, was associated with better recovery markers in studied patients. That doesn’t mean everyone needs every product. It means nutrition is part of root-cause care.
Lifestyle Adjustments That Calm the Loop
Nutrition works best when daily habits support the same goals: less inflammation, better vagal tone, and enough time to repair.
Useful habits include:
Hydration. Spinal discs and the gut both need water. Pale-yellow urine is a simple check.
Sleep protection. The brain clears waste and rebuilds during sleep. Keep a dark, regular schedule as much as symptoms allow.
Vagus-friendly breathing. Slow nasal breathing and longer exhales can nudge the body out of fight-or-flight.
Gentle movement after clearance. Short walks and guided mobility beat long bed rest once a clinician says it is safe.
Stress-load reduction. Extra screens, arguments, and intense training can keep the sympathetic system switched on.
Alcohol limits. Alcohol adds inflammation and disrupts sleep and gut-barrier function.
These steps look simple. After a neck or head injury, they are often the difference between a nervous system that can repair and one that stays reactive. Lifestyle is not extra advice. It is metabolic and neurological first aid.
How Integrative Chiropractic Care Fits This Treatment
Integrative chiropractic care does not treat the gut by adjusting the abdomen as if it were a joint. It restores motion and neurological signaling through the spine, especially the neck, so the vagus nerve and spinal pathways can do their jobs.
Restricted cervical joints, muscle guarding, and forward-head posture after whiplash can keep the body in a braced, high-alert pattern. Care that improves joint motion and reduces mechanical irritation can support clearer brain-gut messaging.
In this framework, chiropractic care is one measured pillar:
Cervical and thoracic adjustments to improve motion and nerve signaling
Soft-tissue work to ease guarded neck and upper-back muscles
Posture and breathing drills that reduce forward-head strain
Rehab that rebuilds deep neck stability so tissues are not re-injured
Coordination with nutrition and medical care so structure and metabolism heal together
When the spine moves better, patients often tolerate food, sleep, and exercise more easily. That is the practical test of the triangle: less pain, clearer thinking, and a calmer gut, not just a better X-ray angle.
Dr. Jimenez’s clinical work links spinal care with functional nutrition because mechanics and metabolism travel together. A neck that cannot move well keeps the nervous system loud. A gut that stays inflamed keeps the neck loud. Treating only one side of that loop is incomplete care.
Regenerative and Interventional Therapies: Repair From Both Ends
Cutting-edge regenerative and interventional treatments can significantly speed healing when they are built into a chiropractic and functional medicine framework. They treat head and neck conditions such as whiplash and post-concussion syndrome by reducing systemic inflammation and physiologically mending damaged physical structures along the gut-brain-spine loop.
Common tools used in integrative injury care include:
Platelet-rich plasma (PRP). A concentrated portion of the patient’s own blood may be injected into injured neck ligaments, muscles, or joints. Growth factors can support collagen repair and quieter inflammation. PRP has been used in whiplash protocols to help mobility return so rehab can progress.
Platelet products and related injections. Case-series work on cervical pain using platelet products and prolotherapy has reported meaningful drops in pain and function scores when the whole functional spinal unit is addressed, not only one spot.
Microfragmented adipose tissue (MFAT) and related orthobiologics. These may be considered for more complex soft-tissue or joint problems when appropriate and within scope.
Laser and shockwave therapies. These are often layered with PRP or chiropractic care to increase local circulation and comfort.
IV nutrient therapy. When gut absorption is poor, or intake is low, IV vitamins, minerals, amino acids, and fluids can support cellular repair while the oral diet is rebuilt.
These therapies work best as part of a plan, not as stand-alone shots. Regenerative injections can signal repair in tissues with poor blood flow. Chiropractic care and rehab restore motion and load sharing. Nutrition lowers the inflammatory background that would otherwise keep tissues angry. That is how the loop is treated from both ends: structure and chemistry.
A Multidisciplinary Team in El Paso
Injury recovery is safer when chiropractic skill and medical oversight work together. At Injury Medical Clinic PA in El Paso, Texas, Dr. Alex Jimenez, DC, provides chiropractic, functional medicine, personal injury, and rehabilitative care. Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), has over 40 years of experience as an internist and works with Dr. Jimenez as the medical director and collaborative physician.
This multidisciplinary setup is common in integrative or injury care clinics, where an MD provides medical direction alongside a chiropractor. The team integrates:
Chiropractic care for spinal motion, nerve signaling, and soft-tissue function
Medical oversight in internal medicine for safety, labs, and collaborative decisions
Functional medicine for lifestyle, metabolic health, and root-cause resolution
Personal injury care and documentation
Rehabilitation to rebuild strength, balance, and daily function
Related services such as regenerative procedures and nutrient support when appropriate
Root-cause care means asking why headaches, nausea, neck stiffness, and poor sleep arrive as a cluster. It also means not forcing a single tool—an adjustment, a supplement, or an injection—to do the work of the whole system.
A Clear Path Forward
A practical plan after head or neck injury often looks like this:
Get a proper exam. Rule out red flags. Document the injury.
Protect sleep, hydration, and protein intake in the first days.
Use an anti-inflammatory, protein-forward plate and limit ultra-processed foods.
Restore cervical motion and vagal tone with guided chiropractic and rehab.
Add targeted nutrients only when they match labs, diet, and medical history.
Consider regenerative options when ligaments, facets, or delayed healing are holding recovery back.
Recheck function: neck motion, headache load, gut comfort, energy, and thinking clarity.
Healing isn’t just “wait until the neck stops hurting.” It is restoring the conversation among gut, brain, and spine so the body can finish the job it started after the injury.
If symptoms are severe, worsening, or include vomiting, confusion, weakness, or new neurological changes, seek urgent medical care first. Nutrition and integrative therapies support recovery. They do not replace emergency evaluation.
From Emergency Discharge to Measurable Recovery: How Integrative Care Breaks the Wait-and-See Loop
Abstract
Conventional personal injury treatment often sends accident victims home from the emergency department with muscle relaxers and NSAIDs. Those medicines can hide immediate discomfort. They do little to repair joint, ligament, nerve, or cellular injury. This article explains why that wait-and-see loop can stall healing and weaken a claim. It then follows the path used at Dr. Alex Jimenez’s Injury Medical Clinic PA in El Paso: instant multimodal assessment, chiropractic mechanical alignment, regenerative therapies, tissue-rebuilding peptides, laser therapy, dual FNP-BC and DC care under one roof, SOAP notes, functional impairment mapping, and a three-phase plan from acute pain to Maximum Medical Improvement (MMI).
The Wait-and-See Loop After the Emergency Department
A crash can sprain ligaments, bruise discs, pinch nerves, and knock the spine out of line. The emergency department is built to find life-threatening problems. If no fracture needs surgery, many people go home with rest, ice, a muscle relaxer, and an anti-inflammatory pill. Pain may drop for a short time. Structural and cellular injury can remain.
When discomfort fades, people may think they are fine. Days or weeks later, stiffness, headaches, numbness, or sleep problems appear. Insurers often treat that gap as proof the crash was minor or that something else caused the symptoms. A delay can also let a fresh sprain become a long-term problem. That is how wait-and-see care can leave a person with both a slower recovery and a weaker claim.
Why Delayed Care Hurts Healing and the Record
Personal injury claims rest on records. Strong files show three facts: the crash caused the injury, care started soon, and treatment was reasonable and tracked over time. Late or thin notes give an adjuster room to argue that the injury was small, old, or unrelated.
Notes that list range of motion, nerve findings, daily limits, and progress help turn “I hurt” into measurable facts. Clinics that document function—work, driving, sleep, and lifting—give attorneys a clearer picture of damages. Thorough documentation can support a stronger settlement picture because it shows medical need and real-life impact, not only a pain score.
Harmonized Care Under One Roof
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, is dually credentialed as a Family Nurse Practitioner and a Doctor of Chiropractic. That mix lets patients receive structural care and medical care in one place. They do not have to coordinate with separate clinics for alignment work, medical review, imaging decisions, and injury documentation.
This dual-scope model matters after a crash because injuries are rarely only “a sore neck.” Joints may be restricted. Soft tissue may be inflamed. Nerves may be irritated. Sleep and inflammation can slow repair. A provider who can examine mechanics and medical risk in the same visit can build one plan instead of two disconnected plans.
Medical Direction With Dr. Maria Guadalupe Cardenas
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933). She has more than 40 years of experience as an internist and serves as medical director and collaborative physician at Injury Medical Clinic PA in El Paso, Texas.
This multidisciplinary setup is common in integrative and injury-care clinics. An MD provides medical direction. A chiropractor leads mechanical and functional care. Dr. Jimenez provides chiropractic care, functional medicine, personal injury documentation, and rehabilitation guidance. Dr. Cardenas provides medical oversight, risk review, and coordination for advanced services. The team also integrates rehabilitation and related injury services so care stays aligned under one roof.
Instant Multimodal Assessment
The clinic interrupts the wait-and-see cycle with an early, complete exam rather than a “come back if it still hurts” packet.
A typical first visit includes:
History of the collision and delayed symptoms
Orthopedic and neurologic testing
Range-of-motion and posture checks
Review of emergency-department notes and imaging when needed
Mapping of joints, muscles, ligaments, and nerves involved
Dr. Jimenez has observed that many accident injuries are missed at first because they involve soft tissue rather than a broken bone. Whiplash, ligament sprain, and nerve irritation may not show on a basic X-ray. That is why early motion testing and timely follow-up imaging matter.
From that exam, care can combine chiropractic mechanical alignment with modern medical procedures. Regenerative therapies, tissue-rebuilding peptides, and laser therapy may be added when the findings support them. Functional medicine looks at sleep, nutrition, and inflammation that can stall repair.
How Integrative Chiropractic Care Fits
Integrative chiropractic care is the mechanical core. Gentle adjustments, soft-tissue work, traction, and spinal decompression aim to restore joint motion, ease nerve pressure, and reduce muscle guarding. When the spine and joints move better, blood flow and nerve signals improve. That gives regenerative and rehab work a better chance to succeed.
Integrative chiropractic does not stand alone. The clinic pairs it with:
Regenerative therapies such as PRP, platelet-rich fibrin, or microfragmented adipose tissue when medically appropriate, to support tendon, ligament, and joint repair
Tissue-rebuilding peptides studied for signaling related to inflammation, collagen support, and blood vessel growth
Laser therapy (photobiomodulation / MLS laser) that uses light to support cellular energy and local circulation
Rehabilitation to rebuild strength, balance, and work-ready movement
Medical oversight from Dr. Cardenas for safety, referrals, and internal medicine issues that can affect healing
The point is simple: line up the frame, then support the tissue that must rebuild.
SOAP Notes and Functional Impairment Mapping
Even with proper care, a claim can still be denied if the chart is thin. The clinic uses detailed SOAP notes to track a patient from the initial injury to MMI.
Subjective: pain, sleep, work limits, and daily tasks in the patient’s words
Objective: motion degrees, strength, spasm, and neurologic signs
Assessment: how findings link to the crash
Plan: why the next step is needed
Functional impairment mapping goes further. It tracks how the injury changes driving, sitting, lifting, and household tasks. Those details help show why care continues and when the patient reaches MMI—the point at which further major improvement is not expected. Clear notes also help explain any pause in care so insurers cannot treat every gap as proof the injury was gone.
Attorneys look for this kind of file because it is easier to defend. It shows causation, timely care, and a reasoned path rather than a stack of pain pills.
A Scannable Three-Phase Recovery Plan
Recovery is easier to follow when it has stages. The clinic uses a phase-by-phase approach that patients and attorneys can scan.
Phase 1: Acute pain alleviation (days 1–14)
Calm inflammation and muscle spasm
Restore basic joint motion with gentle chiropractic care
Use laser therapy and supportive medical care as needed
Start a paper trail that links symptoms to the crash
Protect sleep and basic daily function
Care in this window helps prevent the “it must not have been serious” argument. It also reduces the chance that a sprain becomes long-term instability.
Phase 2: Cellular regeneration and stability (weeks 3–8)
Continue alignment work so tissue heals in a better position
Add regenerative therapies or peptides when the exam supports them
Use laser and soft-tissue methods to support repair
Address nutrition, hydration, and inflammation through functional medicine
Recheck motion, strength, and nerve findings
Feeling a little better is not the finish line. The team looks for tissue stability, not only a lower pain score.
Phase 3: Functional rehabilitation to MMI (8+ weeks)
Build strength, endurance, and work or driving tolerance
Correct posture and movement patterns that keep re-irritating the injury
Document remaining limits and future care needs
Reach MMI with a clear summary of what improved and what remains
MMI does not always mean perfect. It means the chart can show the true end of expected medical gain. That honesty protects both the patient and the claim.
Clinical Observations From Dr. Alexander Jimenez
From years of accident and sports-injury work in El Paso, Dr. Jimenez notes that people often look “fine” on a first X-ray and still have ligament, disc, or nerve injury that shows up later. He also notes that care works best when mechanical correction and cellular support run together. Adjusting a joint while nearby tissue stays inflamed or poorly supplied can stall progress. Pairing chiropractic care with regenerative tools, peptides, laser therapy, and medical direction is meant to close that gap.
The same observations apply to documentation. A note that only says “patient improved” is weak. A note that shows degrees of motion gained, tasks the patient can now do, and why the next phase is needed is useful in both the treatment room and a settlement file. Dual-credentialed care, plus medical direction from Dr. Cardenas, lets the clinic tell that story from both a chiropractic and a medical viewpoint.
A Clearer Path From Injury to MMI
Conventional personal injury treatment often keeps accident victims in a prolonged state of uncertainty. Muscle relaxers and NSAIDs can mask immediate discomfort while structural and cellular injury go unaddressed. Dr. Jimenez’s clinic interrupts that cycle with instant multimodal assessment, harmonized structural and medical care under one roof, and objective tracking from first injury to MMI.
The journey is straightforward: ease acute pain in days 1–14, support cellular regeneration and stability in weeks 3–8, then rebuild function from week 8 onward. For people in El Paso facing auto or work injuries, that structure can protect both recovery and the record that supports fair compensation.
When to Seek a Second Opinion for Complex Spinal Joint and Nerve Pain in El Paso, Texas
Abstract
Complex spinal joint and nerve pain is long-lasting discomfort that comes from more than one spinal structure at the same time. Wear, injury, or pressure can affect the bones, facet joints, discs, and nearby nerve roots at the same time. That overlap is why a single pill, a short course of physical therapy, or one injection often fails to bring lasting relief. This article explains what the condition is, how nerve pain differs from joint pain, and when people in El Paso, Texas, should seek a second opinion. It also shows how integrative chiropractic care can work with medical oversight and combined therapies such as shockwave therapy, MLS laser therapy, IV infusion therapy, PRP, PFP, MFAT, and epidural spinal injections. The goal is a clear path toward better movement and less daily pain.
What Is Complex Spinal Joint and Nerve Pain?
Complex spinal joint and nerve pain is chronic discomfort caused by overlapping damage, wear, or pressure on the vertebrae, facet joints, discs, and surrounding nerve roots in the spine.
The spine is a stack of bones called vertebrae. Between most of those bones sit discs that act like cushions. Small joints on the back of the spine, called facet joints, help you bend and twist. Nerve roots leave the spinal canal through narrow openings and travel into the arms or legs. When more than one of these parts is irritated at the same time, pain can feel mixed, confusing, and hard to treat.
Spine problems often involve the vertebrae, discs, nerves, and nearby muscles together. That mix can cause back or neck pain, stiffness, limited motion, numbness, tingling, or weakness in an arm or leg.
This is not the same as Complex Regional Pain Syndrome (CRPS). CRPS is a separate nerve condition that usually affects a hand, arm, foot, or leg after injury and can include changes in skin color, temperature, and swelling. Complex spinal joint and nerve pain stays centered on the spine and the nerves that exit it.
Why Joint Pain and Nerve Pain Feel So Different
Joint pain and nerve pain do not feel the same, even when they start in the same region of the back or neck.
Joint pain often feels like:
A deep ache in one spot
Stiffness after sitting or first thing in the morning
Pain that worsens when you arch backward or stand for a long time
Soreness that stays close to the spine
Nerve pain often feels like:
Burning, stabbing, or electric-shock sensations
Tingling, numbness, or “pins and needles”
Pain that travels into a shoulder, arm, hip, or leg
Weakness in a muscle group
Kansas Pain Management notes that muscle pain tends to feel dull and tight, nerve pain often shoots or burns, and facet joint pain is more localized and position-based. Oakland Spine explains that nerve pain can start far from where you feel it, while joint pain usually stays in one area unless a swollen joint also presses on a nerve.
When both problems exist together, a person may have a stiff low back and burning pain down the leg. Treating only the joint, or only the nerve, leaves half the problem untouched.
Common Causes of Pressure on Spinal Joints and Nerves
Nerve compression happens when the space around a nerve root becomes smaller. Common causes include:
A bulging or herniated disc
Bone spurs from arthritis
Spinal stenosis (a narrowed spinal canal)
Degenerative disc disease
Injury from a fall, work accident, or car crash
Thickened ligaments
Long-term posture strain
“Radiculopathy” is the medical term for a pinched nerve root. It can cause pain, numbness, tingling, or weakness along the nerve’s path. It is most common in the neck and lower back.
Facet joints can also wear down. When those small joints become inflamed, they can create local spine pain and, in some cases, add extra pressure near a nerve root. That is one reason symptoms overlap.
When to Seek a Second Opinion in El Paso, Texas
A second opinion is not a sign that the first provider failed. It is a smart step when the picture is incomplete.
Consider a second opinion if:
Pain has lasted more than a few weeks and is not clearly improving
You have numbness, tingling, or weakness in an arm or leg
Imaging was done, but no one explained how the findings match your symptoms
You were told “everything looks fine,” yet you still cannot work, sleep, or drive comfortably
Steroid shots or pain medicine helped only for a short time
Surgery was offered as the next step before a full non-surgical plan was tried
You were treated for only one pain source when your symptoms sound mixed
An auto accident, work injury, or old sports injury still bothers you months later
You live in El Paso or elsewhere in West Texas and want a team that can look at both the mechanical and medical sides of the problem
People often seek a new evaluation when traditional care focused on rest, medication, or a single procedure and the pain kept returning. Accurate identification of the pain source—nerve, joint, disc, muscle, or a combination—guides better treatment.
Why One Treatment Often Is Not Enough
A herniated disc on an MRI does not always explain every symptom. Facet arthritis, muscle guarding, inflammation, poor movement patterns, and nerve irritation can all sit at the same spinal level. If care targets only one layer, relief can stall.
Educational videos on spine anatomy and nerve pain show how discs, joints, and nerves sit close together and can fail as a unit rather than as isolated parts. That close relationship is why a combined plan often makes more sense than a single procedure.
Early, complete evaluation also matters because delayed care can allow stiffness, weakness, and guarded movement to become habits. Those habits then keep feeding into the pain cycle.
How Integrative Chiropractic Care Fits Into Treatment
Integrative chiropractic care looks at how the spine moves, how the joints stack, and how nearby muscles and nerves respond. The goal isn’t just to ease pain for a day. The goal is to restore cleaner motion, so nerves have more room and joints share load more evenly.
Chiropractic care can help by:
Improving spinal joint motion with precise adjustments
Reducing mechanical pressure around irritated nerve roots
Pairing care with spinal decompression when discs are compressed
Retraining posture and core support so the spine stays more stable
Coordinating soft-tissue work so muscles stop guarding the injured area
Oakland Spine notes that chiropractic care and physical therapy can help both nerve pain and joint pain when the plan corrects alignment and builds support around the injured structures.
In an integrative clinic, chiropractic care does not stand alone. It is timed with medical evaluation, rehabilitation, and regenerative options so the spine can move better while tissues repair.
Combined Therapies for More Thorough Healing
Complex pain often needs more than one tool. The therapies below are commonly used together, not as competing choices.
Shockwave therapy
Shockwave therapy sends acoustic waves into tight or scarred tissue. Those waves can increase local blood flow, break up dense scar tissue, and help a stalled healing response start again. It is often used before or after regenerative injections so the area is more ready to repair.
MLS laser therapy
MLS laser therapy uses specific light wavelengths to lower inflammation and support cellular energy. It can calm swelling after an adjustment, decompression session, or injection and make it easier to stay consistent with rehab.
IV infusion therapy
IV therapy delivers fluid and selected nutrients into the bloodstream. It does not replace spinal treatment. It may support hydration, recovery, and the broader healing environment while other therapies work on the joints and nerves.
PRP (platelet-rich plasma)
PRP uses a concentrated portion of a person’s own blood platelets. Platelets release growth factors that may support tissue repair in joints, soft tissue, or selected spinal structures when used as part of a larger plan.
PFP (platelet-fibrin plasma / platelet-fibrin products)
PFP is a related blood-based product. Clinics use it when a more fibrin-rich preparation may better support a treatment area. Like PRP, it is a supportive option, not a stand-alone cure.
MFAT (microfragmented adipose tissue)
MFAT uses a small amount of a person’s own fat tissue that is processed into smaller fragments. It may be considered when a more complex injury requires structural or cushioning support.
Epidural spinal injections
An epidural injection places medication near an irritated nerve root to reduce inflammation in the space around that nerve. Conservative care for radiculopathy often includes rehabilitation, medication, and interventional options such as epidural injections. Injections can create a window of lower pain so a person can move, adjust, and strengthen more effectively.
These options work best when they are sequenced. Decompression and adjustments can create space. Shockwave and laser can prepare tissue and control inflammation. Regenerative procedures and selected injections can support biology. Rehabilitation then teaches the spine how to hold the new motion.
The Collaborative Team in El Paso
At Injury Medical Clinic PA in El Paso, Texas, care is built as a team model rather than a one-provider visit.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides chiropractic care, functional medicine, personal injury evaluation, and rehabilitation planning. His clinical observations, shared on dralexjimenez.com and his LinkedIn profile, emphasize finding both the mechanical problem and the metabolic or inflammatory factors that keep pain going. He often notes that patients improve more when alignment, soft-tissue health, nutrition, and cellular support are addressed together.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine. Her NPI is #1164426749, and her Texas medical license is #J2933. With more than 40 years of experience as an internist, she serves as medical director and collaborative physician at Injury Medical Clinic PA. This MD–DC partnership is common in integrative and injury-care clinics. The medical director provides medical oversight while the chiropractic and rehabilitation team addresses spinal mechanics, movement, and recovery.
Together, the team can coordinate:
Chiropractic and spinal decompression
Functional medicine and nutrition support
Personal injury documentation and rehabilitation
Shockwave and MLS laser therapy
Regenerative options such as IV infusion therapy, PRP, PFP, and MFAT
Medical decision-making around injections and co-existing health issues
That structure matters in El Paso, Texas, where patients may travel from across El Paso, the Upper Valley, or nearby desert communities and want one coordinated plan instead of disconnected referrals.
What a Second-Opinion Visit Should Cover
A useful second opinion should do more than repeat the last MRI report. It should connect your story to a clear exam.
A thorough visit often includes:
A detailed history of how the pain started and what makes it travel
A movement exam of the neck or low back
Nerve testing for strength, sensation, and reflex changes
Review of prior imaging and whether it matches the exam
Screening for joint pain versus nerve pain versus mixed pain
A discussion of non-surgical options before any new procedure
A staged plan that may combine chiropractic care, rehab, laser or shockwave therapy, and selected regenerative or injection options
If you have personal injury, veteran, or work-related documentation needs, those records should be part of the same conversation so care and paperwork stay aligned.
A Clear Next Step for El Paso, Texas Patients
Complex spinal joint and nerve pain is particularly challenging because it is rarely “just a disc” or “just arthritis.” It is often both, plus muscle guarding and nerve irritation. That is why people feel stuck after standard care.
A second opinion is worth seeking when pain is mixed, persistent, or poorly explained. Integrative chiropractic care can restore motion and reduce mechanical pressure. Medical oversight can keep the plan safe and complete. Combined therapies such as shockwave therapy, MLS laser therapy, IV infusion therapy, PRP, PFP, MFAT, and epidural spinal injections can support healing from more than one angle.
If you live in El Paso or elsewhere in West Texas and your current plan has not given you a clear path forward, a multidisciplinary evaluation can help you see which structures are driving the pain and which combination of care is most likely to help you move again.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine