Back Clinic Auto Accident Injuries Chiropractic Physical Therapy Team. Car accidents are one of the leading causes of injuries. Over 30,000 were fatal and another 1.6 million involved other injuries. The damage they cause can be immense. The economic cost of car accidents is estimated to be $277 billion each year or about $897 for every person living in the United States.
Many automobile accidents occur throughout the world every year, affecting individuals both mentally and physically. From neck and back pain to bone fractures, auto injuries can challenge the daily lives of those who are affected. Automobile accidents occur throughout the world every year, affecting a wide number of individuals, both physically and mentally.
From neck and back pain to bone fractures and whiplash, auto accident injuries and their associated symptoms can challenge the daily lives of those who experienced unexpected circumstances. Dr. Alex Jimenez’s collection of articles discusses auto accident injuries caused by trauma, including which specific symptoms affect the body and the particular treatment options available for each injury or condition resulting from an auto accident.
Being involved in a motor vehicle accident can not only lead to injuries but they can be full of confusion and frustrations. It is very important to have a qualified provider specializing in these matters completely assess the circumstances surrounding any injury. For more information, please feel free to contact us at (915) 850-0900 or text to call Dr. Jimenez personally at (915) 540-8444.
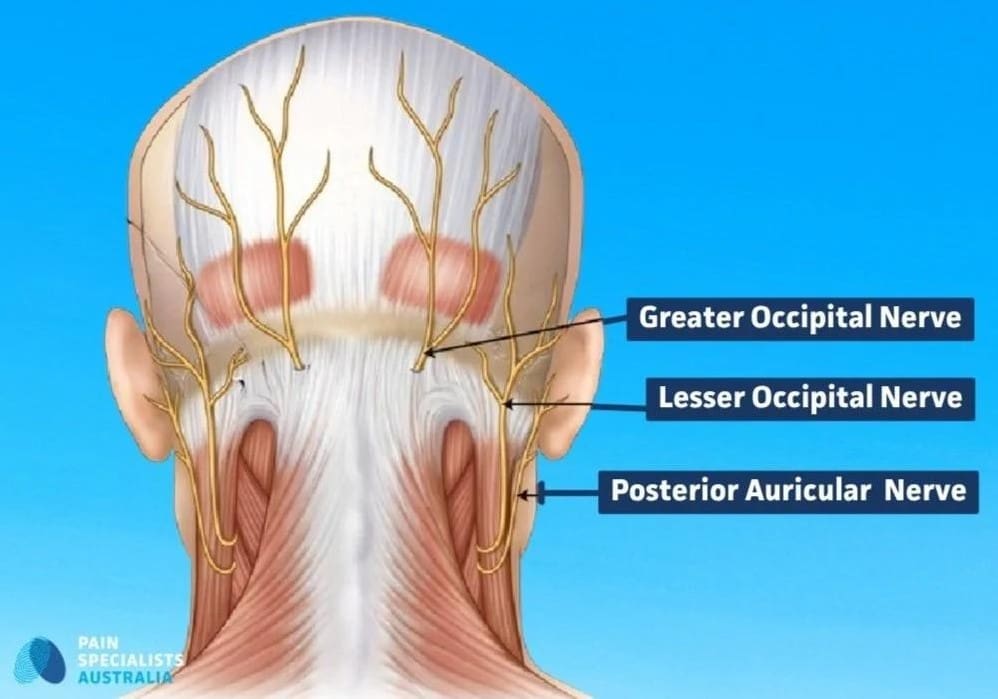
Why Sub-Occipital Headaches Often Follow Neck Strain in Accidents—and How Structural Care Fits
Abstract
After a car accident, many people notice a new headache that starts right at the base of the skull and flares when they turn their head, look down at a phone, or hold one posture too long. These sub-occipital headaches often reflect strain in the upper cervical joints and the small muscles that connect the skull to the top of the neck. Careful screening first rules out serious injury; targeted structural care and rehabilitation can then address the mechanical drivers while the patient stays in charge of decisions.
You walk away from a rear-end collision on I-10 or Loop 375 feeling mostly stiff. A day or two later, a dull, heavy ache settles at the base of your skull. Turning your head to check a blind spot, working at a computer, or even resting your head on a pillow makes it sharper. The pain may stay local or spread over the top of the head. This pattern is common after neck strain, and it does not automatically mean the brain itself was injured. Upper cervical joints and the suboccipital muscles frequently become sources of referred pain once rapid deceleration loads them beyond their normal range.
The upper neck and the base of the skull share nerve pathways inside the trigeminocervical complex. Irritation in the joints or muscles of the upper cervical spine can feel like a headache even when the brain is otherwise uninjured. After appropriate trauma screening clears more serious concerns, evaluating these structures and restoring their function becomes a practical part of recovery.
How Accident Forces Load the Upper Neck
Rapid acceleration-deceleration—especially in rear-end impacts—forces the head into sudden flexion and extension. The small joints between the occiput, atlas (C1), and axis (C2), along with the four suboccipital muscles that stabilize them, absorb much of that motion. Ligaments can stretch, joint capsules can become inflamed, and the muscles can go into protective spasm. The result is often local tenderness, reduced rotation or extension, and pain that is provoked by sustained postures or specific movements.
Patients commonly describe the headache as starting at the skull base and worsening with neck motion or prolonged sitting. Some also notice stiffness when they first get out of bed or difficulty looking over their shoulder while driving. These clues point clinicians toward a mechanical contribution rather than a purely primary headache disorder.
Not every base-of-skull headache is cervicogenic, and not every post-collision headache is purely muscular. A thorough evaluation looks for:
Pain reproduced by sustained or repeated neck positions
Restricted upper cervical motion, especially rotation in flexion
Tenderness over the suboccipital muscles or upper cervical joints
Improvement when those structures are temporarily unloaded or treated
ICHD-3 criteria for cervicogenic headache require evidence that a cervical disorder is capable of producing the headache and that the two are linked in time or by response to treatment. Imaging findings alone (mild disc changes or degenerative joints) are not enough; many asymptomatic people show similar changes. The clinical examination, the timing after trauma, and the response to carefully selected care supply the stronger connection.
Non-maleficence requires that elective structural treatment wait until red flags have been ruled out. After a collision, the first priorities are neurological screening, assessment for cervical vascular injury when indicated, and imaging if progressive neurological signs, severe unrelenting pain, or other concerning features appear. Only after those steps does manual care or progressive rehabilitation proceed. This sequence protects the patient from delayed recognition of rare but serious complications while still allowing timely treatment of the far more common soft-tissue and joint findings.
Targeted Structural Support and Rehabilitation
When examination supports a mechanical driver, care focuses on restoring motion, reducing protective muscle guarding, and rebuilding endurance so the upper neck can tolerate daily postures again. Selected approaches may include:
Gentle joint mobilization or manipulation matched to the specific restricted segments
Soft-tissue techniques directed at the suboccipital group, upper trapezius, and deep neck flexors
Progressive deep-neck-flexor and postural endurance exercises
Education on workstation setup, sleep positioning, and gradual return to activity
Evidence summaries consistently list spinal manipulation and mobilization, together with therapeutic exercise, among the interventions with moderate support for cervicogenic headache (Bryans et al., 2011; Jull et al., 2002). The goal is not simply temporary relief; it is measurable improvement in range of motion, reduced provocation of headache with neck movement, and greater ability to maintain normal head-on-neck posture without fatigue.
Patients who also experience tension-type features or overlapping migraine symptoms may benefit from coordinated strategies discussed in the clinic’s stress-headache and integrated migraine resources. Structural work remains complementary, not a replacement, for medical evaluation when migraine criteria are met.
Bioethical Pillars in Practice
Beneficence is served by directing care at the structures that examination shows are contributing to the headache, rather than applying a one-size-fits-all protocol. Non-maleficence is protected by the clearance step already described and by the preference for non-invasive, drug-free options that lower the chance of long-term analgesic dependence or premature surgical consideration. Autonomy is strengthened when the patient understands the neck-to-headache connection: why certain postures flare the pain, what the examination findings mean, and how home exercises and posture changes fit into the plan. Shared records and clear explanations allow the patient and any legal counsel to see the same objective timeline.
What Makes the Clinic Unique
Dr. Alex Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is one of the only clinics in El Paso that combines a dual-licensed soft-tissue specialist with a board-certified medical director under one roof.
Dr. Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, brings chiropractic structural evaluation together with advanced practice nursing scope, allowing objective digital range-of-motion measurements, soft-tissue assessment, and selected regenerative or photobiomodulation options when indicated.
Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine and serving as Medical Director, provides medical oversight for complex cases, laboratory interpretation, and coordination with outside physicians.
This dual-scope model produces co-signed notes that document both the mechanical findings and the medical context—documentation that supports both clinical recovery and medical-legal causation under the Texas Eggshell Rule.
Connecting Structural Findings to the Larger Clinical Framework
Integrated structural documentation—timed range-of-motion values, provocation findings, and progressive functional improvement—appears in the broader clinical framework at dralexjimenez.com. Attorneys and patients reviewing a file can see how upper-cervical joint and muscle findings were measured, how they changed with care, and how they relate to the original collision mechanics. That continuity reduces the chance that a defense examiner will successfully characterize the headache as unrelated or purely subjective.
Cross-links that expand on related topics include discussions of cervicogenic triggers, headache trigger points, and the full medical-legal causation guide available on the master site.
Practical Steps Patients Can Take
Note which movements or postures reliably change the headache and share that list at the evaluation.
Complete any recommended imaging or specialist referral promptly so that elective care can begin without delay.
Practice the specific postural and strengthening drills prescribed rather than generic stretches found online.
Keep a simple diary of headache days, neck stiffness, and activities that help or hinder; this record supports both treatment adjustments and any later legal documentation.
Most people with post-collision sub-occipital headaches improve when clinicians identify mechanical contributors early and address them with graded, evidence-aligned care. Careful screening, targeted structural treatment, and patient understanding of the neck-to-headache link lead to clearer recovery and more defensible documentation.
If your headaches began or worsened after a collision and are provoked by neck movement or posture, a dual-scope evaluation can clarify whether upper cervical joints and suboccipital muscles are contributing drivers and what the next safe steps look like.
References
Bryans, R., Descarreaux, M., Duranleau, M., Marcoux, H., Potter, B., Ruegg, R., Shaw, L., Watkin, R., & White, E. (2011). Evidence-based guidelines for the chiropractic treatment of adults with headache. Journal of Manipulative and Physiological Therapeutics, 34(5), 274–289. doi.org/10.1016/j.jmpt.2011.04.008
Headache Classification Committee of the International Headache Society (IHS). (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. doi.org/10.1177/0333102417738202
Jull, G., Trott, P., Potter, H., Zito, G., Niere, K., Shirley, D., Emberson, J., Marschner, I., & Richardson, C. (2002). A randomized controlled trial of exercise and manipulative therapy for cervicogenic headache. Spine, 27(17), 1835–1843. doi.org/10.1097/00007632-200209010-00004
Linking Specific I-10 and Loop 375 Force Vectors to Documented Changes in Daily Sitting and Standing Tolerance
After a rear-end or multi-vehicle impact on Interstate 10 or Loop 375, many patients leave the emergency room with imaging that shows disc height loss, annular changes, or mild herniation. Attorneys later face the familiar defense argument that the MRI looks “degenerative” and that range-of-motion numbers alone do not prove real impairment. What often decides the case is something simpler and more practical: whether the patient can still sit through a workday or stand long enough to complete ordinary tasks.
When clinic notes carefully connect the specific force vectors of those freeway collisions to measured drops in seated and standing endurance, the file moves beyond pictures and pure motion scores into documented, daily functional loss that juries and adjusters understand.
Why Highway Force Vectors Matter for Disc Cases
Highway collisions in El Paso generate distinctive loading patterns that differ from ordinary daily activity:
On I-10, high-speed rear impacts produce rapid axial compression combined with sudden flexion-extension through the lumbar spine.
On Loop 375, merging and lane-change impacts often add rotational and lateral shear forces.
These forces load the lower lumbar discs far beyond normal sitting or standing loads.
Disc tissue that may have shown age-related narrowing before the crash can still sustain acute annular strain or altered hydrostatic pressure, reducing its ability to tolerate sustained postures.
The clinical task is to document that change in endurance rather than rely solely on degrees of flexion or extension.
Lower Back Pain
Personal Injury
Auto Accident Injuries
Car Accident Specialist
Collision & Injury Dynamics
Med-Legal Corner
Lawyers
Herniated Disc
Chronic Back Pain
Spine Care
What Objective Notes Must Capture
Objective notes that capture this difference typically include three linked elements:
A clear mechanism description timed to the collision (for example: “The patient was a restrained driver stopped on I-10 near the Loop 375 interchange when struck from behind at highway speed; the lumbar spine underwent rapid axial compression and flexion”).
Baseline functional history obtained early: how long the patient could sit or stand before the crash for work, driving, or household tasks.
Serial timed measurements of current tolerance—how many continuous minutes of sitting or standing are possible before pain, numbness, or the need to change position forces a break.
These endurance times are recorded independently of digital range-of-motion numbers. A patient may regain near-normal ROM yet still be limited to 12–15 minutes of continuous sitting because of disc-related loading intolerance.
Why Endurance Data Adds Value Beyond ROM
Pure ROM does not capture sustained postural load. A disc that has lost height or developed an acute annular lesion can still allow a single movement through a full arc, yet fail under the constant compression of sitting or the prolonged axial load of standing. Notes that record both the highway force description and the timed endurance data give the attorney concrete evidence that the impairment is real, measurable, and linked to the event rather than to ordinary aging.
How Specific Force Vectors Translate into Daily Limits
I-10 Rear-End Impacts
Consider a typical I-10 rear-end scenario. The sudden deceleration compresses the L4-L5 and L5-S1 discs while the torso is driven into the seat. Pre-existing mild degeneration, common on imaging of asymptomatic adults, does not prevent acute aggravation under the Texas Eggshell Plaintiff rule.
Common documented changes include:
Before the crash: ability to sit through a full eight-hour shift with only brief breaks.
After the crash: continuous sitting limited to 15–20 minutes before radiating pain or stiffness requires standing.
Standing tolerance drops from several hours of intermittent work to 10–15 continuous minutes before the need to sit or lean.
These numbers are recorded at each visit, plotted over time, and co-signed by the dual-licensed team.
Loop 375 Merging and Lane-Change Collisions
Loop 375 collisions often involve more lateral or oblique forces. The notes describe the vector (“left-rear impact while merging onto Loop 375”) and then document corresponding asymmetric endurance limits—greater difficulty sitting with the trunk rotated or standing with weight shifted to one side. The same timed-sitting and timed-standing protocol captures the deficit. Because the measurements are simple, repeatable, and patient-reported under clinical observation, they survive cross-examination better than subjective pain scores alone.
Building the Serial Objective Record
Serial documentation typically follows a consistent sequence:
At the initial post-collision visit, record the mechanism in detail.
Pre-injury sitting and standing capacity is quantified from the patient’s history.
Current continuous tolerance is timed under observation.
Subsequent visits re-measure the same endpoints after treatment intervals.
Improvements or plateaus are noted, along with any residual gap between pre-injury and current capacity.
Digital ROM and imaging findings are included, but they are not treated as the sole proof of impairment.
Endurance data provide the real-world functional translation that imaging cannot provide on its own. This approach also supports future-care planning. When sitting tolerance remains limited, the notes can justify ergonomic modifications, graded activity progression, or continued non-surgical care aimed at restoring postural endurance rather than simply chasing degrees of motion.
Bioethical Integration of Functional Tracking
Beneficence is served by focusing care on functional restoration. The goal is not merely to increase ROM numbers but to lengthen the time the patient can sit or stand so that work, driving, and daily activities become possible again.
Non-maleficence is observed by relying on non-invasive measurement and conservative progression. Timed endurance tracking avoids unnecessary procedures when the documented functional deficit can be addressed through structural care, activity modification, and monitored recovery.
Autonomy is preserved because the patient actively tracks and owns the tolerance data. Simple logs or clinic-timed sessions give the patient a clear record they can share with counsel and use to judge their own progress.
What Makes This Clinic’s Documentation Different
Injury Medical Chiropractic and Functional Medicine Clinic is the only integrated practice in El Paso that combines a dual-licensed soft-tissue specialist with an internal-medicine medical director. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, focuses on the structural and soft-tissue findings, digital motion assessment, and functional endurance testing. Dr. Maria Guadalupe Cardenas, MD, serves as medical director, providing internal medicine oversight, risk stratification, and coordination of any needed medical diagnostics. Together, they produce co-documented notes that pair the specific I-10 or Loop 375 force description with measured changes in sitting and standing endurance. This dual-scope record meets both clinical and legal documentation standards.
These functional linkages are packaged inside medical-legal causation documentation standards at dralexjimenez.com. Related discussions of disc findings, pre-existing condition claims under the Eggshell rule, and practical sitting tolerance appear throughout the site, including pages on herniated disc care, low-back pain with sitting and standing, and post-collision recovery pathways.
Attorneys who need more than imaging to demonstrate real-world impairment after disc injury will find that timed sitting and standing endurance, when clearly linked to the documented highway force vectors, supplies the missing practical proof. The measurements are straightforward, the mechanism is specific to El Paso freeways, and the dual-licensure notes keep the entire record courtroom-ready.
References
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. doi.org/10.3174/ajnr.A4173
Li, J. Q., Kwong, W. H., Chan, Y. L., & Kawabata, M. (2022). Comparison of in vivo intradiscal pressure between sitting and standing in human lumbar spine: A systematic review and meta-analysis. Life, 12(3), 457. doi.org/10.3390/life12030457
Rohlmann, A., Claes, L., Bergmann, G., Graichen, F., Neef, P., & Wilke, H.-J. (2001). Comparison of intradiscal pressures and spinal fixator loads for different body positions and exercises. Ergonomics, 44(8), 781–794. doi.org/10.1080/00140130110047673
Wilke, H.-J., Neef, P., Caimi, M., Hoogland, T., & Claes, L. E. (1999). New in vivo measurements of pressures in the intervertebral disc in daily life. Spine, 24(8), 755–762. doi.org/10.1097/00007632-199904150-00005
Rainville, J., Sobel, J. B., Hartigan, C., & Wright, A. (2004). Sitting and standing tolerance in patients with chronic back pain: Comparison between physician prediction and covert observation. Archives of Physical Medicine and Rehabilitation, 85(5), 837–839. doi.org/10.1016/j.apmr.2003.08.095
Andersson, G. B. J., Ortengren, R., & Nachemson, A. (1974). Intradiscal pressure, intra-abdominal pressure and myoelectric back muscle activity related to posture and loading. Clinical Orthopaedics and Related Research, 103, 156–164. doi.org/10.1097/00003086-197409000-00014
Nachemson, A. L. (1966). The load on lumbar disks in different positions of the body. Clinical Orthopaedics and Related Research, 45, 107–122.
Texas Pattern Jury Charges: General Negligence & Intentional Personal Torts (PJC 28.8 series). (2020). State Bar of Texas.
Persistent Lower Back Pain After a Car Accident: When Is Further Treatment Medically Justified?
Marcus finished his first six weeks of care after a rear-end collision on Loop 375. At rest, his lower back pain had dropped from an 8 out of 10 to a 3 or 4. He could sit through meetings and drive short distances. However, he could not perform the core functions of his job. As a warehouse supervisor in El Paso, he still needed to lift and move 50-pound boxes several times a day. Each time he bent and lifted, a sharp catch radiated across his lower back and into one hip. He paused mid-lift, shifted his weight, and felt the familiar fear that the next box would set him back weeks. His digital range-of-motion measurements remained restricted, and his orthopedic tests stayed positive on the same side the collision loaded.
That gap between “I feel better sitting still” and “I still cannot do my job safely” is common after motor vehicle accidents. It is also the point where further treatment must be medically justified—not by the simple fact that pain continues, but by clear clinical findings that residual traumatic effects are limiting function.
Pain persistence alone does not support unlimited care. Pain is a subjective report. Insurance reviewers, independent medical examiners, and courts look for objective evidence that the injury continues to produce measurable impairment, that prior care produced a meaningful response, and that additional treatment has a reasonable expectation of improving function or preventing further loss. Under the Texas Eggshell Plaintiff rule, a person with pre-existing disc degeneration can still recover for traumatic aggravation, but the file must show the change. Timed digital motion data, positive mechanical tests that match the collision forces, and documented inability to meet job demands provide that evidence. Without them, continued care can appear open-ended.
When Reassessment Is Medically Indicated
Reassessment is appropriate when a patient has completed an initial course of care yet still shows residual mechanical or functional deficits that interfere with prior activities. Common indicators include:
Restricted lumbar range of motion measured digitally that has not returned to expected levels
Persistent positive orthopedic tests (for example, Kemp’s test or straight-leg raise) that reproduce the patient’s familiar pain pattern
Documented difficulty with specific job tasks such as repeated lifting, prolonged standing, or bending under load
Failure to progress as expected after an adequate trial of care, or a pattern in which symptoms improve at rest but flare with the physical demands of work
New or progressive neurological findings that require clarification
In Marcus’s case, the combination of ongoing positive mechanical findings and clear work-related limitations justified a structured reassessment rather than simply extending the same passive treatments. The goal was to determine whether further active rehabilitation and selected conservative interventions could close the remaining functional gap or whether specialist referral and additional diagnostics were needed.
Active Rehabilitation That Targets Real Demands
Once acute inflammation has settled, active rehabilitation becomes the core of further care. Passive treatments alone rarely restore the capacity required for physically demanding work. Progressive programs focus on trunk and hip stability, controlled loading, and job-specific movement patterns. Directional preference exercises (often based on McKenzie principles), graded lifting practice, and endurance work for the core and posterior chain help the patient relearn safe mechanics under load. Clinical guidelines support these approaches, emphasizing early return to activity with modifications rather than prolonged rest.
For a warehouse supervisor, rehabilitation includes practicing the exact lifts required at work—close to the body, with neutral spine, and progressive weight—while monitoring symptom response. Serial functional testing documents whether capacity is improving, plateauing, or limited by residual structural findings. This objective record supports both clinical decision-making and any future-care or work-restriction opinions.
Selected Conservative Interventions Under Dual-Scope Oversight
When residual mechanical findings persist, selected conservative interventions remain appropriate. Spinal manipulative therapy can restore segmental motion. Non-surgical spinal decompression may reduce intradiscal pressure and support disc nutrition in selected patients with disc-related mechanical pain. Electroacupuncture and other neuromodulatory techniques can help modulate pain signals and support recovery without heavy reliance on medication. Class IV laser therapy and targeted soft-tissue work address persistent muscle guarding that limits motion.
These options are not endless by default. They are continued only while objective measures (range of motion, functional tests, and patient-reported work capacity) show benefit, and they are coordinated with the patient’s overall medical picture. At Injury Medical Clinic PA, this coordination occurs under the medical direction of Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine with more than 40 years of experience, working alongside dual-licensed Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP. Dr. Jimenez’s dual credentials allow him to address the structural, soft-tissue, and mechanical aspects of the injury, as well as the broader medical context. This integrated setup is one of the only clinics in El Paso that provides these treatments under true MD/NP and DC collaboration.
When Specialist Referral or Additional Diagnostics Are Needed
Further treatment is also justified when reassessment reveals findings that require more specialized input. Progressive neurological deficits, saddle anesthesia, or bowel/bladder changes demand urgent imaging and specialty referral. Even without red flags, flexion-extension radiographs can quantify alteration of motion segment integrity (AOMSI). For the lumbar spine, translation exceeding roughly 4.5 mm or abnormal angular motion relative to adjacent levels documents ligamentous insufficiency that scar tissue alone may not restore. These measurements support AMA Guides impairment ratings and help isolate traumatic aggravation from longstanding degeneration.
Timed MRI can clarify disc morphology when symptoms persist. High-intensity zones, specific annular findings, and correlation with the mechanism of injury help distinguish acute or subacute changes from purely chronic degeneration. Consider electrodiagnostic studies if radiculopathy remains in question. These diagnostics are not ordered routinely; they are ordered when clinical findings indicate they will change management or strengthen the causation record.
In personal injury cases arising from I-10 or Loop 375 collisions, this level of documentation helps establish both clinical and proximate causation. The mechanics of rapid deceleration and axial loading are linked to the residual mechanical findings and functional deficits. The resulting records support Letters of Protection, special damages, and future-care projections that include necessary rehabilitation or monitoring rather than open-ended passive care.
Bioethical Pillars in Ongoing Care
Three principles guide decisions about further treatment.
Beneficence means the integrated approach—chiropractic mechanical care, targeted rehabilitation, and medical oversight—exists to restore root function rather than simply suppress symptoms. The goal is a safer return to the physical demands of work and daily life.
Non-maleficence means preferring non-invasive, drug-sparing options first. When residual deficits respond to progressive loading and selected conservative interventions, the risks of prolonged opioid use or premature surgical consideration are reduced.
Autonomy means the patient remains the informed decision-maker. Clear explanations of findings, options, and expected outcomes allow the patient to participate in decisions about work modifications, further diagnostics, or specialist referral. Coordination with the patient’s existing primary care physician is maintained so care remains seamless.
Marcus’s residual work limitations were not dismissed as “just pain.” They were measured, linked to residual mechanical findings that matched the collision forces, and addressed with a plan that combined progressive rehabilitation and continued dual-scope oversight. That approach is medically justified because it ties treatment to objective function, not the mere presence of discomfort.
For a deeper look at how objective measurements and dual-licensure documentation establish medical-legal causation after collisions, visit dralexjimenez.com. Related pages on lumbar disc nomenclature, AOMSI and AMA Guides ratings, and functional recovery after injury provide additional context for both patients and the attorneys who represent them.
If you or a client is still limited in physically demanding work after an initial course of care following a car accident, a structured reassessment can clarify whether further treatment is medically indicated. Contact Injury Medical Clinic PA in El Paso to discuss an evaluation focused on residual mechanical findings and functional capacity.
References
American College of Physicians. (2017). Noninvasive treatments for acute, subacute, and chronic low back pain: A clinical practice guideline from the American College of Physicians. Annals of Internal Medicine, 166(7), 514–530. doi.org/10.7326/M16-2367
American Medical Association. (2008). AMA Guides to the evaluation of permanent impairment (6th ed.). American Medical Association. (Classic criteria for alteration of motion segment integrity [AOMSI] and Diagnosis-Related Estimates remain widely referenced in impairment rating; updated editions continue to address motion-segment findings.)
Department of Veterans Affairs & Department of Defense. (2022). VA/DoD clinical practice guideline for the diagnosis and treatment of low back pain (Version 3.0). healthquality.va.gov/guidelines/Pain/lbp
Fardon, D. F., & Milette, P. C. (2001). Nomenclature and classification of lumbar disc pathology: Recommendations of the combined task forces of the North American Spine Society, American Society of Spine Radiology, and American Society of Neuroradiology. Spine, 26(5), E93–E113. doi.org/10.1097/00007632-200103010-00006
State Bar of Texas. (2020). Texas pattern jury charges: General negligence & intentional personal torts (PJC 28.8B & 28.8C). State Bar of Texas. (These charges instruct juries on aggravation of pre-existing conditions under the eggshell-plaintiff principle.)
Cervical Contributions to Chronic Migraine and How Guideline-Based Botox Complements Structural Care
After a low-speed rear-end collision on Loop 375, Elena noticed her neck stayed tight even after the initial soreness faded. Within weeks, the headaches that once arrived a few times a month now filled most of her calendar. Turning her head to assess a blind spot, sitting through a long meeting, or simply waking with stiff shoulders seemed to launch the next attack. Like many people in El Paso whose migraines intensify after injury or with ongoing neck tension, she discovered that the cervical spine and the upper-shoulder muscles can feed the same pain pathways that drive chronic migraine. Addressing both the structural findings and the preventive injection map used in guideline-based Botox care can reduce the total burden when neither approach is used alone.
Neck pain appears in a large share of people who live with migraine, and the overlap is not random. Sensory nerves from the upper cervical joints, discs, ligaments, and deep muscles converge with trigeminal pathways inside the trigeminocervical complex. Ongoing mechanical irritation or muscle guarding in the neck can therefore add extra input to networks already sensitized in migraine. After trauma—whiplash-type forces, abrupt deceleration, or repeated postural load—the same structures may show restricted motion, segmental stiffness, or altered disc height that keeps the input elevated. Cervical paraspinal muscles, the suboccipital group, and the upper trapezius often carry tender points that patients recognize as where their headaches begin or linger.
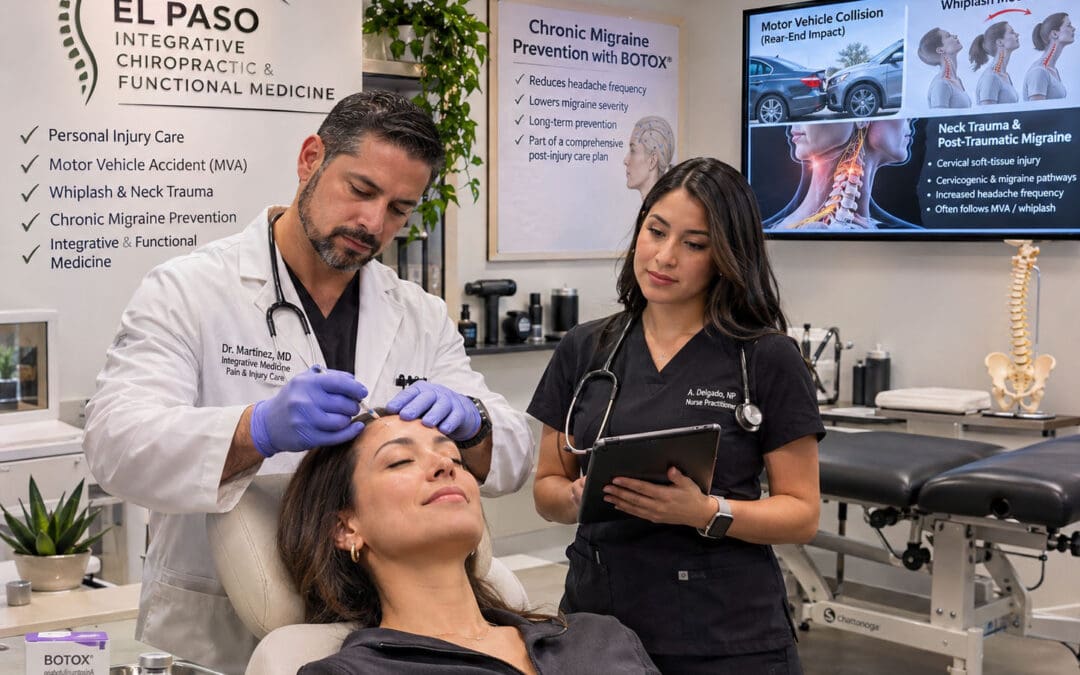
The Phase III Research Evaluating Migraine Prophylaxis Therapy (PREEMPT) trials established a fixed-site, fixed-dose injection pattern that remains the FDA-approved framework for onabotulinumtoxinA in chronic migraine (typically defined as 15 or more headache days per month). The full protocol places 155 units across 31 sites in seven muscle groups. Three of those groups sit precisely in the regions Elena and many others describe as sources of tension:
Occipitalis receives six sites (three per side) for 30 units, positioned near the external occipital protuberance.
Cervical paraspinal muscles receive four sites (two per side) for 20 units, placed a short distance below the occipital ridge and lateral to the midline.
Trapezius receives six sites (three per side) for 30 units along the upper portion of the muscle from the base of the neck toward the shoulder.
Optional “follow-the-pain” sites may add up to 40 more units when tenderness is prominent, bringing the total as high as 195 units. These posterior injections do not “freeze” the muscles in a cosmetic sense; they reduce the release of pain-signaling chemicals from peripheral nerve endings, which can lower the drive that reaches the trigeminocervical complex. Because the same muscles and nearby joints are often examined during a structural evaluation, you can review the injection map and cervical findings together rather than in isolation.
A practical assessment begins with the patient’s own timeline: when neck stiffness or reduced turning first appeared relative to the rise in headache days, and whether certain postures or movements reliably precede an attack. Range-of-motion measurements, segmental motion testing, and palpation of the occipitalis, paraspinals, and trapezius identify areas of restriction or tenderness that overlap the PREEMPT landmarks. When imaging or prior records show disc changes or segmental findings at upper or mid-cervical levels, those details are noted so the structural plan can address mobility and load without assuming every radiographic change drives migraine alone. The goal is clarity for the patient: which findings are being treated with alignment and soft-tissue work, which sites will receive the standardized Botox doses, and how the two will be timed across the typical 12-week injection cycle.
Structural care focuses on restoring usable motion and reducing unnecessary muscle guarding. Gentle mobilization or adjustment of restricted segments, soft-tissue work along the paraspinals and trapezius, and progressive loading exercises help the neck tolerate daily positions with less protective tension. Patients often notice smoother head turning and reduced baseline tightness between the shoulder blades. When these changes occur alongside fewer headache days after the first or second Botox cycle, the combined effect supports both fewer attacks and greater confidence in everyday movement. Sleep can improve because the neck no longer forces a guarded posture through the night, and the need for rescue medication may decline as the overall frequency drops.
Beneficence is served when both approaches work toward the same outcome: fewer disabling headache days and a better ability to move, work, and rest. The structural work addresses mechanical contributors that can feed the pain system, while the guideline-based injections dampen peripheral signaling in the exact regions patients identify as tender. Non-maleficence favors starting with these non-surgical options. Careful screening for red flags, precise injection technique, and graded mobility work reduce the chance that a patient will move prematurely toward more invasive procedures or long-term reliance on daily preventive medications. Autonomy is protected when the patient understands both the injection sites—occipitalis, cervical paraspinals, and trapezius—and the concurrent alignment plan. Clear explanations of what each treatment targets, how progress will be measured (headache-day counts, range of motion, and functional tolerance), and how the schedule will be adjusted let the patient remain the decision-maker while coordinating with any existing medical team.
What makes Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic unique is its medical director, Dr. Maria Guadalupe Cardenas, MD, along with a dual-licensed nurse practitioner who specializes in soft-tissue injury. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, evaluates cervical motion, segmental findings, and soft-tissue contributions while coordinating with Dr. Cardenas on overall medical direction. This integrated model is the only clinic in El Paso, Texas, that provides these combined structural and guideline-based preventive treatments under one coordinated team. Patients receive both hands-on assessment of disc and joint factors and the standardized PREEMPT injection pattern without shuttling between separate offices for each element of care.
Further detail on how cervical findings and headache patterns are documented appears in the integrated migraine treatment resources and the causation framework available at dralexjimenez.com. Related discussions of neck pain, whiplash mechanics, and functional recovery after injury appear in the clinic’s guides on cervical contributions to headache and on establishing clear clinical timelines. Integrated structural and preventive documentation appears in the medical-legal causation framework at https://dralexjimenez.com.
When neck tension and chronic migraine travel together, examining the cervical muscles and joints alongside the PREEMPT map gives a practical way to match treatment to the tissues that are actually contributing. Structural work restores motion and reduces guarding; guideline-based Botox lowers the peripheral drive from the same regions. Together, they support fewer headache days, easier daily movement, and a clearer plan the patient can understand and use to guide care.
References
Al-Khazali, H. M., Younis, S., Al-Sayegh, Z., Ashina, S., Ashina, M., & Schytz, H. W. (2022). Prevalence of neck pain in migraine: A systematic review and meta-analysis. Cephalalgia, 42(7), 663–673. https://doi.org/10.1177/03331024211068073
Blumenfeld, A., Silberstein, S. D., Dodick, D. W., Aurora, S. K., Turkel, C. C., & Binder, W. J. (2010). Method of injection of onabotulinumtoxinA for chronic migraine: A safe, well-tolerated, and effective treatment paradigm based on the PREEMPT clinical program. Headache: The Journal of Head and Face Pain, 50(9), 1406–1418. https://doi.org/10.1111/j.1526-4610.2010.01766.x
Headache Classification Committee of the International Headache Society (IHS). (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. https://doi.org/10.1177/0333102417738202
Sterling, M., Jull, G., & Vicenzino, B. (2019). Whiplash-associated disorders and post-traumatic headache. In Textbook of neuromodulation and physical medicine (related clinical reviews on cervical contributions after trauma).
Why Mechanism-to-MRI Linkage of Disc Injury Is Required to Justify Lumbar Causation at Trial
Abstract
Defense counsel routinely labels annular tears and modest disc-height loss as “pre-existing degeneration.” A precise mechanism-to-MRI linkage—correlating specific highway force vectors (axial compression, lateral shear, rotation) to the level, side, and morphology of the imaging findings—is required to establish clinical and proximate causation under Texas law and to support special damages for future non-surgical care. This article shows attorneys how structural MRI, timed to the collision and interpreted against the Texas Eggshell Plaintiff framework, neutralizes those challenges while future-care projections for extracorporeal shockwave therapy (ESWT) and spinal decompression document ongoing structural needs.
Imagine the defense expert in an El Paso courtroom pointing at a lumbar MRI and stating, “The annular fissure and 2 mm height loss are age-related.” Without a clear biomechanical bridge from the crash forces to those exact findings, the jury is left with competing medical opinions, and the claim is vulnerable. Mechanism-to-MRI linkage supplies that bridge. It converts a radiologic observation into courtroom-ready evidence of traumatic aggravation.
The Trial Reality of Annular Tears and Disc-Height Challenges
Annular tears (more precisely termed annular fissures in NASS nomenclature) and measured disc-height loss are the two findings most often attacked as pre-existing. Defense radiologists emphasize that high-intensity zones on T2-weighted images can appear in asymptomatic individuals and that modest height loss is common after age 40 (Fardon et al., 2014). Attorneys therefore need more than the finding’s mere presence; they must show that the morphology, laterality, and timing match the collision’s known force vectors and differ from multilevel, symmetric baseline degeneration.
Texas law does not require a perfectly healthy spine. Under the Eggshell Plaintiff doctrine (PJC 28.8 series), the defendant takes the plaintiff as found. If the collision created a new fissure, extended a pre-existing one, or accelerated previously asymptomatic height loss, the resulting functional impairment and future care are compensable (Texas Pattern Jury Charges). The clinical task is to document that acceleration with objective imaging and a reasoned causation narrative.
Correlating Highway Force Vectors to Structural MRI
A high-speed impact on an El Paso corridor transmits forces in milliseconds. Pure axial compression from a rear-end or frontal collision loads the disc vertically, increasing intradiscal pressure and stressing the annulus. Lateral or oblique impacts (common on Loop 375 and similar highways) add shear and rotational components that preferentially load the posterolateral fibers—the anatomically weakest region of the annulus (NCBI StatPearls, 2023). When those forces exceed tissue tolerance, a radial or transverse fissure forms, nuclear material migrates or dehydrates, and measurable height loss appears at the loaded level.
Key imaging correlates that support causation include:
Single- or dominant-level abnormality matching the predicted segment (commonly L4–L5 or L5–S1 after low-lumbar loading).
Asymmetric high-intensity zone or height reduction greater on the side of the force vector.
Temporal relationship: symptoms beginning immediately or within days, with MRI performed after the collision and compared, when available, to any pre-accident imaging.
Distinction from baseline: the traumatic pattern is focal and asymmetric, while degenerative change is typically multilevel and symmetric.
Clinic notes at Injury Medical Clinic PA capture this linkage in plain language: “The left posterolateral L4–L5 annular high-intensity zone and 2 mm asymmetric disc-height reduction are morphologically and temporally consistent with the lateral shear and rotational forces of the collision. These findings differ from the mild, symmetric multilevel desiccation representing age-related baseline change.” Such statements survive Colossus review and deposition because they rest on biomechanics, not advocacy.
Future-Care Projections That Support Special Damages
Once the mechanism-to-MRI link is established, the same objective findings justify future non-surgical interventions that restore disc hydration and height. Spinal decompression reduces intradiscal pressure, promotes nutrient inflow, and has been shown to improve height and pain in selected lumbar disc cases (Choi et al., 2017). Extracorporeal shockwave therapy (ESWT) stimulates neovascularization and extracellular-matrix remodeling; recent laboratory and clinical observations indicate it can attenuate endplate degeneration under compressive stress and facilitate resorption of herniated material (Frontiers in Bioengineering and Biotechnology, 2026; Orthopedic Reviews case report, 2026).
These modalities are not speculative. When serial MRI or functional testing demonstrates persistent height loss or annular signal that correlates with ongoing symptoms, a future-care spreadsheet listing a defined course of decompression and ESWT is supported by the same causation evidence that proves the injury. The resulting impairment evidence is packaged inside medical-legal causation documentation standards at https://dralexjimenez.com.
Bioethical Integration of Care
Beneficence is realized when chiropractic spinal adjustments, decompression, and ESWT are combined with MD/NP-directed laboratory and imaging oversight to restore structural integrity at the disc level rather than merely mask symptoms. Non-maleficence is achieved by prioritizing these non-invasive, drug-free options, thereby delaying or avoiding the risks of surgery or prolonged opioid exposure. Autonomy places the patient in control of the imaging timeline and treatment decisions. The clinic orders serial MRI scans when clinically indicated, explains results in plain language, and lets the patient coordinate care with any existing medical team.
What Makes the Clinic Unique
Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is the only practice in El Paso, Texas, that integrates a board-certified internal medicine medical director with a dual-licensed chiropractor/nurse practitioner specializing in soft-tissue and disc injury.
Dr. Maria Guadalupe Cardenas, MD (Texas License #J2933, NPI 1164426748), provides medical direction, advanced laboratory panels, and risk stratification for complex metabolic comorbidities that influence disc healing.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP (Texas License #1191402, Prescriptive Authority #59628, NPI 1205907805), delivers structural and regenerative interventions—chiropractic adjustments, spinal decompression, ESWT, and electroacupuncture—while maintaining complete collaborative notes that meet clinical and legal standards. This dual-credentialed, single-clinic model eliminates fragmented records and supplies the continuous, objective documentation attorneys require for Letters of Protection and trial.
Accident reconstruction or black-box data establishing direction and approximate magnitude of force.
Immediate or near-immediate symptom onset recorded in emergency or early clinical notes.
MRI protocol that includes T2 sagittal and axial images with measurements of height loss and description of annular signal laterality.
Comparison to any pre-accident imaging or, in its absence, clear language distinguishing focal traumatic morphology from multilevel degenerative baseline.
Functional testing (range of motion, neurologic exam, patient-reported outcome scores) timed to imaging.
Future-care cost projections tied to the same structural findings that support causation.
When these elements are present, annular tears and disc-height loss stop being defense talking points and become the foundation of special damages. Patients regain mobility and sleep quality through non-invasive care, while attorneys get courtroom-ready proof that the collision—not ordinary aging—caused measurable structural change.
Schedule a comprehensive evaluation at Injury Medical Clinic PA. The team will map the collision’s force vectors to current MRI findings, design a plan to restore disc hydration and height, and prepare the objective documentation needed for trial or settlement.
References
Choi, J., Lee, S., & Hwangbo, G. (2017). Influences of spinal decompression therapy and general traction therapy on the pain, disability, and straight leg raising of patients with intervertebral disc herniation. Journal of Physical Therapy Science, 29(4), 697–699. https://doi.org/10.1589/jpts.29.697
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Rothman, S. L. G., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology, and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Frontiers in Bioengineering and Biotechnology. (2026). ESWT attenuates compressive stress-induced cartilaginous endplate degeneration via modulation of the SOST/Wnt/β-catenin signaling pathway. Frontiers in Bioengineering and Biotechnology, 14, Article 1769920. https://doi.org/10.3389/fbioe.2026.1769920
Texas Pattern Jury Charges—General Negligence, Intentional Personal Torts & Workers’ Compensation. (2024). Committee on Pattern Jury Charges, State Bar of Texas.
Micro-fragmented adipose tissue, or MFAT, is a minimally invasive regenerative treatment. It uses a small amount of a person’s own fat. Mechanical processing cleans the fat and breaks it into tiny pieces, without harsh enzymes or extra chemicals. The finished tissue holds healing cells, growth factors, and a soft natural framework. After a car accident, injuries are often layered. Joints may be misaligned. Ligaments may tear or stretch. Soft tissues may stay swollen and take a long time to heal.
MFAT can be injected into selected joints, tendons, or ligaments to help reduce inflammation and support repair. This article explains what MFAT is, how it is prepared, why auto injuries are complex, and how MFAT works with integrative chiropractic rehabilitation. It also describes the team at Injury Medical Clinic PA in El Paso, Texas, where Dr. Alexander Jimenez provides chiropractic and integrative care and Dr. Maria Guadalupe Cardenas, MD, offers medical direction.
What MFAT Is
MFAT starts with adipose tissue, the medical name for body fat. Fat does more than store energy. It also contains structural tissue, blood-vessel-related cells, signaling cells, and growth factors. In this treatment, a small sample of the patient’s own fat is taken, usually from the abdomen or thigh. The sample is washed and broken into micro-fragments. Those fragments are then placed into an injured joint, tendon, or ligament.
Because the material comes from the same person, the chance of rejection is very low. The goal is to support the local healing environment. MFAT may help calm swelling, add cushion, and send repair signals to nearby tissue.
It does not promise that cartilage will grow back.
It does not replace surgery when a structure is fully torn or unstable.
It is one option for selected injuries that have not settled with basic care.
In plain language, MFAT is the patient’s own tissue, prepared in a limited way, and placed where the body is having trouble healing.
How Mechanical Processing Concentrates Healing Support
The processing step is what sets this treatment apart. The fat is handled in a closed system and reduced in size with mild mechanical force. The process removes oil, excess fluid, and blood residue. The useful tissue stays together. No harsh enzymes are added. No cells are grown in a lab.
A typical visit follows this path:
A clinician reviews the injury, exam findings, and imaging.
A small amount of fat is collected under local anesthesia.
The tissue is washed and micro-fragmented the same day.
The processed tissue is injected, often with ultrasound guidance.
A protection and rehabilitation plan begins after the procedure.
This same-day process is one reason MFAT is called minimally invasive. Most people go home the same day and return to light activity within a few days. Activity then increases under a guided plan.
Why Car Accidents Cause More Than One Problem at a Time
A crash can injure several layers of the body at once. A knee can strike the dashboard. A shoulder can brace against the seat belt. The neck can snap forward and back. Ligaments can stretch. Cartilage can bruise. Muscles can tighten to protect the area. Those changes do not always show up as one simple finding on the first visit.
Common results of auto accidents include:
Joints that no longer move in a smooth, centered way
Ligament tears or sprains that leave the area less stable
Tendon injuries that heal slowly because blood supply is limited
Soft tissues that stay inflamed for weeks or months
Muscle guarding and poor posture that add extra stress
Weakness and balance changes that alter walking, driving, and work tasks
This is why some people still hurt long after the bruise fades. The original tissue injury may remain. The way the body moves may also keep loading that same spot. Older accident injuries can linger as neck pain, low back pain, shoulder or knee pain, stiffness, or reduced motion when those layers are left uncorrected.
Pain medicine may take the edge off symptoms. It does not by itself rebuild tissue or restore motion. That is why an integrative plan looks at both the injured structure and the whole movement pattern.
How MFAT Can Support Auto Injury Recovery
MFAT is usually considered after conservative care has already been tried. That earlier care may include examination, imaging, activity changes, chiropractic care, rehabilitation, and sometimes platelet-rich plasma (PRP). MFAT may be discussed when the injury is more complex, more degenerative, or slower to heal.
When used with an integrative plan, MFAT can address several stages of recovery:
The tissue stage. The injection may reduce local inflammation and support repair inside a joint, tendon, or ligament.
The support stage. The micro-fragments provide a soft scaffold, which can help a worn or injured area feel more cushioned.
The signaling stage. Growth factors and related cells can send repair messages over weeks and months, not only for a few days.
The movement stage. Chiropractic care and rehab then help the body load that tissue more evenly.
The best-studied use is knee osteoarthritis, including cases linked to earlier trauma. Reviews report that some patients have less pain and better function after MFAT. Similar support has been discussed for selected tendon problems, partial soft-tissue tears, and chronic joint irritation. Results vary. When improvement happens, it often builds over weeks to months.
MFAT is not first-line care. It is not a fit for unstable fractures, complete ruptures, active infection, or joints that already need reconstruction. Regenerative treatments used this way are still being studied and are not FDA-approved as a cure for osteoarthritis or tendon injuries. Careful screening matters.
How Integrative Chiropractic Care Fits Into MFAT Treatment
Advanced regenerative medicine and chiropractic rehabilitation work on different parts of the same problem. MFAT supports the biology of the injured tissue. Integrative chiropractic care supports the mechanics of the body around that tissue.
If a joint stays crooked, a hip stays stiff, or the spine keeps moving poorly, the treated area can remain under extra load. Chiropractic adjustments, soft-tissue treatment, posture work, and guided exercise help restore cleaner motion. Rehabilitation then rebuilds strength, balance, and daily function so healing tissue isn’t overloaded.
A clear combined plan often moves through these stages:
Evaluation first. The team identifies the injured tissue and the movement problems that keep stressing it.
Early protection. After MFAT, the injection site needs time. Heavy loading is avoided.
Guided motion. Gentle chiropractic care and light exercise restore range without forcing the area.
Strength and control. Rehab adds stability so work, driving, and home tasks are safer.
Return to function. Care then focuses on lasting mechanics and injury prevention.
This pairing covers several levels of recovery at once: tissue quality, joint position, muscle balance, and whole-body movement. Direct trials of “MFAT plus chiropractic” are still limited, so the combination is based on complementary roles, not on a claim that the pair is proven better than MFAT alone.
A Multidisciplinary Team in El Paso
At Injury Medical Clinic PA in El Paso, Texas, care is built as a coordinated plan rather than a single procedure. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides integrative chiropractic care, family nurse practitioner services, functional medicine, personal injury evaluation, and rehabilitation planning. That mix is useful after auto accidents because the same patient may need spinal care, soft-tissue rehab, injury documentation, and a plan that also looks at sleep, nutrition, and inflammation.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine and has more than 40 years of experience as an internist. She works with Dr. Alex Jimenez, DC, and serves as the medical director and collaborative physician at Injury Medical Clinic PA. Her NPI is #1164426749, and her Texas MD license is #J2933. In this model, the MD provides medical direction, health screening, and oversight. The chiropractic and rehabilitation team restores motion and function. This multidisciplinary setup is common in integrative or injury care clinics, where an MD provides medical direction alongside a chiropractor.
The team integrates several services into one path:
Chiropractic care from Dr. Jimenez for spinal and joint mechanics
Medical oversight from Dr. Cardenas in internal medicine
Functional medicine support for inflammation, nutrition, sleep, and recovery
Personal injury evaluation and documentation after auto accidents
Rehabilitation and return-to-activity planning
Related services that support whole-person healing
This matters after a crash because the injured joint is rarely the only issue. Body-wide inflammation, poor sleep, blood-sugar stress, or missed medical problems can slow tissue repair. Medical review and chiropractic care can sit side by side instead of sending the patient through disconnected offices.
Clinical Observations From Dr. Alexander Jimenez
Dr. Jimenez has observed that auto-injury patients often present with layered problems. A painful knee may also come with limited hip motion, guarded spinal movement, weak core control, and a walking pattern that keeps twisting the same ligament. Treating only the local tissue can leave those extra forces in place.
His clinical approach asks a simple question: why is this area still hurting? Possible answers include poor alignment, incomplete soft-tissue healing, leftover swelling, nerve irritation, or daily habits that continue to stress the injury. In that view:
MFAT may support the tissue environment.
Chiropractic care may improve motion and reduce compensation.
Rehabilitation may prepare the area for real-life loading.
Functional medicine may address nutrition, inflammation, and recovery capacity.
These observations come from integrated clinical practice in El Paso and from educational posts on his clinical sites and professional profile. Read them as practice-based insight. They are not the same as a controlled trial that proves one exact combination works for every accident injury.
Who May Be Considered and What Recovery Can Look Like
People who may be candidates often have moderate joint damage, a cartilage problem that still causes swelling or catching, a larger partial tendon tear, or a chronic soft-tissue injury that did not settle after therapy or simpler injections. People who are usually not candidates include those with complete tears, unstable fractures, infection, or advanced destruction that already needs surgery.
If MFAT is appropriate, patients should expect a full work-up first. After the procedure, light activity often returns quickly. Structured rehab follows a short protection period. Pain and function, if they improve, usually change over weeks to months. Progress is tracked with motion, strength, swelling, work ability, and daily tasks.
No injection replaces good diagnosis, better mechanics, and follow-through. The strongest plan uses regenerative support when the tissue needs it and chiropractic rehabilitation when the body keeps moving in a way that reloads the injury.
Final Thoughts
MFAT is a minimally invasive regenerative procedure made from a small amount of a patient’s own fat. Mechanical processing concentrates healing cells and growth factors without harsh enzymes or chemicals. After a car accident, this biologic support may help selected joints, tendons, and ligaments calm down and repair more effectively.
Integrative chiropractic care completes the picture by restoring alignment, motion, and strength. At Injury Medical Clinic PA in El Paso, Dr. Jimenez and Dr. Cardenas work within a multidisciplinary model that also includes functional medicine, personal injury care, and rehabilitation. Together, these layers address both the injured tissue and how the whole body moves.
Anyone with lingering pain after an auto accident should get a complete evaluation from a qualified team. That visit can sort out whether continued conservative care, rehabilitation, MFAT, or another option is the safest next step. This article is for education only and is not personal medical advice.
Overlooked Injuries After Work and Auto Accidents: Why X-Rays Often Miss Them
Abstract: Soft-tissue damage, mild concussions, and hairline spinal issues are among the most frequently overlooked injuries after workplace incidents and motor vehicle accidents (MVAs). These problems often lack immediate, visible signs and do not appear on standard X-rays. This article explains why micro-tears in spinal ligaments, subtle annular tears in discs, hidden facet joint capsule trauma, and chronic myofascial trigger points are so often missed. It describes how untreated damage can lead to lasting pain. It then shows how an integrative approach that combines mechanical restoration through chiropractic care with biological tissue repair can support better recovery. Clinical observations from Dr. Alexander Jimenez and the collaborative team at Injury Medical Clinic PA in El Paso, Texas, illustrate how this model works.
A person can walk away from a crash or a workplace incident feeling only somewhat sore. The first exam often looks for broken bones, bleeding, and other obvious emergencies. When the X-rays look normal, many people receive reassurance that they are fine. Days or weeks later, neck stiffness, headaches, back pain, or trouble concentrating can develop and persist. These delayed symptoms are common. They often come from injuries that standard films cannot show.
Right after trauma, adrenaline hides pain. Inflammation then builds slowly. Soft tissues can stretch or tear without breaking bone. That is why so many injuries after MVAs and workplace events stay hidden at first. If they go undiagnosed, they can leave people with persistent discomfort and reduced daily function.
Why Standard X-Rays Miss These Injuries
X-rays are useful for bones. They show fractures and major joint problems. They do not show muscles, ligaments, tendons, fascia, joint capsules, or the outer layers of spinal discs. Mild concussions also leave little clear mark on routine scans. The injury can still be real even when the pictures look clean.
After a collision, the body is thrown forward and then stopped. Ligaments and joint capsules can be stretched past their safe limit. Disc fibers can develop small cracks. Deep muscles can form tight, painful knots. Workplace injuries can follow the same path after a sudden lift, a fall, or months of repetitive strain. Because symptoms often start later, people may assume the pain is only ordinary muscle tightness.
The Injuries Most Often Overlooked After Crashes and Work Events
Several specific problems recur when a more complete evaluation is done.
Micro-tears in spinal ligaments: Ligaments hold the vertebrae in place. Sudden force can create tiny tears that allow slight extra motion. The spine may feel unstable even when X-rays look perfect. People notice stiffness after sitting, pain with certain movements, or a sense that the back “becomes unstable.”
Subtle annular tears in intervertebral discs: The tough outer ring of a disc can crack without a full herniation. These tears can irritate nearby nerves. Pain may travel into an arm or a leg days later. Early tears are easy to miss on routine imaging.
Hidden facet joint capsule trauma: Facet joints guide how the spine bends and twists. Their capsules can stretch or partially tear. This can cause local pain, reduced motion, and headaches. Standard films rarely capture this soft-tissue damage.
Chronic myofascial trigger points: Trauma can create tight bands in deep stabilizing muscles. These knots send pain to other areas. Headaches, shoulder tightness, or low-back discomfort may actually start in these guarded muscles.
Mild concussions are another frequent miss. The brain can move inside the skull even without a direct blow to the head. Symptoms such as foggy thinking, poor concentration, light sensitivity, or mood changes may appear later. A normal scan rules out large bleeding. It does not prove the brain is uninjured.
Workplace injuries often develop in two ways. One is a single event, such as a fall or a sudden lift. The other is cumulative trauma from repeated motions, awkward postures, or vibration. Tendon irritation, shoulder strain, and low-back tightness can build slowly. Because there is no single dramatic moment, these injuries are easy to overlook until function is already limited.
What Happens When These Injuries Stay Untreated
The body tries to protect itself. Muscles tighten around unstable segments. Posture and walking patterns change. Circulation drops in the guarded areas. Scar tissue can form in a less organized way. Over time, the nervous system can become more sensitive to pain. A treatable soft-tissue injury can then settle into chronic pain, reduced movement, and trouble returning to work or daily tasks.
Early, thorough evaluation changes that path. A clear history of how the injury happened, a careful hands-on exam of joint motion and muscle texture, and selected advanced tests can reveal the real sources of symptoms.
An Integrative Approach: Mechanical Restoration Plus Biological Tissue Repair
Recovery works best when two goals are met together. First, the mechanical environment must improve. Joints need proper motion. Muscles need balanced length and strength. Movement patterns need retraining so healing tissue isn’t constantly re-stressed. Second, damaged soft tissues need biological support to rebuild stronger collagen and quiet leftover inflammation.
Integrative chiropractic care addresses the mechanical side. Specific adjustments restore joint motion and reduce extra load on injured segments. Soft-tissue work releases guarded muscles and improves local blood flow. Corrective exercises rebuild strength and coordination. When it is appropriate, spinal decompression can reduce pressure on discs and nerves. These steps create a better setting for repair.
Biological tissue support may include regenerative options such as platelet-rich plasma or related plasma products when clinically appropriate. These approaches use the patient’s own growth factors to help ligaments, tendons, and other soft tissues heal. Mechanical correction and biological support together aim at lasting function, not only short-term relief.
How the El Paso Team Applies This Model
Clinical observations from Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, note that patients with overlooked soft-tissue and joint injuries often develop secondary changes in posture, gait, and spinal motion. Treating only the most painful spot can leave those broader patterns in place and slow recovery. A complete assessment that includes biomechanics, nerve function, and movement helps build a more complete plan.
At Injury Medical Clinic PA in El Paso, Texas, care follows a multidisciplinary structure. Dr. Jimenez provides chiropractic care, functional medicine insight, personal injury evaluation, and rehabilitation planning. Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), serves as Medical Director and Collaborative Physician. With more than 40 years of experience as an internist, she provides medical oversight and diagnostic direction.
This setup is common in integrative and injury-focused clinics: an MD supplies medical direction while a chiropractor focuses on spinal mechanics, movement, and hands-on restoration. The team integrates chiropractic adjustments and soft-tissue care with medical evaluation, functional medicine strategies, personal injury documentation, and progressive rehabilitation. Patients receive one coordinated plan rather than isolated treatments.
A Clear Next Step After a Crash or Workplace Injury
If pain, stiffness, headaches, or concentration problems linger after a motor vehicle accident or workplace incident—even when early X-rays were normal—further evaluation is reasonable. Soft-tissue damage, mild concussions, and small spinal issues are real. They respond best when they are found early and treated with both mechanical correction and support for biological healing.
An integrative model that pairs chiropractic care for joint and soft-tissue function with medical oversight, functional strategies, and rehabilitation offers a practical path. In the collaborative setting of Injury Medical Clinic PA, chiropractic expertise and internal medicine direction work together to help people move from hidden injury toward better daily function.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine