Progress can be challenging for individuals in post total ankle replacement surgery. How can physical therapy help in recovery and restoring leg function?
Total Ankle Replacement Post Surgery Physical Therapy
Total ankle replacement surgery is a major procedure that takes time to recover. A total ankle replacement surgery or arthroplasty can benefit individuals with chronic ankle pain or disability. This procedure can significantly improve an individual’s overall pain and function with time. Physical therapy is essential to regaining movement in the ankle and restoring full mobility. A physical therapist will work with the individual to control pain and swelling, restore the ankle’s range of motion, train on walking gait and balance, and rebuild strength in the leg. This will help maximize the chances of a successful outcome after surgery.
Total Ankle Replacement
The ankle joint is the section of the lower leg where the shinbone/tibia meets the talus bone on the top of the foot. What can happen is the slippery surface/articular cartilage that coats the ends of these bones begins to thin or deteriorate. As the deterioration progresses, it can lead to significant pain, disability, and difficulty walking. (Cleveland Clinic. 2021) This is where a specialist may recommend total ankle replacement for the best results. Various conditions can be helped by this procedure, including:
During an ankle replacement procedure, an orthopedic surgeon removes the damaged ends of the tibia and talus bones and replaces them with an artificial covering. A polyethylene component is also secured between the two structures to support the smooth movement of the new joint endings. (Massachusetts General Hospital. N.D.) Following the procedure, individuals are typically placed in a protective boot or splint. The healthcare provider will recommend staying off the leg for 4 to 8 weeks to allow healing.
Physical Therapy
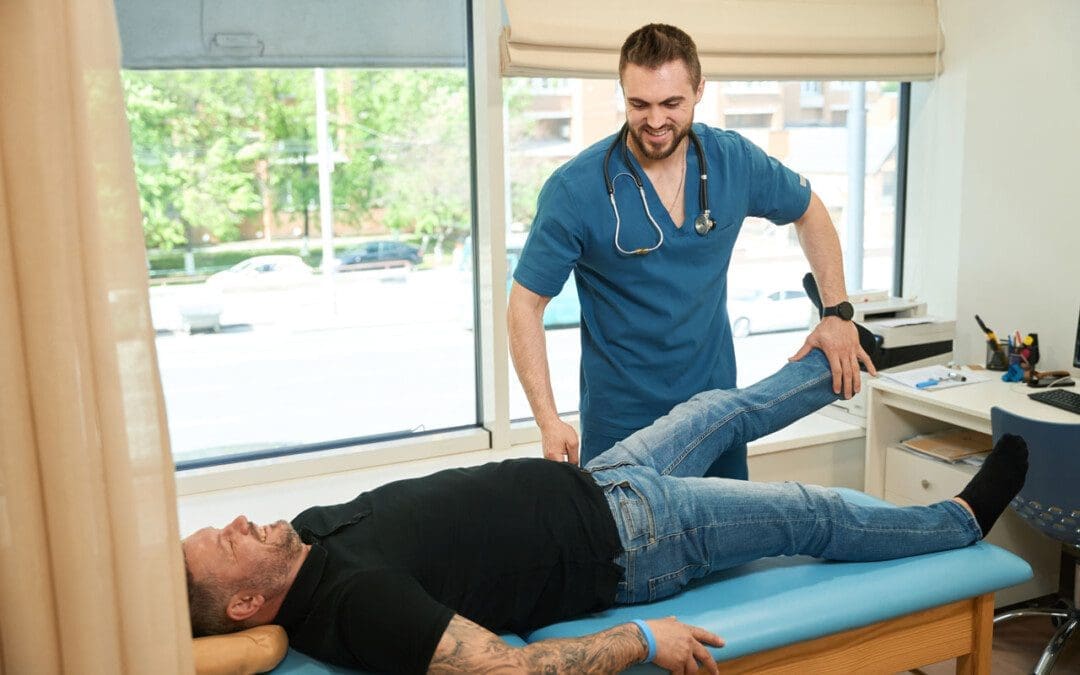
Outpatient physical therapy is usually initiated several weeks after the ankle operation. (UW Health Orthopedics and Rehabilitation. 2018) Physical therapy can last for five months or more, depending on the severity of the condition and injury. The physical therapist will focus on different areas to get the best results. (Cort D. Lawton et al., 2017)
Pain and Swelling Control
Post-operative pain and swelling are normal after a total ankle replacement. It is not unusual for an ankle to be swollen for even six to 12 months after the operation. (UW Health Orthopedics and Rehabilitation. 2018) The surgeon will normally prescribe medication to help manage discomfort early on, and physical therapy also plays an important role in addressing the symptoms. Treatments used can include:
Electrical stimulation – mild electrical pulses applied to the muscles.
Ice
Vasopneumatic compression, where an inflatable sleeve is used to create pressure around the area, is commonly utilized at the beginning of physical therapy to reduce pain or swelling.
Other modalities, such as stretching and targeted exercises, are combined with other treatments.
Range of Motion
Early after the procedure, the ankle will be very stiff and tight. This is due to several factors, including the inflammation and swelling after surgery and the time spent immobilized in a boot.
The physical therapist will employ various techniques to improve the ankle joint’s range of motion to rotate and flex.
The physical therapist may employ passive stretching induced by an outside force such as the therapist or a resistance band) to help improve mobility.
After multiple weeks of reduced movement and lack of bearing any weight on the ankle, the muscles that surround the ankle have often atrophied/weakened, which can impact balance.
When the individual can begin placing weight on the leg, the therapist will apply proprioceptive/sense of body position training to improve overall stability. (UW Health Orthopedics and Rehabilitation. 2018)
Balance exercises will be added to the home program and will progress from week to week.
Strength
The muscles in the leg, ankle, and foot become weak from the surgery and the time spent in a splint or boot. These structures have a significant role in balance, the ability to stand, walk, and go up or down the stairs.
Regaining the strength and power of these muscles is a critical goal of rehabilitation.
In the first weeks, the physical therapist will focus on gentle strengthening exercises.
Isometrics lightly activate the muscles but avoid irritating the surgical site.
As time passes and weight-bearing is allowed, these gentle moves are replaced with more challenging ones, like resistance bands and standing exercises, to accelerate strength gains.
Lawton, C. D., Butler, B. A., Dekker, R. G., 2nd, Prescott, A., & Kadakia, A. R. (2017). Total ankle arthroplasty versus ankle arthrodesis-a comparison of outcomes over the last decade. Journal of orthopaedic surgery and research, 12(1), 76. https://doi.org/10.1186/s13018-017-0576-1
For individuals affected by headaches that occur 15 or more days a month for more than three months, can knowing the signs and symptoms help healthcare providers help treat and prevent chronic tension headaches?
Chronic Tension Headaches
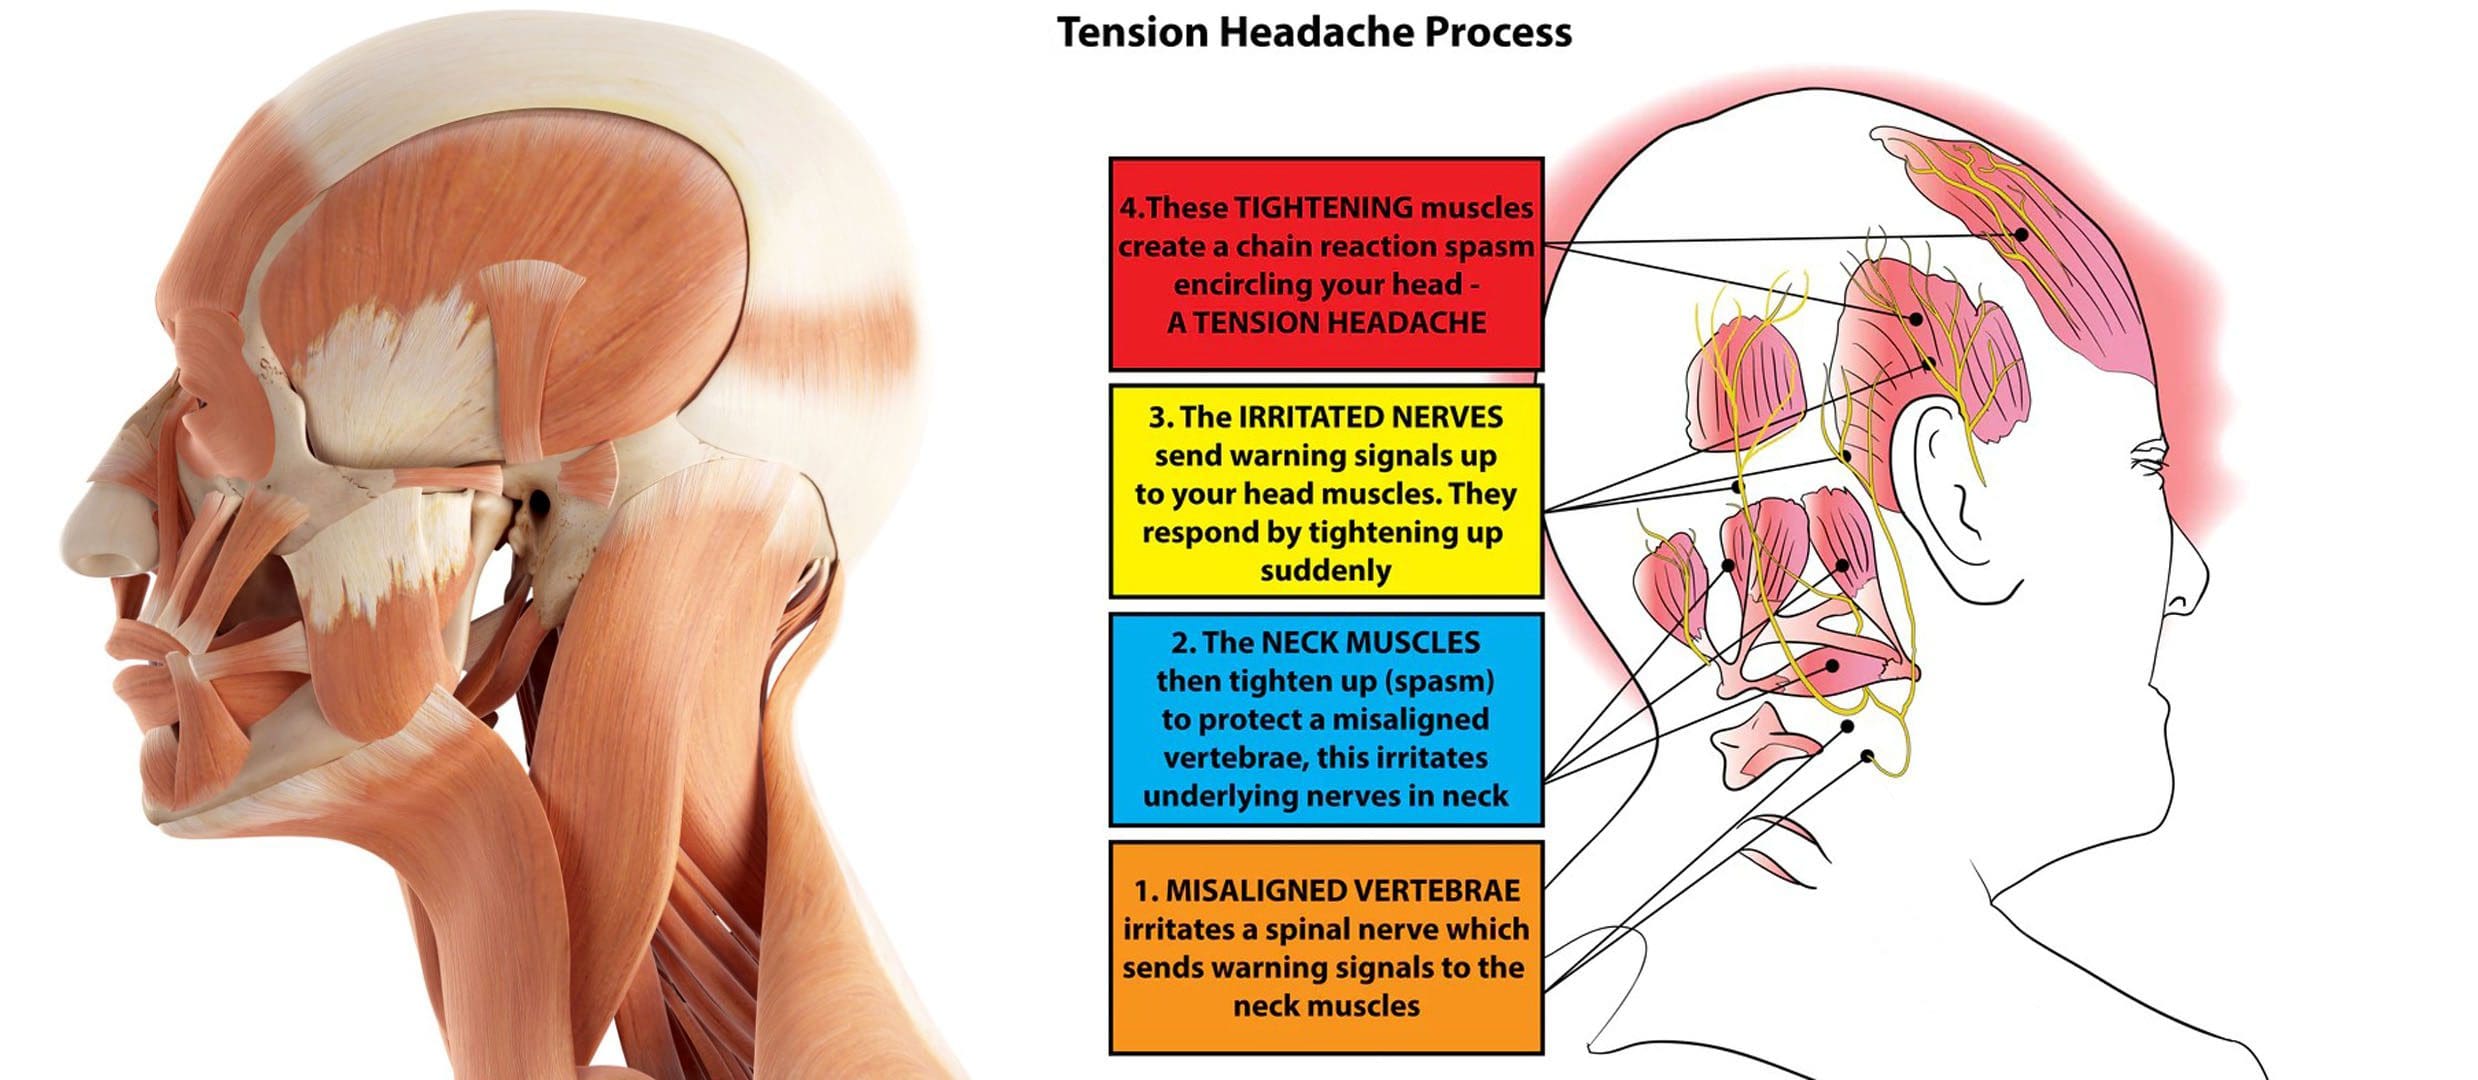
Most individuals have experienced a tension-type headache. The pain is usually described as a dull tightening or pressure on both sides of the head, like having a tightening band around the head. Some individuals experience these headaches frequently, a condition known as chronic tension headaches. Chronic tension headaches are uncommon but can be debilitating, as they can interfere with a healthy quality of life and daily living.
Tension headaches are typically caused by stress, anxiety, dehydration, fasting, or lack of sleep and usually resolve with over-the-counter medications. (Cleveland Clinic. 2023)
This is a primary headache disorder that affects around 3% of the population.
Chronic tension headaches can occur daily and negatively impact the quality of life and daily functioning. (Cleveland Clinic. 2023)
Symptoms
Tension headaches can be referred to as stress headaches or muscle contraction headaches.
They can present with dull, aching pain and include tightness or pressure across the forehead, sides, or back of the head. (Cleveland Clinic. 2023)
Additionally, some individuals experience tenderness on the scalp, neck, and shoulders.
Chronic tension headaches materialize 15 or more days a month on average for more than three months.
The headache can last for several hours or be continuous for several days.
Causes
Tension headaches are typically caused by tight muscles in the shoulders, neck, jaw, and scalp.
Teeth grinding/bruxism and jaw clenching can also contribute to the condition.
Headaches can be brought on by stress, depression, or anxiety and are more common in individuals who:
Individuals experiencing headaches that interfere with daily life or need to take medication more than twice a week are recommended to consult a healthcare provider. Before the appointment, it can be helpful to keep a headache diary:
Record the days
Times
Description of the pain, intensity, and other symptoms.
Some questions the healthcare provider may ask include:
Is the pain pulsating, sharp, or stabbing, or is it constant and dull?
Where is the pain most intense?
Is it all over the head, on one side, on the forehead, or behind the eyes?
Do the headaches interfere with sleep?
Is working or doing tasks difficult or impossible?
A healthcare provider will likely be able to diagnose the condition based on symptoms alone. However, if the headache pattern is unique or different, the provider may order imaging tests, like MRI or CT scans, to rule out other diagnoses. Chronic tension headaches can be confused with other chronic daily headache disorders like chronic migraine, hemicrania continua, temporomandibular joint dysfunction/TMJ, or cluster headaches. (Fayyaz Ahmed. 2012)
Treatment
Pharmacological therapy for chronic tension headaches usually involves preventive medication.
Amitriptyline is one medication that has been found to be beneficial in chronic tension headache prevention.
According to a meta-analysis of 22 published studies in the Journal of General Internal Medicine, these medications are superior to placebo in reducing headache frequency, with an average of 4.8 fewer headache days per month.
Additional preventive medications may include other antidepressants like:
Remeron – mirtazapine.
Anti-seizure medications – like Neurontin – gabapentin, or Topamax – topiramate.
A healthcare provider may also prescribe medication to treat headache episodes, which include:
Prescription non-steroidal anti-inflammatory drugs or NSAIDs, including acetaminophen, naproxen, indomethacin, or ketorolac.
Opiates
Muscle relaxants
Benzodiazepines – Valium
Non-Medication Treatment
Behavioral therapies are sometimes used on their own or in combination with medication to prevent and manage chronic tension headaches. Examples include:
Acupuncture
An alternative therapy that involves using needles to stimulate specific points on the body believed to connect with certain pathways/meridians that carry vital energy/chi throughout the body.
Biofeedback
In Electromyography – EMG biofeedback, electrodes are placed on the scalp, neck, and upper body to detect muscle contraction.
The process can be costly and time-consuming, and there is little evidence to support its effectiveness.
Physical Therapy
A physical therapist can work out stiff and tight muscles.
Train individuals on stretches and targeted exercises for loosening tight head and neck muscles.
Cognitive Behavioral Therapy/CBT
Involves learning how to identify headache triggers and cope in a less stressful and more adaptive way.
Headache specialists often recommend CBT in addition to medication when developing a treatment plan. (Katrin Probyn et al., 2017)
Teeth-grinding and jaw-clenching training/treatment can help when they are contributors.
Regular exercise, as well as practicing healthy sleep hygiene, can be beneficial in prevention.
Supplements
Some individuals with chronic tension headaches may find relief using supplements. The American Academy of Neurology and the American Headache Society report the following supplements can be effective: (National Center for Complementary and Integrative Health. 2021)
Butterbur
Feverfew
Magnesium
Riboflavin
If the headaches come on suddenly, cause waking up from sleep, or last for days, it’s important to consult a healthcare provider to rule out any underlying causes and develop a personalized treatment plan.
Ahmed F. (2012). Headache disorders: differentiating and managing the common subtypes. British journal of pain, 6(3), 124–132. https://doi.org/10.1177/2049463712459691
Jackson, J. L., Mancuso, J. M., Nickoloff, S., Bernstein, R., & Kay, C. (2017). Tricyclic and Tetracyclic Antidepressants for the Prevention of Frequent Episodic or Chronic Tension-Type Headache in Adults: A Systematic Review and Meta-Analysis. Journal of general internal medicine, 32(12), 1351–1358. https://doi.org/10.1007/s11606-017-4121-z
Probyn, K., Bowers, H., Mistry, D., Caldwell, F., Underwood, M., Patel, S., Sandhu, H. K., Matharu, M., Pincus, T., & CHESS team. (2017). Non-pharmacological self-management for people living with migraine or tension-type headache: a systematic review including analysis of intervention components. BMJ open, 7(8), e016670. https://doi.org/10.1136/bmjopen-2017-016670
Individuals that have gone through a back injury may develop a synovial spinal cyst as a way to protect the spine that could cause pain symptoms and sensations. Can knowing the signs help healthcare providers develop a thorough treatment plan to relieve pain, prevent worsening of the condition and other spinal conditions?
Spinal Synovial Cysts
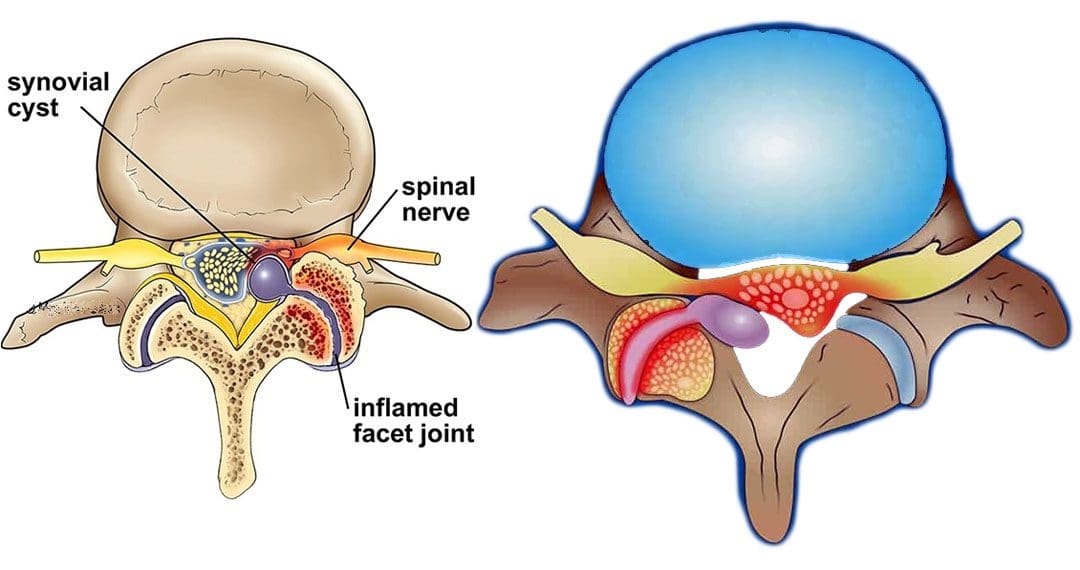
Spinal synovial cysts are benign fluid-filled sacs that develop in the spine’s joints. They form because of spinal degeneration or injury. The cysts can form anywhere in the spine, but most occur in the lumbar region/lower back. They typically develop in the facet joints or junctions that keep the vertebrae/spinal bones interlocked.
Symptoms
In most cases, synovial cysts don’t cause symptoms. However, the doctor or specialist will want to monitor for signs of degenerative disc disease, spinal stenosis, or cauda equina syndrome. When symptoms do present, they typically cause radiculopathy or nerve compression, which can cause back pain, weakness, numbness, and radiating pain caused by the irritation. The severity of symptoms depends on the size and location of the cyst. Synovial cysts can affect one side of the spine or both and can form at one spinal segment or at multiple levels.
Effects Can Include
Radiculopathy symptoms can develop if the cyst or inflammation caused by the cyst comes into contact with a spinal nerve root. This can cause sciatica, weakness, numbness, or difficulty controlling certain muscles.
Neurogenic claudication/impingement and inflammation of spinal nerves can cause cramping, pain, and/or tingling in the lower back, legs, hips, and buttocks. (Martin J. Wilby et al., 2009)
If the spinal cord is involved, it may cause myelopathy/severe spinal cord compression that can cause numbness, weakness, and balance problems. (Dong Shin Kim et al., 2014)
Symptoms related to cauda equina, including bowel and/or bladder problems, leg weakness, and saddle anesthesia/loss of sensation in the thighs, buttocks, and perineum, can present but are rare, as are synovial cysts in the middle back and neck. If thoracic and cervical synovial cysts develop, they can cause symptoms like numbness, tingling, pain, or weakness in the affected area.
Causes
Spinal synovial cysts are generally caused by degenerative changes like osteoarthritis that develop in a joint over time. With regular wear and tear, facet joint cartilage/the material in a joint that provides protection, a smooth surface, friction reduction, and shock absorption begins to waste away. As the process continues, the synovium can form a cyst.
Traumas, large and small, have inflammatory and degenerative effects on joints that can result in the formation of a cyst.
Around a third of individuals who have a spinal synovial cyst also have spondylolisthesis.
This condition is when a vertebrae slips out of place or out of alignment onto the vertebra underneath.
It is a sign of spinal instability.
Instability can occur in any spine area, but L4-5 are the most common levels.
This segment of the spine takes most of the upper body weight.
Epidural corticosteroid injections can reduce inflammation and could be an option to relieve pain.
Patients are recommended to receive no more than three injections per year.
Surgical Options
For severe or persistent cases, a doctor may recommend decompression surgery to remove the cyst and surrounding bone to relieve pressure on the nerve root. Surgical options range from minimally invasive endoscopic procedures to larger, open surgeries. The best surgical option varies based on the severity of the situation and whether associated disorders are present. Surgical options include:
Laminectomy – Removal of the bony structure that protects and covers the spinal canal/lamina.
Hemilaminectomy – A modified laminectomy where a smaller portion of the lamina is removed.
Facetectomy – The removal of part of the affected facet joint where the synovial cyst is located, usually following a laminectomy or hemilaminectomy.
Fusionof the facet joints and vertebra – Decreases vertebral mobility in the injured area.
Most individuals experience immediate pain relief following a laminectomy or hemilaminectomy.
Fusion can take six to nine months to heal completely.
If surgery is performed without fusion where the cyst originated, the pain could return, and another cyst could form within two years.
Surgery Complications include infection, bleeding, and injury to the spinal cord or nerve root.
How I Gained My Mobility Back With Chiropractic
References
Wilby, M. J., Fraser, R. D., Vernon-Roberts, B., & Moore, R. J. (2009). The prevalence and pathogenesis of synovial cysts within the ligamentum flavum in patients with lumbar spinal stenosis and radiculopathy. Spine, 34(23), 2518–2524. https://doi.org/10.1097/BRS.0b013e3181b22bd0
Kim, D. S., Yang, J. S., Cho, Y. J., & Kang, S. H. (2014). Acute myelopathy caused by a cervical synovial cyst. Journal of Korean Neurosurgical Society, 56(1), 55–57. https://doi.org/10.3340/jkns.2014.56.1.55
Epstein, N. E., & Baisden, J. (2012). The diagnosis and management of synovial cysts: Efficacy of surgery versus cyst aspiration. Surgical neurology international, 3(Suppl 3), S157–S166. https://doi.org/10.4103/2152-7806.98576
For individuals looking to spice up their diet, can jalapeño peppers provide nutrition, and be a good source of vitamins?
Jalapeño Pepper Nutrition
Jalapeños are one of many types of chili peppers that are used to accent or garnish and add heat to a dish. This pepper variety is generally harvested and sold when it is a glossy dark green but turns red as it matures. The following nutrition information for one 14-gram jalapeño pepper. (FoodData Central. U.S. Department of Agriculture. 2018)
Jalapeño peppers contain very little carbohydrates and cannot be tested with the standard GI methodology. (Fiona S. Atkinson et al., 2008)
6 grams of carbohydrates in 1-cup serving has an extremely low glycemic load, meaning the peppers do not raise blood sugar levels rapidly or provoke an insulin response. (Mary-Jon Ludy et al., 2012)
Fat
Jalapeños have a trace amount of fat that is mostly unsaturated.
Protein
The peppers are not a recommended source of protein, as they contain less than a gram of protein in a full cup of sliced jalapeños.
Vitamins and Minerals
One pepper contains about 16 milligrams of vitamin C, about 18% of the recommended daily allowance/RDA.
Jalapeños are a good source of vitamin A, which supports skin and eye health.
In 1/4 cup sliced jalapeño peppers, individuals acquire around 8% of the recommended daily amount of vitamin A for men and 12% for women.
Jalapeños are also a source of vitamins B6, K, and E.
Health Benefits
Many health benefits have been attributed to capsaicin which is the substance that generates the heat in the peppers, including alleviating pain and itching by blocking a neuropeptide that transmits those signals to the brain. (Andrew Chang et al., 2023)
Pain Relief
Research shows capsaicin – supplements or topical ointments/creams – can relieve nerve and joint pain. (Andrew Chang et al., 2023)
Lower the Risk of Heart Disease
A study of individuals with low levels of healthy HDL cholesterol, who are at risk of coronary heart disease/CHD, showed that capsaicin supplements improved risk factors for CHD. (Yu Qin et al., 2017)
Reduce Inflammation
The vitamin C in the peppers acts as an antioxidant, which means it can repair cells damaged by oxidative stress and reduce inflammation.
They can be consumed raw, pickled, canned, or smoked/chipotle peppers and are hotter than fresh or canned because they are dried and treated.
Storage and Safety
Fresh jalapeños can be stored at room temperature for a few days or in the refrigerator for about a week.
Once a jar is opened, keep it in the refrigerator.
For an open can of peppers, transfer to a glass or plastic container for refrigerator storage.
Peppers can be frozen after preparing by cutting off the stems and scooping out the seeds.
Frozen jalapeños are best within 6 months for the best quality, but can be kept for much longer.
Preparation
Removing the seeds can help reduce the heat.
Jalapeños can be eaten whole or sliced and added to salads, marinades, salsa, or cheeses.
Some add jalapeños to smoothies for a spicy kick.
They can be used in various recipes for added heat and tanginess.
Chiropractic, Fitness, and Nutrition
References
FoodData Central. U.S. Department of Agriculture. (2018). Peppers, jalapeno, raw.
Atkinson, F. S., Foster-Powell, K., & Brand-Miller, J. C. (2008). International tables of glycemic index and glycemic load values: 2008. Diabetes care, 31(12), 2281–2283. https://doi.org/10.2337/dc08-1239
Ludy, M. J., Moore, G. E., & Mattes, R. D. (2012). The effects of capsaicin and capsiate on energy balance: critical review and meta-analyses of studies in humans. Chemical senses, 37(2), 103–121. https://doi.org/10.1093/chemse/bjr100
National Institutes of Health Office of Dietary Supplements. (2021). Vitamin C: Fact Sheet for Health Professionals.
Chang A, Rosani A, Quick J. Capsaicin. [Updated 2023 May 23]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2023 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK459168/
Qin, Y., Ran, L., Wang, J., Yu, L., Lang, H. D., Wang, X. L., Mi, M. T., & Zhu, J. D. (2017). Capsaicin Supplementation Improved Risk Factors of Coronary Heart Disease in Individuals with Low HDL-C Levels. Nutrients, 9(9), 1037. https://doi.org/10.3390/nu9091037
American Academy of Allergy Asthma and Immunology. (2017). Ask the Expert: Pepper Allergy.
Individuals with neck and shoulder pain may experience what feels like tightened lumps or knots in and around the muscles where the neck and shoulder meet. Can using kinesiology tape for neck and shoulder trigger points help to loosen and release them, restore function, and bring pain relief?
Kinesiology Tape For Neck and Shoulder Trigger Points
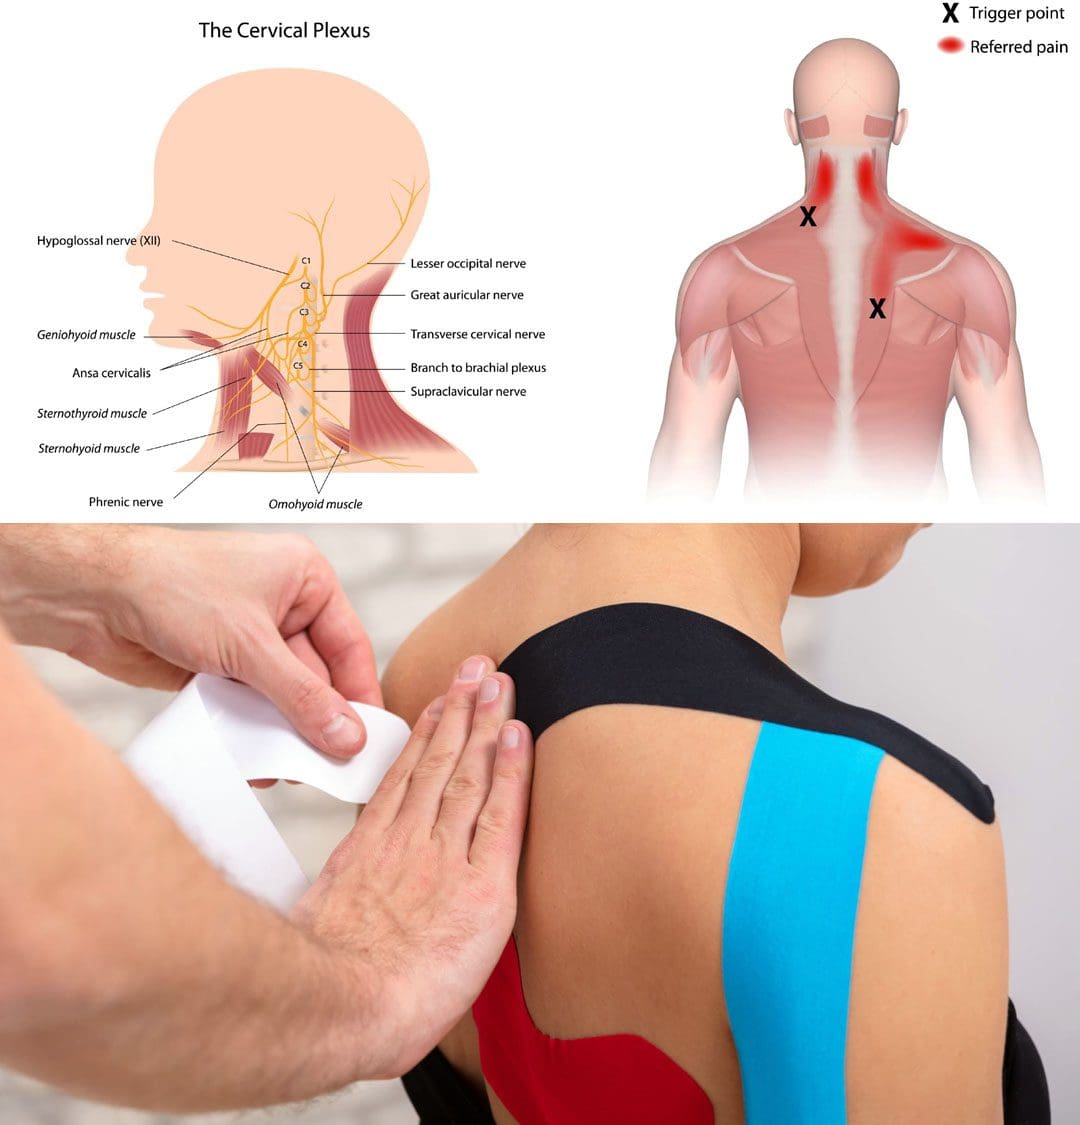
The upper trapezius and levator scapula muscles are where the shoulder and neck come together and are often the location of trigger point formations. These trigger points can cause tension, pain, and muscular spasms in the neck and shoulders. Various treatments for releasing trigger points and alleviating the pain symptoms include therapeutic massage, trigger point release, and chiropractic adjustments in a multidisciplinary treatment approach.
Electrical stimulation and ultrasound have often been used to break up the knots, but scientific evidence has shown that these treatments alone are not the most effective. (David O. Draper et al., 2010)
Stretching the neck muscles can bring tension relief and help release the knots.
Kinesiology tape can decrease the pain and spasms and help to release the trigger points.
Therapy
Using kinesiology tape is a form of physical therapy that can be used in various ways.
The tape helps lift the upper tissues from underlying tissues to increase circulation and release muscular spasms.
It can help improve muscular contractions, decrease swelling, and inhibit pain in injured tissues.
Helps stop the trigger points and knots from worsening.
The tape can also be used for managing lymphedema.
Usage
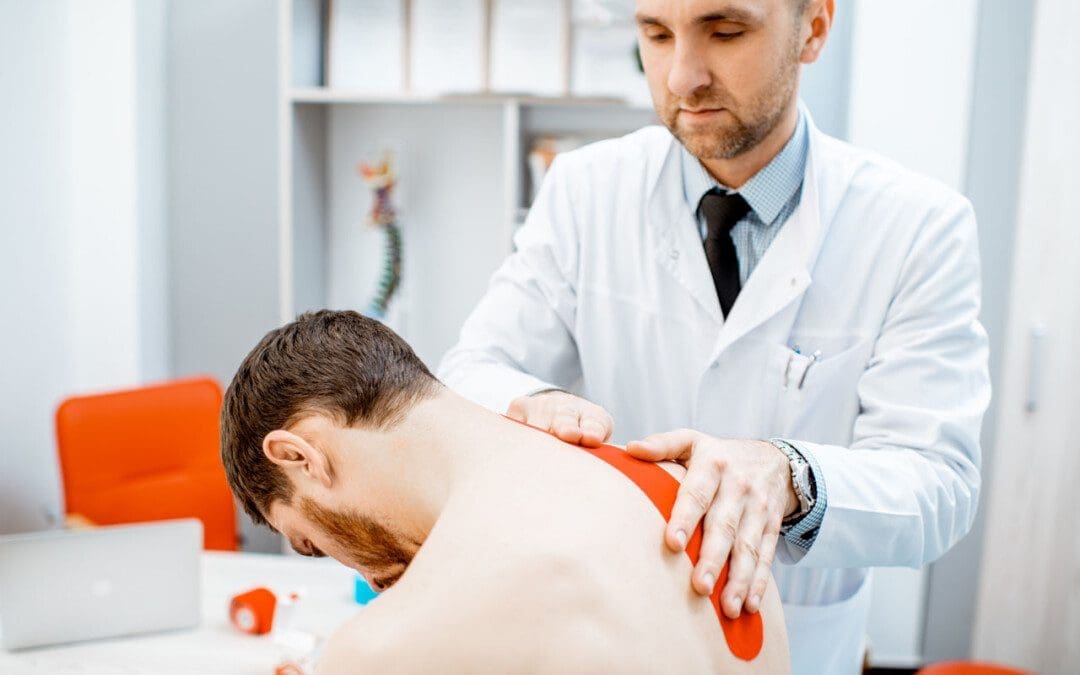
To decrease trigger points, individuals can use a specific kinesiology tape strip called a lift strip. Individuals can consult their healthcare provider or physical therapist to show them the various types of strips to learn how to cut them properly.
Before using kinesiology tape, consult a healthcare provider or physical therapist to assess the injury and situation.
Kinesiology tape is not for everyone, and some people have conditions where the use of kinesiology tape should be avoided altogether.
A therapist can evaluate the neck pain and trigger points to determine if the individual should use kinesiology tape.
To use kinesiology tape for neck and shoulder trigger points:
Get comfortable with the neck and shoulders exposed.
Cut one lift strip for each side of the neck, if necessary.
The lift strip should be around 3 to 4 inches long.
Remove the paper backing in the center with the exposed tape in the center, which should look like a band-aid.
Both ends of the lift strip should still have the paper backing on.
Stretch out the kinesiology tape.
Place the stretched tape directly over the trigger points in the upper shoulder area.
Remove the backing on either side of the lift strip and place the ends on without stretching.
Gently rub the tape to help the adhesive adhere.
Once the tape has been applied, it can be left there for 2 to 5 days.
It’s ok if it gets wet with a bath or shower.
Monitor the skin around the tape to watch for redness or other signs of a negative reaction to the tape.
Kinesiology taping can be a useful tool to decrease pain and spasms but does not replace professional treatment, prescribed exercises and stretches, and posture retraining.
The physical therapy team will teach proper self-care strategies for the individual’s condition.
For individuals with neck and shoulder pain and muscle spasms, a trial of kinesiology taping may help alleviate symptoms and improve the overall injury.
The Non-Surgical Approach to Wellness with Chiropractic Care
References
Draper, D. O., Mahaffey, C., Kaiser, D., Eggett, D., & Jarmin, J. (2010). Thermal ultrasound decreases tissue stiffness of trigger points in upper trapezius muscles. Physiotherapy theory and practice, 26(3), 167–172. https://doi.org/10.3109/09593980903423079
For individuals experiencing gluteus minimus pain and are unsure where to start to deal with it, can a physical therapist, chiropractor, or general practitioner help diagnose lower extremity pain and develop an appropriate treatment plan?
Gluteus Minimus Muscles
The gluteus minimus is the smallest muscle of the gluteal muscles. Combined with the gluteus maximus and gluteus medius, these muscles make up the glutes. The glutes help form the buttocks shape, stabilize the hips, rotate the legs, and raise the thighs. The gluteus minimus and medius specifically support the gluteus maximus’s ability to raise the leg to the side and rotate the thigh inwards. (ScienceDirect. 2011)
Anatomy
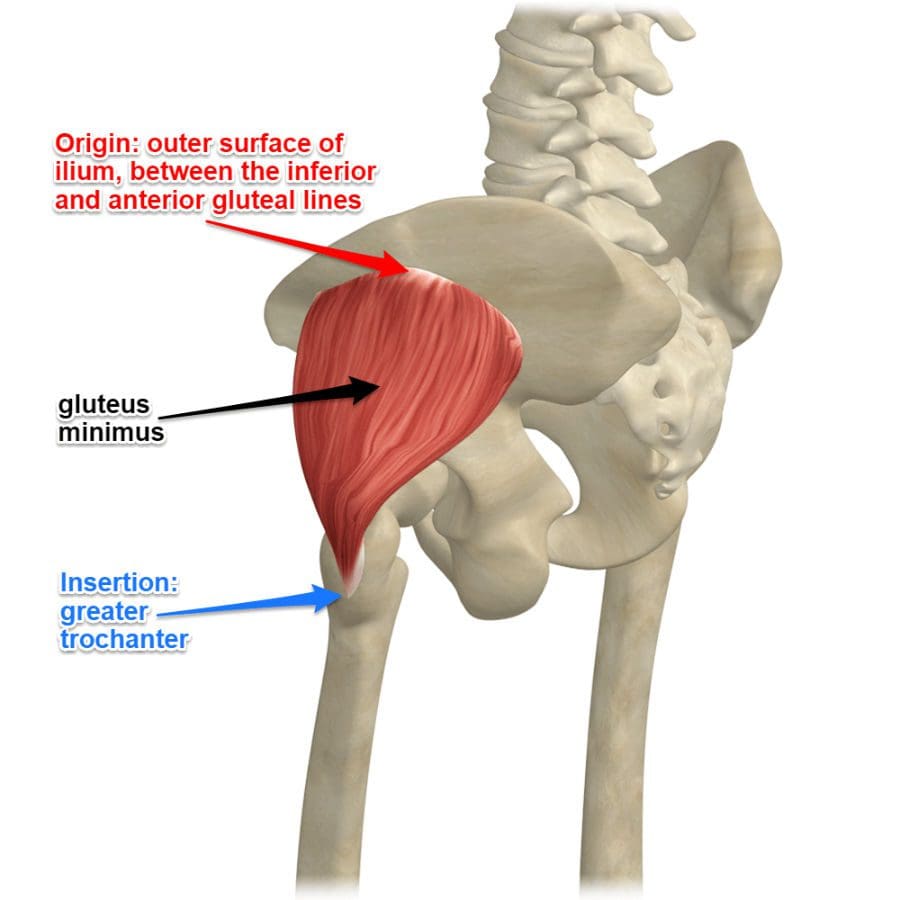
The gluteus minimus muscles are triangular and lie underneath the gluteus medius near the rotators of the hip joints. The muscles start in the lower ilium region, the upper and largest area of the hip bone that makes up the pelvis and attaches to the femur/thigh bone.
The fibers on the top part of the muscle are thick and compact, while the lower fibers are flat and spread out.
The superior gluteal nerves and blood vessels separate the gluteus minimus and the medius.
The gluteus medius muscles start on the upper ilium region, which covers the gluteus minimus muscle entirely. The location of the gluteus minimus muscles envelopes the sciatic notch or the area in the pelvis that houses the piriformis muscle, superior gluteal vein, and superior gluteal artery, which provide a certain amount of protection.
Function
Movement depends on the location of the femur. The gluteus minimus muscle’s function is to:
Flex
Rotate
Stabilize
When the thigh is extended, it helps abduct or swing the leg out away from the body.
When the hip bones are flexed, the gluteus minimus rotates the thigh inward with the help of the gluteus medius.
The movements are done with the support of the muscle fibers, which contract to move the thigh in both directions. (ScienceDirect. 2011)
The gluteus minimus and the medius also stabilize the hips and pelvis during movement and when resting.
Associated Conditions
One of the most common injuries is muscle wearing and tearing, which can cause pain over and around the greater trochanter. This is known as greater trochanteric pain syndrome or GTPS, a condition usually caused by a gluteus medius or minimus tendinopathy, which can include inflammation of the surrounding bursae. (Diane Reid. 2016) For a gluteus minimus tear, the pain/sensations will be felt outside the hip, especially when rolling or applying weight on the affected side. A tear can happen suddenly with no particular activity causing the tear to occur aside from normal use and stress on the muscle. Physical activities like walking may be painful.
Rehabilitation
Treatment depends on the severity of the condition. Usually, rest, ice, and over-the-counter medication can help reduce swelling and pain symptoms. For pain symptoms that are not subsiding, it’s recommended to see a healthcare provider who can run an MRI or X-ray to see the condition of the muscle and rule out other causes of pain. The healthcare provider will refer the patient to a physical therapy team that can evaluate the strength of the gluteus minimus and provide a list of exercises and stretches to help repair the muscle while conditioning the surrounding muscles. (SportsRec. 2017) Depending on the level of pain, sometimes the healthcare provider will prescribe a cortisone injection to the gluteus minimus muscle in conjunction with physical therapy. This will help alleviate the pain so that the physical therapy exercises can be done comfortably, allowing the gluteus maximus muscle to heal properly and strengthen. (Julie M. Labrosse et al., 2010)
Reid D. (2016). The management of greater trochanteric pain syndrome: A systematic literature review. Journal of orthopaedics, 13(1), 15–28. https://doi.org/10.1016/j.jor.2015.12.006
Labrosse, J. M., Cardinal, E., Leduc, B. E., Duranceau, J., Rémillard, J., Bureau, N. J., Belblidia, A., & Brassard, P. (2010). Effectiveness of ultrasound-guided corticosteroid injection for the treatment of gluteus medius tendinopathy. AJR. American journal of roentgenology, 194(1), 202–206. https://doi.org/10.2214/AJR.08.1215
For individuals experiencing a turf toe injury, can knowing the symptoms help athletes and non-athletes with treatment, recovery time, and returning to activities?
Turf Toe Injury
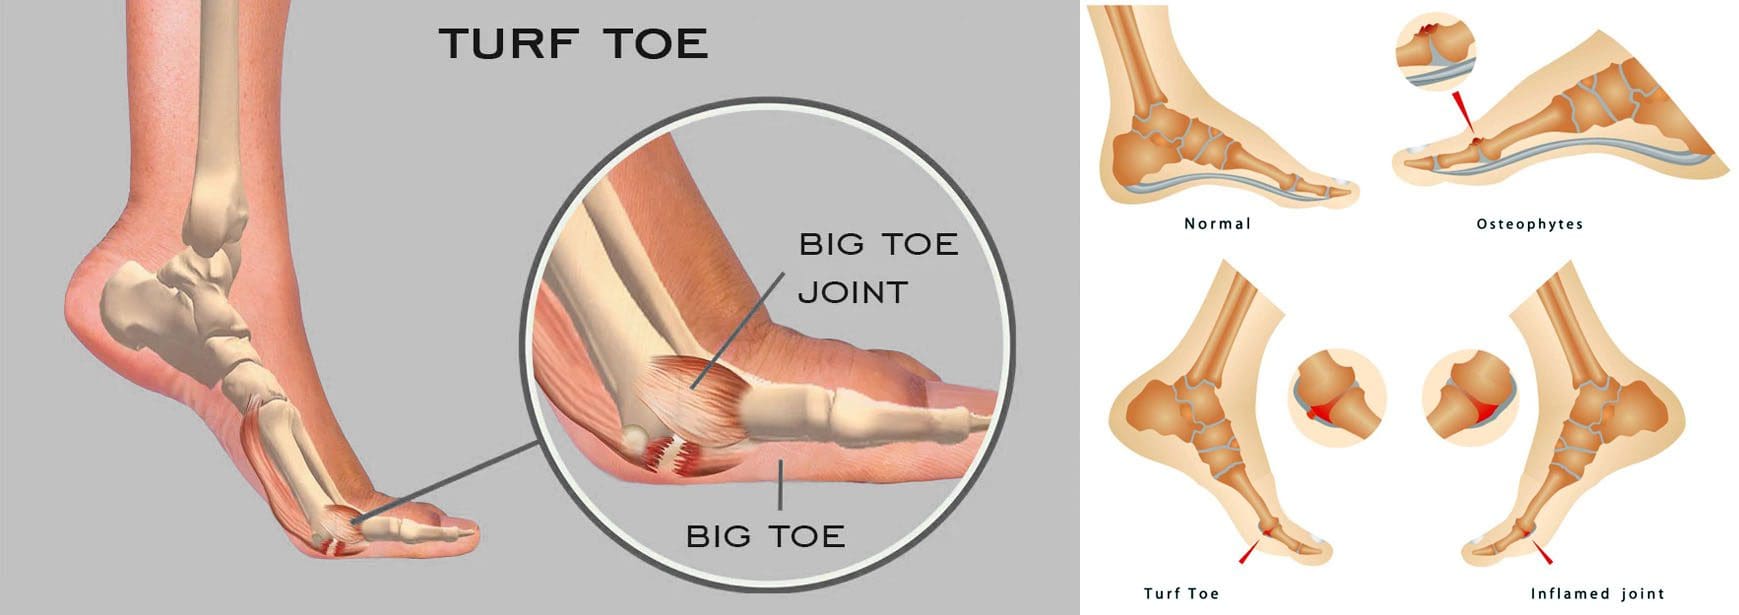
A turf toe injury affects the soft tissue ligaments and tendons at the base of the big toe under the foot. This condition usually occurs when the toe is hyperextended/forced upward, such as when the ball of the foot is on the ground and the heel is lifted. (American Academy of Orthopaedic Surgeons. 2021) The injury is common among athletes who play sports on artificial turf, which is how the injury got its name. However, it can also affect non-athletes, like individuals working on their feet all day.
Recovery time after turf toe injury depends on the severity and the type of activities the individual plans to return to.
Returning to high-level sports activities after a severe injury can take six months.
These injuries vary in severity but usually improve with conservative treatment. In severe cases, surgery could be required.
Pain is the primary issue that stops physical activities after a grade 1 injury, while grades 2 and 3 can take weeks to months to heal completely.
Meaning
A turf toe injury refers to a metatarsophalangeal joint strain. This joint comprises ligaments that connect the bone on the sole of the foot, below the big toe/proximal phalanx, to the bones that connect the toes to the larger bones in the feet/metatarsals. The injury is usually caused by hyperextension that often results from a pushing-off motion, like running or jumping.
If experiencing turf toe symptoms, see a healthcare provider for a proper diagnosis so they can develop a personalized treatment plan. They will perform a physical exam to assess pain, swelling, and range of motion. (American Academy of Orthopaedic Surgeons. 2021) If the healthcare provider suspects tissue damage, they may recommend imaging with X-rays and (MRI) to grade the injury and determine the proper course of action.
Grades 2 and 3 come with partial or complete tissue tearing, severe pain, and swelling. Treatments for more severe turf toe can include: (Ali-Asgar Najefi et al., 2018)
Limited weight bearing
Using assistive devices like crutches, a walking boot, or a cast.
Physical therapy also includes proprioception and agility training exercises, orthotics, and wearing recommended shoes for specific physical activities. (Lisa Chinn, Jay Hertel. 2010)
A physical therapist can also help ensure that the individual does not return to physical activities before the injury is fully healed and prevent the risk of re-injury.
Grade 1 – Subjective as it varies depending on the individual’s pain tolerance.
Grade 2 – Four to six weeks of immobilization.
Grade 3 – Eight weeks minimum of immobilization.
It can take up to six months to return to normal function.
Returning To Normal Activities
After a grade 1 turf toe injury, individuals can return to normal activities once the pain is under control. Grades 2 and 3 take longer to heal. Returning to sports activities after a grade 2 injury can take around two or three months, while grade 3 injuries and cases that require surgery can take up to six months. (Ali-Asgar Najefi et al., 2018)
Sports Chiropractic Treatment
References
American Academy of Orthopaedic Surgeons. (2021). Turf toe.
American College of Foot and Ankle Surgeons. Foot Health Facts. (2023). RICE protocol.
Najefi, A. A., Jeyaseelan, L., & Welck, M. (2018). Turf toe: A clinical update. EFORT open reviews, 3(9), 501–506. https://doi.org/10.1302/2058-5241.3.180012
Pinter, Z. W., Farnell, C. G., Huntley, S., Patel, H. A., Peng, J., McMurtrie, J., Ray, J. L., Naranje, S., & Shah, A. B. (2020). Outcomes of Chronic Turf Toe Repair in Non-athlete Population: A Retrospective Study. Indian journal of orthopaedics, 54(1), 43–48. https://doi.org/10.1007/s43465-019-00010-8
Chinn, L., & Hertel, J. (2010). Rehabilitation of ankle and foot injuries in athletes. Clinics in sports medicine, 29(1), 157–167. https://doi.org/10.1016/j.csm.2009.09.006
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine