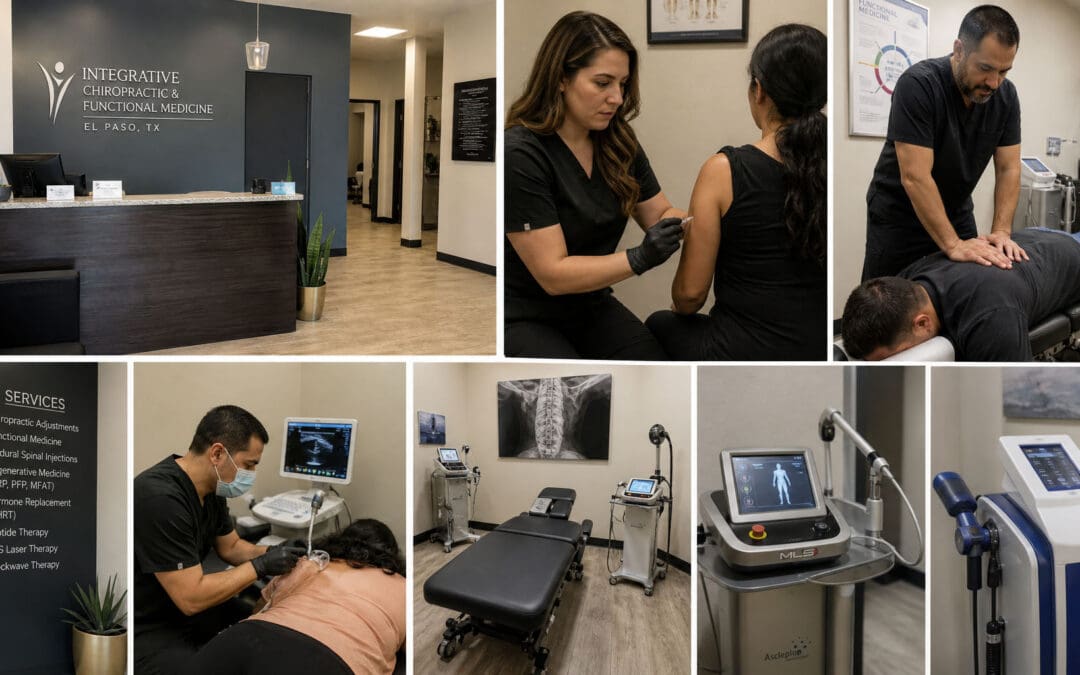
Back Clinic Functional Medicine Team. Functional medicine is an evolution in the practice of medicine that better addresses the healthcare needs of the 21st century. By shifting the traditional disease-centered focus of medical practice to a more patient-centered approach, functional medicine addresses the whole person, not just an isolated set of symptoms.
Practitioners spend time with their patients, listening to their histories and looking at the interactions among genetic, environmental, and lifestyle factors that can influence long-term health and complex, chronic disease. In this way, functional medicine supports the unique expression of health and vitality for each individual.
By changing the disease-centered focus of medical practice to this patient-centered approach, our physicians are able to support the healing process by viewing health and illness as part of a cycle in which all components of the human biological system interact dynamically with the environment. This process helps to seek and identify genetic, lifestyle, and environmental factors that may shift a person’s health from illness to well-being.
Why Coughing or Sneezing Can Suddenly Light Up Back or Leg Pain: Disc Pressure, Nerve Irritation—or Something Else?
Abstract
A cough, sneeze, or strain can briefly raise pressure in the trunk and lumbar discs. If a nerve root is already irritated, that spike may light up back or leg pain. The flare is a clue, not proof of a herniated disc. This post covers the mechanics, the exam, imaging limits, red flags, conservative care, and why an epidural is a short rehab window, not a cure.
A sneeze hits halfway through a shift, a code review, or a lane change. The low back grabs, or a hot line runs into the calf, then settles. Programmers at a second monitor, technicians under racks, Amazon workers mid-pivot, drivers in a seat, and desk professionals in allergy season all describe the sensation. It is not a diagnosis on its own.
What a Cough Does to Disc Pressure
A cough, sneeze, or strain is a short Valsalva maneuver. Chest and belly pressure rises, and some of that load reaches the lumbar discs. This effort generally increases intradiscal pressure in classic measurements, though the rise varies (Nachemson & Morris, 1964). Bending, lifting, and combined postures push pressure well above quiet standing (Wilke et al., 1999).
A healthier disc works like a water-filled cushion. A sudden belly brace can push the soft center outward. If the outer ring is torn, or disc material sits near a nerve root, that spike can press the root and flash pain into the back or leg.
Loaded postures that stack the spike
A programmer often sneezes in a flexed, rotated chair.
A data center technician may cough while kneeling at a rack.
An Amazon associate may pivot with a tote, then strain as dust hits.
A driver may be seated, hips flexed, with no chance to stand and unload.
A worn disc does not hold pressure like a young disc (Wilke et al., 1999). The symptom is still mechanical, not random.
A Useful Clue, Not Proof of a Herniated Disc
In 395 adults with severe sciatica, leg pain that worsened with coughing, sneezing, or straining was linked to nerve-root compression and disc herniation on MRI. The diagnostic odds were about 2.3 and 2.5. Back pain alone was weaker (Verwoerd et al., 2016).
That history is meaningful. It is not proof. It does not name the level or decide who needs a procedure. A disc bulge on a scan may be silent, and a cough wince may come from a facet, a hip, or a sensitive nerve that is not compressed.
What Else Can Light Up With a Sneeze?
Facet irritation prefers extension and rotation, though a stiff brace can still jar it.
Hip or sacroiliac pain may grab the buttock, then fade.
Deep gluteal irritation can mimic sciatica after long sitting.
Abdominal wall strain stays in the belly.
Kidney irritation is usually higher in the flank and often brings urinary changes.
Poor circulation usually hurts after a set walking distance and eases when you stand still. One sneeze rarely causes it.
Strength, Reflexes, and the Straight-Leg Raise
The visit asks where pain travels, whether the cough hits the back, the leg, or both, and whether the leg feels weak or numb. The exam checks toe and ankle strength, heel-and-toe walking, knee and ankle reflexes, light touch, hip motion, and the first steps after sitting. Amazon and rack workers often notice those first steps most.
The straight-leg raise lifts the leg with the knee straight. Between about 30 and 70 degrees, tension rises on the lower lumbar roots. A clearly negative test makes a large compressive herniation less likely, but tight hamstrings can also hurt, so the test is not specific (Camino Willhuber & Piuzzi, 2023). A crossed straight-leg raise is less sensitive and more specific. Nerve-pattern pain, a sensory change, reflex or strength loss, and a positive raise together make a disc-related root problem more likely (Verwoerd et al., 2016).
When Imaging Helps, and When It Does Not
Early MRI is not the default. Routine imaging in the first weeks, without red flags, does not speed recovery (Chou et al., 2011). Imaging is usually not appropriate before a trial of care, but prompt MRI is appropriate if cauda equina syndrome is suspected or weakness is severe or worsening (American College of Radiology, 2021).
Scans overcall. Disc bulges are common in adults without symptoms and more common with age (Brinjikji et al., 2015). A picture does not prove the cause of the sneeze. Imaging is indicated when pain or weakness is not improving, strength is dropping, a procedure is planned, or a red flag is present.
Red Flags That Should Not Wait
Most flares are mechanical. Seek same-day care for trouble starting urination, new bladder or bowel loss, saddle numbness, rapidly worsening weakness, fever, unexplained weight loss, cancer history, or pain after major trauma. These can signal cauda equina compression or infection (American College of Radiology, 2021). Knowing what should not wait is part of directing your care.
Conservative Care Before a Needle Is Discussed
The first gain is movement you can tolerate. Strict bed rest usually stiffens the hips and keeps the root sensitive. Short walks and unloading positions work better.
At El Paso Back Clinic, care centers on function.
Spinal decompression, manual or mechanical, reduces load while an irritated root settles.
Chiropractic alignment is used for joints that are not guarding a severe deficit.
Hip and mid-back mobility keep the lumbar discs from being the only hinges.
Pacing matches desk reach, rack crouches, aisle pivots, and long drives.
MLS laser therapy may help when swelling keeps the root angry.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges that structural work with medical evaluation. He holds Texas APRN license #1191402 and prescriptive authority #59628 (NPI 1205907805). Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (Texas license #J2933, NPI 1164426748), directs medical care at Injury Medical Clinic PA in Mission Plaza, including blood pressure, diabetes, and clotting risk.
That pairing is beneficence: structural care and medical screening serve the same person. It is also non-maleficence, because drug-free decompression and movement can reduce the pull toward opioids or an early surgery talk. Many El Paso programmers, data center employees, Amazon associates, and drivers have group benefits that may cover the evaluation and, when indicated, imaging or a procedure. Benefits vary.
If nerve pain blocks walking and decompression, an image-guided epidural may be discussed. It is not the first step, and it is not a disc repair.
What happens during the procedure?
Under fluoroscopy, or sometimes ultrasound, a thin needle is guided into the epidural space near the root, not into the disc. Contrast may confirm placement. A small dose of corticosteroid, often with local anesthetic, is placed around the nerve so swelling can settle and movement can restart.
A 2025 review of 90 trials found that epidural steroids probably help with short-term radicular pain and disability. About 4 people had to be treated for one short-term pain benefit. Long-term pain relief was not clearly proven (Armon et al., 2025). That is a window of weeks, not a cure.
How the window should be used
Use the window to walk farther, tolerate decompression, and rebuild strength for ladders and aisle pivots. Recheck before any repeat injection. Risks include a pain flare, higher blood sugar, headache after a dural puncture, and rare infection or bleeding. Doing no harm includes saying no when the exam does not support a needle.
You Remain the Decision-Maker
A sneeze that lights up the leg says the symptom is pressure-sensitive. It does not assign a herniated-disc label or a procedure. Ask what strength and reflexes showed and what better should look like after two weeks of walking and decompression. Care at Injury Medical Clinic PA is meant to stay coordinated with the clinician you already trust.
If coughing, sneezing, or straining keeps shooting pain into the buttock or leg, schedule an evaluation at El Paso Back Clinic with Dr. Alex Jimenez, DC, APRN, FNP-BC, and the team led by Dr. Maria Guadalupe Cardenas, MD. Bring the pattern with you. Leave with a next step.
Can Nutrition Change How Well an El Paso Spine Recovers?
Abstract: Mechanical care remains central to spinal recovery. This article explains why protein, glucose control, hydration, sleep, and smart loading still matter for shift workers recovering from disc, ligament, muscle, or spinal injuries. Food does not heal a herniated disc. Nutrition can support collagen remodeling, muscle preservation, and rehab tolerance. Poor meals, glucose swings, dehydration, and sleep loss can slow the same plan. El Paso Back Clinic pairs non-surgical decompression with medical oversight so patients can use group insurance and choose next steps with clear information.
The server room is quiet at 2:17 a.m. A data center technician finishes a rack job that required a crouch and a twist. An Amazon associate on the same clock has already walked miles of concrete. A programmer covering an overnight deploy has been in one chair since dinner. All three later need care for a disc, ligament, or muscle injury that will not settle.
Someone always offers the same advice. Eat cleaner. Drink collagen. Cut sugar. The advice is incomplete. At El Paso Back Clinic, the sentence is this: your disc does not eat dinner.
A herniated disc doesn’t tuck itself back in because breakfast included eggs. Ligaments do not restitch because a shake lists twenty grams of protein. Mechanical load, joint motion, nerve protection, and a graded return to work decide most of the outcome. Nutrition is the supply line, not the decompression table.
Two Different Kinds of “Disc Nutrition”
People use nutrition for two jobs. Mixing them creates false hope.
The disc’s own grocery route
An intervertebral disc has almost no direct blood supply. Glucose, oxygen, and waste move mostly by diffusion through the endplates. Slow, cyclic loading—the kind seen in walking and well-dosed rehab—can help that exchange. Long static postures and sudden heavy flexion can work against it (Gullbrand et al., 2015; Belavy et al., 2016). That is why non-surgical spinal decompression, alignment work, and movement coaching stay central. They change the mechanical environment the disc lives in. A protein bar cannot.
The tissues that do use your plate
The muscles that brace the spine, the tendons that transmit force, and the ligaments that limit end-range motion rebuild with amino acids, energy, and time. They waste away when nights get long, meals get irregular, and loading stops. Shift work fills that gap. Night schedules change when you eat, how you sleep, and how your body handles glucose. Food did not cause the herniation. The construction crew around the injured segment may still be underfed, under-rested, and asked to work a full shift (Matre et al., 2021; Oosterman et al., 2020).
Why Mechanical Care Still Comes First
Beneficence starts with the step most likely to help and least likely to harm. For many people with severe lumbago or disc-related pain, that means a non-surgical plan:
Examination of posture, hip motion, nerve tension, and work tasks
Imaging review when symptoms and function do not match
Adjustments and flexion-distraction or decompression when indicated
MLS laser or shockwave for surrounding soft tissue when appropriate
A loading plan that protects the segment while the body stays useful
Conservative care can reduce the rush toward surgery or long medication courses when those steps are not required. You should know what the spine needs mechanically before anyone sells a disc-healing diet.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, leads the structural side and, with collaborative medical oversight, can add diagnostics and selected procedures. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, directs laboratory interpretation, metabolic risk, and coordination with existing physicians.
Protein: Building Material, Not a Reset Button
After injury or reduced loading, muscle protein breakdown rises. Rehab then asks those same muscles to stabilize a sore spine. Injury-nutrition reviews commonly place protein needs near 1.6 to 2.2 grams per kilogram per day, spread across meals (Smith-Ryan et al., 2020; Papadopoulou, 2020). Energy drinks and one burrito are a weak supply line.
What protein actually supports
Muscle preservation when you sit, stand, or protect a painful segment
Rehab quality, because weak, underfed muscle fails first
Amino acids for remodeling tissue, not a disc reset overnight
Collagen peptides plus training have some evidence for tendon morphology and joint comfort, but the effect depends on loading (Khatri et al., 2021; Aussieker et al., 2023; Bischof et al., 2024).
Shift-work protein problems we see in El Paso
One large meal after the shift, then almost nothing for ten hours
Protein pushed to 3 a.m., when appetite is low
“I’ll eat when I get home,” which becomes sleep
A practical target is protein every few waking hours: eggs, yogurt, leftover chicken, beans with rice, or a shake if food is not available on the floor. That supports recovery. It will not replace decompression.
Glucose: The Quiet Load on Collagen
High or swinging blood sugar does not cause every herniated disc. It can change collagen quality over time. Excess glucose helps form advanced glycation end-products (AGEs). AGEs cross-link collagen, reduce fiber slide, and make some tissues stiffer and more brittle. Research links diabetes and AGE burden with disc and tendon changes (Kakadiya et al., 2020; Rosenberg et al., 2023; Li et al., 2024).
For a programmer, NOC operator, or Amazon lead, the pattern is familiar: fasting through half the shift, a sweet drink for alertness, a heavy meal at the wrong clock, and poor sleep, which worsens glucose handling (Oosterman et al., 2020). That can raise inflammation and lower rehab tolerance. That doesn’t mean an MRI will reverse if you switch drinks. It means the same mechanical program may work better when glucose is steadier.
This is where MD and NP lab work earns its place. A1C, fasting glucose, lipids, and related markers help Dr. Cardenas see whether recovery is inflamed, insulin-resistant, or under-fueled. Treating numbers without treating the spine is incomplete. Treating the spine while ignoring uncontrolled glucose is also incomplete.
Sleep, Water, and the Night-Shift Recovery Tax
Shift work is associated with higher odds of chronic musculoskeletal pain, and low-grade inflammation is one proposed link (Matre et al., 2021). Circadian misalignment also reduces muscle insulin sensitivity and disturbs repair timing (Oosterman et al., 2020). A technician who decompresses at noon and then sleeps five broken hours is asking collagen to work nights too.
Hydration is simpler and still ignored. Caffeine-only nights and hot warehouse aisles do not dry a disc like a sponge on a stove, but they increase fatigue and make people move worse.
A short list that fits a night schedule
Keep water at the station; pair each energy drink with water
Protect a dark, cool sleep block even if it starts at 9 a.m.
Eat protein before the shift, not only after
Do not save the entire recovery plan for days off
Loading Still Writes the Script—Including After PRP
If a ligament, tendon, or joint later needs platelet-rich plasma (PRP), the injection is a signal, not a substitute. Mechanical loading after the procedure shapes the tissue response. Skipping rehab or returning to a poor lift can waste the appointment (Neph et al., 2020; Gremeaux et al., 2026). The same logic applies to image-guided epidurals. A calmer nerve is a window for movement, not a cure on its own.
The clinic keeps that hierarchy visible: protect the segment and restore motion; reload muscle in a way the job can survive; support protein, glucose, micronutrients, and sleep so the plan is tolerable; and add procedures only when they serve that sequence.
Using Group Insurance Without Guessing
Many data center, IT, and fulfillment employers in El Paso carry strong group insurance. That benefit can cover evaluation, chiropractic and decompression visits, medical assessment, and indicated labs. Using the plan early is often cheaper than waiting until lifting limits or sleep collapse.
A visit may include a mechanical exam tied to rack height, pallet work, chair time, or night rotation; a plain-language imaging review; a decompression plan with home loading rules; and labs when fatigue or slow tissue response is part of the story. You remain the decision-maker.
Call El Paso Back Clinic at 915-850-0900 or schedule through Injury Medical Clinic PA at Mission Plaza. Bring your work schedule, insurance card, and the movements that still scare you. The spine needs mechanics first. The body still has to show up with materials.
The Programmer Who Forgot to Breathe: Can Shallow Screen-Time Breathing Contribute to Rib, Mid-Back, and Low-Back Stiffness?
Abstract: Long coding sessions can change how you sit, move, and breathe. When the rib cage stays compressed and the trunk barely changes position, some people notice rib stiffness, mid-back tightness, low-back fatigue, or a deep breath that feels restricted. This article explains how the diaphragm, ribs, thoracic spine, abdominal wall, and lumbar stabilizers work together, what rehabilitation may address, and which breathing or chest symptoms need medical evaluation first.
A programmer can spend two hours solving one problem and barely notice anything below the neck. Then the task ends. The shoulders drop. The person sits back, tries to inhale deeply, and suddenly feels the ribs resist, the mid-back ache, or the low back feel tired.
That experience does not prove that “bad breathing” caused back pain. Pain is rarely that simple. However, prolonged flexed sitting, low movement variety, and shallow breathing can change how the chest wall and trunk share mechanical work. Research has linked prolonged sitting with immediate increases in low-back discomfort in some adults. A small laboratory study also found that greater posterior pelvic tilt reduced thoracic expansion and respiratory measures in healthy young men (De Carvalho et al., 2020; Aramaki et al., 2021).
The Diaphragm Is Also Part of Trunk Control
The diaphragm is the dome-shaped muscle beneath the lungs. When it contracts, it descends and helps draw air into the chest. It also works with the abdominal wall, pelvic floor, multifidus, and other trunk muscles to manage pressure and support the spine during movement.
That dual role matters at your desk. Your trunk must remain stable enough for typing, reaching, standing, and lifting while still allowing the ribs and abdomen to expand. Research on chronic low-back pain suggests that breathing and diaphragm function may interact with trunk control, but the evidence does not show that diaphragm dysfunction causes every back problem. Breathing is one variable in a much larger mechanical system (Chen et al., 2026; Li et al., 2026).
What a Long Screen Session Can Change
Picture a developer leaning toward a laptop during a difficult debugging session. The pelvis rolls backward, the low back rounds, the thoracic spine stays flexed, and the lower ribs move closer to the pelvis. That position may continue for long periods with little movement outside the hands.
Several changes can follow:
Rib movement can feel limited. A compressed trunk position may make comfortable expansion harder.
Thoracic motion narrows. The mid-back spends less time extending and rotating.
Support muscles stay active. Spinal and abdominal muscles continue to provide low-level control.
Breathing may become smaller. Some people brace the abdomen, briefly hold their breath, or breathe mainly into the upper chest when concentrating.
One position becomes the problem. There is rarely one perfect posture; low movement variety may be more important than a single snapshot of alignment.
These changes can help explain why the first deep breath after a long work block feels stiff, but they do not establish a simple cause-and-effect relationship between shallow breathing and pain.
Why Rib, Mid-Back, and Low-Back Symptoms Can Travel Together
The ribs attach to the thoracic spine, so every comfortable breath includes small movements through rib joints, chest-wall tissues, the thoracic spine, the diaphragm, and abdominal muscles. If the upper body stays flexed and still, those tissues may feel temporarily stiff.
The low back can fatigue at the same time because trunk control is shared. The diaphragm helps regulate pressure while the abdominal wall and spinal muscles manage load. That is why a useful examination should look beyond “take deeper breaths.”
A clinician may assess:
thoracic and rib mobility;
lumbar control and sitting tolerance;
hip mobility and trunk endurance;
symptom reproduction with breathing or movement;
neurological findings; and
whether breathing changes during reaching, lifting, or exercise.
The goal is to identify what is actually limiting function rather than assigning every symptom to posture.
Can Breathing Exercises Help?
Possibly, as an adjunct to rehabilitation.
A 2026 systematic review of 17 randomized trials found that breathing exercises may improve pain and function in chronic nonspecific low-back pain, but the evidence was low to very low certainty because studies varied and several had a high risk of bias (Chen et al., 2026). A separate 2026 meta-analysis found moderate-certainty evidence that diaphragmatic training may reduce pain and disability when added to care, while longer-term effects still need clarification (Li et al., 2026).
The practical message is not “breathe correctly and fix your back.” You can train breathing alongside mobility, strength, coordination, and graded activity when the examination suggests it matters.
A Five-Step Mechanical Reset
For ordinary screen-related stiffness, and only when no medical warning signs are present, a simple reset can restore movement options:
Change position. Sit taller, stand, or walk briefly, then take a deep breath.
Let the lower ribs widen. Place your hands around the lower rib cage and allow gentle expansion without straining.
Move the mid-back. Add comfortable extension, rotation, or reaching instead of repeatedly stretching only the low back.
Release unnecessary bracing. If you have been gripping your abdomen, let it soften enough for normal breathing.
Reload the trunk. Follow mobility with walking, light resistance, or prescribed stabilization exercises so the change transfers into function.
The target isn’t perfect posture. It improves variability, trunk capacity, and coordination.
When Chiropractic and Rehabilitation Fit
For mechanical rib, thoracic, or lumbar complaints, chiropractic and rehabilitation may be appropriate after excluding dangerous or non-musculoskeletal causes. Care may combine spinal or rib-joint assessment, manual treatment when indicated, mobility work, progressive trunk training, ergonomic changes, and exercise.
A 2026 review found that thoracic manual techniques and breathing exercises may improve pain or disability in some low-back-pain populations, but the certainty was low and treatment effects varied (Seyedhoseinpoor et al., 2026). That supports personalized care, not a one-size-fits-all breathing plan.
At El Paso Back Clinic, the useful outcome is physical function: sitting with less fatigue, moving more comfortably, tolerating work demands, and building capacity without rushing toward invasive treatment.
Red Flags: When Breathing Is Not a Posture Problem
Difficulty taking a satisfying deep breath can be musculoskeletal, but unexplained shortness of breath can also reflect heart, lung, vascular, infectious, or other medical conditions.
Seek emergency care for sudden severe shortness of breath, unexplained chest pain or pressure, fainting, blue lips or nails, confusion, or major breathing difficulty. New breathlessness after prolonged immobility, surgery, illness, or a long trip also deserves prompt medical attention because a blood clot is one possible cause (Mayo Clinic, 2025).
A persistent cough, fever, wheezing, worsening exercise tolerance, or breathlessness that doesn’t match your activity level deserves medical evaluation. Chiropractic treatment should not delay that workup.
Integrated Care, Informed Choices
When symptoms appear mechanical, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, can connect chiropractic assessment, rehabilitation, and medical evaluation within one coordinated plan. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with over 40 years of experience, provides medical direction when cardiopulmonary, metabolic, medication-related, or other non-musculoskeletal factors need consideration.
This approach supports beneficence, non-maleficence, and autonomy: use care that is likely to help, avoid unnecessary risk, and give patients enough information to choose among reasonable options. Prioritize non-invasive treatment when appropriate, and add imaging, laboratory testing, referral, or medical treatment when findings justify it. Care can also coordinate with the patient’s existing medical team.
The Bottom Line
Screen-time breathing is not a diagnosis. Prolonged flexion and low movement variety may reduce rib and thoracic motion and alter how the diaphragm, abdominal wall, and spinal muscles share work. For some people, that pattern can accompany rib stiffness, mid-back tightness, or low-back fatigue.
Do not obsess over every breath. Restore movement options, strengthen the trunk, vary posture, and investigate symptoms that do not behave like ordinary mechanical stiffness. If pain keeps returning or breathing feels genuinely abnormal, get evaluated before assuming the screen is the only factor.
A practical starting point is simple: notice when concentration makes your body rigid, then change position before discomfort becomes the only signal you hear. Small, repeated movement choices throughout the workday can support comfort without turning posture or breathing into another performance task that creates unnecessary worry during demanding coding sessions.
Testosterone and Androgen Physiology in Women: Subcutaneous Injections in Coordinated Care
Abstract: Testosterone is a normal hormone in women. The ovaries, adrenal glands, and many local tissues help make and use it. Levels fall slowly with age, not all at once at menopause. A single blood test rarely proves deficiency. The strongest research support for testosterone therapy in women is for distressing low sexual desire after menopause, after other causes are checked. Subcutaneous injections can provide steadier levels in some studied groups, but evidence in women is thinner and remains off-label. Integrative chiropractic care does not replace medical decisions about hormones. It can help patients gain pain relief, better mobility, and improved sleep while the medical team keeps treatment coordinated and safe.
Testosterone is a female hormone
Androgens are often called male hormones. That label is incomplete. Testosterone is the main circulating active androgen and a normal part of female biology. Women keep lower amounts than men—typically 10 to 20 times lower—but those amounts still guide important physical and metabolic functions (Cleveland Clinic, n.d.; Davis & Wahlin-Jacobsen, 2015). For much of adult life, a woman’s circulating testosterone is higher than her circulating estradiol (Davis & Wahlin-Jacobsen, 2015).
Testosterone works in two ways:
Directly, on androgen receptors in muscle, bone, brain, fat, skin, and sexual tissues
Indirectly, when local enzymes turn it into estradiol or into the stronger androgen dihydrotestosterone (DHT)
These pathways help explain effects on sexual function, tissue upkeep, and metabolism even when blood levels look low (Davis & Wahlin-Jacobsen, 2015; Labrie et al., 2017).
Where women’s androgens come from
Women do not rely on one gland. Production is shared.
The ovaries release some testosterone and larger amounts of precursors
The adrenal glands release DHEA and DHEA-sulfate (DHEAS), a large precursor pool
Peripheral tissues—fat, skin, muscle, and other organs—convert those precursors into the small amounts of hormone they need
This last step is called intracrinology. Many tissues make the hormone they need on site and then break it down before much of it returns to the blood (Labrie et al., 2017). A blood testosterone result is only the visible tip of a larger local system.
Enzymes in tissues can convert DHEA to testosterone, make DHT, or turn testosterone into estradiol. The same precursor can become an androgen in one tissue and an estrogen in another. Local enzymes, not just the lab, decide the outcome (Labrie et al., 2017; Schiffer et al., 2018).
A long slope, not a sudden cliff
Estradiol falls sharply at menopause. Androgens do not. DHEA and DHEAS begin to fall from about the third decade of life and may be down by roughly 60% by menopause (Davis & Wahlin-Jacobsen, 2015). A woman in her forties is already below her own earlier peak.
Midlife data measured by mass spectrometry found median testosterone falling from about 0.56 nmol/L in the early forties to about 0.42 nmol/L in the late fifties, with a low point near ages 58–59. In women of similar age, testosterone did not differ by menopausal stage. Natural menopause itself is not a stand-alone reason to administer testosterone (Wang et al., 2025).
Two exceptions matter:
Surgical menopause (both ovaries removed) cuts the ovarian share at once
Premature ovarian insufficiency creates an earlier deficit than the usual age-related slope (Davison et al., 2005; Soman et al., 2019)
The postmenopausal ovary can also continue to produce some testosterone for years after estradiol output has collapsed (Davis & Wahlin-Jacobsen, 2015).
Why one lab number rarely settles the question
Measuring female testosterone is challenging. Routine immunoassays were built for the much higher male range. Liquid chromatography–tandem mass spectrometry (LC-MS/MS) is more reliable. Most circulating testosterone is bound to sex hormone-binding globulin (SHBG), so free hormone can change when SHBG changes even if total testosterone stays the same (Rosner & Vesper, 2010).
What moves SHBG—and the free fraction:
Oral estrogen and high thyroid hormone tend to raise SHBG and lower free testosterone
Obesity and insulin resistance tend to lower SHBG and raise free testosterone
Androgen excess, including polycystic ovary syndrome (also discussed as polyendocrine metabolic ovarian syndrome, or PMOS), also lowers SHBG (Luo et al., 2024; Teede et al., 2023)
Low SHBG is also a metabolic clue and has been linked to higher diabetes risk in women (Ding et al., 2009). Guidelines do not diagnose androgen deficiency based on a single value. A level is a baseline and a safety check, not the whole diagnosis (Davis et al., 2019; Parish et al., 2021).
What the evidence supports—and what it does not
The clearest evidence is in sexual function. Higher endogenous testosterone tracks modestly with better desire (Maseroli & Vignozzi, 2022). In randomized trials, testosterone improved desire, arousal, orgasm, pleasure, and satisfaction and reduced sexual distress in postmenopausal women with low desire (Islam et al., 2019).
Androgen receptors sit in bone, muscle, fat, vessels, and the brain. That map is real. This is not the same as a proven benefit. Trials supporting sexual-function gains have not firmly shown better body composition, bone, mood, or cognition to the same standard (Davis, 2025; Islam et al., 2019). Some tissue effects may also come from local conversion to estradiol.
Too much androgen is the other problem: acne, unwanted hair, cycle changes, and higher cardiometabolic risk in PMOS/PCOS (Teede et al., 2023). Risk can appear at both ends of the female range (Luo et al., 2024). The target is a physiologic band, not “more is better.”
International groups have not endorsed a broad “female androgen deficiency syndrome,” because no blood cutoff cleanly separates symptomatic women from normal variation (Davis et al., 2019; Wierman et al., 2014). The one consensus indication is hypoactive sexual desire disorder (HSDD) in postmenopausal women—low desire that causes distress—after other causes are addressed (Parish et al., 2021). There is still no FDA-approved testosterone product for women in the United States. Prescribing remains off-label, and long-term heart and breast data in women are limited (Islam et al., 2019; Panay et al., 2024).
What subcutaneous testosterone injections are
A subcutaneous (SubQ) injection places testosterone into the fatty layer under the skin, usually in the abdomen or thigh, with a short, thin needle. An intramuscular (IM) injection goes deeper into muscle.
In men and in some gender-affirming care settings, weekly SubQ testosterone esters can reach therapeutic levels with smaller peaks and troughs, less pain, and easier self-use than some IM schedules (Figueiredo et al., 2022). That data should not be copied wholesale onto women.
Women need much smaller doses
Female physiologic ranges are far lower
Randomized evidence in women is mainly transdermal, not SubQ (Davis et al., 2019)
Guidelines do not establish a subcutaneous route for women and do not endorse compounded products as first-line (Parish et al., 2021)
If a clinician considers low-dose SubQ testosterone cypionate in oil, it is an individualized, off-label choice. The goal is to keep exposure within the premenopausal physiologic range, monitor for acne, hair changes, voice changes, or metabolic shifts, and document informed consent (Davis et al., 2019; Jimenez, 2026b). If this route is used at all, start low, titrate to symptoms plus labs, use the same assay method over time, and do not treat menopause itself as an automatic indication (Wang et al., 2025). Compounded prefilled low-dose syringes are not FDA-approved for women. They are a delivery tool, not proof that therapy is indicated.
What patients gain from integrative chiropractic care
Hormone questions and musculoskeletal problems often show up together. Women with midlife androgen decline may also notice joint stiffness, slower recovery, fatigue, and poorer sleep (Davis, 2025; Jimenez, 2026a). After an auto accident or work injury, neck pain, low-back pain, and delayed stiffness can stack on top of that picture.
Integrative chiropractic care does not replace a hormone plan. It focuses on what the patient can gain:
Pain relief through restored joint motion and less mechanical strain
Improved mobility so walking, lifting, work, driving, and home tasks feel more possible
Better sleep when night pain, muscle tightness, and poor recovery ease
Stronger return to activity after crashes, work strain, or chronic back and neck pain
Chiropractic adjustments, soft-tissue care, and rehabilitation are non-invasive and drug-free. Used well, they can lower the chance that pain is managed only with long-term medication or rushed toward surgery. That is a simple safety idea: first do no harm, then add only what the person needs.
Integrative care also means working with the patient’s existing medical team. Supervising clinicians handle hormone dosing, lab review, and medication decisions. Chiropractic care adds movement, recovery, and function so the whole plan stays coordinated rather than split into separate silos.
How the El Paso team works together
At Injury Medical Clinic PA in El Paso, Texas, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, provides chiropractic care, functional-medicine framing, and dual-licensed nurse-practitioner evaluation. In clinical observation, he describes testosterone as one part of a wider plan, not a stand-alone energy shot. He notes that women have androgen receptors across muscle, bone, and brain; that levels often fall by the mid-forties compared with the mid-twenties; and that low-dose, monitored strategies may support libido, energy, and musculoskeletal integrity in selected patients when labs, symptoms, and safety checks line up (Jimenez, 2026a, 2026c). He also stresses that SubQ use in women is not the same as male testosterone replacement and should not be sold as routine wellness care (Jimenez, 2026b). More clinical notes appear on dralexjimenez.com and LinkedIn.
Off-label hormone decisions need medical oversight. Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), has more than 40 years of experience as an internist. She serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA. This multidisciplinary setup is common in integrative and injury clinics: an MD provides medical direction while a chiropractor delivers hands-on spinal and rehabilitation care.
Together, the team can connect:
Medical screening and comorbidity review
Chiropractic care for pain, mobility, and sleep-related musculoskeletal strain
Functional medicine review of sleep, gut, thyroid, iron, and metabolic drivers that also change SHBG
Personal injury care and rehabilitation after crashes, work injuries, or delayed symptoms
Clear communication with the patient’s other physicians so care stays safe and well coordinated
Putting the pieces together
A careful visit starts with the story—desire, distress, energy, sleep, pain, injuries, medicines, and surgery—then an exam and labs used as a baseline, not a verdict. Other causes come first: relationship strain, depression, pain, vaginal dryness, thyroid disease, and medication effects. For many women, that means no testosterone. For some postmenopausal women with HSDD, a carefully dosed, monitored plan may be discussed. If SubQ is chosen, it stays small, measured, and reversible while chiropractic care rebuilds the capacity to move and recover.
Testosterone is a normal female hormone made in more than one place and used inside many tissues. It declines on a long slope. Blood tests tell only part of the story. The honest evidence base is strongest for distressed low sexual desire after menopause, not for menopause itself. Subcutaneous injections can offer steady delivery in other groups, but in women they remain an individualized, off-label option that must stay within a physiologic range.
The safest frame is coordinated care: medical direction for hormone decisions, chiropractic and rehabilitation for pain relief, mobility, and sleep, and a plan that prefers non-invasive options when they can help a person function without adding avoidable risk.
“Your body works as a unified system—your hormones directly dictate how well your spinal muscles heal and protect your joints. You don’t have to navigate chronic discomfort or confusing hormonal shifts alone; reach out to our team today to learn how safe, monitored subcutaneous protocols can be seamlessly coordinated with your physical care to help you live without limits.”
Davis, S. R., Baber, R., Panay, N., Bitzer, J., Perez, S. C., Islam, R. M., Kaunitz, A. M., Kingsberg, S. A., Lambrinoudaki, I., Liu, J., Parish, S. J., Pinkerton, J., Rymer, J., Simon, J. A., Vignozzi, L., & Wierman, M. E. (2019). Global consensus position statement on the use of testosterone therapy for women. The Journal of Clinical Endocrinology & Metabolism, 104(10), 4660–4666.
SubQ Testosterone for Women: Dosing, Monitoring, and Muscle Support
Abstract: Testosterone is not a male-only hormone. Women make more of it than estrogen by weight throughout much of their adult lives, and those levels decline with age. The strongest research supports low-dose therapy for postmenopausal women who have distressing low sexual desire. Subcutaneous injections place a modest, consistent amount of the hormone into the fat under the skin so blood levels can return to a typical female range. This article explains how that route works, who may be a candidate, how clinicians monitor the dose, how muscle and bone support movement, and how integrative chiropractic care in El Paso can work alongside medical oversight to treat the spine, joints, and hormones as one system.
Why Women Need Testosterone, Too
Testosterone is not just a leftover male hormone; women produce it in significant amounts. Across most of adult life, a woman’s ovaries and adrenal glands produce more testosterone than estrogen by mass. That output falls with age and drops further after the ovaries are removed (Davis et al., 2019; Hatzilabrou, 2025).
When levels sit at the low end of a woman’s own range, some women notice a persistent, unwanted loss of desire. That problem has a name: hypoactive sexual desire disorder, or HSDD. Distress is the key. A quiet fade that does not bother her is not the same as a loss that troubles her every day (Davis et al., 2019; Parish et al., 2021).
Pooled randomized trials in thousands of women show that restoring testosterone into the normal premenopausal range can improve desire, arousal, orgasm, pleasure, and satisfaction, and can lower sexual distress. The gains are real and consistent, but they are moderate, not magic, and a strong placebo response is part of the picture (Islam et al., 2019; Hatzilabrou, 2025).
What Subcutaneous Injections Actually Do
A subcutaneous (SubQ) injection delivers medicine into the fatty layer just under the skin, not deep into muscle. Typical sites are the abdomen or outer thigh. The needle is short and thin. Oil-based testosterone—often testosterone cypionate—then seeps out slowly, which can keep blood levels steadier than a large intramuscular shot (FOLX Health, n.d.; Hone Health, 2024).
Think of it as a small, measured drip rather than a flood. Women need far less than men, often about one-tenth of a typical male dose. Clinics that use weekly SubQ cypionate often start in a low milligram range and then adjust to a lab result, not to a feeling (Highland Longevity, n.d.; Hone Health Help Center, n.d.).
Keep these route facts in view:
Most high-quality trials in women used patches, creams, or gels, not weekly shots (Hatzilabrou, 2025).
One older implant study in women was positive for desire and bone density, but fixed pellets can overshoot the female range and cannot be turned down once placed (Hatzilabrou, 2025).
No published milligram conversion exists from a 300-microgram patch to a SubQ syringe. The honest method is to dose to a measured blood level (Davis et al., 2019; Hatzilabrou, 2025).
No testosterone product is FDA-approved for women in the United States. Use is off-label and requires informed consent (Cedars-Sinai, n.d.; Parish et al., 2021).
Some compounding programs offer low-concentration, prefilled single-dose syringes of testosterone cypionate in MCT oil for SubQ use. A ready syringe does not change the rules. Exposure still has to stay inside the female physiologic band (Hatzilabrou, 2025; Medivant Health, n.d.).
The Target Is Narrow, Not “Bigger Is Better”
A healthy young woman typically has a total testosterone level of about 15 to 46 ng/dL. That is a sliver of the male range. The job of therapy is to land inside that band and stay there (Hatzilabrou, 2025; Braunstein et al., 2011).
Pushing past the ceiling does not add extra desire. It shows up as acne, extra facial hair, scalp thinning, voice change, and other androgen effects (Islam et al., 2019; Parish et al., 2021).
A practical path looks like this:
Confirm HSDD with real distress after other causes are checked.
Draw a baseline total testosterone with a sensitive LC-MS/MS test, not a routine immunoassay built for men (Rosner et al., 2007).
Start low.
Recheck the level and symptoms at about 8-12 weeks.
Assess benefit at 3 to 6 months. If distressing low desire has not improved, stop rather than climb (Davis et al., 2019; Parish et al., 2021).
Baseline testosterone does not diagnose HSDD. It is a safety tool once treatment starts (Hatzilabrou, 2025).
Two problems are often mistaken for low desire. Antidepressants, especially SSRIs, can blunt desire on their own. Genitourinary syndrome of menopause—dryness, atrophy, and pain with sex—can look like low desire when the real issue is pain. Local estrogen, not a systemic androgen, is built for that problem (Parish et al., 2021; Cedars-Sinai, n.d.).
What the Body May Gain Beyond Desire
Sexual function is the outcome with the firmest trial support. Other claims need a quieter voice.
Muscle and strength. Testosterone helps muscle protein building in both sexes. Some women report better lean mass and training response when testosterone levels return to a mid-physiologic range. Large pooled trial data in women have not shown a robust body-composition effect at the low doses used for HSDD, so frame this as possible support, not a guarantee (Islam et al., 2019; Hatzilabrou, 2025).
Bone. One small two-year implant trial found faster gains in spine, hip, and total-body density when testosterone was added to estradiol. Guidelines still do not list bone as an approved reason to prescribe it because the study was small and not designed to prevent fractures (Davis et al., 1995; Wierman et al., 2014).
Energy and mood. Early and smaller studies sometimes showed better well-being. Dedicated trials and systematic reviews have been mixed or null for mood, fatigue, and cognition. Societies do not endorse testosterone as a general menopause tonic (Islam et al., 2019; Dichtel et al., 2020; Cedars-Sinai, n.d.).
Red blood cells. Testosterone can raise red-cell production. That is a monitoring issue at higher exposure, not a reason to treat ordinary anemia in women (Hatzilabrou, 2025).
For the spine and joints, even modest improvements in muscle and bone health matter. Stronger hip and core muscles help the pelvis stay level. Better bone quality supports the vertebrae that a chiropractor adjusts. After a car crash, a work injury, or months of guarded movement, patients who can train without crashing energy often stay in rehab longer (Jimenez, n.d.-a).
Safety, Side Effects, and the Long View
Short- and medium-term data at physiologic doses are generally reassuring for the day-to-day effects clinicians watch: acne, extra hair, and oily skin. Those effects are usually dose-related and often fade if the dose is cut (Islam et al., 2019; Nachtigall et al., 2011).
What is missing is the long view. Adequately powered trials have not settled cardiovascular and breast outcomes over many years. That gap—not a proven harm signal—is a main reason no female product has been approved (Hatzilabrou, 2025; Cedars-Sinai, n.d.).
Therapy is not for pregnancy, breastfeeding, or people trying to conceive. Women with high baseline heart or breast-cancer risk need an especially clear shared decision (Hone Health Help Center, n.d.; Parish et al., 2021).
How Integrative Chiropractic Care Fits
Hormones don’t exist apart from the skeleton. Low energy, weaker muscles, and slower recovery make spinal joints stiffer and make rehab after an auto accident harder. Integrative care treats that loop instead of handing a woman only a syringe or only an adjustment.
At Injury Medical Clinic PA in El Paso, Texas (11860 Vista Del Sol, Suite 128), we build care as a team. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, is dual-licensed as a chiropractor and board-certified family nurse practitioner. His clinical writing stresses that female testosterone use is not a copy of male replacement: the best randomized evidence is still transdermal; SubQ use in women is an individualized off-label choice, and the goal is a physiologic range with a stop rule if desire does not improve (Jimenez, n.d.-b).
Dr. Maria Guadalupe Cardenas, MD, is his internist and is board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), with more than 40 years of experience. She serves as medical director and collaborative physician. In this model, the internist provides medical direction, reviews labs and overall health, and helps keep advanced or off-label therapies within safe bounds. The chiropractor restores joint motion, posture, and neuromuscular control. Functional medicine looks at sleep, gut health, thyroid, iron, and medications that can blunt desire. Personal injury and rehabilitation services rebuild strength after crashes, falls, and sports injuries, so a hormone plan isn’t asked to do the work of a weak core or an unhealed disc (Jimenez, n.d.-a).
That mix is common in integrated injury clinics: an MD directs the medical lane while a DC treats the mechanical lane. For a woman on low-dose testosterone, the practical payoff is simple. If the muscles around the spine hold better, adjustments last longer. When bone and lean mass improve, fall risk and “I feel fragile” complaints may ease. If pain and sleep improve, desire often has a clearer path—without pretending testosterone is a cure for every menopausal complaint.
A Clear Path Forward
Testosterone treatment in women is neither a wellness trend nor a male protocol scaled down by guesswork. It is a narrow, evidence-backed option for postmenopausal HSDD with distress, given at a female physiologic dose, watched with the right lab, and stopped if it does not help.
Subcutaneous injections can deliver that modest, steady dose into the fat under the skin. They ask for discipline: start low, measure, stay inside the range, and pair the hormone with the rest of the care—local vaginal treatment when dryness is the real problem, medication review when an antidepressant is the real problem, and hands-on musculoskeletal care when the spine and hips cannot carry the load.
In El Paso, that whole-person path is the point of the collaboration between Dr. Cardenas’s internal medicine oversight and Dr. Jimenez’s chiropractic, functional medicine, and injury rehab work. The hormone is only one tool. The goal is a woman who can move, recover, and feel like herself again.
Legal Peptides and Integrative Chiropractic Care: A Clear Guide
Abstract
This article explains legal peptide use in plain language. Legal peptide use means giving, making, or prescribing certain short chains of amino acids that regulatory bodies such as the Food and Drug Administration (FDA) have officially approved for medical use. Readers will learn how approved drugs differ from compounded products and research-only chemicals. The article then reviews the New Mexico Board of Nursing’s September 2026 peptide FAQs. It covers a valid patient-provider relationship, telehealth, advertising, nutrition, and muscle care. The last sections show how integrative chiropractors and nurse practitioners work together, and how Dr. Alexander Jimenez, DC, APRN, FNP-BC, and Dr. Maria Guadalupe Cardenas, MD, run that model at Injury Medical Clinic PA in El Paso.
What Legal Peptide Use Means
Peptides are short chains of amino acids. The body already makes many of them. They act like small messages that can change appetite, hormone release, inflammation, and tissue repair (Findlay, 2026; Vibrant Health of Colorado, 2026).
Legal peptide use means giving, making, or prescribing certain short chains of amino acids that regulatory bodies such as the Food and Drug Administration (FDA) have officially approved for medical use (Findlay, 2026; Peptide Laws, n.d.). In everyday terms, a peptide plan is safer when:
A regulator has officially approved that product for medical use.
A licensed clinician examines the patient and writes a prescription.
Any compounded version follows federal compounding law and state pharmacy rules.
The chart shows a reason, informed consent, and follow-up (ByrdAdatto, n.d.; LumaLex Law, n.d.).
Insulin, semaglutide, tirzepatide, tesamorelin, and bremelanotide (PT-141) are examples of peptides with FDA-approved products for specific conditions (Findlay, 2026; DJ Holt Law, 2026). Approval covers a product and its use. It does not make every similar vial on the internet legal.
Approved, Compounded, or Research-Only
FDA-approved medicines have finished clinical trials and manufacturing review. A clinician may use an approved drug off-label when science and judgment support that choice, but the product itself is still an approved drug (DJ Holt Law, 2026; ByrdAdatto, n.d.).
Compounded peptides are custom medicines made for one named patient when the law allows it. They are not FDA-approved. They may differ in formula, stability, and oversight (New Mexico Board of Nursing, 2026). After branded GLP-1 shortages eased, federal policy tightened around copies of those products (DJ Holt Law, 2026; Peptide Laws, n.d.).
Research-only chemicals are often sold as “not for human use.” Popular names include BPC-157, TB-500, and several growth-hormone secretagogues. That label does not make clinical use legal. The FDA treats marketing for human treatment as a drug claim (Findlay, 2026; LumaLex Law, n.d.). Status can also change as compounding committees review bulk substances (DJ Holt Law, 2026).
State boards rarely ban peptides as a whole class. They do ask whether the prescriber stayed in scope, did a real exam, and used a lawful pharmacy (Peptide Journal, 2026; ByrdAdatto, n.d.).
What the New Mexico Board of Nursing Said
In September 2026, the New Mexico Board of Nursing published clinical-practice FAQs on peptide therapies. The Board said the page is guidance, not a legal opinion, and it does not change the Nursing Practice Act (New Mexico Board of Nursing, 2026). The answers still give a clear map.
Key points include:
APRNs may prescribe compounded medicines within their population focus and prescriptive authority if they have the education and judgment to do so. The Board uses LACE: licensure, accreditation, certification, and education.
GLP-1 medicines are among the most watched peptides because they help and they carry risk.
A valid patient-provider relationship must exist before prescribing.
A compounded GLP-1 vial must stay patient-specific. It cannot be shared.
Pharmacies should be licensed and able to share sterility testing.
Patients must be told when a product is compounded rather than a brand-name FDA-approved drug.
Reckless prescribing—not peptide use alone—invites discipline (New Mexico Board of Nursing, 2026).
New Mexico grants nurse practitioners full practice authority. Texas generally requires a collaborating physician (Peptide Journal, 2026). The clinical standard still looks the same: exam, reason, consent, monitoring, and a clean pharmacy.
The Exam, Telehealth, and Honest Ads
The Board listed what should happen before GLP-1 or related peptide care starts (New Mexico Board of Nursing, 2026):
A health history and a review of current medicines
A check for higher-risk problems, such as family medullary thyroid cancer or MEN-2, pancreatitis, gallbladder disease, kidney disease, pregnancy plans, eating disorders, or frailty
A physical exam and baseline labs when they are needed
Consent that covers benefits, common side effects, serious risks, other options, how long care may last, lifestyle changes, and weight regain after stopping
A written plan and later checks of weight, nutrition, tolerance, and dose
Telehealth can be used when the standard of care is still met. A questionnaire alone is not enough. The prescriber must also be licensed in the state where the patient is located (New Mexico Board of Nursing, 2026). Ads must be truthful. Claims of guaranteed weight loss do not meet professional standards. The Federal Trade Commission watches those claims (New Mexico Board of Nursing, 2026). A med-spa name does not change the duty of the person who evaluates and prescribes.
Food and Muscle Still Come First
The Board was clear: medicine is not the whole treatment. Providers should counsel patients on protein, resistance exercise, lean-mass protection, vitamins, and long-term habits. Skipping that work can lead to muscle loss, frailty, and poor results after the drug stops (New Mexico Board of Nursing, 2026). Integrative clinics make the same point. Peptides work best when you address food, sleep, and movement (Nourish House Calls, n.d.; Evolution Integrative Medicine, n.d.).
How Integrative Chiropractic Care Fits
Teams of integrative chiropractors and nurse practitioners (NPs) work together in integrative medical offices. Most of the time, chiropractors do the manual therapies, biomechanics, and structural rehabilitation. Nurse practitioners, on the other hand, conduct clinical evaluations and have the medical authority to prescribe and oversee therapies (ProCredits, n.d.; Jimenez, 2026a). That split protects both the patient and the license.
Chiropractic care links to peptide treatment by making muscles and bones stronger:
Adjustments and mobilization restore joint motion and lower mechanical stress on nerves and soft tissue.
Better motion lets a person load a tendon, hip, or spine pattern with less guarding.
Rehab—easy isometrics, then controlled loading—tells muscle, tendon, and bone to remodel.
Protein-forward eating provides the building blocks those tissues need.
A legal metabolic peptide, when indicated, may help appetite, blood sugar, and body composition so rehab is easier to finish.
Any tissue-support peptide is an add-on to loading, not a replacement for it (El Paso Back Clinic, n.d.; Gruber Chiropractic, n.d.).
Dr. Jimenez has written that peptides should not be sold as a shortcut to grow cartilage, discs, or ligaments. Food cannot unlock a stuck joint. An adjustment cannot replace protein. Each tool has a job (Jimenez, 2026a).
The El Paso Team: Dr. Jimenez and Dr. Cardenas
Injury Medical Clinic PA in El Paso shows how those roles work in daily care. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, is a dual-licensed chiropractor and board-certified family nurse practitioner. He leads conservative care, rehabilitation, functional medicine, and personal-injury documentation (Jimenez, n.d.).
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine (NPI #1164426749; Texas MD License #J2933). With more than 40 years of experience as an internist, she serves as medical director and collaborative physician. This multidisciplinary setup is common in integrative or injury clinics, where an MD provides medical direction alongside a chiropractor. The team integrates chiropractic care from Dr. Jimenez with medical oversight by Dr. Cardenas, plus functional medicine, personal injury care, rehabilitation, and related services (Jimenez, n.d.; El Paso Back Clinic, n.d.).
A simple path for crash, sports, or chronic back pain recovery looks like this:
Map the problem with history, exam, and movement testing.
Restore motion with chiropractic and soft-tissue care.
Rebuild muscle and bone loading with graded rehab.
Address nutrition and metabolic gaps.
Add a legal, patient-specific peptide only after the reason, labs, and consent are on the chart.
Clinical Observations on Strength and Recovery
Clinical observations shared by Dr. Jimenez describe peptides as possible signaling helpers, not magic. Progress often looks better when spinal care is paired with inflammation control, body-weight support, protein intake, and sleep (Jimenez, 2026a; El Paso Back Clinic, n.d.). Other clinics describe peptides for recovery, metabolism, gut integrity, sleep, and connective tissue (New Life Physicians, n.d.; RevitalIV, n.d.). Those descriptions are not the same as FDA approval. Patients should ask which product is approved, which is compounded for them alone, and which is still experimental.
Questions to Ask Before Starting
Before any peptide begins, ask four plain questions:
Is this an FDA-approved product or a compounded one?
Who is the licensed prescriber, and which state does the patient live in?
What exam, labs, and follow-up will I receive?
How will chiropractic care, exercise, and nutrition work with the medicine?
Boards expect those answers in the record (New Mexico Board of Nursing, 2026; ByrdAdatto, n.d.). Legal peptide use is a medical act. Integrative chiropractic care is a movement and strength act. When a clinic keeps both lines clear, patients build stronger muscles and bones—and, when appropriate, receive carefully chosen peptide support without a gray-market detour.
Abstract
Subcutaneous testosterone injections place hormone therapy in the fat layer just under the skin instead of deep inside a muscle. Men and women can both receive this type of shot when a clinician decides it is appropriate. The smaller needle is often easier to use at home, and weekly levels can stay more even than with a deep muscle shot. This article explains how the method works, how testosterone supports muscle and bone, and how integrative chiropractic care in El Paso can sit beside medical hormone care. It is an option for people who don’t want pellets or a deep intramuscular injection.
What a Subcutaneous Shot Is
A subcutaneous (SubQ) injection goes into the thin layer of fat beneath the skin. Common sites are the belly and the outer thigh. The needle is short and thin. An intramuscular (IM) shot goes deeper into muscle, often the glute or thigh, and usually requires a longer needle.
Both routes can use the same familiar esters, such as testosterone cypionate or enanthate. The medicine is not a brand-new drug. The change is where the oil sits. Fat has less blood flow than muscle, so the hormone often leaves the depot more slowly. Average blood levels can land in a similar place. The shape of the week is often calmer.
For about eighty years, deep muscle injection was simply the habit. In The Quiet Case for the Subcutaneous Needle, Dr. Thomas A. Hatzilabrou, M.D., of Worldborne Medical, makes a narrow claim: move the same ester from muscle to fat, and therapy can become easier to live with without giving up the average level guidelines care about (Hatzilabrou, n.d.).
That claim is about a route, not a brand.
Why the Weekly Curve Matters
The Endocrine Society and the American Urological Association tell clinicians to restore testosterone to a mid-normal range in men who truly need treatment, match the plan to the person, and check labs on a schedule.
Two plans can share the same average and still feel like different weeks. A deep IM shot can spike high, then sag before the next dose. People feel that sag as low energy, low mood, or a crash. Modeling of testosterone enanthate found that SubQ dosing blunts that peak-to-trough swing. The average is the number on the lab report. The swing is the number a person lives in (Hatzilabrou, n.d.; Figueiredo et al., 2022).
A review found SubQ testosterone to be feasible, practical, and reasonable for routine use, with comparable mean levels. A 52-week study of weekly SubQ enanthate found that 92.7% of men were in the target range by week 12, and more than 95% reported no injection-related pain.
One dosing rule matters at every switch visit. A milligram under the skin may not equal a milligram in the muscle. After a change, assess the level and how the person feels. Do not assume syringe-for-syringe equality.
SubQ Testosterone for Men and for Women
Both men and women can receive SubQ testosterone when a licensed clinician chooses that plan. The smaller needle is often more convenient for women and for anyone who prefers not to receive a deep glute injection.
The research is not even, and that honesty belongs here.
In men with low testosterone, SubQ shots have produced target-range levels and better comfort than IM.
In gender-affirming care, people who switched from IM to SubQ often preferred SubQ, and levels still reached the intended range.
In women, no testosterone product is FDA-approved in the United States. Use is off-label. The goal is a physiologic, premenopausal-range level—not a male dose. The strongest randomized evidence in women is still transdermal gel, not injection (Hatzilabrou, n.d.).
So SubQ can be easier as a technique. It is not automatically the best-proven female route. Any plan in women should stay inside a safe female range, with labs to prove it. Start low. Go slow. Watch skin, hair, voice, and mood.
What This Route Wins On
If average exposure is close to a tie, daily life breaks the tie.
A short, fine needle is easier to use on your own.
Pain and dread before the shot are usually lower.
There is no awkward reach to the glute and less concern about the sciatic path.
The week can feel steadier.
Cost can stay low because the same generic esters are used.
There is no skin-to-skin transfer risk like gels and patches.
Needle fear is common. It turns a five-minute task into the one a person keeps putting off. A delayed dose becomes a missed dose. A missed dose becomes “this isn’t working.” An easier shot is not a luxury. It is how long-term care survives.
Safety does not get lighter because the needle is shorter. High red-cell count, fertility changes, prostate checks in men, and androgenic effects in women track with the hormone level, not with “IM versus SubQ.” Monitoring stays the same.
How the Home Shot Is Done
A clinician teaches the first doses. The usual steps are simple:
Wash hands. Set out a clean syringe, a short needle (often 25- to 30-gauge and about half an inch), an alcohol wipe, and a sharps container.
Choose a clean site on the abdomen or outer thigh. Rotate sites.
Pinch a fold of skin. Insert the needle at about a 45-degree angle. Inject slowly.
Do not share syringes. Place used needles in a sharps box.
Xyosted is one FDA-cleared weekly auto-injector for men that is used in the abdomen. Some clinics use compounded syringes. The treating clinician still manages the dose, storage, and follow-up.
This method is straightforward for people who don’t want pellet placement or a deep muscle shot. It is still an injection. It is a middle-path option.
What Testosterone Does for the Body
Testosterone helps the body maintain lean muscle, support bone health, recover after strain, and maintain energy and drive. When levels stay too low, people often feel weak, foggy, and slow to bounce back. Stairs feel taller. Rehab after a sprain, a fall, or a car crash lasts longer.
That is the link to musculoskeletal health. Weaker muscles mean less support around the spine, hips, and knees. Joints take more load. Guarding becomes a habit. Sleep and mood often fall with the strength loss.
A steadier hormone curve does not replace exercise or alignment work. It can give muscle and bone a clearer internal signal while those programs run.
How Integrative Chiropractic Care Fits
Hormone therapy works inside the body. Chiropractic care works on the frame that carries the body.
When the spine and pelvis are restricted, muscles stay tight. Joints load on one side. The nervous system stays loud. That mix can blunt the gains people hope to see from hormone care. Integrative chiropractic care aims to restore motion, ease muscle tightness, and improve how the body shares load. Strength work then has a better platform for these gains.
In my clinical observations, patients often report easier hip and low-back mechanics after treatment for spinal and pelvic restrictions alongside other therapies. I have also seen some men do better when large, infrequent depot shots are changed to smaller, more frequent SubQ doses. The mid-cycle crash—fatigue, irritability, a sense that “the shot wore off”—often settles when the curve flattens. Labs still decide the number. The person decides whether the week feels livable (Jimenez, n.d.).
Chiropractic care does not replace testosterone. Testosterone does not replace an adjustment, a rehab plan, or a strength progression. Together they treat the signal and the structure.
The El Paso Team Model
Injury Medical Clinic PA uses a multidisciplinary model. I serve as clinical director, a chiropractor, and a board-certified family nurse practitioner. Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933). She has more than 40 years of experience as an internist and serves as medical director and collaborative physician.
This setup is common in integrative and injury clinics. The MD provides medical direction, internal medicine risk review, and hormone oversight. The chiropractic and rehab team addresses alignment, soft tissue, personal injury recovery, and return to work or sport. Functional medicine adds labs, nutrition, sleep, and gut-muscle links so the plan isn’t just a shot.
A person in this model may move through:
Medical review of symptoms, medicines, fertility goals, and safety screens
Targeted hormone and metabolic labs
Chiropractic care for spinal and pelvic mechanics
Rehabilitation for strength, balance, and daily demands
Nutrition and recovery habits that support hormone work
Follow-up labs for testosterone, hematocrit, and PSA when indicated
Main East Side clinic: 11860 Vista Del Sol, Suite 128, El Paso, TX 79936. Office: 915-850-0900 or 915-412-6677.
Who This Option May Suit
SubQ testosterone may be worth a supervised talk when:
Labs and symptoms support treatment, and the person can learn a home shot.
Deep IM shots cause pain, fear, or missed doses.
Pellets feel like too much commitment or are difficult to fine-tune.
Gels are messy or raise transfer concerns at home.
The goal is a steadier week, not a bigger peak.
It is a poor first choice when fertility is an immediate goal, when there is a prostate or breast cancer concern, when hematocrit is already high, or when a woman needs the route with the strongest female trial data. Those calls belong in the clinic.
Conclusion
The quiet case for the subcutaneous needle is simple. Same ester. Different depot. Comparable average levels for many patients. It’s a shot that most people can keep getting. Pair that with integrative chiropractic care, and the aim isn’t just a better lab printout. The aim is a body that can still move.
This article is educational. The FDA does not review compounded medicines in the same way it reviews approved branded products. The prescribing clinician makes final treatment decisions after a full evaluation.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine