The Hip That Hurts After Sitting: Is Your Low-Back Problem Actually Being Driven by the Hip?
Abstract: Prolonged sitting holds the hip in flexion, reduces usable hip extension, and can force the lumbar spine to move more than it should. Programmers, engineers, data analysts, gamers, and remote workers often feel these symptoms as front-of-hip tightness, buttock discomfort, or low-back pain after a long session. This article explains those mechanics and when structural care, mobility, strengthening, or decompression belong in the plan.
The call ended an hour ago. You are still in the chair. When you stand, the front of one hip feels pinched, the buttock feels thick, and the low back won’t straighten. A few steps later, the back eases. That pattern is common in people who sit to think. It doesn’t prove that every desk worker has tight hip flexors. Sitting changes the hip, but a stretch does not automatically repair the spine.
What Sitting Does to the Hip
Sitting is a flexed-hip posture. The thigh stays bent toward the trunk, often near 90 degrees, for hours, and the tissues around the hip adapt to that demand (Chamberlain, 2021).
The hip is designed for large ranges of motion. The lumbar spine is built for a smaller, more controlled range.
In a typical sit, the pelvis tilts backward slightly and lumbar lordosis decreases. That sit-to-stand strategy is normal, not a diagnosis by itself (Devin et al., 2012).
Perching on the chair edge or gaming with a collapsed trunk keeps the hip bent while the low back flexes or twists.
Front-of-hip tissues can feel short because they have been held short, because the joint does not tolerate end-range flexion, or because a lumbar nerve refers symptoms to the groin or buttock.
The useful question is not “Are the hip flexors tight?” It is “Where is motion missing, and what is setting the limit?”
When the Hip Cannot Extend, the Low Back Often Pays
Hip extension takes the thigh behind the body. Walking needs only about 10 to 15 degrees of that motion. If the hip does not extend, the pelvis and lumbar spine often finish the job by extending or rotating more than they should (Gómez-Hoyos et al., 2020).
That is the core of hip-spine thinking. Offierski and MacNab described coexisting hip and lumbar problems that can mimic, amplify, or hide each other (Offierski & MacNab, 1983). Later reviews add a practical rule: if the hip cannot supply sagittal motion, the lumbopelvic region often will (Devin et al., 2012).
For a desk-based engineer or analyst, the day can look like hours of hip flexion, brief standing with a hip that no longer extends easily, extra lumbar motion to keep the trunk upright, and a return to the chair before the hip practices the missing motion. People with low back pain often show reduced hip range of motion and weaker hip extensors and abductors than pain-free adults (Pizol et al., 2024). That does not make the hip the villain in every case. It does show that the hip and low back share a job.
Reduced Gluteal Capacity Is a Loading Problem
The gluteal muscles extend and stabilize the hip. In sitting, they are lengthened, unloaded, and rarely asked to produce force. Capacity drops because they are undertrained for controlling the pelvis when you stand or walk. If the hip cannot create or control extension, lumbar extensors often work harder. The back starts doing a hip job. That can feel like a tight belt after a long coding block or a late gaming session.
Adding hip strengthening to a low-back plan can reduce pain and disability in nonspecific low back pain (Santamaría et al., 2023). That is not a reason to load the glutes on day one. If the hip joint is irritated, aggressive bridging can increase groin pinch instead of building capacity.
Hold four targets at once: the hip needs motion, the gluteals need force and endurance, the trunk needs to stabilize instead of steal extra motion, and the workday needs more than one posture.
Tight Muscle, Stiff Joint, or Nerve Irritation?
A stretch that feels good in the front of the hip does not identify the source.
Adaptive muscle stiffness
The front-of-hip muscles have spent the day in flexion. They may resist lengthening when you stand. Symptoms often ease after walking, without catching or a sharp groin pinch at the end of range. This is the usual tight-flexor pattern, not the only one.
Hip joint limits
Intra-articular problems such as femoroacetabular impingement, labral irritation, or early degenerative change often prefer the groin. Sitting, crossing the legs, or tying a shoe can pinch. Clicking or limited internal rotation raises concern that the joint, not just the muscle, is setting the barrier (Chamberlain, 2021; Enseki et al., 2023).
Extra-articular hip pain
Lateral hip pain with side-lying or stair climbing can point toward gluteal tendon irritation. Deep buttock pain can come from posterior hip muscles, the sacroiliac region, or referred lumbar symptoms.
Nerve-related pain
A lumbar disc or irritated nerve root can send symptoms into the buttock, thigh, or groin. Numbness, tingling, shooting pain, or true weakness are not flexor tightness. They need a spinal and neurological exam.
Seek prompt evaluation for fever, unexplained weight loss, unchanging night pain, progressive weakness, or bowel or bladder changes. Those signs are not stretch problems.
A Direct Plan That Respects Both Regions
El Paso Back Clinic treats this as a mechanical problem first. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, evaluates spinal motion, hip motion, strength, and nerve signs in the same visit. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, provides medical direction when findings suggest more than postural overload.
A useful exam compares hip and lumbar motion, sit-to-stand quality, single-leg control, and nerve tension tests. The goal is to decide whether the low back is primary, the hip is primary, or both share the load. That is beneficence: treat the driver, not only the loudest complaint.
Chiropractic structural care can improve joint mechanics in the lumbar spine, pelvis, and hips when restriction is present. The intent is to give each region its own range so one area stops compensating for the other. Gentle hip mobilization may help when the capsule, not the muscle, is the barrier. Aggressive end-range stretching is a poor first choice if groin pinching suggests impingement.
Mobility work should look like the missing task: hip extension without extra lumbar arching, rotation without twisting through the lowest lumbar joints, and sit-to-stand without a lurch. Movement variability—standing, walking, sitting, and changing sides—reduces the hours the hip spends in one angle.
Once pain allows, training should include quiet hip hinges or bridges, side-lying or standing abduction, split-stance work that asks one hip to extend, and trunk endurance that resists motion instead of creating it. A programmer who sits for ten hours does not need a max squat in week one. They need a hip that can stand and walk without handing the job to the low back.
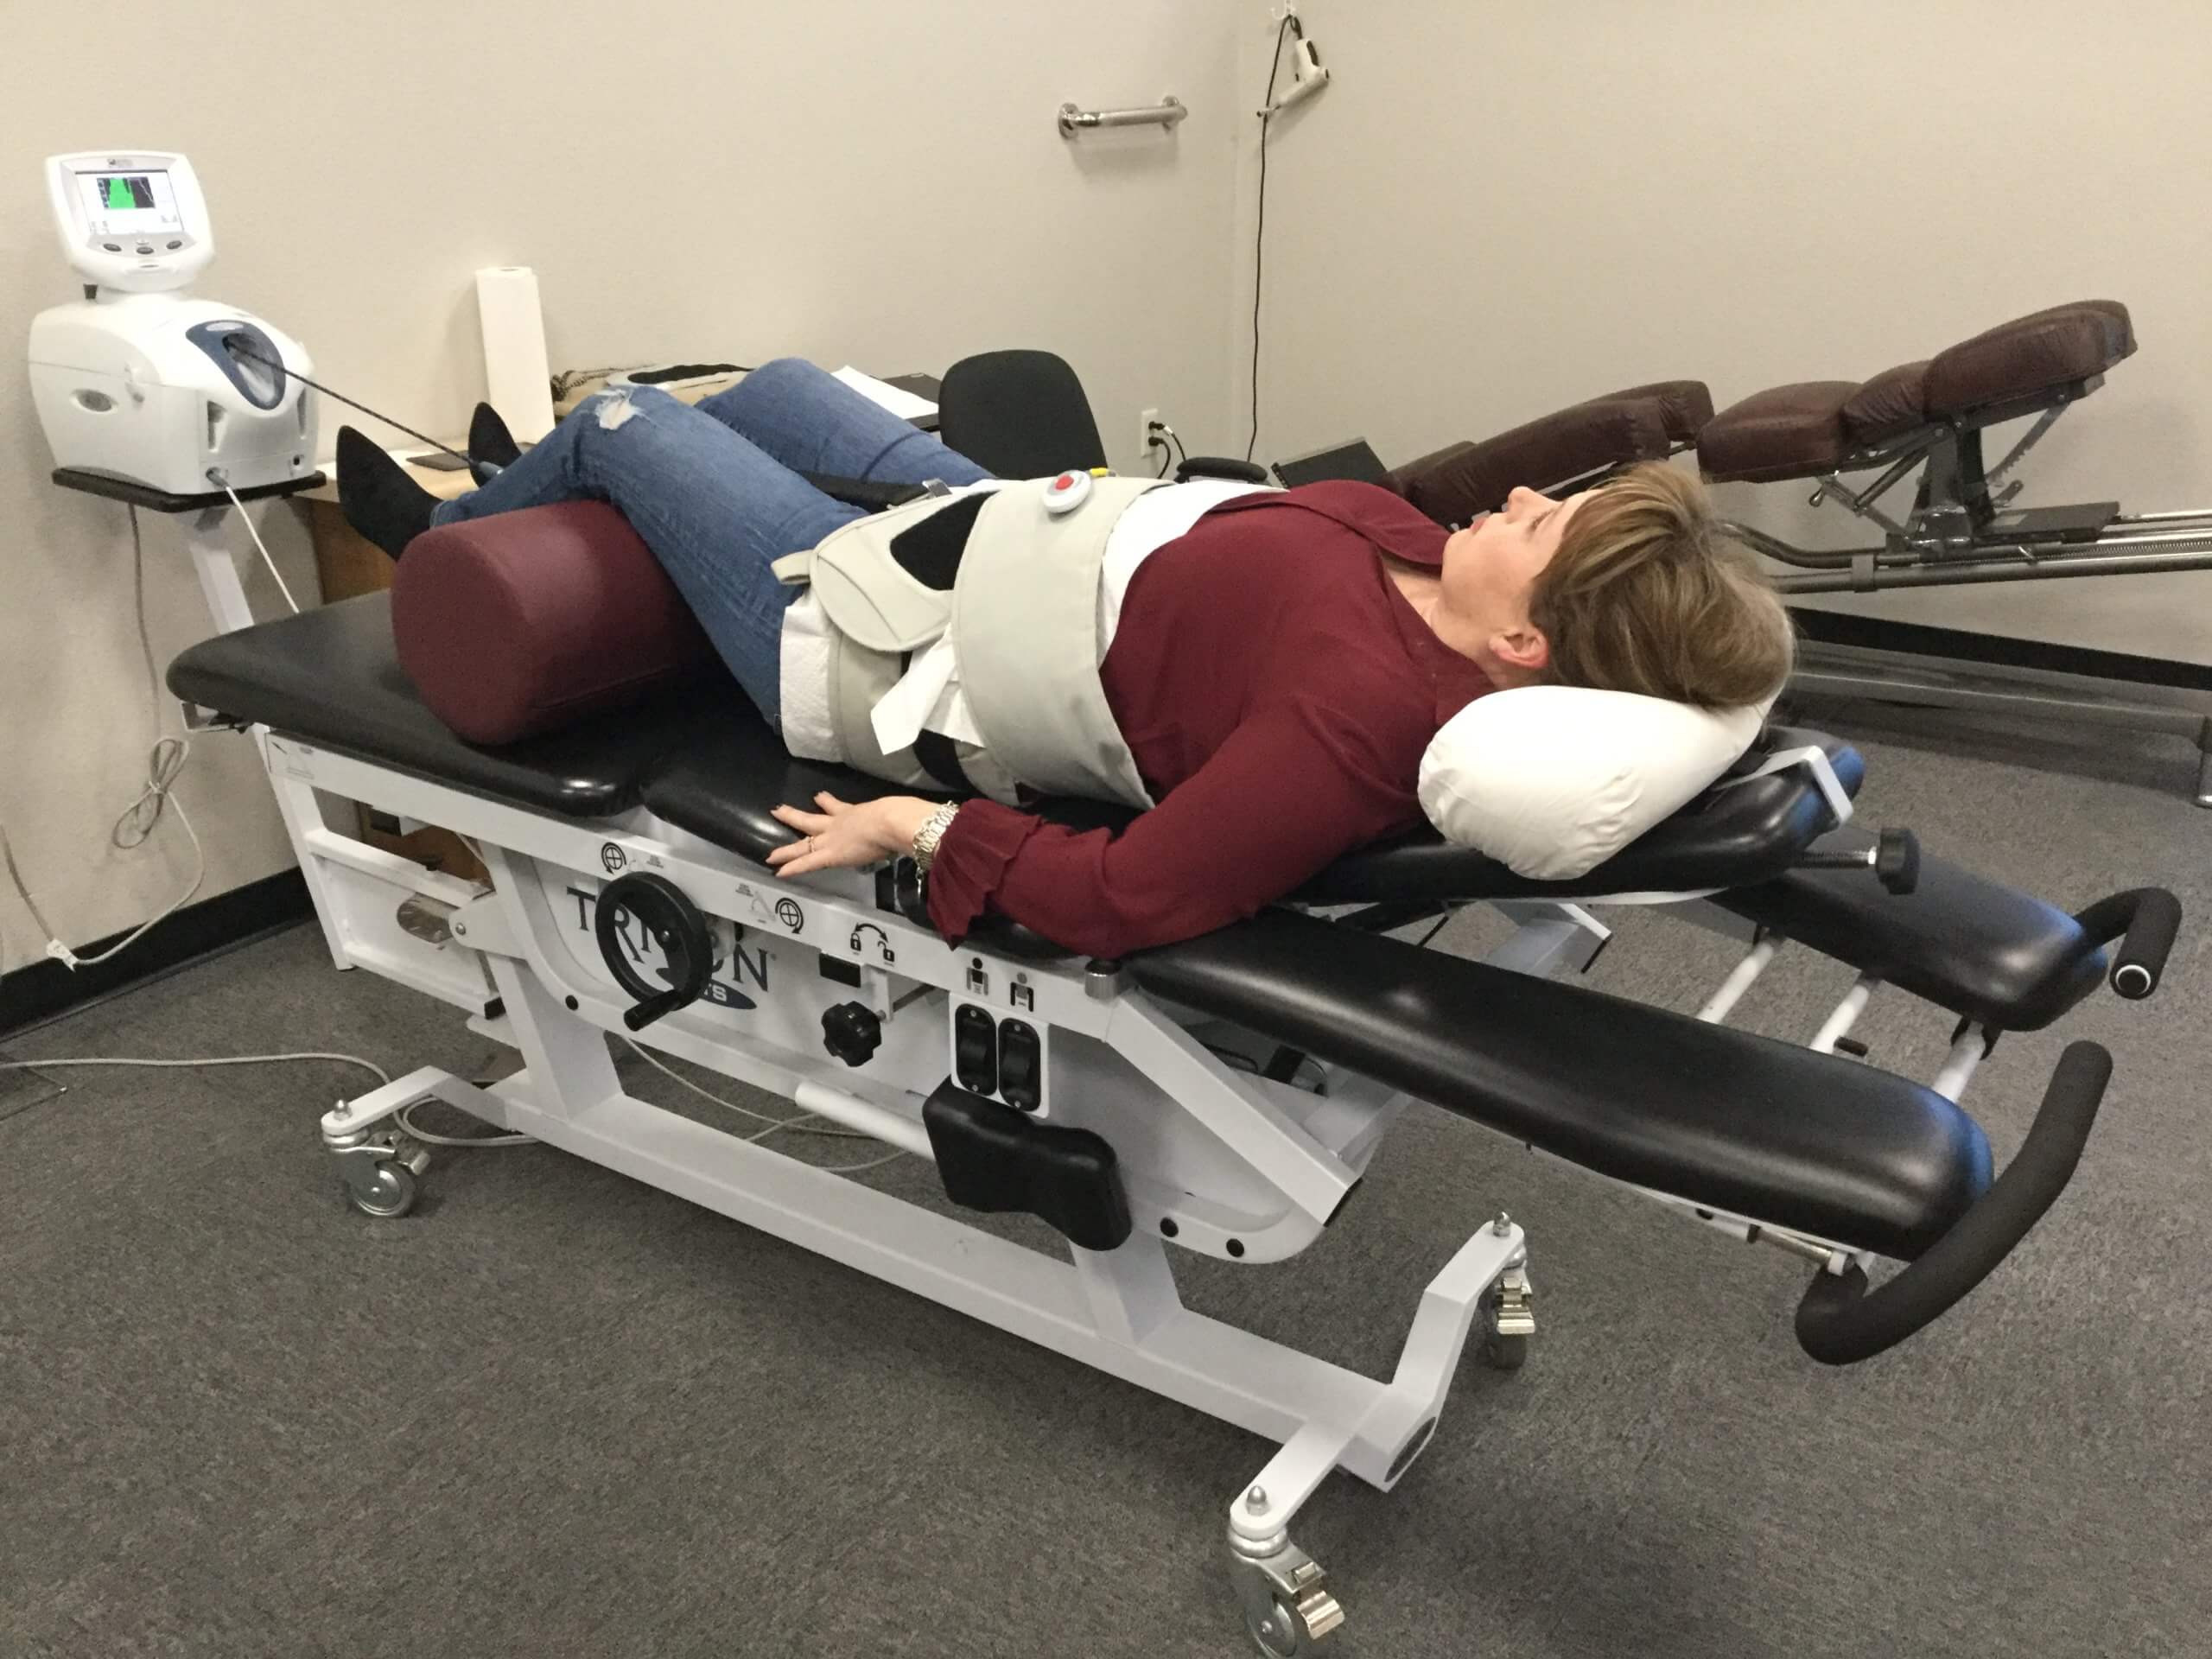
Non-surgical spinal decompression is a targeted tool for disc-related compression and selected nerve findings. It is not a default treatment for a stiff hip. If an exam and imaging support a disc or stenosis driver, decompression may reduce neural irritation while rebuilding capacity. If the spine is quiet and the hip is the limiting factor, the plan should focus on the hip. Choosing a non-invasive path first can reduce the rush toward long-term medication or surgery when those steps are not required. That is how the plan avoids adding risk the patient does not need.
What You Gain When Both Regions Share the Work
The outcomes patients want are practical: stand after a long review without grabbing the chair, walk without a chopped stride, and sit through focused work without a pinched groin or a locked low back. The hip should supply motion and force. The low back should supply controlled motion and stability.
Autonomy means you leave with a map: which symptoms are reasonable to train through, which signs should stop a stretch, and how this plan can sit alongside the care you already receive from your medical team.
Next Step With the El Paso Back Clinic Team
If sitting leaves a mark on the hip or low back, a focused exam can separate a short, adapted muscle from a joint or nerve problem. That is the difference between stretching what is loud and treating what is driving the load. Schedule an evaluation with Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, and the collaborative medical team directed by Dr. Maria Guadalupe Cardenas, MD, so structural care, hip mobility, progressive strengthening, and—only when spinal findings justify it—decompression can be matched to your exam, not to a generic desk-stretch list.
Devin, C. J., McCullough, K. A., Morris, B. J., Yates, A. J., & Kang, J. D. (2012). Hip-spine syndrome. Journal of the American Academy of Orthopaedic Surgeons, 20(7), 434–442.
When the Standing Desk Starts Hurting: Why Standing All Day Is Not the Opposite of Sitting All Day
Abstract
Buying a standing desk feels like a solution. For many programmers, engineers, remote workers, and analysts, it is not. This article explains why standing all day is not the opposite of sitting all day. It covers static loading, lumbar compression, hip position, foot fatigue, and movement variability, then shows how a structural exam, chiropractic care, decompression when indicated, and trunk-hip conditioning shift the load away from the furniture.
You did the responsible thing. After months of low-back tightness at the keyboard, you raised the desk and promised to stand through stand-ups and tickets. For two weeks it felt like progress. Then the low back felt heavy by afternoon, one hip locked, and the feet ached. By dinner, standing no longer felt like relief.
That pattern is common among programmers, engineers, remote workers, and analysts who treat furniture as the solution. A standing desk can be useful. It is not a cure. The spine needs a changing load, not one perfect posture.
The Myth of the Perfect Desk Posture
The sales pitch is simple: sitting compresses the discs, and standing unloads them, so more standing should mean less pain. The body does not work that way.
Sitting and standing are both static postures. In both, the pelvis, lumbar segments, and hips hold a relatively fixed shape while the eyes stay on a screen. The muscles that keep you upright do not rest. They hold. After enough minutes, they fatigue, the pelvis drifts, and the lumbar curve collapses or over-arches. Pain follows the drift, not the desk brand.
Research on sit-stand workstations is mixed. Some reviews show a modest drop in low-back discomfort when people alternate positions (Agarwal et al., 2018). A Cochrane review of workplace standing and walking interventions found no clear reduction in musculoskeletal symptoms (Parry et al., 2019). Changing position tends to matter more than choosing one “better” position and staying there.
What Static Loading Actually Does
Static loading means a tissue is compressed, stretched, or contracted without enough change in length or force. Holding a grocery bag with a straight arm is the same idea. The bag is not heavy. The hold is.
In a standing workday, that holds stacks up:
The lumbar discs and facet joints accept a steady compressive force.
Hip and gluteal muscles co-contract to keep the pelvis from tipping.
Calves and foot muscles lock to keep you from swaying.
Blood return from the lower legs slows because the muscle pump is not cycling during walking.
Prolonged constrained standing has been linked to low-back discomfort, leg fatigue, foot pain, and venous pooling (Waters & Dick, 2015; EU-OSHA, 2021). Standing more than about four hours a day, especially without walking breaks, is also associated with a higher risk of chronic venous problems (Hirsch et al., 2024). The standing desk concentrated these loads into eight hours of “optimal posture.”
Lumbar Compression: Sitting Is Not Always Worse
Classic studies suggested sitting raised disc pressure compared with standing. A 2022 systematic review found that sitting often produces higher pressure in healthy discs, but later studies and studies of degenerated discs often show little difference between the two postures (Li et al., 2022).
That matters if you already have disc irritation or chronic lumbago. Switching desks may not unload the segment that hurts. Locked knees, a forward head, and a distant mouse can raise lumbar shear even as you feel “more active.” Laboratory work found standing produced the most fidgeting and the highest front-to-back shear, while both prolonged sitting and prolonged standing increased low-back discomfort (Le & Marras, 2016; Park & Srinivasan, 2021). Alternating sit-stand blocks changed trunk stiffness and muscle activity more favorably than either posture alone.
If your low back hurts after two hours of sitting, two hours of standing is not automatically medicine. It is a different static load.
Hips, Feet, and the Standing Fatigue Pattern
Desk workers who stand for long blocks often describe a cluster:
A dull lumbar ache below the belt line
One hip that feels pinched or stuck
Tightness across the front of the thighs
Heaviness in the calves
Tired, hot feet by mid-afternoon
Standing with the pelvis tucked under flattens the lumbar curve and keeps the hip flexors short. Standing with an exaggerated arch jams the lumbar facets. Neither version includes the motion those joints were built for: flexion, extension, rotation, and weight shift. Without walking, the calf pump is quiet, fluid pools, and the plantar fascia takes a continuous load. A thick mat can delay the complaint. It does not remove the need to move.
Movement Variability Beats Longer Standing
Tissues tolerate changing forces better than identical forces. Discs like cycles of load and unload. Hips like a changing angle. Feet like a push-off.
A useful work block is not “stand until it hurts, then sit until it hurts.”
Sit for focused typing with the lumbar curve supported.
Stand for shorter review or call blocks with soft knees and weight shifting.
Walk two to five minutes between tickets or meetings.
Change the mouse side or foot position before symptoms peak.
The goal is not to collect standing minutes. The goal is to interrupt the hold.
Change the Load, Don’t Just Change the Furniture
A standing desk is a tool. So is a chair. Neither one evaluates a stiff thoracic spine, a rotated pelvis, a weak hip abductor, or a disc that does not tolerate axial load.
El Paso Back Clinic starts with the structure, not the catalog. A focused exam looks at lumbar motion, hip extension and rotation, trunk endurance, foot and ankle stiffness, and nerve tension if pain travels into the leg. Imaging and medical screening are added when red flags appear.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, evaluates both the mechanical pattern and the medical context. His dual licensure as a Doctor of Chiropractic and a board-certified Family Practice Nurse Practitioner allows structural care to work alongside appropriate diagnostics. Dr. Maria Guadalupe Cardenas, MD, Board-Certified in Internal Medicine, provides medical direction and laboratory oversight when metabolic or vascular issues could be amplifying fatigue or delaying recovery.
That collaboration is the ethical core of the visit. Beneficence means the plan exists to restore function and spare a larger intervention the patient may not need. Non-maleficence means starting with non-invasive, drug-sparing options instead of unnecessary surgery or long-term medication dependence. Autonomy means the patient sees the findings and chooses the next step with their existing medical team still in the loop.
What Care Looks Like When the Desk Is Not the Diagnosis
Chiropractic structural care
Adjustments and mobilization restore motion where the lumbar spine, pelvis, and hips have locked into a standing or sitting pattern so one joint is not doing the work of three.
Non-surgical decompression when indicated
If exam and imaging point to disc-related lumbago or radicular irritation, computer-guided non-surgical spinal decompression may be appropriate. In selected patients, adding decompression to standard physical care has improved pain, motion, endurance, and function compared with physical therapy alone (Amjad et al., 2022; Schueren et al., 2025). It is a targeted option when disc load, not furniture, is the limiter.
Mobility and progressive trunk-hip conditioning
Remote workers and engineers also need hip extension they can use at a desk: split-stance hip-flexor and calf lengthening, thoracic rotation, ankle rocks, and pain-free lumbar motion. Once irritability drops, the program targets weak areas with hip abduction, anti-extension trunk work, sit-to-stand control, and short carries.
A Practical Desk Reset
You do not need a new desk to start changing the load.
Cap uninterrupted standing at 20 to 30 minutes until hips and feet tolerate more.
Cap uninterrupted sitting the same way.
Use shoes with a stable heel if you stand at home.
Raise the monitor so you don’t fold your neck.
Walk during calls that do not require a shared screen.
Stop standing the moment the low back starts to brace. Bracing is a warning, not a badge.
If pain, numbness, or leg heaviness persists after you rotate positions, bring that data to a structural exam.
The Point
Desk workers did not fail the standing desk. Sitting overloads the lumbar spine in one pattern. Standing overloads it in a different way. The solution is a spine, pelvis, and hip complex that can change shape, share load, and recover. Change the load. Do not just change the furniture.
If standing still leaves a heavy low back, a locked hip, or tired legs, schedule a structural evaluation at El Paso Back Clinic. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, and Dr. Maria Guadalupe Cardenas, MD, coordinate chiropractic alignment, decompression when indicated, mobility training, and medical oversight on one plan. Bring your desk-setup notes and leave with a load strategy for Monday.
The Server-Rack Crouch: How Mid-Back Stiffness, Hip Restriction, and Awkward Reaching Overload the Lumbar Spine
Abstract: Data center technicians and network engineers crouch behind racks, kneel on hard floors, pull cables, and lift gear in tight aisles. When the mid-back cannot rotate, and the hips cannot flex well, the lumbar spine takes on extra bend, twist, and shear. This article maps that kinetic chain, shows what a structural exam should measure, and outlines alignment, mobility work, mechanical rehab, lifting strategy, and spinal decompression to keep a mechanical problem from becoming a disc or nerve injury.
The job does not look like heavy construction. You slide a switch into a dim rack, kneel to dress fiber, and then stand when a ticket hits. By day three, the low back feels thick and unreliable. Calling that “bad posture” does not tell you what to change.
The real issue is load sharing. The lumbar spine is built to carry compression and resist excess rotation. It is not built to supply the turn your mid-back should provide, or the hip bend your hips should provide, while you also reach and lift. When those neighbors stiffen, the low back becomes the available joint—and available joints get overloaded.
The Kinetic Chain Behind the Rack
Treat the trunk as a three-part system.
The thoracic spine and rib cage should rotate and extend so the arms can reach without dragging the pelvis.
The hips should flex and extend so you can drop or rise without folding the lumbar discs to their end range.
The lumbar spine should stay relatively stable while those two regions move.
When thoracic rotation is limited, the trunk borrows from the lumbar segments. Mobilizing restricted thoracic joints increases thoracic rotation and reduces lumbar rotation during the same turn (Yasuda et al., 2023). Modeling also shows that a stiffer thoracic spine raises lumbar disc stress and L5 pars stress (Morimoto et al., 2024). That is the server-rack crouch: you rotate to see a port, the ribs do not turn, and L4–L5 or L5–S1 supplies the missing degrees.
Hip restriction writes the same story in the sagittal plane. If hip flexion is short, a squat or kneel-to-stand uses extra lumbar flexion. Available hip flexion is linked to how much the lumbar spine flexes during a squat lift (Patterson et al., 2022). People with poorer hip and lumbar mobility also place higher bending stress on the spine during everyday lifts (Dolan & Adams, 1993). On the floor, this means hinging to pick up a box rather than rounding through the belt line.
Awkward reaching multiplies both problems. A reach around a rack post is flexion plus rotation plus a long lever. Confined-space research shows spinal load stays high in restricted height, though kneeling can cut shear compared with stooping because the trunk can stay more upright (Weston et al., 2020). Behind a rack, you often experience the worst mix: a stooped torso, rotated shoulders, and a load at arm’s length, then a sudden stand.
Why This Pattern Progresses
A single shift rarely herniates a disc. The pattern does. Repeated end-range lumbar flexion and rotation under load stress the annulus, facets, and ligaments. Over months, you may notice morning stiffness, a catch when standing from a kneeling position, or buttock pain after a long pull. Those are mechanical warnings. If the segment keeps moving past its useful range while a disc is already irritated, nerve roots can become inflamed. That is a load problem, not “tight muscles.”
What a Structural Assessment Should Measure
A useful exam maps missing motion and excess motion.
Mid-back and rib cage
Seated and quadruped thoracic rotation with the pelvis held still
Thoracic extension, watching for lumbar substitution
Rib and segmental joint play through the levels used in reaching
Hips and pelvis
Hip flexion, extension, and rotation
Hip-hinge quality from standing and from a half-kneel
Pelvic control during sit-to-stand and floor-to-stand
Lumbar spine and nerves
Segmental motion and tenderness
Repeated-movement testing to see whether flexion or extension changes symptoms
Nerve tension signs if pain or tingling travels below the knee
Imaging and a neurologic exam when weakness or progressive numbness appears
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, uses that map with medical screening. Dual licensure lets structural findings sit next to a review of inflammation and medication risk. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, provides collaborative oversight so care stays coordinated with your existing medical team. That is beneficence: the plan exists to protect the disc and the person.
Alignment First: Restore the Joints That Should Move
If the mid-back is locked and the hips are stiff, adjusting only the sore lumbar joints may provide temporary relief, but the improvement often fades by the next session.
Alignment at El Paso Back Clinic restores motion where it belongs:
Thoracic and rib work to return rotation and extension to the cage
Pelvic and hip work so the femur can flex without flattening the lumbar curve
Specific lumbar adjustments after neighboring regions can share load
Patients keep autonomy here. You should know which joint is being treated, why, and how you’ll measure change at the next visit.
Non-maleficence sits in the same step. Skilled, non-invasive adjustments and graded loading can reduce the rush toward long-term medication or surgery while the problem is still mechanical. Surgery has a place for true neurologic emergencies. Most back problems become that case only after the same compensation runs for years.
Mobility Restoration You Can Own
Clinic work does not replace the shift.
Thoracic rotation in a half-kneel, ribs turning, pelvis quiet
Hip-flexor length after long kneeling, so standing does not yank the lumbar spine
Hip-hinge rehearsal so the crease is at the hips, not at the belt
Ankle motion, because a stiff ankle forces an extra lumbar fold when you drop
Short sessions beat heroic stretching after the damage is done. Two minutes before a rack walk and two minutes after is a plan most crews can keep.
Mechanical Rehabilitation and Lifting Strategy
Mobility without strength leaves a new joint unprotected.
Hip-dominant hinges and split-stance pulls so the glutes lift the torso
Anti-rotation holds so the lumbar spine can resist twist while the arms reach
Tall-kneeling and half-kneeling work that mirrors floor-to-stand cable tasks
Gradual loading of lift height and mass so the hips take the extra demand
Lifting rules:
Get the load close before it leaves the floor or the cart
Turn the feet instead of twisting the belt line
Prefer a kneel with an upright trunk over a full stoop when the aisle is low
Split the task: slide, then lift, then turn
Use a partner or lift aid for awkward chassis
Confined work will never be perfect. The goal is fewer cycles at end-range lumbar flexion and twist.
When Spinal Decompression Belongs in the Plan
If the disc is already irritated, alignment and exercise may not be enough in the first weeks. Non-surgical spinal decompression uses controlled traction to reduce load on an injured disc while you rebuild the kinetic chain. In lumbar radiculopathy, adding decompression to routine physical therapy improved pain, lumbar motion, endurance, and disability more than therapy alone over four weeks (Amjad et al., 2022).
Decompression is not a substitute for finding the stiff thorax or the restricted hip. It is a tool to calm a loaded segment so those corrections can stick. At Injury Medical Clinic PA in El Paso, decompression is paired with alignment and, when indicated, medical review by Dr. Cardenas so inflammation and nerve status are not ignored.
A Direct Plan for the Next Cutover
If your low back catches when you stand from behind a rack, treat it as a mechanical diagnosis.
Get a structural exam that measures thoracic rotation, hip motion, and lumbar control.
Restore motion to the mid-back and hips, then protect the lumbar segments.
Rebuild hinge strength and anti-rotation capacity for kneeling and reaching.
Change the lift: closer load, feet turn first, upright kneel in a low aisle.
Use decompression when disc or nerve signs are present, under a plan you understand.
You remain the decision-maker. Integrative care at El Paso Back Clinic is designed to work with your current physicians, not around them. The aim is simple: keep the lumbar spine from doing a job it was never meant to do.
Reversing Severe Lumbago and Disc Compression from Amazon Fulfillment Shifts
Abstract: Severe low-back pain after fulfillment work or delivery routes can feel like a one-way road toward surgery. Yet many cases deserve a careful conservative evaluation first. This guide explains how repetitive bending, sorting, vehicle vibration, and lifting can aggravate lumbago and disc-related pain; where mechanical alignment and selected non-surgical decompression may fit; how medical oversight screens red flags; and how Amazon workers can use practical lifting limits to reduce repeat flares.
When a Shift Starts Loading the Lumbar Spine
A warehouse associate may begin a shift feeling stiff. Hours later, repeated low-bin reaches, package twisting, sorting, pallet work, or lifting away from the body can turn stiffness into severe lumbago. Delivery drivers add prolonged sitting, road vibration, repeated cabin exits, carrying, and awkward curbside lifts.
The problem is often cumulative. When the trunk bends and rotates while a load stays away from the body, spinal muscles must generate more force to control movement. Repetition can fatigue those tissues and degrade movement quality. NIOSH treats load weight, reach distance, vertical height, twisting, lifting frequency, duration, and grip quality as factors that change lifting risk (NIOSH, 2024).
That matters because “safe lifting” is not one universal number. A box manageable at waist height may be too demanding on the floor, far from the body, poorly gripped, or lifted repeatedly near the end of a long shift.
Why Pain Can Spike After the Shift
Symptoms may intensify after clocking out because fatigued muscles provide less support, sitting stiffens the hips, and irritated tissues remain sensitive after repeated loading. Delayed soreness doesn’t mean a disc suddenly worsened. Track which movements, loads, positions, and recovery habits consistently increase or decrease symptoms across workdays.
What “Disc Compression” Really Means
Between the lumbar vertebrae, intervertebral discs distribute load and allow movement. A disc is not a jelly doughnut that simply pops out and can be pushed back into place. It is a load-bearing structure with a fibrous outer ring and softer inner region. Repeated flexion, compression, rotation, aging, prior injury, and anatomy can contribute to disc changes.
Pain may come from several overlapping sources:
Irritated lumbar joints or surrounding soft tissues
Protective muscle spasm and reduced hip motion
Disc-related inflammation or mechanical sensitivity
A disc herniation that irritates a nerve root
Deconditioning after repeated pain episodes and activity avoidance
This is why a structural examination matters. The goal is to match symptoms with movement findings, neurologic testing, work demands, and imaging when indicated. Low-back guidelines support exercise, education, and selected manual or mobilization approaches as part of conservative care rather than a single passive treatment (George et al., 2021).
Step One: Restore Motion Without Forcing the Spine
At El Paso Back Clinic, targeted mechanical care begins with a practical question: which movements are limited, painful, unstable, or poorly coordinated?
One worker may have stiff hips that force repeated lumbar bending. Another may have painful lumbar joints that limit extension. A driver can show a different pattern after hours of seated flexion and vibration.
Chiropractic adjustments and non-thrust joint mobilization may improve mobility and reduce pain when the examination supports them. Guidelines report benefit from joint mobilization for many people with chronic low-back pain, including some with leg symptoms (George et al., 2021). Care should pair manual treatment with rehabilitation so improved motion becomes usable strength.
The Functional Target
The patient gains something measurable: easier standing, smoother walking, less guarded bending, better sleep positions, safer transitions from a delivery van, and more confidence handling daily tasks. Those functional gains matter more than trying to make every spinal image look “perfect.”
Step Two: Use Non-Surgical Decompression Carefully
Non-surgical spinal decompression is commonly described as controlled lumbar traction or unloading. The practical aim is to reduce mechanical stress temporarily and create a position in which painful tissues or irritated nerve roots may become less sensitive.
The evidence requires precision. A systematic review found short-term improvements in pain and disability when certain mechanical traction forms were added to treatment for lumbar radiculopathy, but study quality and results varied (Vanti et al., 2021). WHO guidance for chronic primary low-back pain advises against routine traction for most patients, so decompression should not become an automatic protocol for every painful back (World Health Organization, 2023).
For a selected patient, decompression may be one tool within movement retraining, strengthening, work modification, and medical evaluation. It should never be sold as a guaranteed way to “reinflate” a disc or permanently reverse degeneration.
Preventing Unnecessary Surgery Without Delaying Necessary Surgery
Avoiding surgery is valuable when recovery is safe with conservative care. Lumbar discectomy can be appropriate for selected patients, yet it still carries risks such as recurrent herniation, wound complications, dural tears, reoperation, and neurologic complications (Bombieri et al., 2022).
The safer message is not “never have surgery.” It is “earn the decision with the right evaluation.” Recent spine recommendations support surgery when conservative treatment fails and emphasize urgent or early surgery for cauda equina syndrome or progressive severe neurologic deficits (Costa et al., 2024).
Seek urgent assessment for new bowel or bladder dysfunction, saddle-region numbness, rapidly worsening leg weakness, or serious neurologic changes. Fever, major trauma, unexplained weight loss, or concern for infection, fracture, or cancer also deserves prompt review.
This is non-maleficence in practice: use the least invasive reasonable option when it is safe, but never let a desire to avoid surgery delay care for a true emergency.
Step Three: Set Proactive Lifting Limits
For Amazon associates, prevention must survive the workday. “Lift with your legs” is not enough.
Use these rules:
Bring the package close before standing up.
Turn with the feet instead of twisting under load.
Reduce load size when the object starts low, high, or far away.
Use team lifting or mechanical assistance for demanding or awkward items.
Break up repeated lifting when possible with task rotation or brief recovery periods.
Stop treating pain as a test of toughness; a changing neurologic symptom deserves evaluation.
The Revised NIOSH Lifting Equation is useful because it does not assume every worker should lift the same weight in every position. It calculates a recommended weight limit using task conditions and a lifting index that reflects physical demand. NIOSH recommends keeping the lifting index or composite lifting index at or below 1.0 when evaluating two-handed lifting tasks (NIOSH, 2024).
Integrated Oversight: Structure, Medicine, and Patient Choice
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural alignment, mechanical rehabilitation, and advanced medical diagnostics. He holds Texas Advanced Practice Nursing License #1191402, Prescriptive Authority #59628, and NPI #1205907805. His dual licensure lets the clinic coordinate musculoskeletal examination with broader medical assessment and appropriate advanced interventions.
Dr. Maria Guadalupe Cardenas, MD, is Board Certified in Internal Medicine, has more than 40 years of experience, and holds Texas Medical License #J2933 and NPI #1164426748. As Medical Director, Clinical Director, and Collaborative Physician at Injury Medical Clinic PA in El Paso, she provides internal medicine oversight, risk stratification, interpretation of indicated laboratory tests, and comorbidity coordination.
That collaboration supports beneficence: the plan centers on the patient’s best functional outcome. It supports non-maleficence by screening for medical risks before aggressive treatment and using non-invasive, drug-sparing options when appropriate. It also protects autonomy. Patients are taught what the examination shows, what each option can and cannot reasonably do, and when another specialist or their existing medical team should be involved.
A Better Goal Than “Toughing It Out”
Severe lumbago after warehouse or delivery work is not a character test. The goal is to interrupt the overload cycle before pain, guarding, deconditioning, and poor mechanics reinforce one another.
A conservative plan can include targeted joint care, selected decompression, progressive trunk and hip rehabilitation, work-specific lifting education, and medical oversight. The target is direct: more comfortable movement, safer lifting, better sleep, and the ability to work without organizing each day around the next flare.
Multidisciplinary Call to Action
If repeated bending, sorting, driving, or lifting causes severe low-back pain, start with a coordinated evaluation. El Paso Back Clinic can assess mechanical function, neurologic findings, lifting demands, and medical risks, then explain conservative options and when to refer. Bring your imaging, medication list, job demands, and questions. The final decision remains yours, supported by clear information and coordinated chiropractic and medical care.
Severe Low Back Pain in Amazon Fulfillment Workers: Epidural Injections, Spinal Decompression, and the Treatment Window
Abstract: Severe low back pain can turn a 10-hour fulfillment shift into a battle. Repeated low-bin reaching, standing, twisting, and handling can keep an irritated lumbar nerve from settling. This article explains a function-first strategy: “turn down the fire, then address the load.” When true lumbar radiculopathy is present, an appropriately selected epidural injection may reduce acute nerve inflammation enough to create a treatment window for nonsurgical spinal decompression, mechanical chiropractic care, rehabilitation, and safer work habits. The goal is not temporary numbness. It is restoring movement while addressing the forces that keep symptoms returning.
A picker starts the shift moving quickly: scan, reach, bend, pull, pivot, walk, repeat. By hour seven, a familiar ache becomes sharper. By hour ten, standing upright hurts, the leg may burn, and getting into the car feels harder than moving another tote.
NIOSH identifies heavy physical work, lifting, forceful movement, bending, twisting, and static postures as recognized risk factors for low-back musculoskeletal disorders (National Institute for Occupational Safety and Health [NIOSH], 2024). For fulfillment workers, the problem is cumulative exposure. Low bins encourage trunk flexion, rushed reaches add rotation, and long hours on concrete floors magnify fatigue. Once pain changes how you move, compensation can load the hips, pelvis, and opposite side of the back.
The Key Question: Is the Fire in the Back or the Nerve?
Not every severe backache needs an injection. The first step is to identify what is irritated.
Localized lumbar pain may come from muscles, joints, discs, or other structures. Radicular pain is different. It can occur when a lumbar nerve root becomes irritated or compressed and may produce:
Burning or electric pain into the buttock or leg
Numbness or tingling
Pain that travels below the knee
Weakness in the foot or leg
Symptoms that worsen with certain spinal positions, coughing, or straining
A careful examination should assess strength, reflexes, sensation, movement tolerance, nerve tension, gait, and symptom patterns. Imaging may be appropriate when findings suggest significant disc injury, persistent neurologic symptoms, trauma, or when results would change treatment.
New loss of bowel or bladder control, saddle numbness, rapidly worsening weakness, fever with severe back pain, or major trauma requires urgent medical evaluation. These symptoms are not ones you can just “work through.”
Turn Down the Fire, Then Fix the Load
Think of an irritated lumbar nerve like a fire alarm beside a hot engine. If inflammation is high enough, even small movements can trigger intense pain. The worker may stop bending normally, brace every step, sleep poorly, and avoid rehabilitation because almost everything hurts.
That is where the treatment-window concept matters.
For appropriately selected lumbar radiculopathy, an epidural corticosteroid injection can place anti-inflammatory medication near the affected nerve root. A 2025 American Academy of Neurology review found that epidural steroid injections probably reduce short-term pain and disability in radiculopathy, while long-term pain benefit remains uncertain (Armon et al., 2025).
In plain language: the injection is not rebuilding a disc or correcting lifting mechanics. It may turn down the inflammatory “fire” long enough to make useful movement possible.
That window matters when pain blocks progress. A worker who could not tolerate walking, traction, unloading, or stabilization may gain enough control to begin them.
What an Epidural Injection Can—and Cannot—Do
A properly indicated epidural may help:
Reduce acute radicular pain
Improve tolerance for walking and sleep
Make rehabilitation easier to participate in
Allow a graded return to mechanical treatment
Reduce reliance on passive coping alone
It does not guarantee permanent relief, prevent surgery in every case, or address occupational loading patterns on its own. The AAN review found insufficient evidence that epidural steroid injections reduce the eventual need for surgery (Armon et al., 2025).
There are also risks. The FDA notes rare but serious neurologic complications associated with epidural corticosteroid injections and states that corticosteroids are not FDA-approved specifically for epidural administration (U.S. Food and Drug Administration [FDA], 2014). That makes informed consent, patient selection, appropriate image guidance, and medical oversight essential.
Step Two: Use the Window for Nonsurgical Spinal Decompression
Once the fire is quieter, the next question is simple: what mechanical inputs can the spine tolerate now?
Here, “spinal decompression” means nonsurgical mechanical traction or distraction, not surgery. The goal is controlled lumbar unloading while monitoring symptoms and neurologic response.
Research on traction is encouraging for some lumbar disc herniation patients, but it is not one-size-fits-all. A 2025 systematic review found improvements across traction, exercise, and manipulation studies, while also reporting very high variability between protocols and patient groups (Thavarajasingam et al., 2025).
That is why decompression should be treated as a clinical tool, not a magic table.
During the treatment window, the clinician can look for useful signs:
Leg pain centralizes toward the back
Standing and walking tolerance improves
Numbness or tingling decreases
The patient can change positions with less guarding
Basic trunk and hip exercises become tolerable
If symptoms worsen, spread farther down the leg, or neurologic weakness progresses, reassess the plan.
Step Three: Fix the Load With Mechanical Chiropractic Care
Pain relief is valuable, but function is the finish line.
The picker or packer has to return to the same realities: low bins, repetitive handling, long walking routes, awkward reaches, and a clock that does not care whether the lumbar muscles are fatigued. Mechanical chiropractic care should therefore focus on restoring motion and controlling load, not simply chasing pain scores.
Care may include low-force mobilization, selected chiropractic adjustments, hip mobility, trunk endurance, graded lifting, nerve-mobility exercises, and conditioning. Aggressive manipulation is not automatically appropriate during a highly irritable radicular episode; treatment intensity should match neurologic findings and tolerance.
A useful return-to-function plan teaches the worker to:
Hinge through the hips instead of repeatedly rounding the lumbar spine
Bring the load closer before standing
Pivot with the feet instead of twisting while bent
Alternate positions when task design allows
Break large recovery goals into short movement exposures
Report progressive weakness or spreading numbness promptly
These habits support autonomy. The patient should understand what is being treated, why each step is being used, what alternatives exist, and what would change the plan.
Integrated Care: One Plan, Not Three Disconnected Treatments
Severe radicular pain often crosses professional lanes. That is where multidisciplinary care can improve coordination.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines Doctor of Chiropractic care with board-certified family nurse practitioner authority and advanced practice nursing. Under collaborative medical oversight, his scope includes image-guided epidural spinal injections, structural chiropractic care, mechanical rehabilitation, and functional medicine support.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in Internal Medicine, has more than 40 years of experience, and serves as Medical Director and collaborative physician at Injury Medical Clinic PA. Her role includes medical oversight, risk stratification, laboratory interpretation, and coordination of medical conditions that can affect recovery.
The benefit is sequence and communication: calm the nerve when indicated, restore tolerable motion, rebuild capacity, and coordinate with the patient’s existing medical team. That supports beneficence while respecting non-maleficence—using the least invasive reasonable options first when safe, without delaying surgical or emergency referral when neurologic findings demand it.
Your Treatment Window Should Lead Somewhere
An epidural injection should not become permission to ignore the same loading pattern until the pain returns. The window is valuable because it creates opportunity.
Use it to walk more normally.
Use it to sleep.
Use it to tolerate decompression or rehabilitation.
Use it to relearn bending, lifting, and bracing strategies.
Use it to build enough capacity that the next 10-hour shift is not simply another flare waiting to happen.
For an Amazon fulfillment worker with severe low back pain and leg symptoms, the goal is not to choose between “an injection” and “chiropractic.” The better question is whether each tool fits the diagnosis and timing.
Turn down the fire. Then fix the load.
If severe back pain, sciatica, numbness, or weakness is limiting your work or daily function, schedule a multidisciplinary evaluation at El Paso Back Clinic. A coordinated DC/APRN/FNP-BC and MD-guided plan can help determine whether you need urgent referral, an epidural treatment window, nonsurgical decompression, mechanical rehabilitation, or a different path entirely. You remain the informed decision-maker at every step.
Server Rack to Desk Chair: Why Data Center and IT Work Can Trigger Chronic Low-Back Pain—and What You Can Do About It
A shift can change quickly. For one hour, you sit and answer tickets. The next, you are standing on a server-room floor, crouching behind a rack, reaching for cables, or lifting hardware. By day’s end, your low back may feel tight, tired, or familiar.
For El Paso’s IT professionals, data center technicians, and network teams, recurring low-back pain rarely comes down to one “bad posture.” Sitting, standing, bending, twisting, and lifting can contribute to symptoms, but no single exposure consistently explains every case (Swain et al., 2020). The better question is which combined loads, habits, and recovery limits keep your back irritated.
Why Tech Work Can Become a Mechanical Load Problem
Your lumbar spine is built to move and carry load. Problems can appear when tissues face more stress than they comfortably recover from.
Long desk sessions reduce movement variety. Prolonged standing can also become uncomfortable; substantial occupational standing has been associated with more low-back symptoms, though it has not been proven that standing itself causes pain (Coenen et al., 2018). Add crouching, cable work, twisting, and equipment lifting, and the demand changes again.
The goal is not to fear movement. It is to improve how well your body handles it.
Sitting, Hip Stiffness, and the “Locked Up” Feeling
After hours seated, many workers stand feeling stiff through the hips and lower back. It is tempting to blame “tight hip flexors,” but low-back pain is more complex than one muscle group.
Limited hip motion can change how you bend, squat, or reach. The lumbar region may then take on more motion during some tasks. Hip mobility, trunk control, and movement variety can therefore be reasonable rehabilitation targets without claiming that tight hips automatically cause back pain.
Standing on Concrete Is Not Automatically Better Than Sitting
A standing desk may help, but standing all day is not a cure. Technical workspaces may require long periods on firm surfaces while monitoring equipment.
Variation is usually practical: sit, stand, walk, change foot position, and move when the job permits. NIOSH identifies static posture, heavy physical work, lifting, bending, and twisting among contributors to work-related musculoskeletal stress (National Institute for Occupational Safety and Health [NIOSH], 2024a).
Think “best next position,” not “perfect position.”
Crouching, Cable Work, and Rack-Side Repetition
Working behind equipment can place you in deep hip flexion, kneeling, squatting, rotation, or sustained forward bending. None is inherently dangerous. Trouble may develop when exposure is prolonged, repeated, heavily loaded, or performed while fatigued.
Bring tools closer. Raise work when possible. Use a kneeling pad or stable support when appropriate. Alternate sides instead of always rotating one way. Brief movement breaks can reduce unnecessary repetition.
Lifting Hardware: Control the Load, Not Just Your Back
Servers, batteries, monitors, and UPS components can be awkward or hard to grip. Safe lifting is not simply “keep your back straight.” Weight, distance, height, twisting, frequency, grip, and repetition matter. The Revised NIOSH Lifting Equation estimates physical stress from two-handed lifts and supports safer job design (NIOSH, 2024b).
Get close to the load, use a stable stance, avoid rushed twisting, and use team lifts or assistance when appropriate. Lifting limits should reflect the task and your current capacity.
What a Structural Assessment Should Actually Look For
Recurring low-back pain deserves more than a quick label.
At El Paso Back Clinic, a mechanical assessment can consider spinal and pelvic motion, painful patterns, hip mobility, trunk endurance, lifting mechanics, neurological findings, and positions that change symptoms. The goal is not to claim every painful back is “out of alignment,” but to identify modifiable findings and whether conservative care is appropriate.
Imaging is not necessary for every episode. History and examination help determine when testing may be appropriate. New bowel or bladder problems, saddle numbness, progressive leg weakness, major trauma, fever, or systemic symptoms require prompt medical evaluation.
Mechanical Rehabilitation: Build Capacity for Your Real Job
Rehabilitation should prepare you for work, not only help you feel better on a treatment table. Clinical guidelines support exercise and selected manual therapies for many people with acute or chronic low-back pain (George et al., 2021).
For an IT professional, rehabilitation might include hip mobility, trunk endurance, hinging, graded lifting, strength, walking tolerance, and desk-position changes. A data center technician may also need loaded carries, squat tolerance, kneeling transitions, reaching, and controlled rotation.
The plan should progress with your response. Some people need mobility; others need strength, endurance, or confidence with painful movements. Patient autonomy matters: you should understand what is tested, why treatment is suggested, alternatives, and how progress will be measured.
Where Chiropractic Care and Decompression Fit
Chiropractic care may be one part of conservative treatment when examination indicates manual care is appropriate. Guidelines include spinal manipulation among options that may help some people with chronic low-back pain, especially when paired with active care rather than used alone (World Health Organization [WHO], 2023).
“Decompression” requires careful thinking. WHO does not recommend routine traction for chronic primary low-back pain because the supporting evidence is uncertain (WHO, 2023). Decompression should not be sold as a guaranteed disc fix or universal answer.
If decompression is considered, it should follow examination, fit the symptom pattern, have clear goals, and be reassessed. Beneficence means choosing care for your clinical needs—not applying the same protocol to everyone.
Integrated Care When Back Pain Is More Than Mechanical
Persistent pain can be influenced by sleep, stress, metabolic health, medication use, recovery, and other medical factors. An integrated team can help when those issues matter.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care, mechanical rehabilitation, and functional medical assessment. Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, provides medical direction and oversight for complex medical or metabolic concerns and clinically appropriate laboratory evaluation.
Collaboration does not remove your voice. You remain the informed decision-maker.
A Better Back Strategy for El Paso Tech Workers
Whether your day moves from an El Paso desk to a server room, network closet, help-desk station, or equipment floor, your back needs more than perfect posture. It needs movement variety, smart load management, recovery, and enough strength for the work.
Start with small changes: interrupt long sitting, vary standing, improve workstation reach, keep loads close, plan awkward lifts, and build capacity gradually. If pain keeps returning, limits work, radiates into the leg, or changes how you move, seek a qualified evaluation.
At El Paso Back Clinic, our goal is to identify changeable drivers, explain your options clearly, and coordinate structural chiropractic care, mechanical rehabilitation, and medical oversight when indicated. We build the safest plan around your findings, goals, and informed choices. That approach supports safer movement, stronger function, and more confident workdays ahead.
References
Coenen, P., Willenberg, L., Parry, S., Shi, J. W., Romero, L., Blackwood, D. M., Maher, C. G., Healy, G. N., Dunstan, D. W., & Straker, L. M. (2018). Associations of occupational standing with musculoskeletal symptoms: A systematic review with meta-analysis. British Journal of Sports Medicine, 52(3), 176–183. https://doi.org/10.1136/bjsports-2016-096795
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. https://doi.org/10.2519/jospt.2021.0304
Swain, C. T. V., Pan, F., Owen, P. J., Schmidt, H., & Belavy, D. L. (2020). No consensus on causality of spine postures or physical exposure and low back pain: A systematic review of systematic reviews. Journal of Biomechanics, 102, 109312. https://doi.org/10.1016/j.jbiomech.2019.08.006
World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. World Health Organization. https://www.who.int/publications/i/item/9789240081789
Legal Peptides and Integrative Chiropractic Care: A Clear Guide
Abstract
This article explains legal peptide use in plain language. Legal peptide use means giving, making, or prescribing certain short chains of amino acids that regulatory bodies such as the Food and Drug Administration (FDA) have officially approved for medical use. Readers will learn how approved drugs differ from compounded products and research-only chemicals. The article then reviews the New Mexico Board of Nursing’s September 2026 peptide FAQs. It covers a valid patient-provider relationship, telehealth, advertising, nutrition, and muscle care. The last sections show how integrative chiropractors and nurse practitioners work together, and how Dr. Alexander Jimenez, DC, APRN, FNP-BC, and Dr. Maria Guadalupe Cardenas, MD, run that model at Injury Medical Clinic PA in El Paso.
What Legal Peptide Use Means
Peptides are short chains of amino acids. The body already makes many of them. They act like small messages that can change appetite, hormone release, inflammation, and tissue repair (Findlay, 2026; Vibrant Health of Colorado, 2026).
Legal peptide use means giving, making, or prescribing certain short chains of amino acids that regulatory bodies such as the Food and Drug Administration (FDA) have officially approved for medical use (Findlay, 2026; Peptide Laws, n.d.). In everyday terms, a peptide plan is safer when:
A regulator has officially approved that product for medical use.
A licensed clinician examines the patient and writes a prescription.
Any compounded version follows federal compounding law and state pharmacy rules.
The chart shows a reason, informed consent, and follow-up (ByrdAdatto, n.d.; LumaLex Law, n.d.).
Insulin, semaglutide, tirzepatide, tesamorelin, and bremelanotide (PT-141) are examples of peptides with FDA-approved products for specific conditions (Findlay, 2026; DJ Holt Law, 2026). Approval covers a product and its use. It does not make every similar vial on the internet legal.
Approved, Compounded, or Research-Only
FDA-approved medicines have finished clinical trials and manufacturing review. A clinician may use an approved drug off-label when science and judgment support that choice, but the product itself is still an approved drug (DJ Holt Law, 2026; ByrdAdatto, n.d.).
Compounded peptides are custom medicines made for one named patient when the law allows it. They are not FDA-approved. They may differ in formula, stability, and oversight (New Mexico Board of Nursing, 2026). After branded GLP-1 shortages eased, federal policy tightened around copies of those products (DJ Holt Law, 2026; Peptide Laws, n.d.).
Research-only chemicals are often sold as “not for human use.” Popular names include BPC-157, TB-500, and several growth-hormone secretagogues. That label does not make clinical use legal. The FDA treats marketing for human treatment as a drug claim (Findlay, 2026; LumaLex Law, n.d.). Status can also change as compounding committees review bulk substances (DJ Holt Law, 2026).
State boards rarely ban peptides as a whole class. They do ask whether the prescriber stayed in scope, did a real exam, and used a lawful pharmacy (Peptide Journal, 2026; ByrdAdatto, n.d.).
What the New Mexico Board of Nursing Said
In September 2026, the New Mexico Board of Nursing published clinical-practice FAQs on peptide therapies. The Board said the page is guidance, not a legal opinion, and it does not change the Nursing Practice Act (New Mexico Board of Nursing, 2026). The answers still give a clear map.
Key points include:
APRNs may prescribe compounded medicines within their population focus and prescriptive authority if they have the education and judgment to do so. The Board uses LACE: licensure, accreditation, certification, and education.
GLP-1 medicines are among the most watched peptides because they help and they carry risk.
A valid patient-provider relationship must exist before prescribing.
A compounded GLP-1 vial must stay patient-specific. It cannot be shared.
Pharmacies should be licensed and able to share sterility testing.
Patients must be told when a product is compounded rather than a brand-name FDA-approved drug.
Reckless prescribing—not peptide use alone—invites discipline (New Mexico Board of Nursing, 2026).
New Mexico grants nurse practitioners full practice authority. Texas generally requires a collaborating physician (Peptide Journal, 2026). The clinical standard still looks the same: exam, reason, consent, monitoring, and a clean pharmacy.
The Exam, Telehealth, and Honest Ads
The Board listed what should happen before GLP-1 or related peptide care starts (New Mexico Board of Nursing, 2026):
A health history and a review of current medicines
A check for higher-risk problems, such as family medullary thyroid cancer or MEN-2, pancreatitis, gallbladder disease, kidney disease, pregnancy plans, eating disorders, or frailty
A physical exam and baseline labs when they are needed
Consent that covers benefits, common side effects, serious risks, other options, how long care may last, lifestyle changes, and weight regain after stopping
A written plan and later checks of weight, nutrition, tolerance, and dose
Telehealth can be used when the standard of care is still met. A questionnaire alone is not enough. The prescriber must also be licensed in the state where the patient is located (New Mexico Board of Nursing, 2026). Ads must be truthful. Claims of guaranteed weight loss do not meet professional standards. The Federal Trade Commission watches those claims (New Mexico Board of Nursing, 2026). A med-spa name does not change the duty of the person who evaluates and prescribes.
Food and Muscle Still Come First
The Board was clear: medicine is not the whole treatment. Providers should counsel patients on protein, resistance exercise, lean-mass protection, vitamins, and long-term habits. Skipping that work can lead to muscle loss, frailty, and poor results after the drug stops (New Mexico Board of Nursing, 2026). Integrative clinics make the same point. Peptides work best when you address food, sleep, and movement (Nourish House Calls, n.d.; Evolution Integrative Medicine, n.d.).
How Integrative Chiropractic Care Fits
Teams of integrative chiropractors and nurse practitioners (NPs) work together in integrative medical offices. Most of the time, chiropractors do the manual therapies, biomechanics, and structural rehabilitation. Nurse practitioners, on the other hand, conduct clinical evaluations and have the medical authority to prescribe and oversee therapies (ProCredits, n.d.; Jimenez, 2026a). That split protects both the patient and the license.
Chiropractic care links to peptide treatment by making muscles and bones stronger:
Adjustments and mobilization restore joint motion and lower mechanical stress on nerves and soft tissue.
Better motion lets a person load a tendon, hip, or spine pattern with less guarding.
Rehab—easy isometrics, then controlled loading—tells muscle, tendon, and bone to remodel.
Protein-forward eating provides the building blocks those tissues need.
A legal metabolic peptide, when indicated, may help appetite, blood sugar, and body composition so rehab is easier to finish.
Any tissue-support peptide is an add-on to loading, not a replacement for it (El Paso Back Clinic, n.d.; Gruber Chiropractic, n.d.).
Dr. Jimenez has written that peptides should not be sold as a shortcut to grow cartilage, discs, or ligaments. Food cannot unlock a stuck joint. An adjustment cannot replace protein. Each tool has a job (Jimenez, 2026a).
The El Paso Team: Dr. Jimenez and Dr. Cardenas
Injury Medical Clinic PA in El Paso shows how those roles work in daily care. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, is a dual-licensed chiropractor and board-certified family nurse practitioner. He leads conservative care, rehabilitation, functional medicine, and personal-injury documentation (Jimenez, n.d.).
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine (NPI #1164426749; Texas MD License #J2933). With more than 40 years of experience as an internist, she serves as medical director and collaborative physician. This multidisciplinary setup is common in integrative or injury clinics, where an MD provides medical direction alongside a chiropractor. The team integrates chiropractic care from Dr. Jimenez with medical oversight by Dr. Cardenas, plus functional medicine, personal injury care, rehabilitation, and related services (Jimenez, n.d.; El Paso Back Clinic, n.d.).
A simple path for crash, sports, or chronic back pain recovery looks like this:
Map the problem with history, exam, and movement testing.
Restore motion with chiropractic and soft-tissue care.
Rebuild muscle and bone loading with graded rehab.
Address nutrition and metabolic gaps.
Add a legal, patient-specific peptide only after the reason, labs, and consent are on the chart.
Clinical Observations on Strength and Recovery
Clinical observations shared by Dr. Jimenez describe peptides as possible signaling helpers, not magic. Progress often looks better when spinal care is paired with inflammation control, body-weight support, protein intake, and sleep (Jimenez, 2026a; El Paso Back Clinic, n.d.). Other clinics describe peptides for recovery, metabolism, gut integrity, sleep, and connective tissue (New Life Physicians, n.d.; RevitalIV, n.d.). Those descriptions are not the same as FDA approval. Patients should ask which product is approved, which is compounded for them alone, and which is still experimental.
Questions to Ask Before Starting
Before any peptide begins, ask four plain questions:
Is this an FDA-approved product or a compounded one?
Who is the licensed prescriber, and which state does the patient live in?
What exam, labs, and follow-up will I receive?
How will chiropractic care, exercise, and nutrition work with the medicine?
Boards expect those answers in the record (New Mexico Board of Nursing, 2026; ByrdAdatto, n.d.). Legal peptide use is a medical act. Integrative chiropractic care is a movement and strength act. When a clinic keeps both lines clear, patients build stronger muscles and bones—and, when appropriate, receive carefully chosen peptide support without a gray-market detour.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine