Personal Injury
Back Clinic Personal Injury Chiropractic Team. Injuries from an accident can not only cause physical harm to you or a loved one, being involved in a personal injury case can often be a complicated and stressful situation to handle. These types of circumstances are unfortunately fairly common and when the individual is faced with pain and discomfort as a result of trauma from an accident or an underlying condition that has been aggravated by the injury, finding the right treatment for their specific issue can be another challenge on its own.
Dr. Alex Jimenez’s compilation of personal injury articles highlights a variety of personal injury cases, including automobile accidents resulting in whiplash, while also summarizing various effective treatments, such as chiropractic care. For more information, please feel free to contact us at (915) 850-0900 or text to call Dr. Jimenez personally at (915) 540-8444.

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Chiropractic Examination, Imaging & Diagnostics, Injury Care, Lower Back Pain, Med-Legal Corner, Personal Injury, Spine Care
Why Changing Back Pain Diagnoses During Rehabilitation May Reflect Better Clinical Understanding
After a collision on I-10, Carlos, a 42-year-old warehouse supervisor from El Paso, walked into the clinic with intense low-back pain that made sitting, bending, and even standing long enough to finish a shift feel impossible. Two days after the rear-end impact, his lumbar muscles were locked in protective spasm, swelling limited his ability to twist or extend, and every movement provoked sharp local pain. The first examination pointed to an acute lumbar strain with facet joint irritation—an understandable starting point when inflammation still masks deeper findings. By the second visit, the picture had already begun to shift. By the third, objective imaging and clearer symptoms allowed a more precise diagnosis of a traumatically aggravated lumbar disc injury. Far from signaling inconsistency, these evolving impressions demonstrated careful clinical reasoning that ultimately strengthened both his recovery path and the medical-legal record.

Initial findings in acute spinal trauma are often provisional by necessity. In the first 48–72 hours, inflammatory chemicals flood the injured tissues, producing swelling, muscle guarding, and reduced range of motion that can obscure the full extent of disc, ligament, or nerve involvement. Guidelines and clinical observation confirm that many patients present with nonspecific low-back pain until the acute inflammatory stage begins to resolve. As swelling decreases, patients can better describe the character and radiation of their symptoms, orthopedic tests become more reliable, and clinicians can distinguish simple muscular strain from patterns that suggest disc or nerve-root irritation. When symptoms persist or change in quality, imaging is appropriately obtained and interpreted in the context of the mechanism of injury, the timeline, and serial examinations. Alternative explanations—pre-existing degeneration, subsequent activity, or unrelated conditions—are systematically considered and either ruled out or incorporated. This refinement process is a hallmark of good care, not a sign of error.
Visit One: The Acute Phase and a Provisional Working Diagnosis
Carlos arrived two days after the collision. His history matched the mechanics of rapid deceleration: seat-belt restraint, torso thrust, and immediate low-back pain. Examination showed limited lumbar flexion and extension, tenderness over the paraspinal muscles and lower facets, and a negative straight-leg raise limited by back pain alone. Swelling and spasm made precise segmental testing difficult. The working diagnosis recorded that day was acute lumbar sprain/strain with possible facet irritation secondary to the motor-vehicle collision. Treatment focused on reducing inflammation, restoring gentle motion, and protecting the tissues while they began to settle. Chiropractic adjustments were deferred until guarding decreased; instead, soft-tissue work, gentle mobilization, and education on activity modification helped him manage pain and maintain as much function as possible. Objective measures, including a baseline Oswestry Disability Index, documented the functional impact so that later changes could be compared against a clear starting point.
Visit Two: Swelling Subsides and Symptoms Clarify
Ten days later, the protective muscle spasm had eased. Carlos could now describe a deep, aching low-back pain that occasionally traveled into the buttock and the back of the thigh when he sat for more than twenty minutes or lifted a light box at work. Kemp’s test and repeated extension reproduced familiar symptoms; the straight-leg raise remained limited but now produced mild buttock referral. These findings raised the possibility of disc involvement masked by early swelling. The clinical note explicitly recorded the reasoning: “Initial acute inflammatory presentation limited differential. With reduced edema, radicular-pattern symptoms and provocative testing now support consideration of intervertebral disc injury at the lower lumbar levels. MRI ordered to correlate clinical findings and rule out alternative structural causes.” This documentation is essential. It shows the diagnosis was not arbitrarily changed but updated based on new, objective information. Serial functional scores and range-of-motion measurements further demonstrated that the clinical picture was evolving in a biologically plausible way.
Visit Three: Imaging Confirms, and the Diagnosis Is Refined
MRI obtained in the fourth week revealed a moderate protrusion at L4–5 with annular fissuring, consistent with the timing of the collision and the emerging leg symptoms. Mild pre-existing disc desiccation was noted, yet the acute morphology and symptom correlation supported traumatic aggravation of the disc rather than purely degenerative change. The updated diagnosis—lumbar intervertebral disc protrusion with mild radicular component, traumatically aggravated by the collision—was accompanied by a clear narrative of clinical reasoning: mechanism of injury, temporal relationship, progressive findings once swelling subsided, exclusion of red-flag alternatives, and correlation with imaging. Treatment shifted toward targeted disc decompression, directional preference exercises, and progressive core stabilization while medical oversight addressed any metabolic factors that could slow healing. Patients gain measurable benefits from this approach: reduced nerve irritation, improved sitting and lifting tolerance, better sleep, and a clearer path back to work without reliance on prolonged medication or early surgery.
Documenting the Clinical Reasoning
behind each diagnostic shift protects both the patient and the legal record. In personal-injury cases, defense experts frequently argue that changing diagnoses indicate uncertainty or exaggeration. Thorough notes that explain why new information warranted an updated impression neutralize that argument. They establish the proximate link between the collision forces and the objective injury, support Letters of Protection, and demonstrate that the care plan remained evidence-based as the clinical picture clarified. Tools such as the Oswestry Disability Index, digital range-of-motion measurements, and consistent orthopedic testing provide the objective anchors that allow these evolving impressions to withstand scrutiny. Readers seeking a deeper understanding of how mechanism, timeline, and serial findings establish causation can review the clinic’s detailed discussion of medical-legal causation principles.
Careful Documentation also Serves the Three Bioethical Pillars that Guide Care
Beneficence is realized when the multidisciplinary team—chiropractic biomechanical assessment, nurse-practitioner soft-tissue and functional evaluation, and internal-medicine oversight—works together to identify the true source of pain and address it at its root rather than merely masking symptoms. Non-maleficence is honored by favoring non-invasive options such as chiropractic adjustment, electroacupuncture, and targeted rehabilitation that reduce the risks associated with opioid dependency or premature surgery. Autonomy is strengthened when patients receive clear explanations of why their diagnosis may evolve, what each new finding means, and how they remain active partners in decisions about imaging, activity, and treatment goals. Coordination with the patient’s existing medical providers further supports informed choice.
What makes Injury Medical Chiropractic and Functional Medicine Clinic unique is its integrated structure, which makes this level of precision possible. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than forty years of experience, directs the clinic and provides medical direction, advanced laboratory interpretation, and risk stratification. Working alongside her is Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, a dual-licensed chiropractor and board-certified family nurse practitioner who specializes in soft-tissue injury, structural alignment, and the objective documentation required for personal-injury cases. This dual-licensure model—medical director plus nurse practitioner specializing in soft-tissue injury—is the only integrated arrangement of its kind in El Paso, Texas, allowing the same clinical team to generate both the biomechanical findings and the medical reasoning that appear in a single, coherent causation file.
Readers who wish to explore related topics will find practical guidance on the stages of healing from neck or back injuries, the proper nomenclature for lumbar disc findings, and auto-accident management strategies for sciatica and herniated discs. Each of these resources reinforces the same principle illustrated by Carlos’s three visits: better clinical understanding is not a fixed label applied on day one but a progressive process of observation, testing, and documented reasoning that ultimately produces a clearer diagnosis, more effective treatment, and a more defensible medical-legal record.
References
Brumitt, J., & Cuddeford, T. (2015). Current concepts of muscle and tendon adaptation to strength and conditioning. International Journal of Sports Physical Therapy, 10(6), 748–759. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC4637912/
Duchesne, E., Dufresne, S. S., & Dumont, N. A. (2017). Impact of inflammation and anti-inflammatory modalities on skeletal muscle healing: From fundamental research to the clinic. Physical Therapy, 97(8), 807–817. https://doi.org/10.1093/ptj/pzx056
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Gabriel Rothman, S. L., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology, and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Johnsen, L. G., Hellum, C., Nygaard, Ø. P., Storheim, K., Brox, J. I., Rossvoll, I., Leivseth, G., & Grotle, M. (2013). Comparison of the SF6D, the EQ5D, and the Oswestry Disability Index in patients with chronic low back pain and degenerative disc disease. BMC Musculoskeletal Disorders, 14, Article 148. https://doi.org/10.1186/1471-2474-14-148
Wu, Y. S., & Chen, S. N. (2014). Apoptotic cell: Linkage of inflammation and wound healing. Frontiers in Pharmacology, 5, Article 1. https://doi.org/10.3389/fphar.2014.00001

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Chiropractic, Chronic Pain, Health, Injury Care, Personal Injury, Treatments, Viscerosomatic Reflex
Learn how muscle pain affects daily life and how chiropractic care, combined with causation, can effectively relieve discomfort.

Abstract
Causation forms the critical legal and medical link between a traumatic event such as a motor vehicle collision, slip and fall, or workplace incident and the resulting muscle pain and related injuries that support recovery in personal injury claims. Without evidence that the event more likely than not caused or materially contributed to the harm, even significant pain and functional limitations may not justify full compensation. In clinical practice at Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, in El Paso, Texas, musculoskeletal injuries from trauma rarely occur in isolation. They disrupt joint mechanics, muscle balance, nerve signaling, and overall function, often leading to secondary issues such as chronic pain, reduced mobility, sleep disruption, and compensatory strain in other body regions. Chiropractic care addresses these problems by restoring joint motion, reducing abnormal sensory input to the nervous system, decreasing local inflammation, and supporting the body’s natural healing processes. When integrated with medical oversight from Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, along with functional medicine principles, targeted rehabilitation, and other non-surgical approaches, this model delivers both clinical recovery and the objective documentation required to establish medical causation. This educational post walks through what causation means, how it is justified under legal and scientific standards, why it is essential in muscle pain cases, what chiropractic care is, how it reduces muscle pain and comorbidities through specific physiological mechanisms, how it provides insight into personal injury, and how the multidisciplinary team integrates these elements for non-surgical recovery. The discussion draws on modern evidence-based research and clinical observations to guide readers from the injury event through functional restoration.
Understanding Causation in Personal Injury Cases Involving Muscle Pain
Causation is the requirement that connects a defendant’s negligent or wrongful act to the plaintiff’s injury and resulting losses. In personal injury litigation, courts and insurance evaluators assess whether the incident was both the actual and proximate cause of the harm. Actual cause, often evaluated through the “but for” test, asks whether the injury would have occurred but for the incident. Proximate cause, or legal cause, asks whether the harm was a reasonably foreseeable result of the conduct and whether the connection is sufficiently close to justify liability.
For muscle pain cases, this analysis matters because soft-tissue injuries often involve delayed symptom onset, overlapping pre-existing conditions, and subjective complaints that require careful documentation. Muscle strains, spasms, and related myofascial pain can develop or worsen after trauma due to mechanical overload, inflammation, and altered motor control. Establishing causation requires demonstrating that the incident more likely than not produced or substantially aggravated these findings.
Legal standards generally require proof on the balance of probabilities or to a reasonable degree of medical probability. Factual causation does not demand scientific certainty. Instead, the incident must have materially contributed to the injury. In practice, this means reviewing the mechanism of injury, the temporal relationship between the event and symptom onset or worsening, objective clinical findings, imaging when appropriate, the exclusion of alternative explanations, and the response to treatment.
The Bradford Hill criteria, originally outlined by Sir Austin Bradford Hill in 1965, provide a useful framework for evaluating whether an association is likely causal. These include strength of association, consistency, specificity, temporality, biological gradient, biological plausibility, coherence, experimental evidence, and analogy. Temporality is particularly critical: symptoms that begin or clearly worsen after a documented collision, for example, support a causal link when the mechanism is consistent with the findings. Biological plausibility is supported when the forces involved, such as sudden acceleration-deceleration or rotational loading, can reasonably produce muscle strain, joint restriction, and secondary inflammation. Coherence requires that the explanation fit with existing knowledge of tissue response to trauma. Serial clinical records that show progressive improvement with appropriate care further strengthen the narrative.
In muscle pain cases, delayed onset is common. Inflammatory mediators and muscle guarding often peak one to three days after low-speed impacts, so the absence of severe pain at the time of the accident does not rule out causation. Documentation must distinguish new or aggravated injury from age-related degeneration or prior asymptomatic findings. The eggshell plaintiff principle, recognized in many jurisdictions including Texas, holds that the defendant takes the plaintiff as found. If trauma aggravated a pre-existing condition and produced new functional limitations, those consequences are generally compensable.
Medical evidence is central. Provider notes must capture the patient’s description of the mechanism, the timing of symptoms, examination findings such as restricted range of motion, muscle tenderness, positive orthopedic tests, and strength deficits, along with a reasoned opinion linking these to the incident. Continuity-of-care supplies contemporaneous records that are more persuasive than retrospective reconstruction. Objective measures, including goniometric range-of-motion readings, muscle testing, and functional outcome scores, create a measurable timeline.
Why Causation Is Required in Personal Injury Courtroom Cases Involving Muscle Pain
Causation is required because liability depends on proving that the defendant’s conduct produced the claimed harm. Without it, courts cannot award damages for medical expenses, lost wages, pain and suffering, or future care. Muscle pain presents unique challenges because it is often soft-tissue based, may lack dramatic imaging findings, and can be influenced by psychosocial factors or pre-existing conditions. Courts and insurers therefore scrutinize whether the pain is a direct or material consequence of the trauma rather than an unrelated or inevitable process.
Insurance adjusters and defense experts frequently argue that muscle pain reflects degenerative change, poor posture, or ordinary daily activity. To counter this, the medical record must show a clear temporal association, a biomechanically plausible mechanism, objective clinical correlation, and improvement consistent with the natural history of trauma-related injury when treated appropriately. For example, a patient who reports immediate or near-immediate neck and upper-back muscle pain after a rear-end collision, demonstrates restricted cervical rotation and trapezius hypertonicity on examination, and shows measurable gains in motion and reduced pain scores over subsequent weeks builds a stronger causal case than one whose complaints emerge weeks later without intervening documentation.
Proximate cause considerations also matter. The harm must be a foreseeable result of the type of trauma involved. Sudden muscle strain from impact forces is foreseeable. Courts examine whether intervening causes, such as a subsequent unrelated injury, break the chain. Thorough contemporaneous records help preserve the causal connection.
In courtroom settings, expert testimony often addresses whether the findings are consistent with the reported mechanism to a reasonable degree of medical probability. Chiropractic and medical providers contribute by supplying detailed histories, serial examinations, and treatment responses that allow the trier of fact to evaluate the likelihood of a causal relationship. The absence of such evidence frequently leads to reduced settlements or adverse verdicts even when the patient experiences real pain.
What Is Chiropractic Care
Chiropractic care is a licensed healthcare profession focused on diagnosing, treating, and preventing neuromusculoskeletal disorders, particularly those involving the spine and related muscles and joints. Practitioners use manual therapies including spinal adjustments and mobilizations, soft-tissue techniques, therapeutic exercise, patient education, and lifestyle guidance. The goal is to restore joint motion, reduce mechanical stress on tissues, modulate pain pathways, and improve overall function without reliance on surgery or long-term medication when possible.
Spinal manipulation typically involves a high-velocity, low-amplitude thrust directed at a restricted joint segment. Mobilization uses slower, repetitive movements within the patient’s range of motion. Soft-tissue methods address muscle hypertonicity, fascial restrictions, and adhesions. These approaches draw on biomechanics and neurophysiology. Clinical practice guidelines from organizations such as the American College of Physicians include spinal manipulation among recommended non-pharmacologic options for acute and chronic low back pain. Similar support exists for certain neck pain and headache presentations when used as part of multimodal care.
In the personal injury context, chiropractic care frequently serves as an early, continuous conservative intervention for muscle strains, sprains, joint dysfunction, and related pain. It establishes baseline measurements shortly after the incident, monitors progress, identifies red flags that require medical referral, and documents the clinical course. Treatment plans are individualized according to the phase of healing, patient tolerance, and functional goals.
How Chiropractic Care Works Hand in Hand with Causation in Personal Injury
Chiropractic care and the proof of causation reinforce each other. The initial examination captures the patient’s account of the mechanism of injury in their own words and correlates it with clinical findings. This establishes temporality and biological plausibility. Subsequent visits generate serial data on pain intensity, range of motion, strength, and functional capacity. Improvement that tracks with the expected healing timeline and with specific interventions strengthens the argument that the documented injuries are trauma-related rather than purely degenerative or coincidental.
Objective measures matter. Goniometry quantifies restricted motion. Manual muscle testing or dynamometry records strength deficits. Orthopedic tests reproduce the patient’s symptoms in patterns consistent with the injury mechanism. These findings, recorded contemporaneously, create a paper trail that is difficult to dismiss. When pre-existing conditions exist, careful comparison with prior records or imaging allows the clinician to distinguish baseline change from acute aggravation. For instance, new asymmetric muscle guarding or a sudden drop in range of motion that matches the direction of force supports a causal contribution from the incident.
Chiropractic documentation also addresses the natural history of soft-tissue injury. Early restoration of motion can interrupt the cycle of pain, muscle guarding, and further restriction. Consistent attendance and progressive gains demonstrate that the condition responds to care in a manner expected for trauma-related injury. This continuity of care supplies the contemporaneous evidence that courts and evaluators prefer over later retrospective opinions.
Physiological Underpinnings of How Chiropractic Care Reduces Muscle Pain
Muscle pain after trauma often arises from a combination of direct tissue strain, protective muscle guarding, joint hypomobility, and altered sensory input. Restricted joints increase nociceptor discharge while reducing normal mechanoreceptor signaling from muscle spindles and joint receptors. This abnormal afferent input can facilitate segmental reflex activity, increasing muscle tone, local ischemia, and pain. Over time, central sensitization may amplify pain perception.
Spinal manipulation produces a rapid afferent volley from mechanoreceptors in the manipulated segment and surrounding tissues. Research indicates that this input can reduce the excitability of dorsal horn neurons involved in pain transmission, consistent with gate-control mechanisms. Studies have shown short-term increases in pressure-pain thresholds and reductions in segmental mechanical hyperalgesia following manipulation. Motor-neuron excitability is also modulated. High-threshold afferent stimulation can inhibit excessive muscle activity, helping to interrupt the pain-spasm-pain cycle. Electromyographic studies have reported decreased resting muscle activity in paraspinal muscles after manipulation in symptomatic individuals.
Additional mechanisms include improved local circulation, reduced inflammatory mediators in the immediate area, and facilitation of normal joint kinematics. Restored motion allows better load sharing across tissues and may promote organized collagen remodeling. When combined with soft-tissue techniques, this approach addresses adhesions and normalizes muscle length-tension relationships. Graded exercise then retrains motor control and endurance, reducing the risk of recurrent strain.
These effects are not limited to the manipulated segment. Heterosegmental and supraspinal modulation can occur, including changes in descending pain-inhibitory pathways. Clinical trials and systematic reviews report modest to moderate short-term reductions in pain intensity and improvements in function for low back and neck pain when spinal manipulative therapy is compared with sham or no treatment, particularly when integrated with exercise and education. Adverse events are typically mild and transient, such as temporary soreness.
In clinical observations at Injury Medical Clinic PA, patients who receive early restoration of joint motion, along with soft-tissue care and progressive activity, often report better sleep, less compensatory pain in distant regions, and a faster return to work than those managed primarily with rest or passive modalities alone. These observations align with the literature supporting multimodal, non-pharmacologic approaches.
How Chiropractic Care Reduces Muscle Pain and Its Comorbidities in the Body
Muscle pain rarely remains isolated. Restricted motion and guarding alter posture and movement patterns, producing compensatory overload in adjacent or contralateral muscles and joints. This can lead to secondary headaches, mid-back pain, hip or pelvic dysfunction, and even changes in gait that stress lower-extremity structures. Chronic pain further disrupts sleep, elevates stress hormones, reduces physical activity, and contributes to deconditioning and mood changes.
Chiropractic care interrupts these cascades. By restoring segmental motion and reducing abnormal afferent drive, it decreases local muscle hypertonicity and improves proprioceptive input. Better joint mechanics allow more normal muscle recruitment, reducing the need for compensatory strategies. Soft-tissue work and exercise address residual tightness and weakness. Over successive visits, measurable gains in range of motion and strength correlate with reduced pain scores and improved daily function.
Comorbidities such as sleep disruption often improve once pain and muscle guarding decrease, because nocturnal muscle activity and positional discomfort lessen. Reduced pain also supports greater activity levels, which in turn help maintain muscle mass, joint nutrition, and cardiovascular health. Systematic reviews indicate that spinal manipulative therapy, especially when combined with exercise, can produce clinically meaningful reductions in pain and disability for chronic low back pain, with benefits extending to related neck pain and certain headache types. In personal injury populations, early conservative care has been associated with lower rates of prolonged disability and reduced need for more invasive interventions in observational data.
Each component is grounded in practical reasoning. Adjustments target joint restriction that perpetuates abnormal loading. Soft-tissue techniques address the muscle and fascial components that maintain pain and limited motion. Exercise rebuilds capacity and motor control so patients retain gains. Education helps patients avoid positions or activities that re-injure healing tissues. Medical oversight ensures systemic factors, red flags, and medication needs are managed appropriately.
How Chiropractic Care Can Provide Insight into Personal Injury
Chiropractic care supplies unique insight because practitioners often see patients early and repeatedly after trauma. The initial history and examination capture the mechanism in detail and establish a clinical baseline before significant secondary changes accumulate. Serial measurements document the injury’s natural history and its response to conservative care. This timeline helps differentiate trauma-related findings from chronic degenerative processes.
For example, a sudden loss of cervical rotation that improves progressively with care is more consistent with acute muscle and joint injury than with longstanding spondylosis. Objective testing performed at regular intervals creates data that can be compared across the recovery period. When imaging is obtained, clinical correlation with the mechanism and examination findings allows more precise opinions about whether specific abnormalities are likely acute, aggravated, or incidental.
In personal injury settings, this information assists attorneys and evaluators by providing a coherent clinical narrative grounded in contemporaneous records rather than later speculation. It also identifies when additional medical evaluation or imaging is warranted, supporting coordinated care. Clinical observations indicate that patients who can accurately describe their position at impact, the direction of force, and the immediate versus delayed symptoms allow more precise mechanism-to-finding linkage, which in turn supports clearer causation opinions.
Integrative Chiropractic Care Within Non-Surgical Treatment Pathways
Integrative chiropractic care fits within broader non-surgical strategies by combining manual joint and soft-tissue techniques with exercise, education, functional medicine support, and, when appropriate, other conservative modalities. Non-surgical pathways prioritize restoring function while minimizing risks associated with surgery or prolonged opioid use. Spinal manipulation or mobilization addresses joint restriction. Instrument-assisted or manual soft-tissue methods reduce adhesions and improve tissue mobility. Therapeutic exercise rebuilds strength, endurance, and motor control. Nutritional and lifestyle guidance under functional medicine principles can help modulate systemic inflammation that may slow recovery.
Computerized spinal decompression may treat disc-related issues by reducing intradiscal pressure and improving nutrient diffusion. Clinicians select these tools based on the healing phase and the specific tissue involved. Early care emphasizes pain control and restoring movement. Later phases focus on progressive loading and return to activity. Medical oversight from an internist helps screen for contraindications, manage comorbidities such as hypertension or diabetes that can affect healing, and coordinate any necessary imaging or specialist referral.
Research supports multimodal non-pharmacologic care. Guidelines recommend exercise, spinal manipulation, and other conservative approaches as first-line or early options for many musculoskeletal pain conditions. Observational and trial data indicate that integrated programs can reduce pain intensity, improve function, and lower the likelihood of escalation to more invasive care for appropriately selected patients. The rationale is that no single intervention addresses all contributors to muscle pain after trauma. Joint mechanics, muscle function, inflammation, motor control, and patient education each require attention for durable recovery.
The Multidisciplinary Team at Injury Medical Clinic PA and the Role of Dr. Maria Guadalupe Cardenas
Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, in El Paso, Texas, operates as a multidisciplinary practice. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, provides chiropractic care focused on spinal alignment, joint function, and related rehabilitation. Dr. Maria Guadalupe Cardenas, MD, board-certified in Internal Medicine, works with him. She brings over 40 years of experience as an internist, holds NPI #1164426749, and maintains Texas MD License #J2933. Dr. Cardenas serves as Medical Director and Collaborative Physician at the practice.
This arrangement is common in integrative and injury-care clinics. The medical director oversees complex cases, reviews systemic factors, ensures appropriate medical screening, and collaborates on treatment plans that may include medication management, laboratory evaluation, or referral when indicated. The chiropractor delivers hands-on spinal and musculoskeletal care, detailed documentation of mechanism and progress, and rehabilitation guidance. Together, they integrate functional medicine principles, personal injury documentation standards, and rehabilitation services.
The team addresses both mechanical and systemic contributors to recovery. For example, an internist’s evaluation can identify or manage conditions that influence inflammation or healing capacity, while chiropractic care restores joint motion and reduces muscle guarding. Shared records create a unified clinical narrative that supports both patient care and the causation analysis required in personal injury matters. Clinical observations from the practice emphasize that coordinated plans, precise mechanism documentation, and progress-adjusted interventions produce the most consistent functional gains.
Clinical Observations Supporting Integrated Care
Over more than three decades of practice, patients who receive early, precise documentation of their injury mechanism, along with care adjusted to measured progress, tend to recover function more reliably. Delayed symptom onset of one to three days is frequently observed after low-speed impacts involving rotation or lateral forces. Early restoration of joint motion, combined with soft-tissue care and graded activity, is associated with better sleep quality, fewer secondary compensatory pains, and an earlier return to work than prolonged rest alone. These patterns are consistent with published evidence on multimodal conservative care for musculoskeletal trauma.
Conclusion
Causation in personal injury cases involving muscle pain is established by showing that an incident more likely than not caused or substantially contributed to the diagnosed injuries and their functional consequences. Chiropractic care contributes by facilitating recovery through restored joint motion, reduced abnormal sensory input, and support for tissue healing, and by generating the contemporaneous objective records needed to demonstrate that causal link. When integrated with medical oversight from an experienced internist such as Dr. Maria Guadalupe Cardenas, functional medicine principles, and structured rehabilitation, the approach supports non-surgical recovery while meeting the documentation standards required in personal injury matters. Modern research on neurophysiological mechanisms and clinical outcomes continues to refine these methods, emphasizing individualized, evidence-informed care that addresses both the mechanical and broader physiological consequences of trauma.
References
- Hill, A. B. (1965). The environment and disease: Association or causation? Proceedings of the Royal Society of Medicine, 58(5), 295–300. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC1898525/
- Goertz, C. M., Long, C. R., Vining, R. D., Pohlman, K. A., Walter, J., & Colter, I. (2018). Effect of usual medical care plus chiropractic care vs usual medical care alone on pain and disability among US service members with low back pain: A comparative effectiveness clinical trial. JAMA Network Open, 1(1), e180105. https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2680417
- Pickar, J. G. (2002). Neurophysiological effects of spinal manipulation. The Spine Journal, 2(5), 357–371. https://www.sciencedirect.com/science/article/abs/pii/S152994300200400X
- Gevers-Montoro, C., Provencher, B., Descarreaux, M., Ortega de Mues, A., & Piché, M. (2021). Neurophysiological mechanisms of chiropractic spinal manipulation for spine pain. European Journal of Pain, 25(7), 1429–1448. https://doi.org/10.1002/ejp.1773
- Weeks, W. B., Leininger, B., Whedon, J. M., Lurie, J. D., Tosteson, T. D., Swenson, R., O’Malley, A. J., & Goertz, C. M. (2016). The association between use of chiropractic care and costs of care among older Medicare patients with chronic low back pain and multiple comorbidities. Journal of Manipulative and Physiological Therapeutics, 39(2), 63–75. https://www.jmptonline.org/article/S0161-4754(16)00007-5/abstract
- Additional supporting literature on spinal manipulative therapy outcomes and mechanisms is available through systematic reviews indexed in PubMed and Cochrane Library sources current through 2026.
SEO Tags
causation personal injury, muscle pain after accident, chiropractic care personal injury, integrative chiropractic El Paso, non-surgical treatment muscle pain, Dr Alexander Jimenez DC, Dr Maria Guadalupe Cardenas MD, Injury Medical Clinic PA, evidence-based chiropractic, Bradford Hill criteria injury, spinal manipulation muscle pain, personal injury documentation, functional medicine injury recovery
Disclaimer: This post is for educational purposes and does not constitute legal or medical advice. Individual results vary. Consult qualified professionals for personal circumstances. Clinical observations reflect practice patterns at Injury Medical Clinic PA in El Paso, Texas.

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Herniated Disc, Imaging & Diagnostics, Med-Legal Corner, Personal Injury
What a Lumbar Spine MRI Can and Cannot Tell a Jury About an Accident-Related Disc Injury
A lumbar spine MRI provides one of the clearest pictures medicine can give a jury of what is happening inside the low back after a crash, fall, or workplace impact. It shows the discs, the nerves, and the surrounding structures in high detail. Yet the same scan that reveals a herniation or compressed nerve root often leaves the most important legal questions unanswered: When did this finding appear, and was the accident the cause?
Defense experts frequently point to the MRI and call every abnormality “pre-existing degeneration.” That argument succeeds when the imaging is presented in isolation. It weakens when the MRI is viewed alongside the patient’s history, the collision mechanics, the examination findings, and serial clinical notes. Understanding what the scan can and cannot prove helps patients, clinicians, and attorneys interpret the evidence correctly.
How MRI Shows Lumbar Disc Herniations and Nerve Root Compression
The intervertebral disc has a soft, gel-like center (nucleus pulposus) surrounded by a tough outer ring (annulus fibrosus). On a T2-weighted MRI, the healthy nucleus appears bright because it holds water. When the annulus tears and nuclear material pushes outward, the MRI shows the displaced material as a protrusion, extrusion, or sequestration.
A herniation is called focal when it involves less than 25 percent of the disc circumference. Posterolateral herniations are the most common pattern after trauma because the posterior longitudinal ligament is thinner on the sides. When herniated material compresses a nerve root in the lateral recess or foramen, MRI can show the root flattened or displaced. Surrounding soft-tissue edema or a high-intensity zone (HIZ)—a bright spot on T2 images within the posterior annulus—further signals an acute or subacute annular tear.
Nerve-root compression is not always dramatic. Mild contact may still produce radicular pain through chemical inflammation from the herniated material rather than pure mechanical pressure. Clinical correlation remains essential: the side and level of the imaging finding must match the patient’s leg pain, numbness, or reflex changes. Digital range-of-motion measurements and electrodiagnostic studies (when indicated) help confirm that the compressed root, not an incidental finding, is causing the symptoms.
Degenerative Findings That Commonly Appear on MRI
Disc desiccation (darkening of the nucleus), multilevel bulging, small osteophytes, and mild facet arthropathy appear on MRI scans of many adults who have never been in a crash and who have no pain. Large population studies show that roughly one-third of asymptomatic people in their twenties already have disc bulges or protrusions; by the seventies and eighties the rate approaches 90 percent. These age-related changes do not automatically mean a patient’s current pain is unrelated to trauma.
The key distinction is between symmetric, multilevel, slowly progressive degeneration and a focal, asymmetric finding that matches the biomechanics of the accident and the patient’s new symptoms. An annular high-intensity zone that is bright, a few millimeters of unilateral disc-height loss, or a new extrusion at the level and side of impact is far more suggestive of traumatic aggravation than uniform drying across five levels.
MRI nomenclature follows standardized terms. A bulge is a broad-based extension greater than 25 percent of the circumference, usually from annular redundancy as the disc loses height. A protrusion remains contained by outer annular fibers; an extrusion has broken through them. These distinctions matter for both treatment planning and for explaining the finding to a jury, but the nomenclature itself does not assign cause or date. The official lumbar disc nomenclature notes that dating a herniation from images alone is unreliable; bright signal and surrounding inflammation suggest relative acuteness, yet those changes can persist for months.
Why the MRI Alone Does Not Establish Age or Cause
An MRI is a snapshot. It doesn’t carry a time stamp saying, “This herniation occurred on the day of the collision.” Even an acute-appearing high-intensity zone can remain bright for many months. Without prior imaging, the radiologist cannot know whether a disc protrusion existed silently before the crash. That is why defense experts correctly state that the presence of a herniation on MRI does not, by itself, prove the accident caused it.
Causation is established by linking several elements:
- The patient had no comparable radicular symptoms before the event.
- The mechanism (axial compression plus flexion or lateral shear typical of rear-end or side-impact collisions) is capable of tearing the annulus and forcing nuclear material posterolaterally.
- Symptoms began or dramatically increased shortly after the impact.
- The MRI finding matches the level, side, and clinical examination.
- Serial notes document ongoing functional limitations that track the imaging abnormality.
When these elements are present, the MRI becomes powerful objective evidence of traumatic aggravation under the Texas Eggshell Plaintiff rule. A pre-existing, asymptomatic disc that is torn and made symptomatic by the crash is still a compensable injury. The clinic’s records capture this linkage in plain language so that the attorney and the jury can follow the chain from collision forces to specific MRI morphology.
The Role of Clinical Correlation and Multidisciplinary Documentation
Radiology reports describe anatomy; they do not decide legal causation. The treating clinician must integrate the images with the history, the physical examination, and the functional status. Digital range-of-motion testing, postural analysis, and response to conservative care provide additional objective data that MRI alone cannot.
At Injury Medical Clinic PA, the dual-licensed team coordinates these pieces. Dr. Alex Jimenez, DC, APRN, FNP-BC, documents soft-tissue and structural findings, correlates them with the mechanism of injury and MRI, and tracks the response to non-invasive care. Dr. Maria Guadalupe Cardenas, MD, provides medical direction, reviews metabolic and inflammatory factors that affect disc healing, and ensures the overall clinical picture is medically coherent. The result is a continuous, Colossus-compliant record that withstands cross-examination far better than isolated imaging reports.
Patients benefit from this approach through clearer understanding of their condition, safer non-drug options such as targeted chiropractic care, spinal decompression, and electroacupuncture, and better coordination with any outside physicians. Attorneys receive the objective linkage needed for Letters of Protection and trial. Clinicians outside the clinic can rely on the same transparent interpretation when they review the records.
What Makes the Clinic Unique
- Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is the only practice in El Paso, Texas, that integrates a board-certified internal medicine medical director with a dual-licensed chiropractor and nurse practitioner who specializes in soft-tissue and disc injury.
- Dr. Maria Guadalupe Cardenas, MD, provides medical direction and advanced laboratory oversight for patients with metabolic conditions that affect recovery.
- Dr. Alex Jimenez, DC, APRN, FNP-BC, focuses on the structural and soft-tissue consequences of trauma, using precise imaging correlation, digital functional testing, and non-invasive therapies. This single-clinic model produces unified documentation rather than fragmented records from separate providers, giving both patients and attorneys a clearer, more defensible account of how the accident affected the lumbar spine.
For deeper discussion of how imaging findings are tied to causation, see the detailed review of advanced spinal MRI interpretation for attorneys at dralexjimenez.com and the explanation of why abnormal MRI findings do not automatically establish injury age. The standardized lumbar disc nomenclature used in these reports is also available for reference.
An MRI is indispensable, but it is only one piece of the story. Read in context with the mechanism, history, and clinical course, it becomes courtroom-ready evidence of traumatic disc injury rather than an ambiguous picture the defense can relabel as ordinary aging.
Feeling Better Than Ever After a Semi-Truck Accident | El Paso, TX
References
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. https://doi.org/10.3174/ajnr.A4173
Fardon, D. F., & Milette, P. C. (2001). Nomenclature and classification of lumbar disc pathology: Recommendations of the combined task forces of the North American Spine Society, American Society of Spine Radiology, and American Society of Neuroradiology. Spine, 26(5), E93–E113. https://doi.org/10.1097/00007632-200103010-00006
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Gabriel Rothman, S. L., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Aprill, C., & Bogduk, N. (1992). High-intensity zone: A diagnostic sign of painful lumbar disc on magnetic resonance imaging. British Journal of Radiology, 65(773), 361–369. https://doi.org/10.1259/0007-1285-65-773-361
Boden, S. D., Davis, D. O., Dina, T. S., Patronas, N. J., & Wiesel, S. W. (1990). Abnormal magnetic-resonance scans of the lumbar spine in asymptomatic subjects. A prospective investigation. Journal of Bone and Joint Surgery, 72(3), 403–408. https://doi.org/10.2106/00004623-199072030-00013
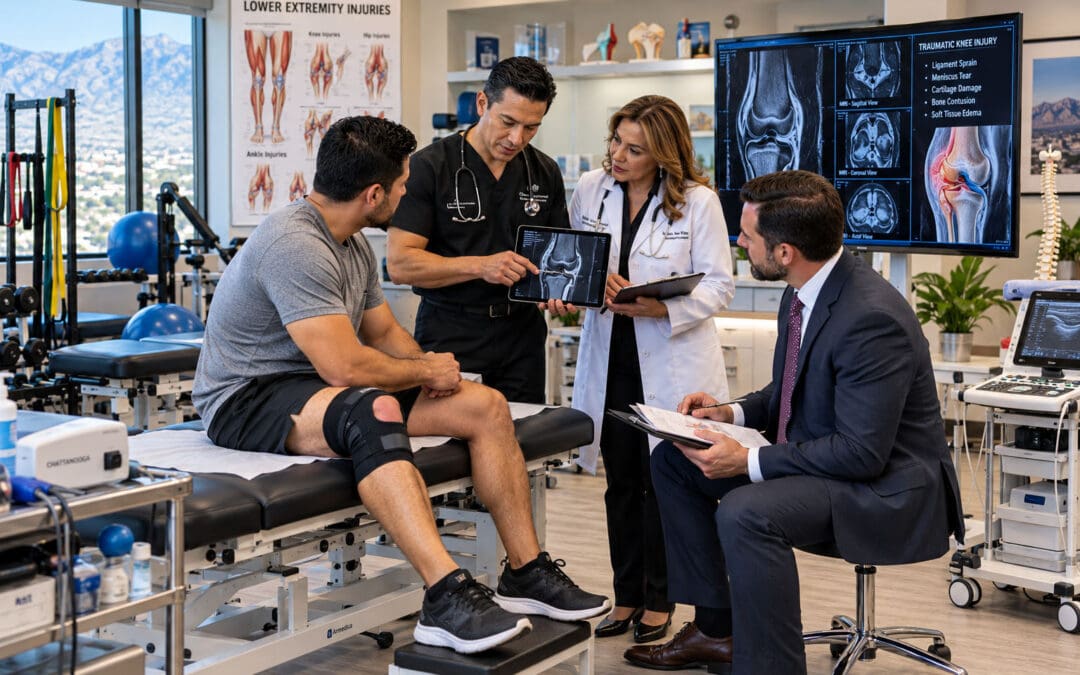
by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Chiropractic Examination, Imaging & Diagnostics, Lower Back Pain, Med-Legal Corner
Why the Location of Back Pain Matters When an Accident Injury Is Disputed
After a car crash, slip-and-fall, or workplace accident, a patient may tell a doctor, “My back hurts.” Clinically, that statement is only the beginning.
Where does the pain begin? Does it stay in the center of the lower back? Is it stronger on one side? Does it spread into the buttock, thigh, calf, or foot? Is there numbness, tingling, weakness, or a change in walking?

Those details matter because the location and distribution of back pain can help clinicians determine whether a patient’s symptoms fit a proposed structural or neurological diagnosis. They become even more important when an insurance company, defense expert, or opposing attorney disputes whether an accident caused the condition.
Pain location does not prove causation by itself. Instead, clinicians look for agreement among the patient’s history, spinal examination, neurological findings, functional limitations, diagnostic imaging, and accident mechanism.
Back Pain Is a Symptom, Not a Diagnosis
Back pain can arise from many structures. Muscles, ligaments, spinal joints, intervertebral discs, nerve roots, and the sacroiliac region can all produce pain in or around the lower back. Conditions outside the spine can sometimes produce similar symptoms.
That is why clinicians begin by defining the pattern.
Pain centered across the lumbar region may be associated with muscular, joint, or disc-related problems. One-sided pain around the lower back or buttock can originate from several musculoskeletal structures. Pain that travels from the back or buttock down a leg raises additional questions about nerve involvement, particularly when it occurs with numbness, tingling, weakness, or altered reflexes.
Clinical research supports evaluating lumbosacral radicular pain through a combination of symptom history, pain distribution, examination findings, and additional testing when appropriate—not through one symptom in isolation (Peene et al., 2024).
Patients wanting a deeper explanation of radiating symptoms can review Dr. Jimenez’s discussion of radiculopathy and sciatica.
Why the Location of Back Pain Matters
Imagine two people with lower-back pain after similar rear-end collisions.
The first person has soreness mainly in the lumbar muscles and stiffness when bending.
The second has lower-back pain that travels through one buttock, down the outside of the leg, and toward the foot. That patient also reports tingling and difficulty walking on the heel.
Both patients have back pain, but their clinical presentations are different.
The second pattern raises more concern for possible nerve-root involvement. A clinician would therefore pay particular attention to sensation, muscle strength, reflexes, gait, and neural tension during the examination.
Research has found that findings such as sensory disturbance, myotomal weakness, decreased reflexes, focal muscle changes, and certain neural tension findings can support a diagnosis of radiculopathy when interpreted together (Bateman et al., 2025).
Pain Patterns Are Helpful—but They Are Not Perfect Maps
Clinicians sometimes compare radiating pain to dermatomes, areas of skin associated with particular spinal nerve roots.
However, the human nervous system doesn’t always follow a textbook diagram.
Studies of patients with confirmed lumbar nerve-root problems have found substantial overlap between pain distributions. Therefore, a patient does not need to trace a perfect line on a dermatome chart for a nerve problem to be possible.
This distinction is especially important in personal injury cases. Pain distribution can support a diagnosis, but it shouldn’t be used alone to claim a particular disc or nerve root caused the symptoms.
The stronger question is:
Does the complete neurological and biomechanical pattern make sense?
What a Spinal Examination Looks For
When accident-related back pain is disputed, a thorough examination provides information that a pain rating alone cannot.
A clinician may compare both sides of the body and evaluate how the patient moves, walks, bends, sits, and responds to specific tests. Common examination components can include:
- Lumbar range of motion and movement tolerance
- Palpation for tenderness, muscle guarding, or spasm
- Orthopedic and neurological provocation testing
- Straight-leg raise or related neural tension procedures
- Lower-extremity muscle strength
- Sensory testing
- Patellar and Achilles reflexes
- Heel and toe walking
- Gait and balance
- Functional tolerance for sitting, standing, bending, lifting, and walking
No single examination maneuver proves a spinal diagnosis.
Newer research has made that point even clearer. A 2026 systematic review found that the straight-leg raise and crossed straight-leg raise tests, by themselves, generally produced only limited changes in the probability of lumbosacral radicular pain. The practical lesson is that clinicians should combine tests rather than diagnose based on one positive maneuver (Nee et al., 2026).
Do the Symptoms Match the Structural Diagnosis?
Suppose an MRI identifies a lumbar disc herniation.
That finding matters, but another question immediately follows:
Does the disc finding explain this patient’s symptoms?
A stronger clinical match includes a disc abnormality that can affect a particular nerve root, pain and sensory complaints in a reasonably compatible area, corresponding strength or reflex changes, and functional limitations consistent with the involved nerve.
Current WFNS Spine Committee recommendations emphasize history, pain localization, muscle strength, sensory testing, sphincter function, and appropriate neurological testing when evaluating suspected lumbar disc herniation. MRI is the preferred imaging study to confirm a suspected disc herniation when advanced imaging is clinically warranted (Pojskic et al., 2024).
Dr. Jimenez provides additional patient education about lumbar herniated discs and sciatica.
An MRI Finding Is Not Automatically Proof of Accident Causation
This distinction is critical for both patients and attorneys.
An MRI can show anatomy. It may demonstrate a disc protrusion, herniation, stenosis, degeneration, or another abnormality. But the image alone usually cannot tell an attorney exactly when that abnormality developed or whether a specific collision made it symptomatic.
Some spinal abnormalities can exist before an accident without producing significant symptoms.
That is why clinicians correlate imaging with the history and examination rather than simply pointing to an MRI and declaring causation.
Current recommendations also discourage routine imaging for uncomplicated acute low-back pain. Imaging becomes more appropriate when red flags are present, radicular symptoms persist, neurological deficits progress, or another clinical reason warrants further investigation (Gushcha et al., 2024).
What If the Pain Pattern Does Not Fit?
A careful clinician should not try to force every symptom into a spinal diagnosis.
Hip disorders, tendon injuries, muscle problems, peripheral nerve disorders, neuropathy, vascular conditions, and other musculoskeletal conditions can sometimes resemble lumbar radiculopathy. Some can even coexist with a spinal injury.
A recent review emphasized the importance of distinguishing true lumbosacral radiculopathy from musculoskeletal conditions that can produce similar radiating pain or weakness (Bateman et al., 2025).
This differential diagnosis becomes especially valuable when an injury claim is challenged.
A medically defensible causation opinion should identify reasonable competing explanations, evaluate them, and explain why the available evidence supports or does not support each possibility.
Connecting the Accident Mechanism to the Symptoms
The next step is to ask whether the accident mechanism is compatible with the proposed injury.
Motor-vehicle crashes can expose the spine and surrounding soft tissues to rapid acceleration, deceleration, compression, rotation, or combined forces. Depending on the circumstances, those forces may affect muscles, ligaments, joints, discs, or neural structures. Dr. Jimenez discusses these mechanisms further in his resource on spinal injuries following motor-vehicle collisions.
Consider a patient who had no meaningful radiating leg symptoms before a crash but soon afterward developed unilateral low-back pain extending into the leg. The examination then identifies compatible sensory loss, weakness, or reflex changes, and clinically appropriate imaging demonstrates a corresponding structural abnormality.
That sequence provides a more coherent causation analysis than simply saying, “The MRI showed a disc problem.”
Clinicians also review prior injuries, previous imaging, medical conditions, treatment history, subsequent accidents, and other possible causes. Injury Medical Clinic’s current medical-legal guidance similarly emphasizes evaluating symptom timing, prior history, neurological findings, imaging, functional limitations, and alternative causes rather than relying on one test.
Attorneys can review that discussion in Medical-Legal Causation Opinions for Attorneys Explained.
Functional Limitations Add Another Layer of Evidence
Pain tells clinicians what the patient feels. Function shows what the condition prevents the patient from doing.
An accident victim may have difficulty sitting through a workday, getting out of a vehicle, lifting a child, climbing stairs, carrying groceries, sleeping comfortably, exercising, or walking for extended periods.
Documenting those limitations helps connect the diagnosis to real-world impairment.
Repeated examinations are also valuable. If strength, range of motion, walking tolerance, and everyday function improve as the patient recovers, clinicians can compare those objective and functional changes over time.
That creates a more complete clinical record than repeatedly documenting only “pain 7/10.”
What Makes Injury Medical Chiropractic and Functional Medicine Clinic Different?
Injury Medical Chiropractic and Functional Medicine Clinic in El Paso uses a multidisciplinary structure that brings structural, neurological, functional, and medical evaluations together.
The Natural Way to Heal: Non-Surgical Chiropractic Care for Pain Relief | El Paso, TX
Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of experience, serves as Medical Director and Collaborative Physician. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, is dual-licensed as a Doctor of Chiropractic and board-certified Family Nurse Practitioner. This allows the clinic to coordinate chiropractic biomechanics and soft-tissue injury evaluation with advanced-practice nursing assessment and medical oversight. The clinic website confirms Dr. Cardenas’s medical-director role and Dr. Jimenez’s dual clinical credentials.
The clinic describes this coordinated combination of chiropractic care, medical oversight, soft-tissue injury evaluation, rehabilitation, diagnostic assessment, acupuncture/electroacupuncture, and advanced treatment options as a unique model in El Paso. Rather than requiring every patient to follow the same protocol, the multidisciplinary approach matches treatment and referrals to examination findings, medical risk, patient preferences, and existing healthcare relationships.
That approach also supports three important principles: helping patients recover function and reduce pain, choosing conservative and non-invasive options when appropriate, and giving patients enough information to participate meaningfully in decisions about their care.
When Back Pain Needs More Urgent Evaluation
Conservative spine care may help appropriate patients improve pain, mobility, sleep, and physical function. Clinicians may incorporate chiropractic care, rehabilitation, mobility work, acupuncture, and electroacupuncture when clinically appropriate.
But treatment should always follow the diagnosis.
New bowel or bladder dysfunction, saddle-area numbness, rapidly progressive leg weakness, significant neurological deterioration, or other signs of serious neural compression require urgent medical assessment rather than routine musculoskeletal treatment. Guidelines specifically identify progressive neurological deficits and bowel or bladder dysfunction as reasons for further investigation.
The Bottom Line: Location Helps Build the Clinical Story
When an accident-related back injury is disputed, where the pain occurs matters—but it’s only the beginning of the analysis.
Strong clinical reasoning looks for agreement among the accident mechanism, symptom timing, pain distribution, spinal examination, neurological findings, imaging, medical history, competing explanations, and functional limitations.
For patients, the lesson is simple: describe your symptoms precisely. Tell your clinician where the pain starts, where it travels, whether you experience numbness or weakness, which movements make it worse, and what you can no longer do comfortably.
For attorneys, the lesson is equally important: don’t evaluate a spinal injury claim based on a single MRI phrase or pain score. Look at whether the complete clinical record demonstrates a coherent relationship between the mechanism of trauma, the patient’s symptoms, objective findings, diagnosis, and resulting functional impairment.
A well-documented examination does more than attach a diagnostic label to back pain.
It explains why the diagnosis fits—or does not fit—the patient standing in front of the clinician.
References
Bateman, E. A., Fortin, C. D., & Guo, M. (2025). Musculoskeletal mimics of lumbosacral radiculopathy. Muscle & Nerve, 71(5), 816–832. PubMed record
Gushcha, A. O., Sharif, S., Zileli, M., Oertel, J., Zygourakis, C. C., & Yusupova, A. R. (2024). Acute back pain: Clinical and radiologic diagnosis: WFNS Spine Committee recommendations. World Neurosurgery: X, 22, 100278. PubMed record
Nee, R. J., Boyd, B. S., Sierra-Silvestre, E., & Coppieters, M. W. (2026). Diagnostic accuracy of the straight leg raise test for lumbosacral radicular pain: A systematic review with meta-analysis. Musculoskeletal Science and Practice, 86, 103666. PubMed record
Peene, L., Cohen, S. P., Kallewaard, J. W., Wolff, A., Huygen, F., van de Gaag, A., Monique, S., Vissers, K., Gilligan, C., Van Zundert, J., & Van Boxem, K. (2024). Lumbosacral radicular pain. Pain Practice, 24(3), 525–552. PubMed record
Pojskic, M., Bisson, E., Oertel, J., Takami, T., Zygourakis, C., & Costa, F. (2024). Lumbar disc herniation: Epidemiology, clinical and radiologic diagnosis—WFNS Spine Committee recommendations. World Neurosurgery: X, 22, 100279. PubMed record

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Herniated Disc, Med-Legal Corner, Personal Injury, Spinal Decompression Treatments
Why Mechanism-to-MRI Linkage of Disc Injury Is Required to Justify Lumbar Causation at Trial
Abstract
Defense counsel routinely labels annular tears and modest disc-height loss as “pre-existing degeneration.” A precise mechanism-to-MRI linkage—correlating specific highway force vectors (axial compression, lateral shear, rotation) to the level, side, and morphology of the imaging findings—is required to establish clinical and proximate causation under Texas law and to support special damages for future non-surgical care. This article shows attorneys how structural MRI, timed to the collision and interpreted against the Texas Eggshell Plaintiff framework, neutralizes those challenges while future-care projections for extracorporeal shockwave therapy (ESWT) and spinal decompression document ongoing structural needs.
Imagine the defense expert in an El Paso courtroom pointing at a lumbar MRI and stating, “The annular fissure and 2 mm height loss are age-related.” Without a clear biomechanical bridge from the crash forces to those exact findings, the jury is left with competing medical opinions, and the claim is vulnerable. Mechanism-to-MRI linkage supplies that bridge. It converts a radiologic observation into courtroom-ready evidence of traumatic aggravation.
The Trial Reality of Annular Tears and Disc-Height Challenges
Annular tears (more precisely termed annular fissures in NASS nomenclature) and measured disc-height loss are the two findings most often attacked as pre-existing. Defense radiologists emphasize that high-intensity zones on T2-weighted images can appear in asymptomatic individuals and that modest height loss is common after age 40 (Fardon et al., 2014). Attorneys therefore need more than the finding’s mere presence; they must show that the morphology, laterality, and timing match the collision’s known force vectors and differ from multilevel, symmetric baseline degeneration.
Texas law does not require a perfectly healthy spine. Under the Eggshell Plaintiff doctrine (PJC 28.8 series), the defendant takes the plaintiff as found. If the collision created a new fissure, extended a pre-existing one, or accelerated previously asymptomatic height loss, the resulting functional impairment and future care are compensable (Texas Pattern Jury Charges). The clinical task is to document that acceleration with objective imaging and a reasoned causation narrative.
Correlating Highway Force Vectors to Structural MRI
A high-speed impact on an El Paso corridor transmits forces in milliseconds. Pure axial compression from a rear-end or frontal collision loads the disc vertically, increasing intradiscal pressure and stressing the annulus. Lateral or oblique impacts (common on Loop 375 and similar highways) add shear and rotational components that preferentially load the posterolateral fibers—the anatomically weakest region of the annulus (NCBI StatPearls, 2023). When those forces exceed tissue tolerance, a radial or transverse fissure forms, nuclear material migrates or dehydrates, and measurable height loss appears at the loaded level.
Key imaging correlates that support causation include:
- Single- or dominant-level abnormality matching the predicted segment (commonly L4–L5 or L5–S1 after low-lumbar loading).
- Asymmetric high-intensity zone or height reduction greater on the side of the force vector.
- Temporal relationship: symptoms beginning immediately or within days, with MRI performed after the collision and compared, when available, to any pre-accident imaging.
- Distinction from baseline: the traumatic pattern is focal and asymmetric, while degenerative change is typically multilevel and symmetric.
Clinic notes at Injury Medical Clinic PA capture this linkage in plain language: “The left posterolateral L4–L5 annular high-intensity zone and 2 mm asymmetric disc-height reduction are morphologically and temporally consistent with the lateral shear and rotational forces of the collision. These findings differ from the mild, symmetric multilevel desiccation representing age-related baseline change.” Such statements survive Colossus review and deposition because they rest on biomechanics, not advocacy.
For deeper discussion of how chiropractic and medical records establish causation elements (mechanism, temporal association, biological plausibility, and exclusion of alternatives), see Causation: Understanding Its Role With Chiropractic Care. Attorneys preparing expert reports will also find practical guidance in Medical Legal Causation Opinions for Attorneys Explained.
Future-Care Projections That Support Special Damages
Once the mechanism-to-MRI link is established, the same objective findings justify future non-surgical interventions that restore disc hydration and height. Spinal decompression reduces intradiscal pressure, promotes nutrient inflow, and has been shown to improve height and pain in selected lumbar disc cases (Choi et al., 2017). Extracorporeal shockwave therapy (ESWT) stimulates neovascularization and extracellular-matrix remodeling; recent laboratory and clinical observations indicate it can attenuate endplate degeneration under compressive stress and facilitate resorption of herniated material (Frontiers in Bioengineering and Biotechnology, 2026; Orthopedic Reviews case report, 2026).
These modalities are not speculative. When serial MRI or functional testing demonstrates persistent height loss or annular signal that correlates with ongoing symptoms, a future-care spreadsheet listing a defined course of decompression and ESWT is supported by the same causation evidence that proves the injury. The resulting impairment evidence is packaged inside medical-legal causation documentation standards at https://dralexjimenez.com.
Bioethical Integration of Care
Beneficence is realized when chiropractic spinal adjustments, decompression, and ESWT are combined with MD/NP-directed laboratory and imaging oversight to restore structural integrity at the disc level rather than merely mask symptoms.
Non-maleficence is achieved by prioritizing these non-invasive, drug-free options, thereby delaying or avoiding the risks of surgery or prolonged opioid exposure.
Autonomy places the patient in control of the imaging timeline and treatment decisions. The clinic orders serial MRI scans when clinically indicated, explains results in plain language, and lets the patient coordinate care with any existing medical team.
What Makes the Clinic Unique
- Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is the only practice in El Paso, Texas, that integrates a board-certified internal medicine medical director with a dual-licensed chiropractor/nurse practitioner specializing in soft-tissue and disc injury.
- Dr. Maria Guadalupe Cardenas, MD (Texas License #J2933, NPI 1164426748), provides medical direction, advanced laboratory panels, and risk stratification for complex metabolic comorbidities that influence disc healing.
- Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP (Texas License #1191402, Prescriptive Authority #59628, NPI 1205907805), delivers structural and regenerative interventions—chiropractic adjustments, spinal decompression, ESWT, and electroacupuncture—while maintaining complete collaborative notes that meet clinical and legal standards. This dual-credentialed, single-clinic model eliminates fragmented records and supplies the continuous, objective documentation attorneys require for Letters of Protection and trial.
From Injury to Recovery (with Chiropractic Care) | El Paso, TX
Practical Documentation Checklist for Counsel
- Accident reconstruction or black-box data establishing direction and approximate magnitude of force.
- Immediate or near-immediate symptom onset recorded in emergency or early clinical notes.
- MRI protocol that includes T2 sagittal and axial images with measurements of height loss and description of annular signal laterality.
- Comparison to any pre-accident imaging or, in its absence, clear language distinguishing focal traumatic morphology from multilevel degenerative baseline.
- Functional testing (range of motion, neurologic exam, patient-reported outcome scores) timed to imaging.
- Future-care cost projections tied to the same structural findings that support causation.
When these elements are present, annular tears and disc-height loss stop being defense talking points and become the foundation of special damages. Patients regain mobility and sleep quality through non-invasive care, while attorneys get courtroom-ready proof that the collision—not ordinary aging—caused measurable structural change.
Schedule a comprehensive evaluation at Injury Medical Clinic PA. The team will map the collision’s force vectors to current MRI findings, design a plan to restore disc hydration and height, and prepare the objective documentation needed for trial or settlement.
References
Choi, J., Lee, S., & Hwangbo, G. (2017). Influences of spinal decompression therapy and general traction therapy on the pain, disability, and straight leg raising of patients with intervertebral disc herniation. Journal of Physical Therapy Science, 29(4), 697–699. https://doi.org/10.1589/jpts.29.697
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Rothman, S. L. G., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0: Recommendations of the combined task forces of the North American Spine Society, the American Society of Spine Radiology, and the American Society of Neuroradiology. The Spine Journal, 14(11), 2525–2545. https://doi.org/10.1016/j.spinee.2014.04.022
Frontiers in Bioengineering and Biotechnology. (2026). ESWT attenuates compressive stress-induced cartilaginous endplate degeneration via modulation of the SOST/Wnt/β-catenin signaling pathway. Frontiers in Bioengineering and Biotechnology, 14, Article 1769920. https://doi.org/10.3389/fbioe.2026.1769920
StatPearls. (2023). Annular disc tear. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK459235/
Texas Pattern Jury Charges—General Negligence, Intentional Personal Torts & Workers’ Compensation. (2024). Committee on Pattern Jury Charges, State Bar of Texas.

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Chiropractic, Chronic Pain, Health, Injury Care, Personal Injury, Treatments, Viscerosomatic Reflex
Explore the role of causation in personal injury combined with chiropractic care and how it can affect your recovery journey.
Abstract
Causation forms the indispensable legal and clinical bridge that connects a specific traumatic event—such as a motor vehicle collision, workplace incident, or slip-and-fall—to the musculoskeletal injuries that entitle an individual to fair recovery of damages in personal injury claims. Without rigorous demonstration that the incident caused or materially contributed to the diagnosed harm, even substantial pain, functional loss, and documented disability may fail to support full compensation. This educational post, written for attorneys, clinicians, and patients, explains why causation matters in court, how evidence-based standards, including the Bradford Hill criteria and reasonable medical probability, support it, and how modern chiropractic care provides critical contemporaneous clinical insight that strengthens both causation opinions and patient recovery. Chiropractic care is defined as a licensed, evidence-based profession focused on the neuromusculoskeletal system that restores joint motion, modulates pain signaling, reduces local inflammation, and supports natural healing without defaulting to surgery or prolonged pharmaceuticals. Drawing on recent research from leading investigators, the post details the physiological underpinnings of spinal and extremity adjustments—including afferent bombardment of mechanoreceptors, segmental and descending pain modulation, improved local circulation, and effects on inflammatory mediators such as TNF-α, IL-6, and BDNF. It further explains how chiropractic interventions reduce musculoskeletal injuries and their common comorbidities, including central sensitization, compensatory strain, sleep disruption, reduced activity, and opioid reliance. The narrative integrates the multidisciplinary model at Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, where Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), with more than 40 years of experience as an internist, serves as Medical Director and Collaborative Physician. This setup combines Dr. Jimenez’s chiropractic and advanced-practice nursing expertise with internal medicine oversight, functional medicine, rehabilitation, and non-surgical regenerative options. Clinical observations from decades of practice, along with resources at elpasobackclinic.com and related professional profiles, show how the team delivers durable functional recovery and the objective documentation attorneys need to establish causation to a reasonable degree of medical probability. The journey from injury mechanism through evidence-based conservative care to courtroom-ready insight is presented in clear, sequential sections so readers can follow the logic from biomechanics and physiology to practical legal and clinical application.
Why Causation Is Essential and Required in the Courtroom for Injury Claims
In every personal injury action grounded in negligence, the plaintiff must prove by a preponderance of the evidence—more likely than not—that the defendant owed a duty, breached that duty, and that the breach was both the actual and proximate cause of the claimed injuries and damages. Actual cause, often tested by the “but-for” inquiry, asks whether the injury would have occurred in the absence of the incident. Proximate or legal cause asks whether the harm was a reasonably foreseeable result of the conduct and whether the causal chain is close enough to justify imposing liability. Medical causation sits at the center of this proof: expert testimony is typically required to establish that the trauma produced the specific diagnoses, that the mechanism is biologically plausible, and that alternative explanations are less likely.
Courts and insurance evaluators demand this linkage because pain and functional limitation alone do not establish liability. Pre-existing degenerative changes, prior injuries, or unrelated conditions can produce similar symptoms. Without contemporaneous records that capture the mechanism of injury, the precise timing of symptom onset or aggravation, objective findings such as restricted range of motion, positive orthopedic tests, and correlated imaging, and a treatment response consistent with expected tissue-healing phases, claims are vulnerable to minimization or dismissal. Delayed symptom onset does not defeat causation in soft-tissue injuries. Strains, sprains, facet capsule injuries, and annular disc disruptions often generate progressive inflammation and protective muscle guarding that peak hours to days later as chemical mediators accumulate. Thorough documentation of impact direction, occupant position, restraint use, and progressive clinical findings distinguishes trauma-related injury from the natural history of pre-existing conditions.
The Bradford Hill criteria, originally articulated by epidemiologist Sir Austin Bradford Hill in 1965, supply a structured framework for evaluating whether an observed association is likely causal. These include strength of association, consistency, specificity, temporality (exposure must precede outcome), biological gradient, plausibility, coherence with existing knowledge, experimental evidence, and analogy. In musculoskeletal personal injury, temporality and biological plausibility carry particular weight. Symptoms that begin or clearly intensify after a documented collision whose forces are consistent with known tissue tolerances support the causal inference. When the same treating provider examines the patient early, records baseline objective measures, follows the response to care through the inflammatory, proliferative, and remodeling phases of healing, and rules out more probable alternative causes, the resulting opinion rests on direct clinical observation rather than retrospective speculation.
Recent appellate decisions in multiple jurisdictions confirm that properly qualified chiropractors may offer causation testimony within the scope of their practice. In Virginia, courts have recognized that authorizing chiropractors to testify about etiology and diagnosis within the scope of chiropractic expressly permits opinions on the causation of human physical injury. Michigan appellate rulings have held that licensed chiropractors may diagnose musculoskeletal and nervous system conditions related to subluxations, misalignments, and joint dysfunctions and may therefore develop and testify about the underlying cause of such conditions when a proper foundation is laid. These rulings align with longstanding principles that expert opinions are admissible when they fall within the witness’s specialized knowledge and rest on reliable methodology. Clinical causation (the injury is consistent with the mechanism) must be distinguished from legal causation (more likely than not that the incident caused or substantially contributed to the injury). Treating providers who document both the acute presentation and the recovery trajectory supply the continuity that strengthens the latter.
Legal Justification of Causation Through Evidence-Based Clinical Documentation
The justification for requiring and accepting causation evidence rests on both fairness and scientific reliability. Defendants should not be held liable for conditions that pre-existed or arose independently; plaintiffs should not be denied recovery for genuine trauma-related harm simply because soft-tissue injuries lack dramatic radiographic findings. Expert testimony must meet reliability standards such as those articulated in Daubert v. Merrell Dow Pharmaceuticals, which evaluate whether the theory can be tested, has been subjected to peer review and publication, has a known or potential error rate, is subject to controlling standards, and is generally accepted in the relevant community. Biomechanical analysis that correlates impact severity, occupant kinematics, and tissue-specific tolerances with clinical diagnoses supplies one such reliable methodology.
In the personal injury setting, serial clinical records create a temporal map. An initial examination that records the patient’s description of the mechanism, immediate or progressive symptoms, and objective findings such as limited cervical rotation, positive Spurling’s or straight-leg-raise tests, and postural deviations establishes the baseline. Subsequent visits documenting decreasing pain scores, increasing goniometric ranges of motion, improved strength, and reduced functional limitations show a recovery trajectory consistent with the expected phases of soft-tissue healing. When these improvements occur under conservative care and alternative explanations have been considered and found less likely, the treating provider’s opinion that the incident caused or materially contributed to the injury carries substantial weight. Courts and juries give particular credence to contemporaneous observations by providers who examined the patient, rather than opinions formed solely from later chart review.
Pre-existing conditions do not automatically defeat causation. Aggravation of a previously asymptomatic or minimally symptomatic degenerative spine is compensable when the incident produces new or substantially increased symptoms and functional loss. Documenting the pre-incident baseline—through history, prior records when available, and a clear temporal correlation with worsening—supports the aggravation theory. Gaps in treatment, non-compliance, or inconsistent histories undermine credibility; conversely, consistent, objective, and progressive documentation strengthens it.
What Chiropractic Care Is and How It Supplies Causation Insight in Personal Injury
Chiropractic care is a licensed healthcare profession focused on diagnosing, treating, and preventing disorders of the neuromusculoskeletal system, with particular attention to the spine and extremities. Doctors of Chiropractic complete rigorous graduate education emphasizing anatomy, biomechanics, neurology, and manual therapy. In contemporary, evidence-based practice, the emphasis is on restoring normal joint motion, reducing abnormal mechanical stress and afferent input, modulating pain signaling, and facilitating the body’s capacity for recovery. High-velocity, low-amplitude adjustments and graded mobilizations are core techniques, often combined with soft-tissue methods, rehabilitative exercise, and patient education.
Modern chiropractic practice is grounded in biomechanics and neurophysiology rather than outdated systemic theories. Clinical practice guidelines from multiple organizations support spinal manipulative therapy as part of multimodal care for acute, subacute, and chronic low back pain, neck pain, and certain headache presentations. Systematic reviews and randomized trials demonstrate reductions in pain intensity and disability when chiropractic care is integrated with exercise and education. In the personal injury context, chiropractic care is frequently the patient’s earliest and most continuous contact after trauma. Early evaluation identifies red flags requiring imaging or medical referral, establishes objective baselines, and initiates conservative management while the inflammatory phase remains active.
Chiropractic care and causation proof reinforce each other. The initial examination captures the mechanism in the patient’s words and correlates it with clinical findings—for example, restricted cervical rotation and positive orthopedic tests after a rear-end impact. Serial measurements of range of motion, muscle strength, and functional capacity create a clear timeline. Objective data improve in parallel with expected tissue-healing phases, supporting the conclusion that the trauma produced a treatable injury. Documenting the absence of prior similar symptoms, or the clear aggravation of pre-existing conditions, is essential when the defense argues natural progression of degenerative change. The treating chiropractor’s ongoing relationship provides continuity that a single independent examination cannot. When the same provider observes both the acute presentation and the response to care, the causation opinion rests on direct observation. Consistency across chiropractic and medical notes within an integrated clinic further strengthens the record.
Physiological Underpinnings of Chiropractic Care for Musculoskeletal Injuries
Trauma disrupts joint mechanics and generates continuous abnormal input from mechanoreceptors and nociceptors. This input facilitates segmental spinal cord neurons, expands pain receptive fields, and maintains protective muscle co-contraction that further restricts motion. High-velocity, low-amplitude manipulation produces a brief, high-frequency burst of discharge from muscle spindle primary afferents and other dynamically sensitive receptors. Animal and human studies show that this afferent volley can reduce the excitability of dorsal horn neurons involved in pain transmission and modulate descending inhibitory pathways originating in the brainstem and higher centers. Segmental effects include attenuation of dorsal-horn neuron hyperexcitability; heterosegmental and supraspinal effects involve the periaqueductal gray and cortical networks that process pain and motor control.
Beyond neural effects, restoring joint motion improves local circulation and reduces concentrations of inflammatory mediators in peri-articular tissues. When synovial fluid redistributes and capsular tension normalizes, the chemical environment that sustains peripheral sensitization improves. Soft-tissue techniques address myofascial trigger points and adhesions that develop from muscle guarding. Together, these changes reduce the mechanical and chemical drivers of pain, allowing patients to resume more normal movement patterns that further promote healing.
Recent pragmatic randomized controlled trials have examined biomarker changes after chiropractic spinal adjustments. One 2025 study reported that 12 weeks of care was associated with increased blood brain-derived neurotrophic factor and interleukin-6 levels and decreased tumor necrosis factor-alpha, supporting modulation of neuroplasticity and inflammation. Other work has shown reductions in pro-inflammatory cytokines and increases in anti-inflammatory interleukin-10 following spinal manipulation in models of neuropathic and postoperative pain. These findings align with clinical observations that patients experience not only local pain reduction but also improvements in sleep, mood, and overall function—outcomes consistent with central nervous system modulation.
For disc-related injuries, controlled distraction or flexion-distraction techniques can reduce intradiscal pressure and may improve nutrient diffusion into the avascular disc. Combined with core stabilization exercise, this strategy restores load-sharing among the spine’s passive (ligaments and discs), active (muscles), and neural control subsystems. Patients who regain segmental motion early and then progress through graded loading recover function more reliably than those who remain immobilized or rely solely on passive modalities.
How Chiropractic Care Reduces Musculoskeletal Injuries and Their Comorbidities
Musculoskeletal injuries from trauma commonly initiate a cascade of secondary problems. Restricted motion leads to muscle atrophy and altered recruitment patterns. Persistent nociceptive input can contribute to central sensitization, sleep fragmentation, and reduced physical activity. Reduced activity then worsens cardiovascular fitness, glycemic control, and mood. Chiropractic care interrupts this cascade at several points by restoring motion, decreasing abnormal afferent drive, and enabling earlier graded activity.
Randomized trials show that adding chiropractic care to usual medical management improves low-back-pain intensity and disability, increases patient satisfaction, and reduces self-reported pain-medication use. Observational studies of older adults and Medicare beneficiaries with chronic low back pain and multiple comorbidities have found lower overall costs and lower rates of subsequent surgery among those who received chiropractic manipulative treatment. Systematic reviews support spinal manipulative therapy as part of multimodal care for neck pain and cervicogenic headache. Meta-analyses indicate that receipt of chiropractic care is associated with substantially lower odds of receiving prescription opioids, with greater reductions when care begins early.
In personal injury populations, frequently observed comorbidities include compensatory shoulder or hip strain from altered gait or posture, tension-type or cervicogenic headache secondary to upper cervical dysfunction, and sleep disruption that prolongs recovery. By restoring cervical and lumbar motion, reducing muscle hypertonicity, and enabling earlier return to graded activity, chiropractic care decreases the likelihood that these secondary problems become entrenched. Patients who recover segmental mobility and core endurance report better tolerance for work and daily activities, which supports mental health and reduces the risk of prolonged opioid exposure. Recent cohort data further associate initial spinal manipulative therapy for low back pain with markedly lower rates of subsequent opioid use disorder diagnosis compared with initial ibuprofen.
Integrative Chiropractic Care Within Non-Surgical Treatment Models
Non-surgical management of traumatic musculoskeletal injury is most effective when mechanical, neurological, and systemic factors are addressed together. Integrative chiropractic care combines joint mobilization or manipulation with rehabilitative exercise, soft-tissue therapy, nutritional support for tissue repair, and, when indicated, regenerative options such as platelet-rich plasma under appropriate medical direction. The reasoning is straightforward: restoring motion reduces abnormal loading and afferent drive, while progressive loading stimulates collagen remodeling and motor-pattern retraining. Functional medicine evaluation can identify co-factors—such as vitamin D insufficiency, sleep disruption, or inflammatory dietary patterns—that slow healing even when local mechanics are improved.
At Injury Medical Clinic PA in El Paso, Texas, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, and Dr. Maria Guadalupe Cardenas, MD, bring this model to life through collaboration. Dr. Cardenas, board-certified in Internal Medicine with more than 40 years of experience as an internist (NPI #1164426749, Texas MD License #J2933), serves as Medical Director and Collaborative Physician. This multidisciplinary arrangement is common in integrative injury-care clinics: the physician provides medical direction, orders or interprets advanced diagnostics when needed, manages systemic conditions or medication requirements, and ensures that care remains within appropriate medical standards, while the chiropractor focuses on biomechanical restoration, soft-tissue recovery, and functional rehabilitation. The team integrates chiropractic adjustments and mobilizations, nurse-practitioner-level evaluation, functional medicine assessment, targeted rehabilitation protocols, nutritional optimization, soft-tissue techniques, spinal decompression, and, when appropriate, consultations for regenerative therapies. Documentation remains coordinated so that clinical findings, treatment responses, and medical oversight appear in a consistent record that supports both recovery and causation analysis.
Clinical Observations from Dr. Alexander Jimenez and the Injury Medical Clinic Team
Over more than three decades of practice in El Paso, clinical observations at Injury Medical Clinic PA have repeatedly shown that early restoration of segmental motion, combined with progressive loading and attention to systemic factors, produces more reliable functional recovery than prolonged passive care or immediate reliance on pharmaceuticals alone. Patients presenting after motor vehicle collisions frequently exhibit restricted cervical or lumbar ranges of motion, positive orthopedic tests consistent with soft-tissue strain or facet irritation, and compensatory postural shifts. Serial goniometric measurements and functional outcome tools document progressive improvement that aligns with the phases of tissue healing. When Dr. Cardenas’s medical oversight addresses concurrent internal-medicine issues—such as hypertension, diabetes, or inflammatory markers that may delay recovery—the overall trajectory improves.
These observations align with published evidence on biomechanical mechanisms of whiplash and soft-tissue injury. Rear-impact collisions produce characteristic S-shaped cervical kinematics with lower-segment extension and upper-segment flexion, loading facet capsules, annular fibers, and supporting ligaments beyond normal physiologic strains in a substantial fraction of cases. Early chiropractic intervention that restores motion and reduces protective muscle guarding interrupts the cycle of ongoing abnormal loading and afferent input. Patients who progress from passive modalities to active stabilization and graded activity report better return-to-work outcomes and fewer secondary complaints. Documenting the mechanism, baseline findings, and serial improvement provides the temporal and clinical consistency attorneys require to establish causation to a reasonable degree of medical probability.
How the Integrative Team Supports Personal Injury Insight and Durable Recovery
The combination of chiropractic expertise and internal-medicine oversight produces records that address both clinical recovery and legal requirements. Objective measurements, treatment responses, and correlated medical findings create a coherent narrative. When alternative causes are considered and found less probable, and when improvement follows expected healing timelines under coordinated care, the resulting expert opinions carry weight. Attorneys benefit from providers who understand the distinction between clinical consistency and the legal standard of reasonable medical probability, document thoroughly from the first visit, and coordinate across disciplines to keep the record internally consistent.
Non-surgical integrative care further reduces the likelihood of escalation to invasive procedures when conservative measures succeed. By addressing biomechanics, inflammation, motor control, and systemic co-factors simultaneously, the approach supports durable function while generating the contemporaneous evidence that justifies causation in the courtroom. Patients recover mobility and reduce pain; the documentation simultaneously strengthens the causal link between the incident and the injuries.
Conclusion
Causation remains the essential requirement that links traumatic events to compensable musculoskeletal injuries in the courtroom. Its justification rests on fairness, scientific reliability, and the need for opinions grounded in reliable methodology and contemporaneous clinical observation. Modern, evidence-based chiropractic care provides this insight by documenting mechanism, objective findings, and recovery trajectories while reducing pain, restoring motion, modulating inflammation and neural signaling, and interrupting the cascade toward comorbidities such as central sensitization, compensatory strain, and opioid reliance. When paired with medical oversight from a board-certified internist such as Dr. Maria Guadalupe Cardenas at Injury Medical Clinic PA, the model delivers durable non-surgical recovery and the coordinated documentation attorneys require. Drawing on the latest research in biomechanics, neurophysiology, and clinical outcomes, this approach offers a clear, evidence-informed pathway from injury event through functional restoration to courtroom-ready causation support.
References
American Medical Association. (n.d.). Maria Guadalupe Cardenas, MD. AMA Find a Doctor. https://find-doctor.ama-assn.org/doctor/maria-guadalupe-cardenas-md/13591899
Basques, B. A., et al. (2025). Chiropractic care and spinal manipulation: Evidence, risks, and referral considerations for spine surgeons. JBJS Reviews, 13(12), e25.00196. https://doi.org/10.2106/JBJS.RVW.25.00196
Bronfort, G., Meier, E. N., Leininger, B., et al. (2025). Spinal manipulation and clinician-supported biopsychosocial self-management for acute back pain: The PACBACK randomized clinical trial. JAMA. Advance online publication. https://doi.org/10.1001/jama.2025.21990
Gevers-Montoro, C., Provencher, B., Descarreaux, M., Ortega de Mues, A., & Piché, M. (2021). Neurophysiological mechanisms of chiropractic spinal manipulation for spine pain. European Journal of Pain, 25(7), 1429–1448. https://doi.org/10.1002/ejp.1773
Jimenez, A. D. (2026). Causation and chiropractic care: Addressing pain and mobility. El Paso Back Clinic. https://elpasobackclinic.com/causation-and-chiropractic-care-addressing-pain-and-mobility/
Lisi, A. J., et al. (2025). The impact of chiropractic care on opioid prescriptions in Veterans Health Administration patients receiving low back pain care. Journal of General Internal Medicine. Advance online publication.
Song, X. J., et al. (2016). Attenuation effect of spinal manipulation on neuropathic and postoperative pain through activating endogenous anti-inflammatory cytokine interleukin 10 in rat spinal cord. Journal of Manipulative and Physiological Therapeutics, 39(1), 42–53. https://doi.org/10.1016/j.jmpt.2015.12.004
Trager, R. J., et al. (2025). Association between spinal manipulative therapy for low back pain with or without sciatica and opioid use disorder: A retrospective cohort study. Health Science Reports, 8, e71267.
Virginia Lawyers Weekly. (2025, November 4). Chiropractor can testify on causation of man’s injuries. https://valawyersweekly.com/2025/11/04/virginia-chiropractor-expert-testimony-new-trial/
SEO Tags
causation in personal injury, chiropractic care for musculoskeletal injuries, evidence-based chiropractic personal injury, integrative non-surgical treatment El Paso, Dr Alexander Jimenez DC APRN, Dr Maria Guadalupe Cardenas MD, Injury Medical Clinic PA, Bradford Hill criteria musculoskeletal, spinal manipulation inflammation biomarkers, opioid reduction chiropractic, whiplash biomechanics, expert testimony chiropractor causation, functional medicine injury recovery, non-surgical rehabilitation trauma, El Paso chiropractic, personal injury documentation

by Dr Alex Jimenez DC, APRN, FNP-BC, CFMP, IFMCP | Auto Accident Injuries, Collision & Injury Dynamics, Med-Legal Corner, Personal Injury, Spinal Decompression Treatments
Annular Tear and Disc Height Loss After Loop 375 Lateral Impact: Mechanism-to-MRI Linkage
A high-speed side impact on El Paso’s Loop 375 can transmit focused lateral shear, axial compression, and rotational forces through the lumbar or cervical spine in a fraction of a second. When those force vectors exceed the tensile strength of the annulus fibrosus—particularly its relatively weaker posterolateral fibers—an acute annular tear can form, allowing nuclear material to migrate and producing measurable disc height loss visible on MRI. At Injury Medical Clinic PA in El Paso, the multidisciplinary team of Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP (Texas License #1191402, Prescriptive Authority #59628, NPI 1205907805) and Medical Director Dr. Maria Guadalupe Cardenas, MD (Board Certified Internal Medicine, Texas License #J2933, NPI 1164426748), systematically links these biomechanical mechanisms to objective imaging so that clinical and proximate causation are clear for patients and attorneys.
How a Loop 375 Lateral Impact Generates Disc Injury
Loop 375 (Joe Battle Boulevard and related segments) is a high-volume corridor where lane changes, side-swipes, and T-bone or angle collisions are common. In a pure lateral impact, the striking vehicle imparts a force vector roughly perpendicular to the struck vehicle’s longitudinal axis. Occupants experience rapid lateral torso acceleration while the pelvis and lower extremities lag or rotate, creating shear across the intervertebral discs and facet joints. At the same time, the sudden change in velocity produces axial compression and, often, a twisting moment as the body rebounds against the seatbelt or door.
The annulus fibrosus consists of concentric lamellae whose fiber orientation alternates for strength; however, the posterolateral region contains a higher proportion of vertically oriented fibers and is a known site of relative weakness (StatPearls, 2023). When lateral shear and rotation are superimposed on compression, these fibers can separate, producing a radial or transverse annular tear. Nuclear material may then extrude or lose hydration and volume, resulting in a measurable reduction in disc height at the affected level. Because the forces are asymmetric, the tear and height loss are often unilateral or more pronounced on the side of impact—an important morphologic clue when compared with the more uniform, multilevel pattern of ordinary age-related degeneration.
MRI Linkage: Reading the Images Through the Force Vectors
On T2-weighted MRI, an acute annular tear typically appears as a high-intensity zone (HIZ)—a focal bright signal within the normally dark annulus caused by increased water content and inflammatory fluid (StatPearls, 2023; Teraguchi et al., 2022). Supporting signs of acute traumatic change, as opposed to a chronic degenerative baseline, include:
- A single or dominant level of abnormality that matches the predicted biomechanics of the impact (for example, L4-L5 or L5-S1 after a low lumbar lateral load, or mid-cervical levels after a higher side-impact).
- Asymmetric height loss or annular signal that is greater on the side of the force vector.
- Associated soft-tissue findings such as ligamentous edema, facet fluid, or paraspinal muscle signal change at the same or adjacent levels.
- Higher T2 hyperintensity and involvement of the outer third of the annulus are more consistent with traumatic disruption than the lower-intensity, inner-two-thirds fissures typical of slow degenerative breakdown (Khurana et al., 2025).
Degenerative disc disease is extremely common and increases with age; imaging studies of asymptomatic volunteers show annular fissures in roughly 19–29% of adults depending on the decade (Brinjikji et al., as cited in clinical radiology reviews). The clinic therefore never equates the mere presence of an HIZ or reduced disc height with trauma. Instead, the team correlates the precise morphology, laterality, and associated acute soft-tissue changes with the documented mechanism, the patient’s immediate post-collision symptoms, and serial clinical examinations. When pre-existing degeneration is present, the records explicitly separate the baseline findings from the new traumatic aggravation—language that prevents defense arguments that “the MRI only shows wear and tear.”
Distinguishing Acute Traumatic Change from Degenerative Baseline
Clear, plain-language documentation is essential. An example of phrasing used in clinic notes and narrative reports reads: “The left posterolateral L4-L5 annular high-intensity zone and 2 mm asymmetric disc-height reduction are morphologically and temporally consistent with the lateral shear and rotational forces of the 14 July Loop 375 side-impact collision. These findings differ from the mild, symmetric multilevel disc desiccation and small inner annular fissures that represent age-related baseline change.” Such statements rest on the mechanism-to-MRI linkage rather than on the radiologist’s impression alone. Digital imaging, functional testing (range-of-motion, neurologic, and strength measures), and Colossus-compliant electronic records further corroborate that the structural changes produce the patient’s objective functional deficits.
Future-Care Modeling with ESWT and Non-Surgical Decompression
Once causation is established, the clinic models evidence-based future care to address both the annular tear and height loss. Non-surgical spinal decompression creates controlled negative intradiscal pressure that can increase disc height and reduce pain; one retrospective cohort demonstrated a statistically significant correlation between restored disc height and decreased low-back pain scores (Apfel et al., 2010). Additional studies confirm improvements in radicular pain and disc morphology after motorized decompression protocols (Choi et al., 2022; Egyptian Rheumatology and Rehabilitation, 2019).
Extracorporeal shock-wave therapy (ESWT) supplies a complementary biologic stimulus. In laboratory models, low-energy ESWT combined with low-tension traction has been shown to restore disc height, improve rehydration, and reduce matrix-degrading enzymes (MMP-3, MMP-13, ADAMTS-4), thereby reshaping the microenvironment for repair (Spine Journal, 2021). Clinical series report pain reduction and facilitation of herniation resorption when ESWT is integrated into staged conservative care (Orthopedic Reviews, 2026; Rehabilitation Medicine, 2024). Because both modalities are non-invasive and drug-free, they align with non-maleficence: they lower the risk of progression to surgery or long-term opioid dependence while still delivering measurable structural and symptomatic benefit.
Unlocking Pain Relief: How We Assess Motion to Alleviate Pain | El Paso, TX
In the future-care cost spreadsheet these interventions appear as a defined course of decompression sessions (typically 20–30 over 6–8 weeks) plus a series of ESWT treatments, accompanied by supportive chiropractic adjustments, neurofunctional acupuncture or electroacupuncture, and functional-medicine laboratory monitoring directed by Dr. Cardenas. The combination targets root-cause healing—restoring disc height and annular integrity where possible, reducing inflammatory cytokines, and improving segmental stability—rather than merely masking pain (beneficence). Patients receive clear education about expected timelines, self-care strategies, and how the plan coordinates with any outside specialists they already see, preserving autonomy and informed decision-making.
Documentation That Withstands Scrutiny
Every element—mechanism narrative, MRI description distinguishing acute from baseline change, functional deficits, and itemized future-care costs—is recorded in a manner suitable for letters of protection and deposition. The dual-licensed perspective of Dr. Jimenez (structural alignment plus advanced practice medical diagnostics), together with Dr. Cardenas’s internal-medicine oversight, supplies both the biomechanical and medical foundation attorneys require. The result is a transparent, mechanism-linked record that supports the patient’s recovery while meeting El Paso personal-injury litigation evidentiary standards.
Patients and counsel seeking this level of integrated causation analysis and future-care planning may contact Injury Medical Clinic PA for a coordinated evaluation.
References
Apfel, C. C., Cakmakkaya, O. S., Martin, W., Richmond, C., Macario, A., George, E., Schaefer, M., & Pergolizzi, J. V. (2010). Restoration of disk height through non-surgical spinal decompression is associated with decreased discogenic low back pain: A retrospective cohort study. BMC Musculoskeletal Disorders, 11, Article 155. https://doi.org/10.1186/1471-2474-11-155
Choi, E., Gil, H. Y., Ju, J., Han, W. K., Nahm, F. S., & Lee, P. B. (2022). Effect of nonsurgical spinal decompression on intensity of pain and herniated disc volume in subacute lumbar herniated disc. International Journal of Clinical Practice, 2022, Article 6343837. https://doi.org/10.1155/2022/6343837
Khurana, B., Khorasani, M., & et al. (2025). Lumbar disc annular tear versus annular fissure: Distinguishing traumatic from degenerative findings on MRI. [PDF]. https://img1.wsimg.com/blobby/go/b1a39d28-bc5a-416f-9f65-e6d871130b13/downloads/f8cc02aa-ed0e-4623-a8fc-400307687027/Khurana%20et%20al%2C%2C%202025%20-%20Lumbar%20disc%20annular%20tea.pdf
National Center for Biotechnology Information. (2023). Annular disc tear. In StatPearls. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK459235/
Orthopedic Reviews. (2026). Spontaneous resorption of prolapsed lumbar disc herniation facilitated by extracorporeal shock wave therapy: A case report. Orthopedic Reviews, 17(1). https://orthopedicreviews.openmedicalpublishing.org/article/172374-spontaneous-resorption-of-prolapsed-lumbar-disc-herniation-facilitated-by-extracorporeal-shock-wave-therapy-a-case-report
Rehabilitation Medicine. (2024). Effect of extracorporeal shock wave therapy on different types of lumbar disc herniation. Rehabilitation Medicine, 34(1), 84–89.
Spine Journal. (2021). Low energy extracorporeal shock wave therapy combined with low tension traction can better reshape the microenvironment in degenerated intervertebral disc regeneration and repair. The Spine Journal, 21(1), 160–177. https://doi.org/10.1016/j.spinee.2020.08.012
Teraguchi, M., Cheung, J. P. Y., & Samartzis, D. (2022). High-intensity zones and annular tears. In Spine phenotypes (pp. 187–201). Academic Press. https://doi.org/10.1016/B978-0-12-822778-7.00016-X
El-Sayed, A. M., et al. (2019). Spinal decompression therapy as an alternative modality for management of low back pain and radicular pain caused by lumbar disc herniation or protrusion. Egyptian Rheumatology and Rehabilitation, 46, 161–168. https://doi.org/10.4103/err.err_34_18
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. https://doi.org/10.3174/ajnr.A4173










