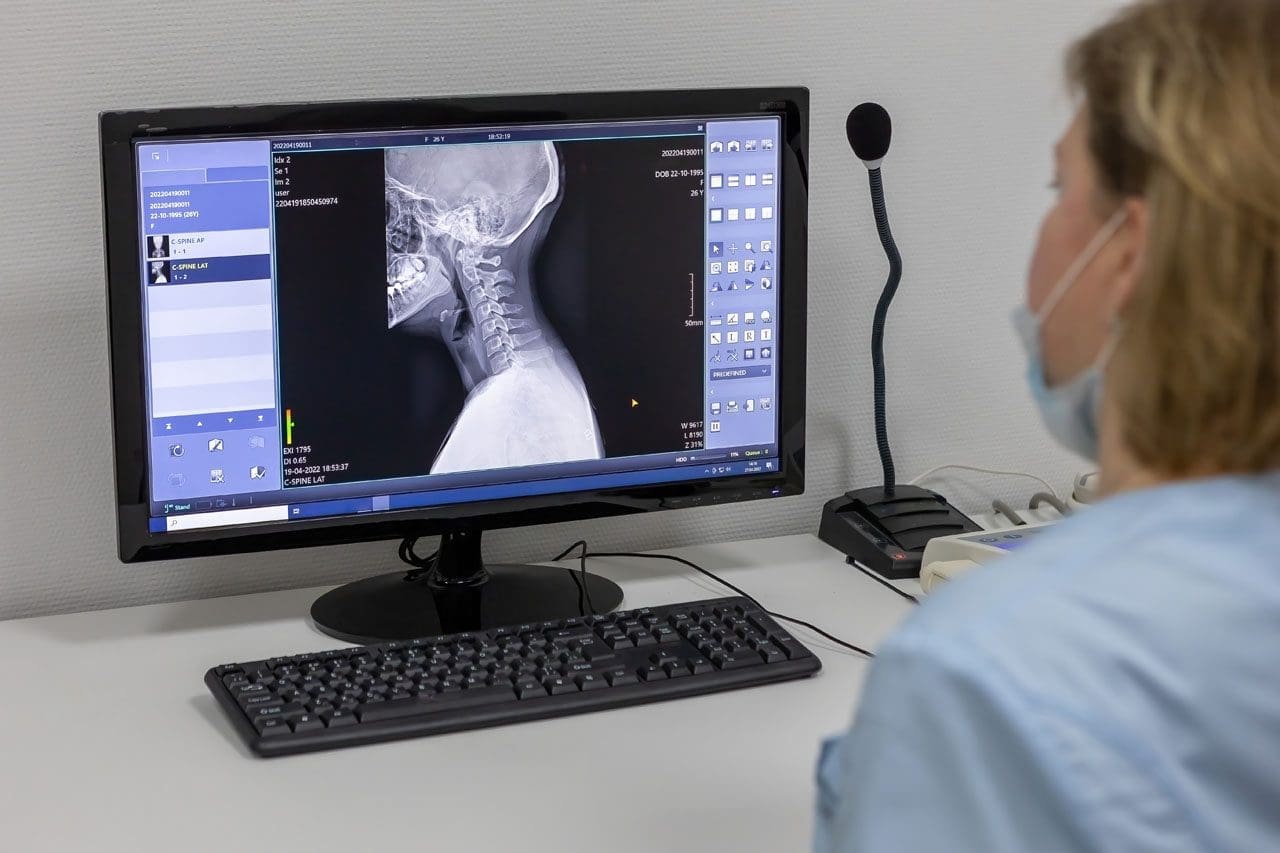
Back Clinic Treatments. There are various treatments for all types of injuries and conditions here at Injury Medical & Chiropractic Clinic. The main goal is to correct any misalignments in the spine through manual manipulation and placing misaligned vertebrae back in their proper place. Patients will be given a series of treatments, which are based on the diagnosis. This can include spinal manipulation, as well as other supportive treatments. And as chiropractic treatment has developed, so have its methods and techniques.
Why do chiropractors use one method/technique over another?
A common method of spinal adjustment is the toggle drop method. With this method, a chiropractor crosses their hands and pressed down firmly on an area of the spine. They will then adjust the area with a quick and precise thrust. This method has been used for years and is often used to help increase a patient’s mobility.
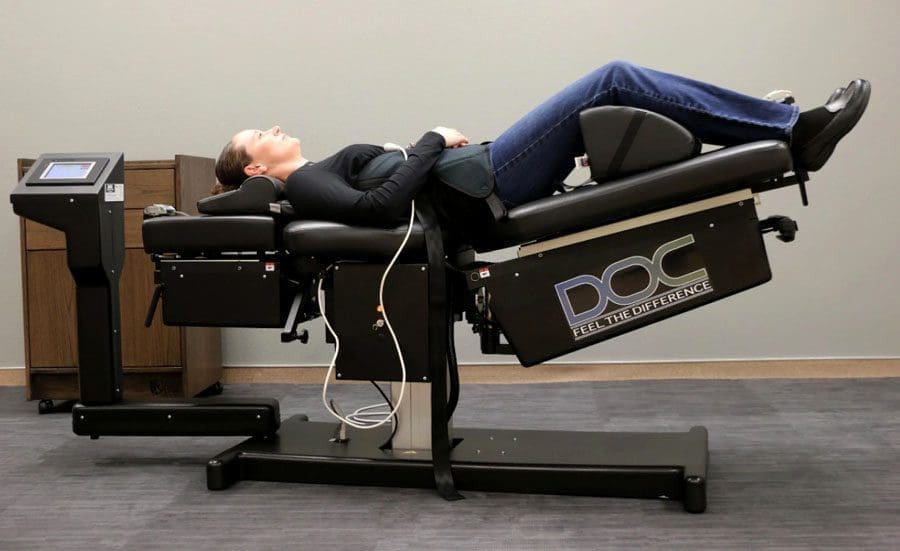
Another popular method takes place on a special drop table. The table has different sections, which can be moved up or down based on the body’s position. Patients lie face down on their back or side while the chiropractor applies quick thrusts throughout the spinal area as the table section drops. Many prefer this table adjustment, as this method is lighter and does not include twisting motions used in other methods.
Chiropractors also use specialized tools to assist in their adjustments, i.e., the activator. A chiropractor uses this spring-loaded tool to perform the adjustment/s instead of their hands. Many consider the activator method to be the most gentle of all.
Whichever adjustment method a chiropractor uses, they all offer great benefits to the spine and overall health and wellness. If there is a certain method that is preferred, talk to a chiropractor about it. If they do not perform a certain technique, they may recommend a colleague that does.
When Sub-Occipital Pain Reflects Cervicogenic Headache — and How Structural Care Fits the Integrated Plan
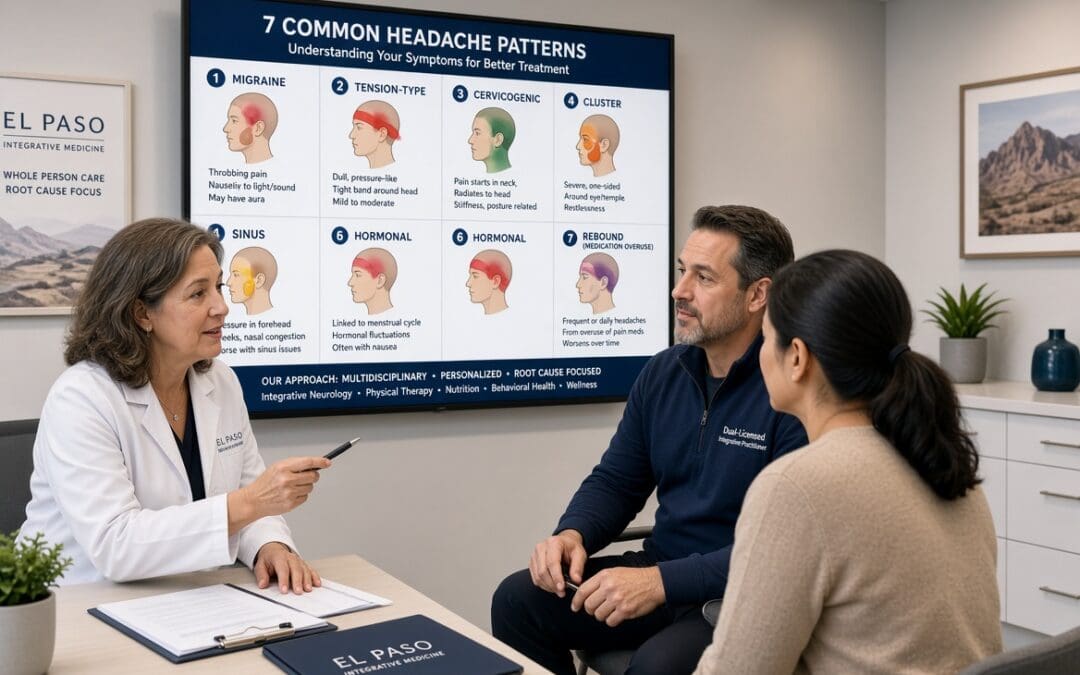
Pain that begins at the base of the skull and intensifies when you turn your head, look up, or sit at a desk for hours often feels like a simple “tension headache.” In many cases, however, that sub-occipital discomfort is a cervicogenic headache—pain referred from the upper cervical joints, ligaments, or soft tissues. Understanding this location-to-diagnosis connection helps patients and their care teams choose targeted structural care that complements, rather than competes with, medical evaluation.
What Is Cervicogenic Headache?
Cervicogenic headache is a secondary headache. The International Classification of Headache Disorders (ICHD-3) requires clinical or imaging evidence of a cervical source plus a demonstrable link—such as pain reproduced by neck movement or palpation, restricted cervical range of motion, or improvement when the cervical problem improves (International Headache Society, 2018).
Typical features include:
Unilateral pain that starts in the occiput or upper neck and may spread toward the temple or forehead
Worsening with sustained postures or awkward head positions
Ipsilateral neck, shoulder, or arm discomfort
Frequent involvement of the C2–C3 zygapophyseal (facet) joint and the suboccipital muscle group (rectus capitis posterior major and minor, obliquus capitis superior and inferior)
These structures generate pain because their sensory input converges with trigeminal afferents in the trigeminocervical complex (Bogduk & Govind, 2009).
How Patients Typically Describe the Pain
Patients commonly describe the sensation as a deep, non-throbbing ache that builds with computer work, driving, or looking down at a phone. Sudden neck movements—sneezing, turning quickly in traffic, or rising from a pillow—can trigger it.
These mechanical clues help clinicians distinguish cervicogenic headache from other conditions:
Primary migraine — more often features throbbing pain, nausea, and light or sound sensitivity
Occipital neuralgia — typically produces sharp, shooting, or electric-like pain along the greater or lesser occipital nerve with scalp tenderness
Overlap is possible, especially after trauma, so careful assessment matters.
Evaluation at the Clinic
At Injury Medical Clinic PA in El Paso, evaluation of suspected cervicogenic headache begins with safety screening. Red-flag symptoms—sudden severe onset, progressive neurological deficits, fever, unexplained weight loss, or history of cancer—prompt urgent medical referral.
Once serious pathology is ruled out, the dual-licensure team examines:
Upper cervical joint mobility
Digital range of motion
Posture and soft-tissue tenderness
Provocative maneuvers that reproduce the patient’s familiar headache
Objective findings are documented alongside any concurrent migraine features so that structural care and medical management remain coordinated.
How Structural Care Helps
Structural care focuses on restoring motion and reducing mechanical load. High-velocity, low-amplitude spinal manipulation of the upper cervical and upper thoracic regions has moderate evidence for reducing headache frequency, intensity, and disability in cervicogenic headache (Nilsson et al., as reviewed in the clinic’s chiropractic headache guidelines).
Additional approaches include:
Joint mobilization
Soft-tissue techniques directed at the suboccipitals and upper trapezius
Deep-neck-flexor endurance exercises
Patients typically notice:
Improved ability to turn the head
Reduced “band-like” pressure at the skull base
Better sleep
Fewer posture-triggered flares
These gains often appear within a few weeks with consistent care.
Bioethical Principles Guiding Care
Bioethical principles guide every step.
Beneficence — targeting the specific joints and soft tissues that generate the pain so relief is mechanical rather than merely masking symptoms
Non-maleficence — screening first and preferring non-invasive, drug-free options (chiropractic adjustment, mobilization, and therapeutic exercise) before considering injections or prolonged medication
Autonomy — helping patients understand the location-to-diagnosis link: which movements provoke symptoms, how posture contributes, and how the structural plan fits alongside any medical care they already receive
Shared records and clear explanations let patients remain the informed decision-makers.
What Makes This Clinic Unique
What makes Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic unique is its fully integrated model. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, serves as Medical Director and Collaborative Physician, providing medical oversight, risk stratification, and coordination of any necessary laboratory or internal-medicine evaluation. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, brings dual licensure as both a Doctor of Chiropractic and a board-certified Family Practice Nurse Practitioner specializing in soft-tissue injury, spinal biomechanics, and functional rehabilitation. This combination allows seamless co-documentation of structural findings and medical context in one facility. It is one of the only clinics in El Paso, TX, that provides this dual-scope structural and medical care under one roof for patients whose sub-occipital pain may reflect cervicogenic headache.
Integrated structural documentation appears in the clinical framework at https://dralexjimenez.com. Related resources include the clinic’s reviews of spinal manipulation versus mobilization for cervicogenic headache, chiropractic headache treatment guidelines, occipital neuralgia approaches, and the broader integrated migraine guide that clarifies when cervical findings coexist with primary migraine. These pages help patients and referring providers see how upper-cervical assessment supports both daily function and, when trauma is involved, clear medical-legal causation.
Key Takeaway
Pain that starts at the base of the skull and is provoked by neck movement or posture deserves a careful look at the upper cervical joints and soft tissues. When safety screening is complete and the diagnosis of cervicogenic headache is supported, targeted structural care—delivered within a dual-licensure, medically directed clinic—offers a practical path toward better mobility, fewer headache days, and informed patient partnership.
References
Bogduk, N., & Govind, J. (2009). Cervicogenic headache: An assessment of the evidence on clinical diagnosis, invasive tests, and treatment. The Lancet Neurology, 8(10), 959–968. https://doi.org/10.1016/S1474-4422(09)70209-1
International Headache Society. (2018). The International Classification of Headache Disorders (3rd ed.). Cephalalgia, 38(1), 1–211. https://doi.org/10.1177/0333102417738202
Nilsson, N., Christensen, H. W., & Hartvigsen, J. (1997). The effect of spinal manipulation in the treatment of cervicogenic headache. Journal of Manipulative and Physiological Therapeutics, 20(5), 326–330.
Discover how chiropractic rehabilitation for cluster headaches can provide relief and enhance your overall well-being with expert care.
Abstract
Cluster headaches represent one of the most severe forms of primary headache disorders, producing excruciating unilateral pain that profoundly disrupts neurological, autonomic, and circadian systems. This educational post explores the physiological mechanisms underlying these attacks, the full spectrum of symptoms, and the far-reaching effects on daily function, mental health, work, and relationships. It addresses the critical requirement of establishing medical and legal causation in personal injury courtroom cases involving post-traumatic or aggravated cluster headache phenotypes, emphasizing objective documentation, temporal linkage, and expert analysis. The discussion then examines chiropractic care as a non-surgical, evidence-informed intervention that targets upper cervical biomechanics, the trigeminocervical complex, and autonomic balance. Integrative approaches combining chiropractic adjustments, soft-tissue work, functional medicine, and rehabilitation are shown to reduce attack frequency, intensity, and associated comorbidities such as sleep disruption, anxiety, and cervical dysfunction. Clinical observations from practice illustrate how these methods provide insight into injury mechanisms and support recovery. Finally, the multidisciplinary model at Injury Medical Clinic PA in El Paso, Texas—where Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST collaborates with Medical Director and Collaborative Physician Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933)—demonstrates coordinated care that safely integrates medical oversight with chiropractic, functional, and rehabilitative strategies for sustainable wellness.
Understanding Cluster Headaches and Their Profound Effects on the Body
Cluster headaches are classified among the trigeminal autonomic cephalalgias. They produce attacks of severe or very severe unilateral orbital, supraorbital, or temporal pain lasting 15 to 180 minutes when untreated, occurring from once every other day to eight times daily, and accompanied by ipsilateral cranial autonomic features or restlessness (Headache Classification Committee of the International Headache Society, 2018).
The hypothalamus plays a central role. Neuroimaging and clinical patterns show activation in the posterior hypothalamic gray matter during attacks. This region regulates the body’s biological clock, explaining the characteristic circadian timing—attacks often begin one to two hours after sleep onset—and circannual clustering (Mayo Clinic, 2025; Schindler & Burish, 2022). Hypothalamic dysfunction is thought to lower the threshold for trigeminal activation, allowing peripheral or environmental triggers to precipitate attacks during active bouts.
The trigeminovascular system becomes activated. Sensory neurons of the first division of the trigeminal nerve release neuropeptides, including calcitonin gene-related peptide (CGRP), substance P, and others, around cranial vessels and dura. Researchers have measured elevated CGRP levels in jugular venous blood during attacks, and intravenous CGRP infusion reliably provokes typical attacks in patients during an active episodic bout or with chronic cluster headache, but not during remission (Vollesen et al., 2018). This peripheral activation feeds into central pathways, amplifying pain perception.
Simultaneously, the trigeminal-autonomic reflex engages. Signals reach the superior salivatory nucleus, producing ipsilateral parasympathetic outflow that accounts for tearing, nasal congestion or rhinorrhea, eyelid edema, and conjunctival injection. Partial sympathetic impairment contributes to miosis and ptosis (partial Horner syndrome). The result is a tightly lateralized, dramatic autonomic picture that distinguishes cluster headache from most other headache types.
Vascular changes occur secondarily. Vasodilation follows neuropeptide release rather than initiating the attack. Central disinhibition of nociceptive and autonomic pathways, combined with genetic susceptibility (reported in a minority of cases) and lifestyle factors such as smoking, completes the current pathophysiological model (Frontiers in Neurology, 2024; Osmosis, 2026).
Comorbidities arise from these same systems. Repeated nocturnal attacks fragment sleep architecture, elevate sympathetic tone, and contribute to anxiety, depression, and, in some patients, suicidal ideation during bouts—the condition has long been called the “suicide headache.” Cervical somatic dysfunction frequently coexists, whether primary or secondary, because C1–C3 afferents converge densely with trigeminal second-order neurons in the trigeminocervical complex. Mechanical irritation or inflammation in the upper cervical joints, suboccipital muscles, or dura can lower the threshold for central sensitization and referred craniofacial pain.
Recognizing the Diverse Symptoms of Cluster Headaches
Attacks begin abruptly, often reaching peak intensity within five to ten minutes. Patients describe the pain as sharp, stabbing, drilling, or burning, localized behind or around one eye, and sometimes radiating to the temple, forehead, cheek, jaw, or neck. Side-locked laterality is typical within a bout, although side-shift between bouts can occur.
Ipsilateral autonomic signs are nearly universal:
Conjunctival injection and/or lacrimation (present in approximately 84–91 percent of patients)
Nasal congestion and/or rhinorrhea
Eyelid edema
Forehead and facial sweating or flushing
Miosis and/or ptosis
Sensation of fullness in the ear (recognized in alternative criteria)
Restlessness or agitation is a diagnostic criterion. Unlike migraine, in which patients prefer to lie still in a dark room, individuals with cluster headache pace, rock, or cannot remain seated (AAFP, 2022; StatPearls, 2023).
Circadian and circannual patterns are striking. Most attacks occur at night. Cluster periods (bouts) last weeks to months, followed by remissions of three months or longer in the episodic form. The chronic form persists for a year or more with remissions shorter than three months (ICHD-3 criteria). Common triggers during a bout include alcohol, nitrates, strong odors, heat, and, in some reports, trauma.
Pre-episode symptoms (prodromes) may include mild head or facial discomfort, restlessness, sleep disturbance, fatigue, or neck tightness in the days before a bout begins. After an attack, patients often feel exhausted yet pain-free until the next episode.
How Cluster Headaches Disrupt Day-to-Day Life and Affect the Individual
During an active bout, the functional impact is immediate and severe. Nighttime attacks repeatedly interrupt sleep, producing cumulative sleep debt, daytime fatigue, and impaired concentration. Work attendance and productivity decline; many patients miss days or reduce hours. Social and family roles suffer because the unpredictability and intensity of attacks lead to canceled plans, isolation, and fear of triggering an episode.
The psychological burden is substantial. Lifetime prevalence of depression is elevated compared with the general population. Anxiety about the next attack, the duration of the bout, and the possibility of chronification is common. Suicidal ideation occurs at higher rates than in the general population during severe bouts, although completed suicide remains rare (StatPearls, 2023; Frontiers in Neurology, 2024). Quality-of-life measures consistently show marked reductions in physical, emotional, and social domains.
Even between attacks within a bout, residual autonomic changes, mild background discomfort, or anticipatory anxiety can limit activity. In the chronic form, the near-continuous presence of attacks removes the restorative remissions that episodic patients eventually experience, amplifying disability.
Establishing Causation in Personal Injury Cases Involving Cluster Headaches
In a personal injury courtroom, the plaintiff must prove that the defendant’s negligence caused or materially contributed to the headache disorder or its aggravation. For cluster headache or a cluster phenotype of post-traumatic headache, causation analysis rests on both medical science and legal standards (typically “more likely than not” or material contribution).
The International Classification of Headache Disorders, 3rd edition, defines post-traumatic headache as one that develops within seven days of the trauma (or of regaining consciousness or of the ability to report pain). Delayed-onset variants are also recognized. When the phenotype meets full criteria for cluster headache and the temporal relationship is clear, the diagnosis of post-traumatic headache with cluster features can be made (Grangeon et al., 2020).
Key elements of justification include:
Detailed pre- and post-injury headache diaries documenting onset, frequency, intensity, duration, laterality, and autonomic features.
Medical records showing the absence of, or a different character of, headaches before the incident.
Imaging and examination findings that exclude other secondary causes and document concurrent cervical or soft-tissue injury.
Expert testimony linking the biomechanical forces of the trauma (for example, whiplash-type acceleration-deceleration) to upper cervical dysfunction capable of activating the trigeminocervical complex and lowering the threshold for hypothalamic or trigeminal dysregulation.
Application of accepted causation frameworks (Hill criteria adapted for clinical use, or methodologies taught in orthopedic and neurological forums) that evaluate temporality, strength of association, biological plausibility, consistency, and dose-response.
Subjective symptoms such as headache require this supportive documentation; pure subjective complaints without temporal linkage or objective correlates are vulnerable to challenge (as illustrated in various appellate decisions involving pre-existing conditions). The “eggshell plaintiff” doctrine protects recovery for aggravation of a pre-existing susceptibility when the trauma materially worsens the condition. Thorough, contemporaneous records from a coordinated medical-chiropractic team strengthen the causal chain.
What Is Chiropractic Care and How It Integrates with Non-Surgical Treatments
Chiropractic care is a licensed health discipline focused on diagnosing, treating, and preventing neuromusculoskeletal disorders, with particular emphasis on spinal biomechanics and the nervous system. Doctors of chiropractic perform spinal manipulative therapy (adjustments), mobilizations, soft-tissue techniques, therapeutic exercise, and patient education. The goal is to restore joint mobility, reduce nociceptive input, improve proprioceptive signaling, and support the body’s intrinsic healing capacity.
In the context of headache, upper cervical and upper thoracic adjustments are commonly employed. Anatomical continuity between the rectus capitis posterior minor muscle, the ligamentum nuchae, and the spinal dura provides a plausible pathway for upper cervical dysfunction to influence intracranial structures. More importantly, convergence of C1–C3 afferents with trigeminal afferents in the trigeminocervical nucleus explains referred pain and the potential for cervical interventions to modulate craniofacial pain processing (Bogduk and others; multiple systematic reviews on cervicogenic headache).
Integrative chiropractic care fits naturally within non-surgical treatment pathways. It is combined with medical management (oxygen, triptans, transitional corticosteroids, verapamil, galcanezumab, or other CGRP-targeted agents when appropriate), physical rehabilitation, lifestyle modification, and functional-medicine strategies that address sleep, inflammation, and autonomic balance. The approach is individualized, evidence-informed, and coordinated under medical direction when complex comorbidities or pharmacologic needs exist.
How Chiropractic Care Reduces Cluster Headaches and Associated Comorbidities
While large randomized trials specific to primary cluster headache remain limited, mechanistic rationale and supportive clinical observations exist. Manual therapy and exercise programs have reduced attack frequency in small case series of patients with cluster headache who continued standard pharmacologic care (de-la-Puente-Ranea et al., 2021). Systematic reviews of spinal manipulative therapy for cervicogenic and tension-type headache, and selected migraine trials, demonstrate reductions in headache days, intensity, and disability, particularly when upper cervical and thoracic segments are addressed.
Proposed mechanisms include:
Restoration of upper cervical joint mobility, reducing mechanical nociceptive drive into the trigeminocervical complex and thereby lowering central sensitization.
Normalization of suboccipital muscle tone, decreasing dural tension and local inflammatory mediators.
Modulation of autonomic outflow through improved cervical proprioception and reduced sympathetic hyperactivity.
Improved sleep architecture once nocturnal attacks diminish and cervical comfort increases.
Reduction of comorbid cervical pain, which itself amplifies overall disability and pain catastrophizing.
Comorbidities such as anxiety, depression, sleep disruption, and medication overuse are addressed concurrently. Decreased attack burden improves mood and sleep; functional-medicine evaluation can identify nutritional, inflammatory, or hormonal contributors that sustain hypothalamic or autonomic dysregulation. Soft-tissue techniques, postural re-education, and graded exercise further support long-term resilience.
Clinical reasoning dictates that chiropractic care is not a stand-alone cure for primary cluster headache but a valuable adjunct that targets modifiable cervical and musculoskeletal drivers, reduces overall nociceptive load, and improves quality of life. At the same time,e pharmacologic and neuromodulatory treatments address the core neurovascular and hypothalamic mechanisms.
Chiropractic Insights for Personal Injury Evaluation and Documentation
In the personal-injury setting, the chiropractic examination supplies objective, reproducible findings that complement imaging and neurological assessment. Restricted upper cervical motion, segmental tenderness, positive cervical flexion-rotation tests, and headache reproduction with sustained upper cervical mobilization provide clinical correlates. Pre- and post-treatment outcome measures (headache diaries, HIT-6, Neck Disability Index, pressure-pain thresholds) document change over time.
These data help establish:
The presence of biomechanical injury consistent with the reported mechanism (for example, whiplash).
A temporal relationship between the trauma, the onset or worsening of cluster-like attacks, and the cervical findings.
Functional impairment that supports claims for medical expenses, lost wages, and pain and suffering.
Response to conservative care, which demonstrates both the injury’s impact and the reasonableness of treatment.
When combined with medical records reviewed by an internal medicine physician, the file resists challenges that the complaints are purely subjective or unrelated.
Benefits of Integrative Chiropractic and Non-Surgical Approaches in Daily Health and Wellness Routines
Patients who incorporate regular chiropractic care, targeted exercise, sleep hygiene, trigger avoidance, and stress-management techniques into their routines often experience fewer and less severe bouts over time. Non-surgical options such as high-flow oxygen, non-invasive vagus-nerve stimulation, and CGRP monoclonal antibodies (galcanezumab approved for episodic cluster headache) can be layered with manual therapy. The combination reduces reliance on abortive medications, lowers the risk of medication-overuse headache, and supports overall autonomic and musculoskeletal health.
Wellness routines may include:
Scheduled chiropractic visits during and between bouts to maintain cervical mobility.
Daily suboccipital self-release and postural exercises.
Consistent sleep-wake schedules to stabilize circadian rhythms.
Nutritional strategies that address inflammation and vascular reactivity.
Gradual return to aerobic activity once attacks are controlled.
These elements are sustainable, low-risk, and complementary to medical care.
The Multidisciplinary Team Approach at Injury Medical Clinic PA with Dr. Cardenas
At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, we deliver care through a coordinated multidisciplinary model. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, with more than 40 years of experience as an internist (NPI #1164426749, Texas MD License #J2933), serves as Medical Director and Collaborative Physician. She provides medical oversight, evaluates systemic contributors, coordinates diagnostic testing, and manages pharmacologic or interventional needs when indicated.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, directs the chiropractic, functional-medicine, and rehabilitation components. The dual credentials allow simultaneous assessment of neuromusculoskeletal drivers and medical aspects of headache within a single clinical relationship, while respecting the distinct roles of the collaborative physician. Additional services include soft-tissue therapies, spinal decompression when appropriate, nutritional counseling, and collaboration with physical therapists and fitness professionals.
This structure is common in integrative injury-care settings. It ensures that red-flag conditions are excluded, comorbidities are managed, and conservative interventions are applied safely and effectively. Patients benefit from seamless communication, reduced care fragmentation, and documentation that meets both clinical and medicolegal standards.
Clinical Observations from Dr Alexander Jimenez
In practice, patients presenting after motor-vehicle collisions frequently describe new or markedly worsened unilateral headaches with autonomic features that meet or approach cluster criteria. Cervical examination often reveals restricted upper cervical motion and suboccipital hypertonicity; restoring segmental mobility and reducing muscle tone correlate with decreased attack frequency, even when advanced imaging is unremarkable. Diary data and validated outcome measures document the improvement, supporting both clinical progress and causal linkage.
Patients with long-standing primary cluster headache who also carry cervical dysfunction frequently report fewer nocturnal attacks and improved sleep once upper cervical care is added to their existing medical regimen. The combination of medical direction from Dr. Cardenas and hands-on chiropractic and functional strategies has allowed many individuals to resume work, reduce emergency-department visits, and regain a sense of control over their condition.
These observations align with the broader literature on manual therapy for headache disorders and underscore the value of addressing every modifiable contributor—biomechanical, autonomic, inflammatory, and lifestyle—within a coordinated team.
Conclusion
Cluster headaches impose a severe physiological and personal burden through hypothalamic, trigeminovascular, and autonomic mechanisms. Accurate diagnosis, comprehensive symptom recognition, and attention to daily-life impact are essential. In personal-injury litigation, rigorous documentation of temporality, biomechanics, and clinical findings establishes the required causation. Integrative chiropractic care, delivered within a multidisciplinary framework that includes experienced internal-medicine oversight, offers a safe, non-surgical way to reduce attack burden, address comorbidities, and support long-term wellness. This collaborative, evidence-informed approach benefits patients and clinicians alike.
de-la-Puente-Ranea, L., Gil-Martínez, A., et al. (2021). Manual therapy and exercise for patients with cluster headache. EXCLI Journal. https://doi.org/10.17179/excli2021-3763
Grangeon, L., et al. (2020). New insights in post-traumatic headache with cluster headache phenotype: A cohort study. Journal of Neurology, Neurosurgery & Psychiatry. https://jnnp.bmj.com/content/91/6/572
Headache Classification Committee of the International Headache Society. (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia. https://ichd-3.org/
Vollesen, A. L. H., et al. (2018). Effect of infusion of calcitonin gene-related peptide on cluster headache attacks: A randomized clinical trial. JAMA Neurology.
cluster headaches, cluster headache symptoms, how cluster headaches affect the body, cluster headache daily life impact, causation personal injury cluster headaches, chiropractic care for cluster headaches, non-surgical treatment cluster headaches, integrative chiropractic El Paso, Dr Alex Jimenez, Dr Maria Guadalupe Cardenas, Injury Medical Clinic PA, trigeminovascular system, hypothalamus cluster headache, CGRP cluster headache, post-traumatic headache, upper cervical chiropractic, wellness routine headaches, El Paso personal injury clinic
This post is intended for educational purposes and does not constitute medical or legal advice. Individual results vary; consult qualified healthcare and legal professionals.
If Spinal Decompression Relieves Back Pain, Does That Prove a Herniated Disc Caused It?
A patient finishes a course of motorized spinal decompression, stands up, and reports that the familiar ache across the low back has eased. The relief feels clear. It is natural to conclude that the treatment “worked on the disc,” and therefore the disc must have been the structure generating the pain. In personal-injury and clinical settings, this reasoning appears often. It is also incomplete.
Symptomatic improvement during a carefully supervised treatment program is valuable information. It tells clinicians and patients that a non-invasive approach can change symptoms and function. It does not, by itself, identify the single anatomical structure that was producing the pain. Clinicians must read disc pathology, nonspecific low-back pain, examination findings, and imaging findings together. Treatment response is one data point among many, not a diagnostic test that names the pain generator.
Disc Pathology Is Common and Often Silent
Intervertebral discs change with age, load, and prior stress. On MRI, disc bulges, protrusions, and even frank herniations appear in people who have never reported meaningful back or leg pain. Systematic reviews of asymptomatic adults show that disc herniations and degenerative findings are present in a substantial fraction of the population, and the prevalence rises with age (Brinjikji et al., 2015). A herniated disc visible on imaging is therefore a morphological observation. The North American Spine Society nomenclature emphasizes that the terms “herniated disc” or “protrusion” describe location and morphology; they do not, by themselves, establish etiology, symptom correlation, or the need for any particular treatment (Fardon et al., 2014).
Even when a disc herniation is present and the patient has pain, the relationship is not automatic. Chemical irritation from annular fissures, mechanical loading of the facet joints, muscle guarding, and altered movement patterns can all contribute. In many patients, more than one structure is sensitized at the same time. A treatment that reduces intradiscal pressure or unloads the posterior elements may improve symptoms by affecting several of those structures simultaneously. The improvement does not isolate which structure was dominant.
Nonspecific Low-Back Pain Remains the Most Common Presentation
Most episodes of low-back pain are classified as nonspecific. That label means that no single, clearly identifiable pathoanatomical source accounts for the symptoms after a careful history and examination. Large clinical guidelines and evidence reviews consistently note that a specific structural diagnosis is established in only a minority of patients presenting with axial low-back pain (Chou et al., 2007; Maher et al., 2017). Nonspecific pain can still be real, functionally limiting, and responsive to mechanical care.
Spinal decompression therapy creates a controlled reduction in intradiscal pressure and can increase intervertebral height temporarily. Those mechanical effects may reduce load on irritated discs, facet joints, and surrounding soft tissues. Patients often report less pain and better tolerance for standing or walking. The same patients may also improve with targeted exercise, manual therapy, or simple activity modification. When multiple interventions that unload or stabilize the lumbar region produce similar relief, the response supports the idea that mechanical loading is relevant. It does not prove that a particular disc herniation seen on one MRI slice was the sole generator.
What the Examination and Imaging Can and Cannot Show
A thorough examination looks for directional preference, symptom changes with repeated movements, neurological findings, and functional limitations. Digital range-of-motion measurements, straight-leg-raise responses, and segmental motion testing provide objective data that clinicians can track over time. These findings help clinicians decide whether a trial of decompression is reasonable and later document whether function changed.
Imaging adds morphological detail. Flexion-extension radiographs can demonstrate altered motion-segment integrity when translation or angular motion exceeds established thresholds used in impairment systems. MRI can show disc contour, annular high-intensity zones, and nerve-root contact. However, none of these studies reliably identify the pain-generating structure in every patient. Studies comparing imaging findings with clinical outcomes show only modest correlations; many patients with clear disc herniations improve without any change in herniation size, and some patients with modest imaging findings remain symptomatic (Chou et al., 2011). Provocative discography was once used to try to link a disc to pain, yet its diagnostic value is limited by high false-positive rates and the fact that it is an invasive procedure whose results do not automatically dictate treatment.
The Limits of Treatment-Response Reasoning
Reasoning that “the treatment relieved the pain; therefore, the structure the treatment targeted must have been the cause” is a form of post-hoc attribution. It is common in everyday clinical conversations and sometimes appears in medical-legal arguments. Several factors make it unreliable as proof of the original pain generator:
Many lumbar structures share innervation and can respond to the same unloading force.
Natural history and concurrent changes in activity, posture, or inflammation can improve symptoms independently of the treatment.
Placebo and contextual effects are well documented in musculoskeletal care; some improvement occurs even when the mechanical intervention is minimal.
Patients often receive more than one intervention. Without a controlled comparison, you cannot assign improvement after a package of care to a single component.
In a medical-legal file, treatment response is most useful when it is documented alongside objective baseline and follow-up measures—range of motion, functional questionnaires, neurological status, and, when indicated, serial imaging. The response then becomes part of a longitudinal narrative rather than a stand-alone diagnostic claim. Attorneys and clinicians reviewing the file can see that mechanical care produced measurable functional change; they cannot, based on the response alone, conclude that a particular disc herniation was the exclusive cause of the original pain.
An Integrated Approach That Respects These Limits
At Injury Medical Clinic PA in El Paso, we begin evaluating lumbar complaints with a dual-scope assessment. Dr. Alex Jimenez, DC, APRN, FNP-BC, documents soft-tissue and biomechanical findings, including digital range-of-motion and segmental testing. Dr. Maria Guadalupe Cardenas, MD, provides medical direction, reviews comorbidities, and coordinates any indicated laboratory or imaging work-up. When spinal decompression is chosen, it is applied within a broader plan that may include targeted exercise, soft-tissue work, and education on load management. Clinicians record symptom change but form the clinical impression from the full set of findings, not improvement alone.
This approach aligns with three practical principles. Beneficence is served by selecting interventions that address modifiable mechanical and inflammatory contributors without assuming a single structure is responsible. Non-maleficence is served by preferring non-invasive unloading and movement strategies before considering more aggressive options. Autonomy is served by explaining to the patient, in plain language, what the imaging shows, what it does not show, and how treatment response will be interpreted as one piece of information rather than proof of a specific diagnosis.
What makes the clinic distinct in El Paso is the combination of a board-certified internist serving as medical director and a dual-licensed nurse practitioner who specializes in soft-tissue and biomechanical injury. Few clinics in the region integrate these scopes under one roof while also offering advanced mechanical decompression, digital motion analysis, and coordinated medical oversight. The result is documentation that describes both the morphological findings and the functional response without overclaiming that one proves the other.
Patients and attorneys who need a clearer picture of how disc findings, examination data, and treatment response fit into a causation narrative can review related discussions on lumbar disc nomenclature, imaging correlation, and the broader process of establishing medical-legal causation. Those resources appear on the clinic’s educational site and reinforce the same principle: relief is welcome, yet the structure that generated the pain is identified only when history, examination, imaging, and longitudinal function are considered together.
Symptom relief after spinal decompression is a positive clinical outcome. It supports the continued use of non-invasive mechanical care for many patients with lumbar pain. It does not, by itself, prove that a herniated disc was the pain-generating structure. That determination still requires the full clinical picture.
References
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., … Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816.
Chou, R., Qaseem, A., Snow, V., Casey, D., Cross, J. T., Jr., Shekelle, P., & Owens, D. K. (2007). Diagnosis and treatment of low back pain: A joint clinical practice guideline from the American College of Physicians and the American Pain Society. Annals of Internal Medicine, 147(7), 478–491.
Fardon, D. F., Williams, A. L., Dohring, E. J., Murtagh, F. R., Gabriel Rothman, S. L., & Sze, G. K. (2014). Lumbar disc nomenclature: Version 2.0. The Spine Journal, 14(11), 2525–2545.
Maher, C., Underwood, M., & Buchbinder, R. (2017). Non-specific low back pain. The Lancet, 389(10070), 736–747.
Alcohol, Chronic Back Pain, and Cancer Awareness: Why Medical Screening Matters
Abstract
Alcohol can quietly undermine sleep quality, medication safety, tissue healing, and long-term cancer risk while masking or worsening musculoskeletal symptoms. Persistent or unexplained back pain is not always a purely mechanical spinal problem and sometimes requires medical evaluation to rule out red-flag conditions. Coordinated physician or nurse practitioner assessment combined with appropriate chiropractic rehabilitation supports safer treatment selection and better recovery outcomes.
Imagine finishing a long day with a drink to “take the edge off” chronic back stiffness, only to wake feeling more fatigued, with tighter muscles and slower recovery. This common pattern hides important biology. Alcohol affects sleep architecture, interacts with common pain medications, slows musculoskeletal repair, and independently raises the risk of several cancers. At the same time, back pain that does not behave like a typical strain sometimes needs medical screening before any hands-on treatment begins. Understanding these connections helps patients make safer choices and receive the right care at the right time.
How Alcohol Disrupts Sleep and Recovery
Even moderate evening drinking can shorten the time it takes to fall asleep, yet it fragments the rest of the night. Alcohol suppresses rapid eye movement (REM) sleep early and then produces rebound fragmentation later, reducing overall sleep efficiency (National Institute on Alcohol Abuse and Alcoholism [NIAAA], 2026). Poor sleep raises pain sensitivity the next day and slows tissue repair because growth hormone and other recovery processes peak during deep sleep stages. For someone already managing back pain, this creates a cycle: alcohol feels helpful at night, yet the resulting sleep loss increases muscle tension, inflammation, and next-day stiffness.
Chronic use also contributes to alcoholic myopathy—muscle wasting and weakness driven by reduced protein synthesis, mitochondrial stress, and impaired regeneration (NIAAA, 2026). Bone density declines with heavier intake because alcohol slows osteoblast activity, the cells that build new bone. Fracture healing can be delayed, and callus formation is weaker. These effects matter for anyone whose back pain involves disc, facet, or soft-tissue loading; slower repair means longer disability and higher risk of reinjury.
Medication Safety and Musculoskeletal Healing
Alcohol interacts with many medications used for back pain. Combining it with opioids deepens sedation and respiratory depression. With acetaminophen, it increases liver stress. Even nonsteroidal anti-inflammatory drugs (NSAIDs) carry higher gastrointestinal risk when alcohol is added. In the recovery window after injury or adjustment, these interactions can turn a routine pain plan into a safety issue.
Beyond drug interactions, alcohol impairs the very processes needed for healing. It promotes systemic inflammation, disrupts collagen remodeling in tendons and ligaments, and reduces the body’s ability to clear waste from strained tissues. Patients who continue drinking while receiving rehabilitation often report slower progress, more night pain, and greater reliance on medication. Reducing or pausing alcohol during active recovery provides the musculoskeletal system a cleaner environment in which to rebuild.
Independent Cancer Risk
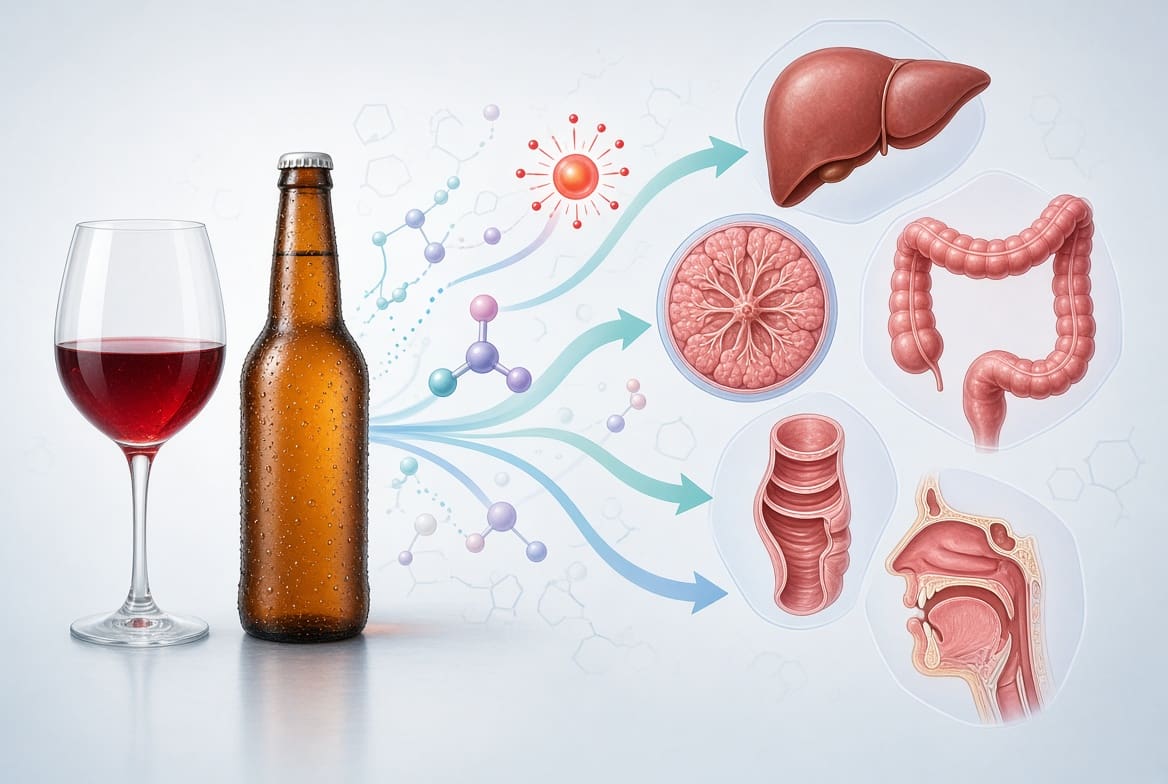
Alcohol is classified as a known human carcinogen. Risk rises with total exposure and appears for several common cancers even at levels some people consider moderate (NIAAA, 2026; Office of the Surgeon General, 2025). Established associations include cancers of the oral cavity, pharynx, larynx, esophagus, liver, colorectum, and female breast. Mechanisms include acetaldehyde production (a toxic metabolite), oxidative stress, hormonal shifts (particularly estrogen), and enhanced absorption of other carcinogens.
This cancer risk is independent of back pain yet relevant to screening decisions. Unexplained weight loss, night pain, or progressive symptoms in a person with significant alcohol history may warrant earlier medical work-up rather than prolonged assumption that the pain is only mechanical. The same lifestyle factor that delays soft-tissue healing also elevates lifetime cancer risk, making coordinated medical awareness valuable.
Why Persistent Back Pain Sometimes Needs Medical Evaluation
Most episodes of back pain improve with activity modification, exercise, and conservative care. A smaller subset does not. Red-flag features raise concern for fracture, infection, malignancy, or serious nerve compression and justify medical assessment before or alongside chiropractic care (Downie et al., 2013; Verhagen et al., 2017).
Key historical red flags include:
History of cancer (especially breast, lung, prostate, kidney, or thyroid)
Unexplained weight loss
Age over 50 with new-onset pain, or age under 18
Fever, intravenous drug use, or immunosuppression
Significant trauma or prolonged corticosteroid use
Progressive neurological deficits, saddle anesthesia, or new bowel/bladder dysfunction
Pain that is constant, worse at night or at rest, and unrelieved by position change
Physical examination may add point tenderness over bone, neurological deficits, or signs of systemic illness. No single red flag is perfectly accurate, but combinations improve diagnostic utility. A history of cancer plus unexplained weight loss, for example, substantially raises the post-test probability of spinal malignancy. Guidelines therefore recommend medical evaluation when red flags are present, rather than automatically attributing symptoms to mechanical spinal dysfunction.
At Injury Medical Clinic PA, initial encounters routinely include this screening. Dr. Alex Jimenez, DC, APRN, FNP-BC, applies both chiropractic and nurse-practitioner perspectives so mechanical findings are interpreted in a medical context. When red flags appear, further diagnostics or referral can occur without delay, protecting patient safety while still allowing appropriate rehabilitation to proceed once serious pathology is excluded.
Coordinated Physician/Nurse Practitioner Assessment and Chiropractic Rehabilitation
Safe treatment selection begins with accurate triage. Physician or nurse practitioner assessment clarifies medication risks, screens for systemic contributors (including alcohol-related neuropathy or metabolic issues), and decides whether imaging or laboratory work is indicated. Once red flags are addressed, chiropractic care focuses on restoring joint mobility, reducing protective muscle spasm, improving movement patterns, and guiding graded exercise.
This sequence prevents the common error of applying manual therapy to an undiagnosed fracture, infection, or metastatic lesion. It also avoids unnecessary imaging in uncomplicated mechanical pain. Outcome measures such as the Oswestry Disability Index help track functional progress objectively (see clinic resources on assessing lower back pain). Patients who reduce alcohol intake during this phase often notice better sleep, less morning stiffness, and faster mobility gains.
Alcohol-related peripheral neuropathy can further complicate the picture by producing burning pain, numbness, or weakness in the extremities that may be mistaken for radiculopathy. Differentiating the two requires a careful neurological examination and, when indicated, laboratory evaluation for nutritional deficiencies (Jimenez, n.d.; see alcoholic peripheral neuropathy overview).
What Makes the Clinic Distinct in El Paso
Injury Medical Chiropractic and Functional Medicine Clinic is unique in El Paso, Texas, because it integrates a medical director, Dr. Maria Guadalupe Cardenas, MD (board-certified in internal medicine), with a dual-licensed chiropractor and board-certified family practice nurse practitioner who specializes in soft-tissue injury. This structure is the only one in El Paso that combines on-site medical direction and nurse-practitioner assessment with comprehensive chiropractic rehabilitation, advanced soft-tissue therapies, and functional medicine tools under one coordinated team. Patients receive medical screening for red flags, medication safety review, and systemic contributors (including alcohol effects) in the same visit where spinal mechanics and rehabilitation are addressed, reducing fragmentation and supporting safer, root-cause-oriented care.
Practical Steps Patients Can Take
Track alcohol intake honestly and note its relationship to sleep quality and next-day pain.
Disclose all medications and supplements so interactions can be reviewed.
Report red-flag symptoms promptly rather than waiting for them to resolve on their own.
Pair any reduction in alcohol with consistent movement, protein intake, and sleep hygiene to support tissue repair.
Seek coordinated evaluation when pain persists beyond several weeks, changes character, or is accompanied by systemic symptoms.
These steps empower patients as informed decision-makers while ensuring care remains aligned with their primary medical team.
Multidisciplinary Call to Action
If you are experiencing chronic or unexplained back pain—especially if alcohol use, sleep disruption, or medication concerns are part of the picture—schedule a coordinated evaluation at Injury Medical Clinic PA. Medical screening by the nurse practitioner and medical director team, followed by appropriate chiropractic rehabilitation, can clarify whether your symptoms are mechanical, systemic, or both, and guide a safer path toward improved mobility, better sleep, and reduced reliance on pain medication. Contact the clinic to begin a personalized assessment that prioritizes both root-cause insight and patient safety.
References
Downie, A., Williams, C. M., Henschke, N., Hancock, M. J., Ostelo, R. W. J. G., de Vet, H. C. W., Macaskill, P., Irwig, L., van Tulder, M. W., Koes, B. W., & Maher, C. G. (2013). Red flags to screen for malignancy and fracture in patients with low back pain: Systematic review. BMJ, 347, f7095. https://doi.org/10.1136/bmj.f7095
Verhagen, A. P., Downie, A., Maher, C. G., & Koes, B. W. (2017). Most red flags for malignancy in low back pain guidelines lack empirical support: A systematic review. Pain, 158(10), 1860–1868. https://doi.org/10.1097/j.pain.0000000000000998
Learn how chiropractic rehabilitation can relieve symptoms and improve quality of life for people with migraines.
Abstract
Migraine is a complex neurological disorder that affects more than one billion people worldwide and disrupts daily life through recurrent attacks of moderate to severe head pain, sensory sensitivities, and associated symptoms. This educational post, written by Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, explains the physiological underpinnings of migraine, its phases and symptoms, its effects on day-to-day functioning, and evidence-based non-surgical approaches. It covers how integrative chiropractic care can be combined with functional medicine, physical therapy, massage therapy, rehabilitation, and medical oversight to raise attack thresholds and reduce cervicogenic drivers into the trigemino-cervical complex. The post also details the role of onabotulinumtoxinA (Botox) for chronic migraine, including mechanisms, clinical guidelines, and the PREEMPT injection protocol, along with practical home strategies. At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, Dr. Jimenez collaborates with Medical Director and Collaborative Physician Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933), who brings more than 40 years of experience as an internist. This multidisciplinary model integrates chiropractic care, medical direction, functional wellness, personal injury rehabilitation, and related services for comprehensive, patient-centered migraine management.
What Migraine Is and How It Affects the Body
Migraine is not simply a bad headache. It is a primary neurological disorder characterized by recurrent attacks of head pain accompanied by other symptoms that reflect widespread nervous system involvement. According to the International Classification of Headache Disorders, 3rd edition (ICHD-3), migraine without aura involves at least five attacks lasting 4 to 72 hours that are unilateral, pulsating, moderate to severe in intensity, aggravated by routine physical activity, and accompanied by nausea, vomiting, photophobia, or phonophobia (Headache Classification Committee of the International Headache Society, 2018). Chronic migraine is defined as headache on 15 or more days per month for more than three months, with at least eight of those days meeting migraine criteria or responding to migraine-specific treatment (Headache Classification Committee of the International Headache Society, 2018).
The physiology begins with a genetically influenced tendency toward neuronal hyperexcitability. Leading research describes activation of the trigeminovascular system, in which nociceptive fibers innervating the dura and large cerebral vessels release neuropeptides such as calcitonin gene-related peptide (CGRP) and substance P. This produces sterile neurogenic inflammation, peripheral sensitization of trigeminal afferents, and subsequent central sensitization in the trigemino-cervical complex and higher centers (Dodick, 2018; Goadsby et al., 2017). Cortical spreading depression is the electrophysiological event thought to underlie aura: a wave of neuronal and glial depolarization that propagates across the cortex and can activate meningeal nociceptors. Hypothalamic and brainstem nuclei that regulate sensory gating, circadian rhythms, and autonomic function appear dysregulated before the pain phase, which helps explain premonitory symptoms. Serotonergic pathways and descending inhibitory controls are also impaired, lowering the threshold for subsequent attacks.
When comorbidities such as cervical musculoskeletal dysfunction, anxiety, depression, sleep disruption, or metabolic factors are present, they amplify this cascade. Forward head posture, restricted upper cervical segments, and myofascial trigger points in the suboccipital, trapezius, and sternocleidomastoid muscles increase afferent traffic into the trigemino-cervical complex, further sensitizing the system. In clinical observation at our El Paso clinic, patients frequently present with these structural findings alongside classic migraine features; addressing them often reduces the frequency of attacks that appear triggered by neck stiffness or postural strain.
Symptoms of Migraines and the Phases of an Attack
Migraine attacks typically unfold in phases, although not every person experiences every phase.
Prodrome (hours to days before pain): Fatigue, yawning, mood changes, neck stiffness, food cravings, difficulty concentrating, or heightened sensory sensitivity. These early signs reflect hypothalamic and limbic involvement and offer a window for early intervention.
Aura (experienced by roughly 25–30 % of people): Fully reversible visual (scintillating scotoma, fortification spectra), sensory (paresthesias), language, or motor symptoms that develop gradually over at least five minutes and last 5–60 minutes. Aura is linked to cortical spreading depression and is distinct from the abrupt deficits of transient ischemic attack.
Headache phase: Moderate to severe unilateral or bilateral throbbing pain, nausea or vomiting, photophobia, phonophobia, osmophobia, and cutaneous allodynia (pain from light touch). Central sensitization explains why ordinary stimuli become painful.
Postdrome: Residual fatigue, cognitive fog, neck stiffness, or mood changes lasting hours to a day or more. Recovery is incomplete until the nervous system resets.
Additional symptoms can include dizziness, nasal congestion, or autonomic features. In day-to-day life, these attacks force people to stop work, cancel family activities, retreat to dark, quiet rooms, and rely on others. Missed workdays, reduced productivity, sleep disruption, and anxiety about the next attack create a cycle that lowers overall quality of life and can lead to social withdrawal or medication overuse.
How Migraines Affect Day-to-Day Life and the Person
The cumulative burden is substantial. Attacks interrupt concentration, driving, exercise, and social plans. Children may miss school; adults may lose career opportunities or struggle with parenting. Chronic migraine is associated with higher rates of depression, anxiety, and sleep disorders, which in turn lower the threshold for further attacks. Personal injury cases seen in our clinic often involve whiplash or trauma that worsens underlying migraine through added cervical nociception; coordinated rehabilitation is therefore essential.
Benefits of Chiropractic Care and Non-Surgical Treatments in an Integrative Routine
Integrative chiropractic care fits within a broader non-surgical framework that addresses both the neurological core of migraine and modifiable peripheral drivers. Spinal manipulation and mobilization of the upper cervical and thoracic spine, soft-tissue release of suboccipital and cervical musculature, postural rehabilitation, and exercise can normalize mechanoreceptor input into the trigemino-cervical complex and reduce secondary muscle guarding. While high-certainty evidence that spinal manipulation alone is superior to sham for pure migraine remains limited, multimodal chiropractic approaches that include education, exercise, and soft-tissue work have shown reductions in migraine days in feasibility studies (Rist et al., 2021). Physical therapy similarly targets strength, endurance, and mobility deficits; massage therapy reduces trigger-point activity and promotes parasympathetic tone; functional medicine evaluates micronutrient status (magnesium, riboflavin, CoQ10), gut health, hormones, and inflammatory drivers.
At Injury Medical Clinic PA, we coordinate these elements under medical oversight. Dr. Jimenez performs neuromusculoskeletal assessment and delivers low-force adjustments, myofascial release, and rehabilitative exercise tailored to each patient’s presentation. Dr. Maria Guadalupe Cardenas, MD, provides differential diagnosis to exclude secondary causes, monitors for red-flag symptoms using frameworks such as SNOOP, oversees pharmacologic options when indicated, and ensures safe co-management. Functional medicine testing and nutrition counseling address root contributors, while personal-injury rehabilitation protocols support patients whose migraine has been aggravated by trauma. The reasoning is straightforward: by lowering overall nociceptive load and supporting central inhibitory mechanisms, the threshold for a full attack rises, attacks become less frequent or severe, and patients regain capacity for daily activities.
Migraine Pain Treatment El Paso, TX Chiropractor- Video
How Botox Helps with Migraines and Clinical Guidelines
OnabotulinumtoxinA (Botox) is FDA-approved for the prevention of headaches in adults with chronic migraine (15 or more headache days per month, each lasting at least four hours). It is not indicated for episodic migraine. The American Migraine Foundation and American Academy of Neurology/American Headache Society guidelines recognize it as an evidence-based preventive option, particularly when patients have not responded adequately to oral preventives (American Migraine Foundation, n.d.; AAN/AHS guidelines).
Mechanism: Purified botulinum toxin type A is injected into multiple sites around the head and neck. It is taken up at nerve terminals and cleaves SNAP-25, blocking acetylcholine release and reducing the release of pro-inflammatory neuropeptides such as CGRP from trigeminal sensory neurons. This dampens peripheral sensitization and, over repeated cycles, central sensitization. The standard PREEMPT protocol uses 155 units distributed across 31 injection sites in seven muscle groups (frontalis, corrugator, procerus, temporalis, occipitalis, cervical paraspinals, and trapezius); a “follow-the-pain” approach may add up to 40 additional units in selected patients. Treatments are repeated every 12 weeks.
Pivotal evidence comes from the PREEMPT 1 and 2 trials (pooled n = 1,384). At 24 weeks, mean headache days decreased by 8.4 with onabotulinumtoxinA versus 6.6 with placebo; secondary measures of disability and quality of life also improved (Dodick et al., 2010). Benefit often increases with successive cycles, and many patients achieve at least a 50 % reduction in headache days. Common side effects are mild and transient (neck pain, injection-site discomfort); an ice pack afterward is often helpful. Insurance coverage often requires failure of two other preventive classes; a trained headache specialist or neurologist typically delivers treatment.
In our multidisciplinary setting, Botox is considered for appropriate chronic migraine patients after medical evaluation by Dr. Cardenas and coordination with neurology when needed. Chiropractic and rehabilitative care continue in parallel to address cervical contributors that may persist even after pharmacologic prevention is optimized.
Home Strategies to Reduce Migraines
Patients can lower attack frequency through consistent daily habits:
Maintain regular sleep and wake times; both too much and too little sleep are common triggers.
Stay hydrated and eat balanced meals at consistent intervals to avoid blood-sugar swings.
Identify and limit personal triggers (certain foods, bright lights, strong odors, weather changes) using a headache diary.
Practice stress-reduction techniques such as diaphragmatic breathing, progressive muscle relaxation, or mindfulness; these enhance descending inhibitory pathways.
Engage in regular moderate aerobic exercise or yoga once cleared by a clinician; abrupt intense exercise can trigger attacks in some individuals, but consistent activity generally raises the threshold.
Apply cold packs to the neck or forehead at the first sign of prodrome and rest in a dark, quiet room.
Consider evidence-supported supplements (magnesium, riboflavin, CoQ10) after discussion with the clinical team, especially when laboratory testing shows deficiency.
These measures form the foundation of the personalized “migraine toolkit” we build with patients; early recognition of prodrome allows timely use of acute medications or non-pharmacologic steps before full sensitization occurs.
Integrating Care at Injury Medical Clinic PA
The collaborative model at our El Paso clinic ensures we address structural, neurological, metabolic, and medical factors together. Dr. Jimenez’s dual training as a chiropractor and board-certified family nurse practitioner allows seamless coordination of hands-on care, patient education, and pharmacologic awareness. Dr. Cardenas’s internal medicine expertise provides rigorous medical direction, laboratory interpretation, and safety oversight for complex or comorbid cases. Rehabilitation, functional wellness, and massage are woven into the same plan rather than delivered in isolation. Clinical observations consistently show that patients who receive this coordinated approach report fewer missed work or family days, reduced reliance on acute medications, and improved confidence in managing their condition.
Migraine management succeeds when it respects the biology of the disorder while systematically reducing every modifiable driver. Integrative chiropractic care, non-surgical rehabilitation, functional medicine, and, when indicated, evidence-based preventives such as Botox, can be combined under proper medical oversight to restore function and quality of life.
Dodick, D. W. (2018). A phase-by-phase review of migraine pathophysiology. Headache, 58(Suppl 1), 4–16. https://doi.org/10.1111/head.13300
Dodick, D. W., Turkel, C. C., DeGryse, R. E., Aurora, S. K., Silberstein, S. D., Lipton, R. B., Diener, H. C., & Brin, M. F. (2010). OnabotulinumtoxinA for treatment of chronic migraine: Pooled results from the double-blind, randomized, placebo-controlled phases of the PREEMPT clinical program. Headache, 50(6), 921–936. https://doi.org/10.1111/j.1526-4610.2010.01678.x
Goadsby, P. J., Holland, P. R., Martins-Oliveira, M., Hoffmann, J., Schankin, C., & Akerman, S. (2017). Pathophysiology of migraine: A disorder of sensory processing. Physiological Reviews, 97(2), 553–622. https://doi.org/10.1152/physrev.00034.2015
Headache Classification Committee of the International Headache Society. (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. https://doi.org/10.1177/0333102417738202
Rist, P. M., Bernstein, C., Kowalski, M., Osypiuk, K., Connor, J. P., Vining, R., Long, C. R., Macklin, E. A., & Wayne, P. M. (2021). Multimodal chiropractic care for migraine: A pilot randomized controlled trial. Cephalalgia, 41(3), 318–328. https://doi.org/10.1177/0333102420963849
SEO tags
migraine treatment El Paso, chiropractic care for migraines, Botox for chronic migraine, integrative migraine management, non-surgical migraine relief, Dr. Alexander Jimenez, Dr. Maria Guadalupe Cardenas, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, trigeminovascular system, CGRP, PREEMPT protocol, cervical dysfunction, migraine, functional medicine, physical therapy, home migraine prevention, chronic migraine, ICHD-3, multidisciplinary migraine care, El Paso
Cervical Muscle and Joint Factors That Amplify Migraine Frequency — and How Structural Care Complements Guideline-Based Prevention
Many people notice their migraines don’t stay confined to the head. The pain often starts or intensifies when the neck feels tight, the base of the skull aches, or turning the head triggers a familiar throb behind the eyes. After a collision or long periods of forward head posture, those neck symptoms can push occasional headaches into a pattern of 15 or more headache days per month. At that point, the condition meets criteria for chronic migraine, and guideline-based prevention such as the PREEMPT injection protocol with onabotulinumtoxinA becomes a medically appropriate option. Structural care that addresses the cervical muscles and joints does not replace that protocol; it reduces the mechanical amplifiers that can keep the frequency high even when preventive injections are used.
Why Neck Tension Amplifies Migraine Frequency
The connection is anatomical and functional. Sensory signals from the upper neck travel through the trigeminocervical complex and converge with pathways that process migraine pain. When certain muscles stay shortened or overloaded, they continuously feed extra input into those shared circuits. Restricted joints add further mechanical irritation. The result is a lower threshold for migraine attacks and more days spent in pain.
Patients commonly describe:
A band of pressure that climbs from the shoulders into the temples
One-sided headache that worsens when looking down at a phone
Increased pain when turning the head while driving on I-10 or Loop 375
Stiffness at the base of the skull that precedes or accompanies the migraine
Key Cervical Muscles That Contribute
Assessment begins with a clear map of the contributing muscles. These same regions appear on the PREEMPT injection map and often respond to structural care.
Occipital and suboccipital muscles
These sit at the base of the skull. They frequently harbor trigger points that refer pain over the top of the head and into the temples.
Cervical paraspinal muscles
These run alongside the spine. After whiplash or prolonged sitting, they often become guarded and contribute to ongoing neck stiffness.
Upper trapezius
This muscle links the shoulder girdle to the neck. It commonly tightens under stress, poor workstation ergonomics, or after-impact injuries.
On the PREEMPT protocol, these muscles receive:
Occipitalis: 30 units across six sites
Trapezius: 30 units across six sites
Cervical paraspinal muscles: 20 units across four sites
Together with other head and neck sites, the full protocol delivers 155 units across 31 sites, repeated every 12 weeks. The injections reduce the release of pain-signaling chemicals from nerve endings in those muscles. When underlying segmental restrictions and muscle imbalances remain unaddressed, however, the mechanical load continues and can limit how far the headache-day count falls.
Digital range-of-motion measurements that document loss of rotation or extension
Segmental restrictions at the atlantoaxial joint or lower cervical levels
Altered disc-height relationships that change load distribution
Soft-tissue findings such as taut bands in the trapezius, shortened suboccipitals, or guarded paraspinals
These findings are recorded alongside the patient’s headache diary so the timeline of neck stiffness and migraine frequency can be compared. This dual documentation supports both clinical decision-making and, when relevant, the medical-legal file by showing how post-injury alignment issues interact with the migraine pattern.
How Structural Care Complements the PREEMPT Protocol
Structural care is sequenced with the preventive protocol rather than replacing it. Typical elements include:
Gentle cervical adjustments that restore segmental motion and reduce aberrant input into the trigeminocervical complex
Soft-tissue techniques that lengthen the occipital, paraspinal, and trapezius groups
Therapeutic exercise that helps the muscles stay lengthened between injection cycles
Patients often notice that neck-related triggers become less potent within the first few weeks of combined care. This can translate into fewer headache days even before the second or third Botox cycle. Because the structural interventions are non-surgical and drug-free, they fit a stepwise approach that prioritizes lower-risk options while still allowing the evidence-based preventive injections to proceed when criteria are met.
Bioethical Principles Guiding Combined Care
Beneficence
Combined structural relief and guideline-based prevention aim to reduce migraine days, improve neck mobility, and increase tolerance for work and driving.
Non-Maleficence
We address mechanical contributors first with non-invasive methods. This reduces the chance that ongoing muscle tension will undermine the preventive treatment or push patients toward more invasive procedures.
Autonomy
Patients learn both the alignment plan—why a specific joint is being mobilized and what home exercises maintain the change—and the injection sites. This shared understanding lets them track how each component contributes to their results and discuss adjustments with the care team.
A Unique Integrated Approach in El Paso
Injury Medical Clinic PA in El Paso is uniquely positioned to deliver this coordinated approach. The clinic’s medical director, Dr. Maria Guadalupe Cardenas, MD, provides internal medicine oversight for complex metabolic and inflammatory factors that can increase headache frequency. Dr. Alex Jimenez, DC, APRN, FNP-BC, specializes in soft-tissue injury and integrates chiropractic structural care with advanced practice nursing. It is the only clinic in El Paso, TX, that provides these treatments under one roof, allowing the same dual-licensed team to document segmental findings, muscle contributions, and the response to both structural care and the PREEMPT protocol in a single continuous record.
Patients who leave with a clear understanding of their neck mechanics and injection map are better able to protect the gains between visits. Simple posture cues, targeted stretches for the upper trapezius and suboccipitals, and consistent headache-day logging become tools they own rather than instructions they merely receive. When they share those daily observations with clinicians, the plan can be refined so structural work continues to support the preventive effect of the injections.
Integrated structural documentation appears in the broader clinical framework at https://dralexjimenez.com. Related discussions of the PREEMPT protocol and integrated migraine care are available in the 2026 Clinical Guide on BOTOX for chronic migraine and the Complete Clinical Guide to Integrated Migraine Treatment. Additional background on cervicogenic contributions and manual approaches is available on the clinic’s pages on cervicogenic headaches associated with neck issues and integrative treatment, including chiropractic care for migraines. Together, these resources help patients and referring providers see how cervical muscle and joint factors are assessed and managed alongside guideline-based prevention.
References
AbbVie. (2026). BOTOX (onabotulinumtoxinA) for injection, for intramuscular use [Prescribing information]. https://www.rxabbvie.com
Aurora, S. K., Winner, P., Freeman, M. C., Spierings, E. L., Heiring, J. O., DeGryse, R. E., VanDenburgh, A. M., Nolan, M. E., & Turkel, C. C. (2011). OnabotulinumtoxinA for treatment of chronic migraine: Pooled analyses of the 56-week PREEMPT clinical program. Headache: The Journal of Head and Face Pain, 51(9), 1358–1373. https://doi.org/10.1111/j.1526-4610.2011.01990.x
Dodick, D. W., Turkel, C. C., DeGryse, R. E., Aurora, S. K., Silberstein, S. D., Lipton, R. B., Diener, H.-C., & Brin, M. F. (2010). OnabotulinumtoxinA for treatment of chronic migraine: Pooled results from the double-blind, randomized, placebo-controlled phases of the PREEMPT clinical program. Headache: The Journal of Head and Face Pain, 50(6), 921–936. https://doi.org/10.1111/j.1526-4610.2010.01678.x
Headache Classification Committee of the International Headache Society (IHS). (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. https://doi.org/10.1177/0333102417738202
Lipton, R. B., Varon, S. F., Grosberg, B., McAllister, P. J., Freitag, F., Aurora, S. K., Dodick, D. W., Silberstein, S. D., Diener, H. C., DeGryse, R. E., Nolan, M. E., & Turkel, C. C. (2011). OnabotulinumtoxinA improves quality of life and reduces impact of chronic migraine. Neurology, 77(15), 1465–1472. https://doi.org/10.1212/WNL.0b013e318232ab65
Potrebic, S., Rizzoli, P., Loder, E., Burch, R., Loder, E., & Burch, R. (2026). 2026 American Academy of Neurology/American Headache Society guideline for the preventive treatment of migraine. Neurology.
Rees, T. A., & others. (2025). Overlapping neurological mechanisms between migraine and neck pain. Cephalalgia or relevant 2025 review as cited in clinical guides.
Learn how omega-3s and chiropractic rehabilitation can support your recovery and promote a healthier lifestyle.
Abstract
In this educational post, we explore how omega-3 fatty acids, particularly eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA), resolve inflammation rather than suppress it. It is grounded in the latest evidence-based research from leading investigators. It describes the physiological pathways through which these vital nutrients produce specialized pro-resolving mediators (SPMs) such as resolvins, protectins, and maresins. They clear inflammatory cells, restore tissue homeostasis, and help healing in multiple body systems. The post also discusses dietary and supplemental sources, systemic benefits for cardiovascular, neurological, joint, and immune health, and the synergistic benefits with integrative chiropractic care. Chiropractic adjustments modulate neuro-immune responses, reduce pain, and improve recovery in non-surgical settings. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST of Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, works with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933) as Medical Director and Collaborative Physician with over 40 years of experience. The multidisciplinary team utilizes biomechanics, medicine, nutrition, functional medicine, personal injury care, and rehabilitation to treat pain, discomfort, and chronic inflammation. Readers will come away with a clear, narrative understanding of how these approaches can build a practical, evidence-informed health and wellness routine.
How Omega-3 Fatty Acids Actively Resolve Inflammation and Support Whole-Body Healing
Omega-3 polyunsaturated fatty acids (PUFAs) are vital nutrients the human body does not synthesize in adequate amounts and must obtain from food or supplements. The major long-chain forms, EPA and DHA, are incorporated into cell membranes throughout the body and influence membrane fluidity, receptor signaling, and the production of bioactive lipid mediators. Omega-3s are not classical anti-inflammatory agents that block enzymes like cyclooxygenase and shut down the entire inflammatory cascade, but they are substrates for an active resolution program. In response to cell injury or infection, a highly regulated switch in lipid mediators is initiated. SPMs replace early pro-inflammatory eicosanoids from arachidonic acid. Lipoxygenase and cyclooxygenase enzymes mediate this switch by acting on EPA and DHA stored in membrane phospholipids. The resolvins (E-series from EPA, D-series from DHA), protectins, and maresins produced bind to specific G-protein-coupled receptors on immune cells, enhancing efferocytosis (phagocytosis of apoptotic cells) to promote neutrophil clearance, reduce further leukocyte recruitment, and stimulate tissue regeneration. Recent preclinical studies show that prophylactic omega-3 enrichment reduces arthritis severity, associated with suppression of non-classical monocytes and VCAM-1-positive synovial fibroblasts, and an increase in MerTK-positive, CD206-positive pro-resolving macrophages. Lipidomics of affected tissues identified elevated resolvin E2 and resolvin E4. Pharmacologic administration of these same resolvins recapitulates the protective phenotype, confirming that it is the mediators themselves and not just reduced substrate competition that drive resolution. Similar studies in models of neuroinflammation show that DHA supplementation increases resolvin D1 levels in brain tissue and serum, restores glutathione peroxidase activity, and decreases malondialdehyde, a marker of oxidative damage. Findings in journals such as Communications Biology and other neuroscience publications explain why blocking inflammation alone is not enough; the body needs the helpful signals that SPMs send to complete healing.
Dietary Sources and Supplemental Forms of Omega-3 Fatty Acids That Optimize Resolution Pathways
In humans, plant-derived alpha-linolenic acid converts inefficiently to EPA and DHA, so marine sources remain the most efficient way to raise tissue levels. Cold-water fatty fish such as salmon, mackerel, sardines, herring, and anchovies contain preformed EPA and DHA, bound as phospholipids or triglycerides. For those who don’t regularly eat fish, concentrated doses are available in high-quality fish oil concentrates, krill oil (which also contains the antioxidant astaxanthin) and algal oil (suitable for vegetarians). Typical therapeutic doses are in the range of 1 to 4 grams of combined EPA plus DHA per day, with higher pure EPA preparations (eg, 4 grams of icosapent ethyl) used in some clinical trials. Algal sources have been considered for their sustainability and high DHA content, which is relevant for neural tissues. Consistency is key: incorporation into erythrocyte membranes, as measured by the omega-3 index, increases over weeks to months. The precursors 18-HEPE and 17-HDHA that feed SPM synthesis increase reliably with supplementation. At Injury Medical Clinic PA, we always start with food in clinical practice and supplement with purified oils if dietary intake is insufficient. We do this under medical supervision, with attention to compatibility with other medications and laboratory monitoring of lipid profiles and inflammatory markers.
Systemic Benefits of Omega-3s for Cardiovascular, Neurological, Musculoskeletal, and Oncologic Health
Higher EPA and DHA status is associated with lower circulating triglycerides, improved endothelial function, reduced platelet aggregation, and favorable changes in the omega-6 to omega-3 ratio that limit excessive production of pro-inflammatory prostaglandins and leukotrienes. Meta-analyses of randomized trials and large prospective cohorts consistently show that moderate intakes of higher blood levels or dietary intake are associated with reduced risk of coronary events, ischemic stroke, and in some analyses, atrial fibrillation. DHA is a major structural component of neuronal membranes in the brain and promotes synaptic plasticity, neurotrophic signaling, and generation of neuroprotectin D1, which inhibits microglial activation. Observational data suggest that higher seafood intake is associated with slower cognitive decline. At the same time, interventional trials have yielded more variable cognitive outcomes, but subgroup analyses indicate benefit in carriers of the APOE4 allele. Recent work shows that DHA can increase brain omega-3 levels even when cognitive scores are stable over 2 years. Joint tissue is no different. A meta-analysis of osteoarthritis trials found that omega-3 supplements reduce pain and improve function. Studies of rheumatoid arthritis found that they reduced the need for NSAIDs. A 2026 Communications Biology investigation also showed that feeding Omega-3 modulated joint cell phenotypes toward resolution via E-series resolvins. The phase 3 EMT2 trial presented at the 2026 European Society for Medical Oncology Congress was especially notable. Patients scheduled for surgery for removal of liver metastases of colorectal cancer were randomized to receive high-purity EPA 4 g/day or placebo beginning before surgery and continuing for two to four years. At five years, overall survival was 62 percent for EPA and 45.1 percent for placebo (hazard ratio, 0.68; p = .03), although progression-free survival did not differ significantly. Researchers suggested mechanisms including anti-cachexia effects, enhanced antitumor immunity, and favorable gut-microbiome shifts. These findings are consistent with previous reports that fish-oil supplementation may improve performance status during chemotherapy in gastrointestinal cancers and increase response rates in advanced non-small-cell lung cancer. In orthopedics, omega-3s have been shown to promote synthesis of the cartilage matrix, alter bone turnover, and hasten resolution of post-traumatic inflammation, providing a biochemical substratum for coupling with mechanical interventions.
Chiropractic Care Mechanisms That Reduce Pain and Modulate Inflammatory Mediators
Chiropractic spinal manipulative therapy is a high-velocity, low-amplitude thrust that stimulates mechanoreceptors in the paraspinal tissues and joint capsules. Large-diameter afferent signals reach the dorsal horn, where they can produce segmental inhibition of nociceptive transmission, reduce central sensitization, and influence descending pain-modulatory pathways from the periaqueductal gray. Targeted changes in animal models of intervertebral foramen inflammation reduce the duration of thermal and mechanical hyperalgesia, normalize dorsal root ganglion excitability, and accelerate histologic resolution of local inflammation. Human trials report decreases in circulating or ex vivo production of tumor necrosis factor-alpha, interleukin-6, and interferon-gamma after short courses of lumbar or thoracic manipulation in patients with acute or chronic low-back pain. In a pragmatic 12-week randomized trial published in 2025, chiropractic care increased brain-derived neurotrophic factor and decreased tumor necrosis factor-alpha compared with sham, consistent with increased neuroplasticity and regulated inflammatory tone. These neuroimmune effects are not merely a result of biomechanical realignment, but rather of improved segmental motion, decreased aberrant afferent barrage, and consequent normalization of autonomic and immune set-points. Furthermore, it is a natural fit for integrative protocols that also address systemic drivers of inflammation because it is non-surgical and low risk when used appropriately.
Synergistic Effects of Combining Omega-3 Supplementation with Chiropractic Care for Pain and Recovery
When membrane stores of EPA and DHA are replete, the same mechanical stimuli that activate local resolution programs can more readily generate SPMs at the site of joint or soft-tissue injury. These changes support burden-resolution pathways by reducing pro-inflammatory cytokine production, and SPMs accelerate macrophage phenotype switching and tissue remodeling. In the clinical setting, patients treated with nutritional optimization and spinal care tend to have a faster decrease in pain scores, a quicker return of range of motion, and fewer flare-ups during rehabilitation. The rationale is simple: mechanical correction removes the ongoing nociceptive and inflammatory drive from restricted segments or myofascial tension, while omega-3-derived mediators provide molecular signals that terminate the residual inflammatory response and promote regeneration. For patients with chronic musculoskeletal pain, stiffness after injury, or inflammatory arthropathies, the combination addresses both the structural and biochemical aspects of the problem. This dual approach in personal-injury and sports-rehabilitation settings supports documentation of progressive functional improvement while minimizing reliance on pharmacologic anti-inflammatories that can delay true resolution.
The Healing Diet: Combat Inflammation, Embrace Wellness- Video
Integrative Multidisciplinary Care at Injury Medical Clinic PA Under Medical Direction
Injury Medical Clinic PA, or Mission Plaza Injury Medical Clinic, is a partnership practice in El Paso, TX. Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, offers chiropractic evaluation and treatment, nurse practitioner medical assessment, functional medicine interpretation of laboratory data, and coordinated rehabilitation planning. Medical Director and Collaborative Physician: Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933). She has over 40 years of experience as an internist and provides physician-level oversight of complex medical comorbidities, medication reconciliation, and overall medical direction of care. This is a common setup in modern integrative and injury clinics, where the chiropractor focuses on the biomechanical and neuromusculoskeletal aspects. At the same time, the internist ensures medical safety, manages systemic disease, and co-manages conditions that may affect recovery. Additional team members provide expertise in personal-injury documentation, physical rehabilitation, nutritional counseling, and performance conditioning. As a result, patients receive a single coordinated plan that may include spinal adjustments, soft-tissue therapies, targeted omega-3 repletion, laboratory monitoring of inflammatory markers and fatty-acid profiles, and progressive exercise. The model reduces care fragmentation and lets clinical observations (e.g., faster resolution of post-traumatic inflammation when nutritional status is optimized) drive ongoing protocol refinement.
Practical Steps for Incorporating Omega-3s and Chiropractic Care into a Health and Wellness Routine
Start with a dietary assessment aiming for two to three servings of fatty fish per week or an equivalent algal or fish oil supplement with at least 1 gram of combined EPA plus DHA. Cut back on excess omega-6 from refined seed oils so resolution pathways aren’t inhibited by competition. Schedule an evaluation with a chiropractor experienced in integrative care to identify segmental restrictions, myofascial contributors, and movement patterns that perpetuate pain. During the acute or subacute phase, treatment frequency is usually higher (two to three visits per week), tapering to maintenance once objective improvement in pain, range of motion, and inflammatory biomarkers is documented. Laboratory monitoring (complete blood count, high-sensitivity C-reactive protein, omega-3 index, and relevant metabolic panels) is done concurrently to guide dose adjustments and confirm safety under medical supervision. Rehabilitation exercises restore motor control and endurance, and lifestyle factors such as sleep, stress management, and moderate physical activity further support SPM generation and neuroimmune balance. The multidisciplinary team can refine the plan by prompting patients to track symptoms, functional milestones, and changes in medication needs. Both are low-risk interventions when properly indicated and monitored, and can be continued as part of long-term wellness rather than used only for crisis management.
Clinical Observations and Evidence-Informed Practice Insights
In the clinic, patients with chronic neck or low-back pain following motor vehicle accidents or repetitive strain often have high levels of inflammatory markers and low omega-3 indices. Many report earlier decreases in morning stiffness and better tolerance for rehabilitative loading when spinal care is combined with supervised EPA/DHA repletion. Recent EMT2 trial data on overall survival in advanced colorectal cancer further underscore the broader physiologic impact of high-dose EPA and the value of targeting systemic inflammation, even in patients whose primary complaint is musculoskeletal issues. These observations align with published mechanistic studies showing that both nutritional and manipulative interventions can simultaneously modulate cytokine production. Ongoing outcome documentation refines protocols within the collaborative medical framework that Dr. Cardenas and the clinic team provide.
Conclusion
Omega-3 fatty acids provide the molecular substrate for the active resolution of inflammation through specialized pro-resolving mediators, while chiropractic care reduces nociceptive drive and modulates neuroimmune signaling. They provide a non-surgical, evidence-informed approach for pain and discomfort. Injury Medical Clinic PA in El Paso integrates chiropractic, internal medicine under the supervision of Dr. Maria Guadalupe Cardenas, MD, functional medicine, and rehabilitation to give you real options to incorporate into your daily health routine. Readers are encouraged to talk with qualified providers about individualized plans, understanding that lasting inflammation resolution is key to recovery from injury and long-term wellness.
Additional foundational reviews on SPM biosynthesis and clinical applications appear in Current Atherosclerosis Reports, Nutrition Reviews, and related peer-reviewed sources.
SEO Tags
omega-3 fatty acids, EPA, DHA, inflammation resolution, specialized pro-resolving mediators resolvins, chiropractic care pain reduction, integrative non-surgical treatment, El Paso, Dr Alexander Jimenez DC, Dr Maria Guadalupe Cardenas MD, Injury Medical Clinic PA, omega-3 supplements benefits, musculoskeletal healing, omega-3, chiropractic, functional medicine, inflammation, personal injury rehabilitation El Paso, evidence-based omega-3 research 2026, spinal manipulative therapy, cytokines, health wellness routine
Disclaimer: This post is intended for educational purposes and does not constitute personalized medical advice. Consult qualified healthcare providers before beginning any new supplement or treatment regimen.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine