Why Your Back May Feel Worse After Poor Sleep, Heavy Meals, and Less Movement
Abstract: Mechanical back discomfort often intensifies during periods of disrupted sleep, heavier meals, and reduced movement. In most cases, these changes do not cause a single sudden injury. Instead, they layer mechanical stress, altered recovery, and occasional inflammatory signals on existing spinal mechanics. This educational overview explains the connections, clarifies that inflammation is only one possible contributor, and outlines how coordinated chiropractic assessment, mobility work, rehabilitation, and medical evaluation can support safer recovery. Readers are encouraged to verify any steps with their providers.
A long drive to visit family, hours spent preparing a large meal, and then settling into extended sitting can leave the low back feeling stiffer or more irritable the next morning. Many people assume a new injury has appeared overnight. In reality, the change often reflects several overlapping lifestyle and mechanical factors that temporarily reduce the spine’s load tolerance. Inactivity, prolonged sitting, disrupted sleep, and shifts in daily movement patterns commonly aggravate existing mechanical back discomfort. Inflammation may play a supporting role in some individuals, yet it is not a universal explanation for pain.
Overlapping Lifestyle and Mechanical Factors
Mechanical back discomfort typically arises from the way joints, discs, muscles, and ligaments respond to posture, load, and recovery. When daily habits change, the same structures that usually tolerate ordinary activity can become more sensitive. Reduced movement lowers the natural pumping action that helps nourish intervertebral discs and keeps surrounding soft tissues pliable. Prolonged sitting increases compressive forces on the lower lumbar segments and shortens hip flexors, which can tilt the pelvis and increase tension across the low back. Disrupted sleep slows tissue repair and raises pain sensitivity the following day. Heavier meals, especially those high in refined carbohydrates and saturated fats, may further disturb sleep quality or contribute to temporary increases in systemic signals that influence comfort.
These factors rarely act alone. A person who sleeps poorly may move less the next day because of fatigue, sit longer to rest, and then eat a larger meal later in the evening. The result feels sudden, yet it is the cumulative effect of several modest changes. Research supports links between these lifestyle elements and back-related outcomes without claiming that any single factor is the sole cause (Haack et al., 2020; Alzahrani et al., 2022).
Poor Sleep and Heightened Mechanical Sensitivity
Sleep and pain are bidirectionally linked. Poor sleep can increase pain sensitivity, and ongoing discomfort can fragment sleep. During deep sleep stages, the body performs important restorative work, including modulating pain pathways and reducing inflammatory mediators. When deep sleep is shortened, individuals often report greater discomfort with ordinary mechanical loads the next day (Haack et al., 2020).
Sleep posture also matters. Supine or well-supported side-lying positions generally maintain more neutral spinal alignment, while prone sleeping can increase lumbar extension and facet loading. Even a few nights of restless sleep or late-night screen use can shift recovery. During family visits, irregular bedtimes and unfamiliar mattresses compound the issue. Addressing sleep hygiene—consistent timing, a cool, dark room, and limited late caffeine—often improves next-day comfort more than any single stretch.
Heavy Meals, Timing, and Tissue Comfort
Large or late meals can affect the back through several pathways. A heavy evening meal may cause abdominal distension that alters posture and increases lumbar lordosis while seated or lying down. Foods high in refined sugars and saturated fats are associated with higher systemic inflammatory markers in some people, which can amplify nociceptive signaling when mechanical irritation is already present. The connection isn’t automatic; many people notice no change in back comfort after an occasional large meal. For others, delayed gastric emptying, poorer sleep, and next-day inactivity create a noticeable difference.
Practical timing helps. Finishing larger meals earlier allows digestion to settle before sleep. Emphasizing protein, fiber, and omega-3-rich choices supports tissue recovery without relying on any single “anti-inflammatory” claim. Readers interested in nutrition’s role in mobility can explore related discussions at the clinic’s nutrition and wellness resources: Healthy Mobility Food and Chiropractic.
Inactivity, Prolonged Sitting, and Reduced Tolerance
Sedentary behavior of three or more hours daily has been linked to greater low-back-related disability even when it does not clearly predict the onset of new pain (Alzahrani et al., 2022). Prolonged sitting reduces blood flow to postural muscles and increases intradiscal pressure. Hip flexor tightness from sitting further loads the lumbar spine when a person finally stands or walks. Holiday travel adds long car rides; meal preparation often involves standing in one place or repeated bending; family gatherings encourage extended sitting. Each of these patterns reduces the variety of movement the spine normally receives.
Gentle movement restores tolerance. Short walks, standing breaks every 30–45 minutes, and simple hip-flexor mobility drills interrupt the cycle without requiring intense exercise. Corrective exercises that restore thoracic mobility and glute activation further unload the lumbar segments. These strategies align with clinical guidelines that favor continued activity over prolonged rest for most mechanical back presentations.
Inflammation as One Possible Contributor, Not the Whole Story
Systemic inflammation can mediate part of the relationship between sleep disturbance, higher body mass, and musculoskeletal pain in some studies. Elevated markers such as IL-6 or prostaglandins have been observed after experimental sleep restriction and correlate with increased pain reports. Yet inflammation is not required for mechanical discomfort to appear. Joint stiffness, muscle guarding, altered movement patterns, and central sensitization can all produce the same sensation of a “worse” back without any measurable rise in inflammatory blood markers.
Clinicians therefore treat inflammation as one possible contributor among several. Laboratory evaluation may be appropriate when symptoms persist, metabolic comorbidities exist, or recovery stalls, but it is not the starting assumption for every episode of mechanical discomfort. Patients should discuss any laboratory questions with their primary medical provider.
Integrative Assessment and Coordinated Care
A thorough evaluation begins with history and physical examination focused on movement quality, joint motion, soft-tissue tone, and neurological screening. Chiropractic assessment identifies restricted segments and movement patterns that increase mechanical load. When indicated, spinal mobility techniques restore segmental motion and reduce local irritation. Corrective exercises and progressive rehabilitation rebuild endurance in the deep stabilizers and hip musculature so the spine tolerates daily loads more comfortably. When medical factors such as metabolic issues, sleep disorders, or medication effects are suspected, appropriate medical evaluation ensures that care remains coordinated and safe.
At Injury Medical Clinic PA in El Paso, this process occurs under dual-scope leadership. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care with advanced-practice nursing diagnostics and functional-medicine principles. Dr. Maria Guadalupe Cardenas, MD, a board-certified internist with more than 40 years of experience, serves as Medical Director and provides medical oversight, risk stratification, and internal-medicine coordination. This combination—chiropractic assessment and rehabilitation integrated with medical direction and nurse-practitioner expertise in soft-tissue injury—is uncommon in El Paso and allows non-invasive, drug-sparing options to be matched with timely medical evaluation when needed. Learn more about the clinic’s approach at About Dr. Alexander Jimenez and the back-pain treatment pages. Additional sleep-focused discussions appear at Achieving Better Sleep With Chronic Back Pain.
Practical Steps During Busy Periods
Break long sitting every 30–45 minutes with two minutes of walking or standing hip-flexor stretches.
Keep a consistent sleep window even during travel; use a supportive pillow between the knees in side-lying if needed.
Finish heavier meals at least three hours before bed and include protein plus vegetables.
Begin the day with five to ten minutes of gentle spinal mobility (cat-camel, pelvic tilts, thoracic rotations) before prolonged sitting.
Note patterns: if discomfort rises after specific combinations of late meals and short sleep, share that timeline with your provider.
These steps support self-governance while remaining non-diagnostic. They do not replace individualized assessment.
Multi-Disciplinary Call to Action
If mechanical back discomfort continues to limit mobility, sleep, or daily activity, a coordinated evaluation can clarify which overlapping factors are most relevant for you. At Injury Medical Clinic PA, Dr. Jimenez and the clinical team integrate chiropractic spinal mobility work, corrective exercise, rehabilitation, and appropriate medical oversight under Dr. Cardenas to support root-cause recovery without unnecessary reliance on medication or surgery. Contact the clinic to schedule an assessment, review current imaging or labs with your existing providers, and design a plan that matches your goals for pain relief, improved movement, and more restful nights. Visit dralexjimenez.com to explore additional educational articles and begin the conversation.
References
Alzahrani, H., Alshehri, M. A., Alzhrani, M., Alshehri, Y. S., & Al Attar, W. S. A. (2022). The association between sedentary behavior and low back pain in adults: A systematic review and meta-analysis of longitudinal studies. PeerJ, 10, e13127. doi.org/10.7717/peerj.13127
Haack, M., Simpson, N., Sethna, N., Kaur, S., & Mullington, J. (2020). Sleep deficiency and chronic pain: Potential underlying mechanisms and clinical implications. Neuropsychopharmacology, 45(1), 205–216. doi.org/10.1038/s41386-019-0439-z
Why Sub-Occipital Headaches Often Follow Neck Strain in Accidents—and How Structural Care Fits
Abstract
After a car accident, many people notice a new headache that starts right at the base of the skull and flares when they turn their head, look down at a phone, or hold one posture too long. These sub-occipital headaches often reflect strain in the upper cervical joints and the small muscles that connect the skull to the top of the neck. Careful screening first rules out serious injury; targeted structural care and rehabilitation can then address the mechanical drivers while the patient stays in charge of decisions.
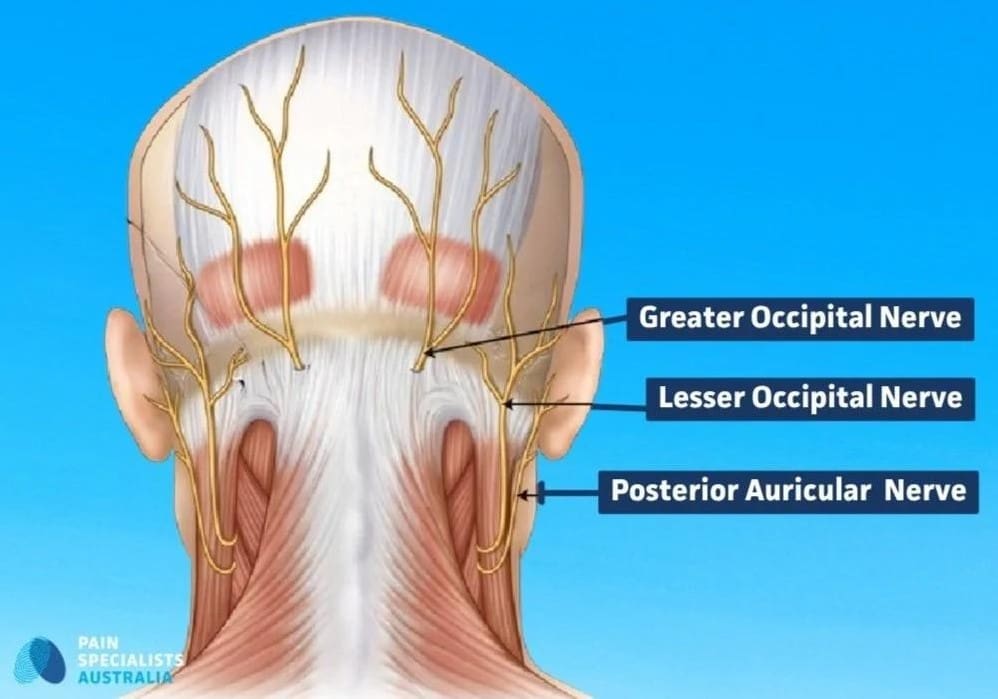
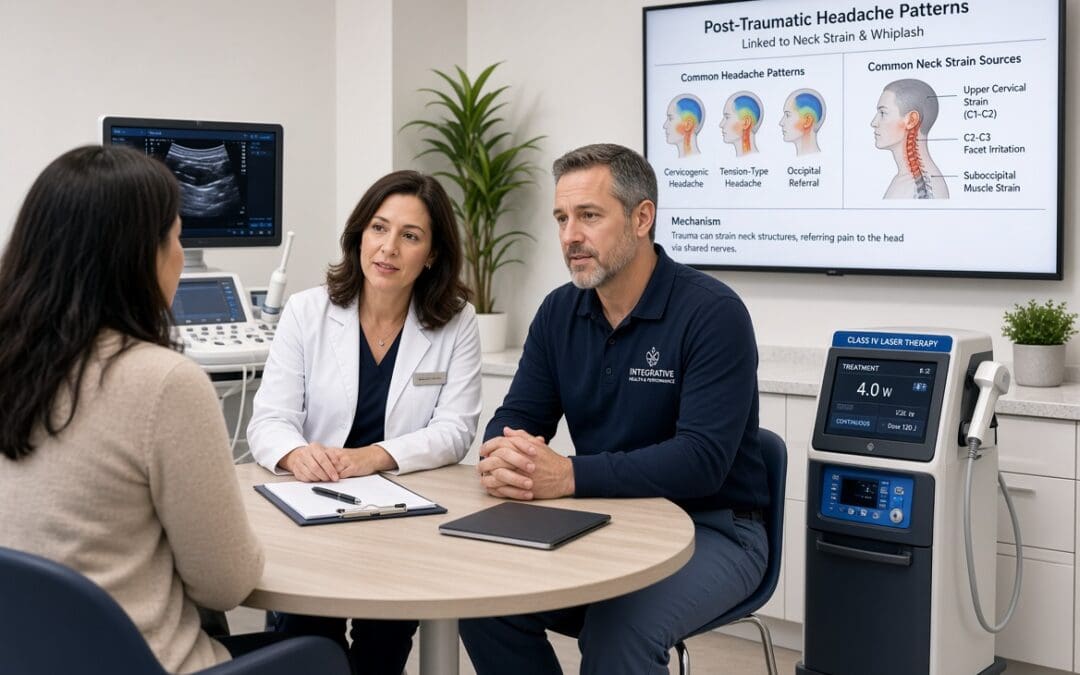
You walk away from a rear-end collision on I-10 or Loop 375 feeling mostly stiff. A day or two later, a dull, heavy ache settles at the base of your skull. Turning your head to check a blind spot, working at a computer, or even resting your head on a pillow makes it sharper. The pain may stay local or spread over the top of the head. This pattern is common after neck strain, and it does not automatically mean the brain itself was injured. Upper cervical joints and the suboccipital muscles frequently become sources of referred pain once rapid deceleration loads them beyond their normal range.
The upper neck and the base of the skull share nerve pathways inside the trigeminocervical complex. Irritation in the joints or muscles of the upper cervical spine can feel like a headache even when the brain is otherwise uninjured. After appropriate trauma screening clears more serious concerns, evaluating these structures and restoring their function becomes a practical part of recovery.
How Accident Forces Load the Upper Neck
Rapid acceleration-deceleration—especially in rear-end impacts—forces the head into sudden flexion and extension. The small joints between the occiput, atlas (C1), and axis (C2), along with the four suboccipital muscles that stabilize them, absorb much of that motion. Ligaments can stretch, joint capsules can become inflamed, and the muscles can go into protective spasm. The result is often local tenderness, reduced rotation or extension, and pain that is provoked by sustained postures or specific movements.
Patients commonly describe the headache as starting at the skull base and worsening with neck motion or prolonged sitting. Some also notice stiffness when they first get out of bed or difficulty looking over their shoulder while driving. These clues point clinicians toward a mechanical contribution rather than a purely primary headache disorder.
Not every base-of-skull headache is cervicogenic, and not every post-collision headache is purely muscular. A thorough evaluation looks for:
Pain reproduced by sustained or repeated neck positions
Restricted upper cervical motion, especially rotation in flexion
Tenderness over the suboccipital muscles or upper cervical joints
Improvement when those structures are temporarily unloaded or treated
ICHD-3 criteria for cervicogenic headache require evidence that a cervical disorder is capable of producing the headache and that the two are linked in time or by response to treatment. Imaging findings alone (mild disc changes or degenerative joints) are not enough; many asymptomatic people show similar changes. The clinical examination, the timing after trauma, and the response to carefully selected care supply the stronger connection.
Non-maleficence requires that elective structural treatment wait until red flags have been ruled out. After a collision, the first priorities are neurological screening, assessment for cervical vascular injury when indicated, and imaging if progressive neurological signs, severe unrelenting pain, or other concerning features appear. Only after those steps does manual care or progressive rehabilitation proceed. This sequence protects the patient from delayed recognition of rare but serious complications while still allowing timely treatment of the far more common soft-tissue and joint findings.
Targeted Structural Support and Rehabilitation
When examination supports a mechanical driver, care focuses on restoring motion, reducing protective muscle guarding, and rebuilding endurance so the upper neck can tolerate daily postures again. Selected approaches may include:
Gentle joint mobilization or manipulation matched to the specific restricted segments
Soft-tissue techniques directed at the suboccipital group, upper trapezius, and deep neck flexors
Progressive deep-neck-flexor and postural endurance exercises
Education on workstation setup, sleep positioning, and gradual return to activity
Evidence summaries consistently list spinal manipulation and mobilization, together with therapeutic exercise, among the interventions with moderate support for cervicogenic headache (Bryans et al., 2011; Jull et al., 2002). The goal is not simply temporary relief; it is measurable improvement in range of motion, reduced provocation of headache with neck movement, and greater ability to maintain normal head-on-neck posture without fatigue.
Patients who also experience tension-type features or overlapping migraine symptoms may benefit from coordinated strategies discussed in the clinic’s stress-headache and integrated migraine resources. Structural work remains complementary, not a replacement, for medical evaluation when migraine criteria are met.
Bioethical Pillars in Practice
Beneficence is served by directing care at the structures that examination shows are contributing to the headache, rather than applying a one-size-fits-all protocol. Non-maleficence is protected by the clearance step already described and by the preference for non-invasive, drug-free options that lower the chance of long-term analgesic dependence or premature surgical consideration. Autonomy is strengthened when the patient understands the neck-to-headache connection: why certain postures flare the pain, what the examination findings mean, and how home exercises and posture changes fit into the plan. Shared records and clear explanations allow the patient and any legal counsel to see the same objective timeline.
What Makes the Clinic Unique
Dr. Alex Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic is one of the only clinics in El Paso that combines a dual-licensed soft-tissue specialist with a board-certified medical director under one roof.
Dr. Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, brings chiropractic structural evaluation together with advanced practice nursing scope, allowing objective digital range-of-motion measurements, soft-tissue assessment, and selected regenerative or photobiomodulation options when indicated.
Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine and serving as Medical Director, provides medical oversight for complex cases, laboratory interpretation, and coordination with outside physicians.
This dual-scope model produces co-signed notes that document both the mechanical findings and the medical context—documentation that supports both clinical recovery and medical-legal causation under the Texas Eggshell Rule.
Connecting Structural Findings to the Larger Clinical Framework
Integrated structural documentation—timed range-of-motion values, provocation findings, and progressive functional improvement—appears in the broader clinical framework at dralexjimenez.com. Attorneys and patients reviewing a file can see how upper-cervical joint and muscle findings were measured, how they changed with care, and how they relate to the original collision mechanics. That continuity reduces the chance that a defense examiner will successfully characterize the headache as unrelated or purely subjective.
Cross-links that expand on related topics include discussions of cervicogenic triggers, headache trigger points, and the full medical-legal causation guide available on the master site.
Practical Steps Patients Can Take
Note which movements or postures reliably change the headache and share that list at the evaluation.
Complete any recommended imaging or specialist referral promptly so that elective care can begin without delay.
Practice the specific postural and strengthening drills prescribed rather than generic stretches found online.
Keep a simple diary of headache days, neck stiffness, and activities that help or hinder; this record supports both treatment adjustments and any later legal documentation.
Most people with post-collision sub-occipital headaches improve when clinicians identify mechanical contributors early and address them with graded, evidence-aligned care. Careful screening, targeted structural treatment, and patient understanding of the neck-to-headache link lead to clearer recovery and more defensible documentation.
If your headaches began or worsened after a collision and are provoked by neck movement or posture, a dual-scope evaluation can clarify whether upper cervical joints and suboccipital muscles are contributing drivers and what the next safe steps look like.
References
Bryans, R., Descarreaux, M., Duranleau, M., Marcoux, H., Potter, B., Ruegg, R., Shaw, L., Watkin, R., & White, E. (2011). Evidence-based guidelines for the chiropractic treatment of adults with headache. Journal of Manipulative and Physiological Therapeutics, 34(5), 274–289. doi.org/10.1016/j.jmpt.2011.04.008
Headache Classification Committee of the International Headache Society (IHS). (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. doi.org/10.1177/0333102417738202
Jull, G., Trott, P., Potter, H., Zito, G., Niere, K., Shirley, D., Emberson, J., Marschner, I., & Richardson, C. (2002). A randomized controlled trial of exercise and manipulative therapy for cervicogenic headache. Spine, 27(17), 1835–1843. doi.org/10.1097/00007632-200209010-00004
Linking Specific I-10 and Loop 375 Force Vectors to Documented Changes in Daily Sitting and Standing Tolerance
After a rear-end or multi-vehicle impact on Interstate 10 or Loop 375, many patients leave the emergency room with imaging that shows disc height loss, annular changes, or mild herniation. Attorneys later face the familiar defense argument that the MRI looks “degenerative” and that range-of-motion numbers alone do not prove real impairment. What often decides the case is something simpler and more practical: whether the patient can still sit through a workday or stand long enough to complete ordinary tasks.
When clinic notes carefully connect the specific force vectors of those freeway collisions to measured drops in seated and standing endurance, the file moves beyond pictures and pure motion scores into documented, daily functional loss that juries and adjusters understand.
Why Highway Force Vectors Matter for Disc Cases
Highway collisions in El Paso generate distinctive loading patterns that differ from ordinary daily activity:
On I-10, high-speed rear impacts produce rapid axial compression combined with sudden flexion-extension through the lumbar spine.
On Loop 375, merging and lane-change impacts often add rotational and lateral shear forces.
These forces load the lower lumbar discs far beyond normal sitting or standing loads.
Disc tissue that may have shown age-related narrowing before the crash can still sustain acute annular strain or altered hydrostatic pressure, reducing its ability to tolerate sustained postures.
The clinical task is to document that change in endurance rather than rely solely on degrees of flexion or extension.
Lower Back Pain
Personal Injury
Auto Accident Injuries
Car Accident Specialist
Collision & Injury Dynamics
Med-Legal Corner
Lawyers
Herniated Disc
Chronic Back Pain
Spine Care
What Objective Notes Must Capture
Objective notes that capture this difference typically include three linked elements:
A clear mechanism description timed to the collision (for example: “The patient was a restrained driver stopped on I-10 near the Loop 375 interchange when struck from behind at highway speed; the lumbar spine underwent rapid axial compression and flexion”).
Baseline functional history obtained early: how long the patient could sit or stand before the crash for work, driving, or household tasks.
Serial timed measurements of current tolerance—how many continuous minutes of sitting or standing are possible before pain, numbness, or the need to change position forces a break.
These endurance times are recorded independently of digital range-of-motion numbers. A patient may regain near-normal ROM yet still be limited to 12–15 minutes of continuous sitting because of disc-related loading intolerance.
Why Endurance Data Adds Value Beyond ROM
Pure ROM does not capture sustained postural load. A disc that has lost height or developed an acute annular lesion can still allow a single movement through a full arc, yet fail under the constant compression of sitting or the prolonged axial load of standing. Notes that record both the highway force description and the timed endurance data give the attorney concrete evidence that the impairment is real, measurable, and linked to the event rather than to ordinary aging.
How Specific Force Vectors Translate into Daily Limits
I-10 Rear-End Impacts
Consider a typical I-10 rear-end scenario. The sudden deceleration compresses the L4-L5 and L5-S1 discs while the torso is driven into the seat. Pre-existing mild degeneration, common on imaging of asymptomatic adults, does not prevent acute aggravation under the Texas Eggshell Plaintiff rule.
Common documented changes include:
Before the crash: ability to sit through a full eight-hour shift with only brief breaks.
After the crash: continuous sitting limited to 15–20 minutes before radiating pain or stiffness requires standing.
Standing tolerance drops from several hours of intermittent work to 10–15 continuous minutes before the need to sit or lean.
These numbers are recorded at each visit, plotted over time, and co-signed by the dual-licensed team.
Loop 375 Merging and Lane-Change Collisions
Loop 375 collisions often involve more lateral or oblique forces. The notes describe the vector (“left-rear impact while merging onto Loop 375”) and then document corresponding asymmetric endurance limits—greater difficulty sitting with the trunk rotated or standing with weight shifted to one side. The same timed-sitting and timed-standing protocol captures the deficit. Because the measurements are simple, repeatable, and patient-reported under clinical observation, they survive cross-examination better than subjective pain scores alone.
Building the Serial Objective Record
Serial documentation typically follows a consistent sequence:
At the initial post-collision visit, record the mechanism in detail.
Pre-injury sitting and standing capacity is quantified from the patient’s history.
Current continuous tolerance is timed under observation.
Subsequent visits re-measure the same endpoints after treatment intervals.
Improvements or plateaus are noted, along with any residual gap between pre-injury and current capacity.
Digital ROM and imaging findings are included, but they are not treated as the sole proof of impairment.
Endurance data provide the real-world functional translation that imaging cannot provide on its own. This approach also supports future-care planning. When sitting tolerance remains limited, the notes can justify ergonomic modifications, graded activity progression, or continued non-surgical care aimed at restoring postural endurance rather than simply chasing degrees of motion.
Bioethical Integration of Functional Tracking
Beneficence is served by focusing care on functional restoration. The goal is not merely to increase ROM numbers but to lengthen the time the patient can sit or stand so that work, driving, and daily activities become possible again.
Non-maleficence is observed by relying on non-invasive measurement and conservative progression. Timed endurance tracking avoids unnecessary procedures when the documented functional deficit can be addressed through structural care, activity modification, and monitored recovery.
Autonomy is preserved because the patient actively tracks and owns the tolerance data. Simple logs or clinic-timed sessions give the patient a clear record they can share with counsel and use to judge their own progress.
What Makes This Clinic’s Documentation Different
Injury Medical Chiropractic and Functional Medicine Clinic is the only integrated practice in El Paso that combines a dual-licensed soft-tissue specialist with an internal-medicine medical director. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, focuses on the structural and soft-tissue findings, digital motion assessment, and functional endurance testing. Dr. Maria Guadalupe Cardenas, MD, serves as medical director, providing internal medicine oversight, risk stratification, and coordination of any needed medical diagnostics. Together, they produce co-documented notes that pair the specific I-10 or Loop 375 force description with measured changes in sitting and standing endurance. This dual-scope record meets both clinical and legal documentation standards.
These functional linkages are packaged inside medical-legal causation documentation standards at dralexjimenez.com. Related discussions of disc findings, pre-existing condition claims under the Eggshell rule, and practical sitting tolerance appear throughout the site, including pages on herniated disc care, low-back pain with sitting and standing, and post-collision recovery pathways.
Attorneys who need more than imaging to demonstrate real-world impairment after disc injury will find that timed sitting and standing endurance, when clearly linked to the documented highway force vectors, supplies the missing practical proof. The measurements are straightforward, the mechanism is specific to El Paso freeways, and the dual-licensure notes keep the entire record courtroom-ready.
References
Brinjikji, W., Luetmer, P. H., Comstock, B., Bresnahan, B. W., Chen, L. E., Deyo, R. A., Halabi, S., Turner, J. A., Avins, A. L., James, K., Wald, J. T., Kallmes, D. F., & Jarvik, J. G. (2015). Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology, 36(4), 811–816. doi.org/10.3174/ajnr.A4173
Li, J. Q., Kwong, W. H., Chan, Y. L., & Kawabata, M. (2022). Comparison of in vivo intradiscal pressure between sitting and standing in human lumbar spine: A systematic review and meta-analysis. Life, 12(3), 457. doi.org/10.3390/life12030457
Rohlmann, A., Claes, L., Bergmann, G., Graichen, F., Neef, P., & Wilke, H.-J. (2001). Comparison of intradiscal pressures and spinal fixator loads for different body positions and exercises. Ergonomics, 44(8), 781–794. doi.org/10.1080/00140130110047673
Wilke, H.-J., Neef, P., Caimi, M., Hoogland, T., & Claes, L. E. (1999). New in vivo measurements of pressures in the intervertebral disc in daily life. Spine, 24(8), 755–762. doi.org/10.1097/00007632-199904150-00005
Rainville, J., Sobel, J. B., Hartigan, C., & Wright, A. (2004). Sitting and standing tolerance in patients with chronic back pain: Comparison between physician prediction and covert observation. Archives of Physical Medicine and Rehabilitation, 85(5), 837–839. doi.org/10.1016/j.apmr.2003.08.095
Andersson, G. B. J., Ortengren, R., & Nachemson, A. (1974). Intradiscal pressure, intra-abdominal pressure and myoelectric back muscle activity related to posture and loading. Clinical Orthopaedics and Related Research, 103, 156–164. doi.org/10.1097/00003086-197409000-00014
Nachemson, A. L. (1966). The load on lumbar disks in different positions of the body. Clinical Orthopaedics and Related Research, 45, 107–122.
Texas Pattern Jury Charges: General Negligence & Intentional Personal Torts (PJC 28.8 series). (2020). State Bar of Texas.
Chiropractic rehabilitation offers a targeted approach to temporal headache. Learn how gentle adjustments and rehab exercises help address the root causes of temple pain.
Abstract
Temporal headaches represent a common yet complex form of head pain localized primarily to the temple regions, arising from diverse primary and secondary sources including tension-type mechanisms, migraine pathophysiology, cervicogenic referral from the upper cervical spine, temporomandibular joint dysfunction, and, in some cases, serious vascular conditions such as giant cell arteritis. These headaches frequently influence and are influenced by structures in the head, neck, and shoulders through shared neural pathways, muscular chains, and biomechanical relationships. Symptoms range from dull pressure and throbbing to sharp pain with neck stiffness, scalp tenderness, jaw discomfort, and, in severe secondary cases, vision changes or systemic signs. Comorbidities commonly include neck pain, shoulder girdle tension, anxiety, depression, sleep disturbances, fibromyalgia-like presentations, and, in older adults, polymyalgia rheumatica.
This educational post explores the physiological underpinnings of temporal headaches with emphasis on trigeminocervical convergence, central sensitization, myofascial trigger points, and vascular inflammation. It details how integrative chiropractic care, grounded in modern evidence-based research methods from leading investigators, addresses musculoskeletal contributors to temporal pain and related comorbidities affecting the head, neck, and shoulders. Spinal manipulation, joint mobilization, soft tissue techniques, therapeutic exercise, and multimodal approaches show particular benefit for cervicogenic and tension-related presentations by improving joint mobility, reducing nociceptive input, normalizing muscle tone, and modulating pain processing. Chiropractic care maintains a productive working relationship with non-surgical treatments including physical therapy, medical management, functional medicine strategies, and lifestyle interventions.
At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic in El Paso, Texas, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, collaborates closely with Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI 1164426749, Texas MD License J2933), who brings over 40 years of experience as an internist and serves as Medical Director and Collaborative Physician. This multidisciplinary model integrates chiropractic interventions with medical oversight, functional medicine assessments, personal injury rehabilitation, and related services to deliver comprehensive, non-surgical care. Clinical observations from the practice highlight the value of thorough differential diagnosis, red-flag screening, and coordinated treatment plans that prioritize patient safety and functional restoration.
Understanding Temporal Headaches and Their Relationship to the Head and Neck
Temporal headaches describe pain experienced predominantly in one or both temple areas. The term encompasses several distinct clinical entities rather than a single diagnosis. Primary headache disorders such as tension-type headache often produce a pressing or tightening sensation across the temples and forehead. Migraine attacks frequently involve unilateral temporal throbbing accompanied by associated features. Cluster headache characteristically presents with severe orbital or temporal pain. Secondary causes include cervicogenic headache, in which pain is referred from the upper cervical spine; temporomandibular joint disorders; and giant cell arteritis, an inflammatory vasculitis of medium and large arteries that classically affects the temporal arteries in individuals over age 50.
The anatomical and functional connections between the head and neck explain why temporal pain so commonly coexists with neck and shoulder complaints. The upper three cervical segments supply sensory innervation to structures that can generate referred pain into the temporal, frontal, and orbital regions. Sensory fibers from C1, C2, and C3 converge with trigeminal afferents in the trigeminocervical nucleus within the upper cervical spinal cord and caudal medulla. When nociceptive signals arise from cervical joints, ligaments, discs, or muscles, second-order neurons may interpret the input as originating from the head, producing the perception of temporal headache. This convergence-projection mechanism accounts for the clinical observation that cervical dysfunction can manifest primarily as head pain even when local neck symptoms remain relatively mild.
Muscular relationships further link the regions. The trapezius, sternocleidomastoid, suboccipital muscles, and temporalis form interconnected myofascial chains. Trigger points in these muscles refer pain into the temples. Prolonged forward head posture, common in modern occupational and screen-based activities, increases load on the cervical extensors and suboccipitals while altering temporomandibular mechanics, thereby contributing to both neck tension and temporal discomfort. Vascular structures such as the temporal artery course through the region and may become inflamed in giant cell arteritis, producing localized temporal pain, scalp tenderness, and systemic inflammatory signs.
Dr. Alexander Jimenez’s clinical observations at the El Paso practice consistently demonstrate that many patients presenting with temporal headaches also exhibit restricted upper cervical mobility, palpable joint dysfunction at C1-C2 or C2-C3, and myofascial tenderness in the neck and shoulder girdle. These findings align with the neuroanatomical basis of referred pain and underscore the importance of evaluating the entire cervicocranial complex rather than isolating the headache symptom.
Symptoms of Temporal Headaches
The symptomatic presentation of temporal headaches varies by underlying mechanism. In tension-type presentations, patients typically describe bilateral or bilateral-dominant pressure or band-like tightness centered around the temples. Intensity is usually mild to moderate. The pain is non-pulsating and is not aggravated by routine physical activity. Associated neck and shoulder muscle tightness is common, and patients often report increased symptoms with prolonged static postures.
Migraine-related temporal pain is more often unilateral, throbbing or pulsating in quality, moderate to severe in intensity, and aggravated by movement. Photophobia, phonophobia, nausea, or vomiting frequently accompany the headache. Some patients experience aura preceding the pain phase. Neck pain occurs in a substantial proportion of migraine sufferers both during and between attacks, reflecting shared central sensitization pathways.
Cervicogenic headache typically begins in the neck or occiput and radiates forward into the temporal region on the same side. The pain is usually non-throbbing and may be provoked or worsened by neck movement, sustained postures, or pressure over the upper cervical joints. Restricted cervical range of motion, particularly in rotation or extension, and reproduction of head pain with cervical provocation tests support the diagnosis. Shoulder girdle discomfort frequently coexists because of shared muscular and postural contributors.
Giant cell arteritis produces a new-onset, persistent temporal headache that is often unilateral and throbbing. Scalp tenderness, particularly over the temporal artery, is characteristic. Jaw claudication—pain in the jaw muscles during chewing—represents an important associated symptom. Visual disturbances ranging from transient monocular vision loss to permanent blindness constitute a medical emergency. Systemic features such as fever, fatigue, weight loss, and proximal muscle aching consistent with polymyalgia rheumatica are common. Because delayed treatment risks irreversible ischemic complications, any new temporal headache in a patient older than 50 years warrants urgent medical evaluation.
Temporomandibular joint-related temporal pain is usually accompanied by jaw clicking, limited mouth opening, or pain with chewing. Ear fullness or tinnitus may occur. The pain often intensifies with clenching or grinding.
Across these presentations, patients commonly report associated neck stiffness, shoulder tension, reduced concentration, sleep disruption, and decreased daily function. Dr. Jimenez notes in clinical practice that patients often underreport neck and shoulder symptoms until specifically questioned, highlighting the value of a comprehensive history and examination.
Comorbidities Associated with Temporal Headaches
Primary headache disorders exhibit well-documented comorbidity with psychiatric conditions. Meta-analytic data indicate elevated rates of depressive disorders and anxiety disorders among individuals with primary headaches. Shared neurobiological pathways involving serotonergic and dopaminergic systems, hypothalamic-pituitary-adrenal axis dysregulation, and central sensitization mediate this bidirectional relationship. Sleep disorders occur at high prevalence and further amplify headache frequency through disruption of restorative processes and increased inflammatory mediators.
Neck pain and cervical dysfunction constitute nearly universal comorbidities in both tension-type and cervicogenic presentations. Shoulder girdle myofascial pain and restricted thoracic mobility commonly accompany upper cervical involvement because of compensatory postural patterns. Fibromyalgia and widespread pain sensitization occur more frequently in patients with chronic headache than in the general population, reflecting overlapping central nervous system hyperexcitability.
Cardiovascular risk factors, including hypertension, show associations with certain primary headaches, particularly migraine. In giant cell arteritis, the condition itself represents a systemic vasculitis that may involve large vessels beyond the cranial circulation, raising the risk of aortic aneurysm, stroke, and ischemic complications. Polymyalgia rheumatica coexists in 40 to 60 percent of giant cell arteritis cases and produces proximal girdle stiffness and pain that can affect the neck and shoulders.
Medication-overuse headache develops in susceptible individuals who rely on frequent analgesic use, creating a cycle of rebound pain that complicates management of the original temporal symptoms. Personal injury and trauma histories, including motor vehicle collisions producing whiplash, frequently underlie the onset or exacerbation of cervicogenic temporal pain.
These comorbidities influence treatment planning. Addressing neck and shoulder dysfunction may reduce headache burden, while recognition of psychiatric or sleep comorbidities supports referral for concurrent management. At the El Paso clinic, the collaborative model allows simultaneous attention to musculoskeletal, medical, and lifestyle contributors.
Physiological Underpinnings of Temporal Headaches
Temporal pain arises and is maintained through peripheral and central mechanisms. In tension-type headache, peripheral myofascial nociception from pericranial muscles contributes to episodic attacks, while chronic forms involve central sensitization with lowered pain thresholds and impaired descending inhibition. Experimental studies demonstrate that noxious input from neck muscles can facilitate temporal muscle pain responses, illustrating segmental and supraspinal interactions.
Migraine pathophysiology centers on activation of the trigeminovascular system. Cortical spreading depression, when present, initiates a cascade of neurogenic inflammation and sensitization of meningeal and vascular nociceptors. The same trigeminocervical complex that mediates cervicogenic referral also participates in migraine, explaining the frequent neck involvement. Central sensitization amplifies pain signals and produces allodynia.
Cervicogenic headache rests on the anatomical convergence described earlier. Experimental stimulation of the C2-3 zygapophysial joint, the most common source, reproduces occipital and temporal pain in healthy volunteers. Inflammation or mechanical dysfunction of upper cervical structures generates ongoing nociceptive traffic that, through central sensitization of second-order neurons, lowers the threshold for subsequent inputs and perpetuates the headache. Muscle guarding and altered motor control further sustain the cycle.
Giant cell arteritis is driven by an antigen-driven T-cell and macrophage response within the vessel wall, leading to granulomatous inflammation, intimal hyperplasia, and luminal narrowing. Ischemia of the optic nerve or other tissues produces the characteristic visual and systemic features. The temporal artery is readily accessible for biopsy, yet imaging modalities such as ultrasound and PET-CT increasingly support diagnosis.
These mechanisms justify targeted interventions. Reducing nociceptive input from cervical joints and muscles can decrease central sensitization. Improving joint mobility and muscle function interrupts the peripheral drivers of referred pain. Medical management addresses inflammatory or vascular processes that mechanical therapies cannot modify.
El Paso, TX Chiropractic Migraine Treatment- Video
How Chiropractic Care Addresses Temporal Headaches and Related Comorbidities
Evidence-informed chiropractic management focuses primarily on cervicogenic and tension-type presentations in which cervical and myofascial dysfunction contribute substantially. A 2026 clinical practice guideline developed through an umbrella review and Delphi consensus strongly recommends spinal manipulative therapy for adults with cervicogenic headache, based on high-certainty evidence. For tension-type headache, the same guideline supports spinal manipulation within a multimodal program that includes joint mobilization, soft-tissue techniques, and exercise.
Spinal manipulation produces both biomechanical and neurophysiological effects. High-velocity, low-amplitude thrusts restore segmental mobility, reduce local inflammation, and stimulate mechanoreceptors that inhibit nociceptive transmission at the spinal and supraspinal levels. These effects can reduce convergence-driven pain referral into the temporal region. Clinical trials have shown reductions in headache days with dose-dependent responses; more visits within a defined period produce greater reductions in cervicogenic headache frequency than light-massage controls.
Soft-tissue techniques address myofascial trigger points in the suboccipital, cervical, and shoulder muscles that refer pain to the temples. Mobilization and therapeutic exercise improve endurance of the deep cervical flexors, scapular stabilizers, and postural muscles, thereby reducing mechanical stress on the upper cervical joints. Systematic reviews consistently show that multimodal programs combining these elements outperform isolated interventions.
For neck and shoulder comorbidities, the same interventions that relieve temporal pain also improve cervical range of motion, reduce muscle hypertonicity, and decrease shoulder girdle discomfort. Patients with coexisting anxiety or sleep disturbance often experience secondary benefits once pain intensity declines and function improves, although concurrent behavioral strategies may be required.
Chiropractic care is not indicated as primary treatment for giant cell arteritis or other serious secondary causes. In such cases, the role is supportive after medical diagnosis and initiation of appropriate pharmacologic therapy, addressing any concurrent musculoskeletal contributors under collaborative medical oversight. Screening for red flags—new headache after age 50, visual changes, jaw claudication, fever, or progressive neurological signs—is essential in every initial evaluation.
Dr. Jimenez’s clinical approach incorporates these evidence-based elements while individualizing care according to examination findings. Patients frequently report reduced temporal pain intensity, fewer headache days, and improved neck and shoulder mobility following a course of multimodal chiropractic care combined with home exercise and postural education.
Integrative Chiropractic Care Within Non-Surgical Treatment Frameworks
Chiropractic interventions integrate readily with other non-surgical modalities. Physical therapy programs emphasizing graded exercise and motor control training complement spinal manipulation by consolidating gains in strength and endurance. Medical management under internal medicine oversight provides pharmacologic options for migraine prevention or acute treatment when indicated, while monitoring for medication overuse. Functional medicine strategies address inflammatory load, nutrient status, sleep quality, and stress physiology that can amplify central sensitization.
Acupuncture and dry needling, when evidence supports them for the specific presentation, may be incorporated. Lifestyle counseling covering ergonomics, hydration, regular physical activity, and stress-reduction techniques forms part of the long-term plan. In personal-injury contexts, the coordinated team documents functional deficits, delivers rehabilitation, and communicates with other providers to support recovery.
The working relationship is bidirectional. Chiropractic care can reduce reliance on analgesics for musculoskeletal contributors, while medical evaluation rules out serious pathology and manages systemic comorbidities. Shared decision-making ensures each component of care fits the patient’s diagnosis and preferences.
The Multidisciplinary Team at Injury Medical Clinic PA
Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas. With more than 40 years of experience as an internist, she provides medical oversight, including a comprehensive history and physical examination, laboratory evaluation, imaging interpretation, and pharmacologic management when required. Her role ensures that potentially serious causes of temporal headache, such as giant cell arteritis or other secondary headaches, receive timely diagnosis and treatment.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, delivers the chiropractic and functional medicine components. Dual licensure as a chiropractor and advanced practice registered nurse facilitates seamless integration of musculoskeletal interventions with medical assessment. Functional medicine evaluations explore root contributors such as inflammatory markers, hormonal balance, and lifestyle factors that may perpetuate headache and related pain.
The team coordinates personal injury care, rehabilitation, nutritional counseling, and related services. Patients benefit from a single coordinated plan rather than fragmented referrals. Clinical observations indicate that this model improves diagnostic accuracy, enhances patient adherence, and supports better functional outcomes for individuals with temporal headaches and neck or shoulder comorbidities.
Clinical Protocols and Reasoning
Initial evaluation begins with a detailed history that screens for red flags and characterizes the headache pattern, followed by cervical and temporomandibular examination, neurological screening, and postural assessment. When giant cell arteritis is suspected, initiate immediate medical referral or co-management before any manipulative therapy.
For appropriate candidates, treatment may include specific upper cervical and thoracic manipulation to restore mobility and reduce nociceptive drive, soft-tissue work to deactivate trigger points, and progressive exercise to retrain deep neck flexors and scapular stabilizers. The rationale is that mechanical and neurophysiological improvements at the source of referred pain will reduce temporal symptoms while also addressing neck and shoulder comorbidities. Frequency and duration are guided by response and the dose-response relationships reported in clinical trials.
Ongoing reassessment monitors headache frequency, intensity, cervical function, and overall disability. Education empowers patients to maintain gains through self-management strategies. When comorbidities require additional expertise, providers arrange coordinated referral or concurrent care.
Conclusion
Temporal headaches arise through multiple mechanisms that frequently involve the head, neck, and shoulders. Accurate differential diagnosis, recognition of comorbidities, and an integrative approach that combines evidence-based chiropractic care with medical oversight and other non-surgical treatments offer a comprehensive pathway to reduced pain and improved function. At Injury Medical Clinic PA in El Paso, the collaboration between Dr. Jimenez and Dr. Cardenas exemplifies this model, prioritizing patient safety, physiological restoration, and long-term wellness.
Trager, R. J., Daniels, C. J., Hawk, C., Taylor, D. N., Walters, S. A., Price, M. R., Anderson, K. R., Crivelli, L. S., Mooring, S. A., Staab, C. A., & Oakley, C. B. (2026). Chiropractic management of adults with cervicogenic or tension-type headaches: Development of a clinical practice guideline. Journal of Integrative and Complementary Medicine. journals.sagepub.com/doi/10.1177/27683605251397769
Haas, M., Bronfort, G., Evans, R., Schulz, C., Vavrek, D., Takaki, L., Hanson, L., Leininger, B., & Neradilek, M. B. (2018). Dose-response and efficacy of spinal manipulation for care of cervicogenic headache: A dual-center randomized controlled trial. The Spine Journal, 18(10), 1741–1754.
Bogduk, N., & Govind, J. (2009). Cervicogenic headache: An assessment of the evidence on clinical diagnosis, invasive tests, and treatment. The Lancet Neurology, 8(10), 959–968.
Capuano, A., et al. (as representative of comorbidity literature). Comorbidities of primary headache disorders: A literature review with meta-analysis. (2021).
SEO Tags
temporal headaches, temple headaches, cervicogenic headache, giant cell arteritis, chiropractic care for headaches, neck pain and headaches, integrative chiropractic El Paso, Dr Alex Jimenez, Injury Medical Clinic PA, non-surgical headache treatment, head and neck pain, shoulder pain comorbidities, functional medicine headaches, personal injury rehabilitation El Paso
Neck Tension and Headaches After a Rear-End Collision: What Is the Connection?
Abstract
After a rear-end collision, patients often notice neck tightness, stiffness, tenderness at the base of the skull, and headaches. These symptoms can occur together because rapid acceleration and deceleration can strain muscles, ligaments, joints, and other structures surrounding the cervical spine. However, tight neck muscles do not automatically prove that the neck is the sole source of someone’s headache. A patient may have a tension-type headache with pericranial tenderness, a whiplash-related headache, a cervicogenic headache, migraine-like symptoms, or multiple overlapping problems. A thorough history, neurological screening, cervical movement testing, muscle examination, and functional assessment help clinicians identify what may be contributing to the symptoms and how to safely perform rehabilitation.
Why Can a Rear-End Collision Affect Both the Neck and the Head?
Imagine sitting at a stoplight when another vehicle suddenly strikes the back of your car.
The vehicle moves forward before your body and head have had time to react normally. The seat pushes the torso forward while the head rapidly accelerates and decelerates. This sudden movement can place mechanical stress on the cervical muscles, joints, ligaments, discs, and surrounding soft tissues.
This injury pattern is commonly called whiplash.
Clinically, whiplash is defined as a sudden acceleration-deceleration movement of the head and neck. It is most often associated with motor vehicle collisions, particularly rear-end impacts (Headache Classification Committee of the International Headache Society [IHS], 2018).
Neck pain and headache are among the most frequently reported symptoms following whiplash. A systematic review and meta-analysis found that headache was reported in approximately 60% of patients during the first seven days after whiplash in the included non-population-based studies, although results varied substantially between studies (Al-Khazali et al., 2020).
Patients may describe:
Neck stiffness or tightness
Reduced ability to turn the head
Upper trapezius soreness
Tenderness at the base of the skull
Shoulder discomfort
Pressure around the forehead or temples
Headache beginning in the back of the head
Pain that increases after prolonged sitting or computer work
These symptoms deserve evaluation, but their presence does not automatically identify one specific headache disorder.
Tight Neck Muscles Do Not Automatically Mean “Cervicogenic Headache”
This distinction is one of the most important points for patients after an accident.
A clinician may examine the upper trapezius, sternocleidomastoid, splenius, suboccipital, and other muscles surrounding the head and cervical spine and find significant tenderness.
That finding matters.
But tenderness alone does not establish that a cervical joint, disc, muscle, or nerve is the direct source of the headache.
The International Classification of Headache Disorders recognizes pericranial tenderness as a finding that can accompany tension-type headache. In fact, the International Classification of Headache Disorders specifically classifies tension-type headache into forms with and without increased pericranial tenderness (IHS, 2018).
Typical tension-type headache characteristics may include:
A pressing or tightening sensation
Pain on both sides of the head
Mild to moderate intensity
Pain that is not significantly aggravated by ordinary physical activity
Absence of vomiting
Tenderness in muscles around the scalp, neck, or shoulders in some patients
Therefore, someone can have tight cervical muscles and still have a headache pattern that is more consistent with tension-type headaches.
The reverse is also true: a patient can have cervical dysfunction contributing significantly to head pain.
The job of the examination is to determine which explanation fits the evidence, not to diagnose based on one tender muscle.
What Is a Headache Attributed to Whiplash?
Headaches beginning after a collision can also fall into a trauma-related category.
According to ICHD-3, an acute headache attributed to whiplash occurs when a headache develops within seven days of a whiplash injury and lasts less than three months. When a qualifying headache continues beyond three months, it may meet the criteria for persistent headache attributed to whiplash (IHS, 2018).
Importantly, “headache attributed to whiplash” describes the relationship between the trauma and development of the headache. It does not mean every post-whiplash headache has exactly the same biological mechanism or pain pattern.
After an accident, patients may experience headaches resembling:
Tension-type headache
Migraine
Cervicogenic headache
Occipital pain
Post-traumatic headache following head injury
Mixed headache patterns
Dr. Jimenez’s Integrated Headache Management guide discusses why post-injury headaches should be evaluated as individual clinical patterns rather than treated as one universal condition.
When Is a Headache Considered Cervicogenic?
A cervicogenic headache has a more specific meaning.
It is a secondary headache attributed to a disorder or lesion involving structures within the cervical spine or surrounding soft tissues that can cause headaches.
ICHD-3 requires more than simply finding neck pain.
Evidence supporting cervical causation can include at least two findings, such as:
The headache beginning in close relationship to the cervical disorder
Improvement in the headache as the cervical condition improves
Reduced cervical range of motion with significant worsening of the headache during provocative movements
Relief following a diagnostic block of an implicated cervical structure or nerve supply
(IHS, 2018).
This is why saying “your neck is tight, so your headache comes from your neck” is too simplistic.
Neck tenderness can be part of the clinical picture without proving cervicogenic headache.
Cervical Movement Assessment After a Collision
One useful part of a post-collision examination is assessing cervical spine movement.
The clinician may assess:
Flexion
Extension
Left and right rotation
Side bending
Movement symmetry
Pain during movement
Muscle guarding
Whether a particular movement reproduces the patient’s familiar headache
Research supports the importance of these functional findings. People with whiplash-associated disorders can demonstrate greater restrictions in cervical movement and other functional impairments compared with people experiencing non-traumatic neck pain (Anarte-Lazo et al., 2021).
However, reduced motion still needs interpretation.
A patient who is frightened, sore, inflamed, or experiencing protective muscle guarding may move less even when no single cervical structure has been established as the headache generator.
That is why range-of-motion testing is combined with history, neurological findings, palpation, orthopedic testing, functional assessment, and imaging when clinically necessary.
Upper Trapezius and Suboccipital Tenderness
Two areas frequently sore after a collision are the upper trapezius and suboccipital muscles.
The upper trapezius extends across the upper back, shoulder, and neck. It helps stabilize and move the shoulder girdle and cervical region.
The suboccipital muscles are smaller muscles located beneath the skull. They contribute to fine control of upper cervical movement and head position.
Following trauma, these muscles may become painful, guarded, fatigued, or tender.
Muscular tenderness can influence how comfortable a person feels moving the neck and may contribute to the overall pain experience. Pericranial tenderness is also well recognized in tension-type headache (IHS, 2018).
But palpation is only one part of the diagnostic process.
Safe Rehabilitation Is More Than Loosening Tight Muscles
Treatment after whiplash should not simply consist of repeatedly working on whichever muscle feels tight.
The bigger goal is restoring function.
Depending upon the examination and stage of recovery, rehabilitation may gradually address:
Comfortable cervical range of motion
Deep cervical muscle control
Shoulder and scapular stability
Posture
Cervical endurance
Coordination
Strength
Balance and proprioception
Tolerance for work and daily activities
Research continues to support appropriately prescribed exercise as part of whiplash rehabilitation. A 2024 systematic review and meta-analysis found guided neck-specific exercise produced greater improvements in neck pain and disability than different or unguided exercise approaches in the studies analyzed, although individual results varied (Muñoz Lazcano et al., 2024).
A newer 2026 systematic review likewise concluded that therapeutic exercise may improve pain and disability compared with minimal intervention in chronic whiplash-associated disorders, while emphasizing that certainty of evidence remains limited (Ferlito et al., 2026).
Chiropractic care may be one component of a broader musculoskeletal rehabilitation plan when examination findings indicate appropriate treatment and no contraindications exist.
Depending on the diagnosis, care may involve:
Gentle joint mobilization
Chiropractic manipulation when clinically appropriate
Soft-tissue treatment
Mobility exercises
Cervical stabilization
Postural rehabilitation
Progressive strengthening
Patient education
Home exercises
The key principle is that treatment should follow the diagnosis, rather than assuming every post-accident headache requires a cervical adjustment.
For example, evidence supporting spinal manipulation for uncomplicated tension-type headache is different from evidence involving a patient with an appropriately diagnosed cervical musculoskeletal problem. Dr. Jimenez’s published chiropractic headache treatment guidelines similarly emphasize matching treatment to the headache classification rather than treating all headaches identically.
This approach supports both beneficence and non-maleficence: provide treatment that may help while avoiding unnecessary intervention.
Why Multidisciplinary Evaluation Matters in El Paso
Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic uses a multidisciplinary structure that is unusual among traditional single-discipline injury clinics in El Paso.
The clinic includes Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician who serves as Medical Director and Collaborative Physician, and Dr. Alex Jimenez, DC, APRN, FNP-BC, whose dual chiropractic and advanced-practice nursing background includes evaluating musculoskeletal and soft-tissue injuries. This structure places the practice among a relatively small group of El Paso clinics that can coordinate chiropractic physical medicine, nurse-practitioner evaluation, rehabilitation, medical oversight, diagnostic assessment, and related integrative treatment within the same injury-care environment.
That coordination becomes especially useful when a post-accident headache does not fit neatly into one category.
A patient may need cervical rehabilitation.
Another may require medical evaluation.
Another may have migraine features.
Another may show neurological symptoms requiring referral.
The goal is not to make every patient fit the same treatment protocol. It is to identify the most likely contributing factors and help the patient make informed decisions about appropriate care.
The Most Important Question Is Not “Are My Neck Muscles Tight?”
It is:
Why am I having this headache?
After a rear-end collision, neck tension, suboccipital tenderness, reduced cervical movement, and headache commonly occur together. Research confirms that neck pain and headache are common after whiplash (Al-Khazali et al., 2020).
But symptoms occurring together do not automatically prove that one symptom completely causes the other.
A careful evaluation asks better questions:
When did the headache begin?
Was there a head impact?
Where is the pain located?
Does neck movement reproduce it?
Is cervical motion restricted?
Are neurological findings present?
Are there migraine-like symptoms?
Are the muscles tender?
Does improving cervical function also improve the headache?
Is another diagnosis more appropriate?
That approach respects the patient’s autonomy and produces a more defensible clinical picture.
For an example of how collision mechanics, examination findings, rehabilitation, and medical coordination can be followed over time, see Dr. Jimenez’s rear-end whiplash clinical case study.
Ultimately, the goal is not simply to “release tight muscles.” It is to understand what happened, determine what structures and systems may be involved, restore safe movement, improve function, and select care based on clinical findings rather than assumptions.
Medical Disclaimer: This article is intended for educational purposes and is not a substitute for individualized medical diagnosis or treatment. New, severe, rapidly worsening, or neurologically complicated headaches following trauma should receive appropriate medical evaluation.
How Spinal Decompression and Targeted Injections Are Justified When Causation Isolates Traumatic Disc Injury
When an El Paso attorney faces a defense that labels a lumbar disc herniation “just degenerative,” the case often turns on whether the medical record shows the collision’s force vectors produced a measurable, trauma-related change rather than ordinary aging. At Injury Medical Clinic PA, dual-licensure documentation links the mechanics of an I-10 or Loop 375 rear-end impact to specific MRI findings. This supports non-surgical spinal decompression and carefully selected injections as medically necessary future care that restores structure while reducing the chance of surgery.
Isolating Traumatic Disc Injury Through Force-Vector Correlation
Consider a 42-year-old warehouse supervisor stopped on Loop 375 when a delivery truck strikes from behind. Within days, he develops sharp low-back pain radiating into the left leg. Pre-accident records show occasional stiffness but no radicular symptoms and no prior MRI. The post-collision MRI reveals:
An L4–L5 left paracentral protrusion
A high-intensity zone in the annulus
Mild disc-height loss
Early Modic Type 1 endplate changes
Flexion-extension radiographs demonstrate increased translation consistent with the sudden flexion-compression and shear forces of rapid deceleration. These findings differ from the diffuse, multilevel, osteophyte-lined degeneration that develops over years.
Force-vector correlation starts with the collision itself. A typical freeway rear-end produces a rapid change in velocity that loads the lumbar spine in combined flexion, compression, and axial rotation. Published biomechanical work shows that relatively modest g-forces can exceed the failure thresholds of annular fibers, especially when the occupant is seated with the lumbar spine in slight flexion (Panjabi et al., 2004; Krafft et al., 2002).
The resulting changes typically include:
Annular disruption and nuclear migration appearing as a focal protrusion or extrusion whose location matches the direction of force
Disc-height reduction and increased segmental motion on digital flexion-extension films
New neurologic findings such as a positive straight-leg raise, reduced reflex, or dermatomal sensory change
When these objective changes are dated to the collision and correlated with the patient’s history, the record distinguishes traumatic aggravation from pre-existing degeneration under the Texas Eggshell Plaintiff Rule. Dual-scope notes record both the soft-tissue and structural measurements performed by Dr. Alex Jimenez, DC, APRN, FNP-BC, and the medical risk stratification and co-signature provided by Dr. Maria Guadalupe Cardenas, MD, Medical Director.
Why Spinal Decompression Is Justified Once Causation Is Isolated
With the traumatic disc injury isolated, the rationale for non-surgical spinal decompression becomes clear. Controlled, computer-guided traction lowers intradiscal pressure, creates negative pressure within the disc space, and improves nutrient diffusion into the damaged annulus and nucleus (Apfel et al., 2010; Choi et al., 2015). Clinical series show measurable increases in disc height and reductions in leg pain after structured protocols lasting several weeks.
At the clinic, protocols are individualized:
Supine positioning for older or flexion-sensitive patients
Prone positioning for younger patients with posterior or posterolateral herniations
Progressive force and cycle increases once tolerance is established
Serial digital range-of-motion and functional testing document objective improvement. This creates a longitudinal record that supports both clinical progress and the medical necessity of continued or future decompression sessions. Because the therapy is non-invasive and drug-free, it aligns with the duty of non-maleficence by delaying or avoiding the risks of open surgery while still addressing the structural lesion the trauma produced.
Role of Targeted Injections in the Future-Care Plan
Targeted injections enter the plan only when objective findings indicate that additional local intervention is required to control inflammation or facilitate active recovery. Under the collaborative direction of Dr. Cardenas and Dr. Jimenez, options may include:
Image-guided epidural or selective nerve-root injections for persistent radicular pain
Regenerative approaches such as platelet-rich plasma when the dual-scope evaluation supports their use
Each injection is justified by the same force-vector and imaging correlation that established the traumatic disc injury. The procedure is not offered simply because a patient reports pain. Detailed notes record:
The clinical rationale
The imaging target
The patient’s informed consent
The functional response
This dual-provider documentation satisfies Colossus-style review criteria and supplies the clear mechanism-to-treatment link that defense experts frequently challenge.
Bioethical Pillars Guiding the Approach
The clinic’s decisions rest on three core principles:
Beneficence: Care focuses on restoring disc height, reducing neural compression, and returning the patient to work and daily activities through structural treatment rather than symptom suppression alone.
Non-Maleficence: We use non-surgical decompression and carefully selected injections first, lowering the risks of anesthesia, infection, and failed back surgery.
Autonomy: Patients receive a plain-language explanation of how the collision forces produced the MRI changes and how the chosen treatments address those specific changes. The clinic documents shared decision-making, and patients remain free to coordinate with any other treating physicians.
What Makes the Clinic Unique in El Paso
What makes Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic unique is the combination of a board-certified internal medicine medical director, Dr. Maria Guadalupe Cardenas, MD, and a dual-licensed soft-tissue specialist, Dr. Alex Jimenez, DC, APRN, FNP-BC. The clinic is one of the only practices in El Paso, Texas, that integrates computer-guided spinal decompression, advanced imaging correlation, and selected injection therapies under a single dual-licensure team. This produces records that simultaneously guide care and withstand legal scrutiny.
Value for Attorneys and Patients
Attorneys reviewing these files receive a coherent package that includes:
Force-vector analysis matched to MRI morphology
Serial objective measurements
Dual-provider co-signatures
A future-care plan listing decompression protocols and any indicated injections with clear medical necessity
By isolating the traumatic disc injury through precise force-vector and imaging correlation, then matching that injury to non-surgical decompression and targeted injections under dual-licensure oversight, the clinic supplies both the patient and the attorney with a defensible path that prioritizes structural restoration while minimizing unnecessary risk.
References
Apfel, C. C., Cakmakkaya, O. S., Martin, W., Richmond, C., Macario, A., George, E., Schaefer, M., & Pergolizzi, J. V. (2010). Restoration of disk height through non-surgical spinal decompression is associated with decreased discogenic low back pain: A retrospective cohort study. BMC Musculoskeletal Disorders, 11, Article 155. doi.org/10.1186/1471-2474-11-155
Choi, J., Lee, S., & Hwangbo, G. (2015). Influences of spinal decompression therapy and general traction therapy on the pain, disability, and straight leg raising of patients with intervertebral disc herniation. Journal of Physical Therapy Science, 27(2), 481–483. doi.org/10.1589/jpts.27.481
Krafft, M., Kullgren, A., Ydenius, A., & Tingvall, C. (2002). Influence of crash severity on various whiplash injury symptoms: A study based on real-life rear-end crashes with recorded crash pulses. In Proceedings of the 19th International Technical Conference on the Enhanced Safety of Vehicles (Paper No. 05-0363).
Panjabi, M. M., Ito, S., Pearson, A. M., & Ivancic, P. C. (2004). Injury mechanisms of the cervical intervertebral disc during simulated whiplash. Spine, 29(11), 1217–1225. doi.org/10.1097/00007632-200406010-00011
Multidisciplinary chiropractic care offers targeted relief for alcohol-induced conditions. Explore non-invasive approaches that support recovery and improve quality of life.
Introductory Abstract
Public awareness that regular alcohol consumption raises the risk of developing cancer later in life has rebounded to 58 percent of U.S. adults, according to a nationally representative poll conducted by the Annenberg Public Policy Center of the University of Pennsylvania from September 22 to October 5, 2026 (Thompson, 2026). This figure sits five percentage points higher than February 2026 levels and roughly matches the 56 percent awareness recorded in February 2025, shortly after the former U.S. Surgeon General issued an advisory establishing a causal link between alcohol and at least seven types of cancer. Ongoing media coverage of research showing alcohol-related cancer deaths more than doubling over three decades has helped restore this knowledge, even as 24 percent of Americans remain unsure and 17 percent incorrectly believe no link exists. Confusion has been fueled in part by the 2025-2030 Dietary Guidelines for Americans, which dropped explicit cancer warnings while still advising limits on drinking for overall health.
This educational post, written by Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, walks readers through the latest evidence-based findings on alcohol as a carcinogen, the symptoms and comorbidities it can affect, and the physiological pathways involved. It then explains what chiropractic care is and how integrative, multidisciplinary non-surgical treatments work hand in hand with medical oversight. At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, Dr. Jimenez collaborates with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933), who serves as Medical Director and Collaborative Physician with more than 40 years of experience as an internist. The post details how their team integrates chiropractic care, functional medicine, personal injury care, rehabilitation, and related services to address musculoskeletal pain and its comorbidities. Readers will see how chiropractic adjustments, soft-tissue work, and guided rehabilitation reduce pain, restore function, and support whole-person wellness, and how these approaches can become a sustainable part of a health routine. The narrative draws on modern research methods and clinical observations to make complex science accessible.
Understanding the Rebound in Public Awareness of Alcohol’s Cancer Risk From the 2026 Annenberg Poll
Nearly six in ten Americans now recognize that regular drinking increases the odds of developing cancer later in life. The Annenberg Science and Public Health survey of 1,842 U.S. adults, conducted with a margin of error of plus or minus 3.2 percentage points, found 58 percent awareness (Annenberg Public Policy Center, 2026). This rebound follows a dip to 53 percent in February 2026 and returns knowledge close to the February 2025 level of 56 percent. Overall awareness stands 18 percentage points higher than the 40 percent recorded when the question was first asked in September 2024.
Laura Gibson, senior data analyst at the Annenberg Public Policy Center, observed that ongoing media coverage plays an important role in amplifying the general public’s awareness of health risks (Thompson, 2026). Shortly before the October survey, University of Miami researchers reported that alcohol-related cancer deaths had more than doubled over three decades. Coverage of that finding, combined with the lasting impact of the January 2025 Surgeon General advisory, helped the numbers recover even though the newer Dietary Guidelines removed explicit language about cancer.
The advisory by former Surgeon General Dr. Vivek Murthy stated that alcohol consumption is the third leading preventable cause of cancer in the United States, after tobacco and obesity, contributing to about 100,000 cases and 20,000 deaths annually (Office of the Surgeon General, 2025). It established a causal relationship for at least seven types of cancer regardless of whether the drink is beer, wine, or spirits. Risk rises with total exposure, and for some cancers the increase begins at levels many people consider moderate—one or fewer drinks per day.
Despite the rebound, more than four in ten Americans still do not recognize the link. Twenty-four percent are unsure, and 17 percent believe alcohol does not affect cancer risk. This gap matters clinically because patients who do not connect drinking with long-term disease risk may continue patterns that also slow musculoskeletal healing, disrupt sleep, and increase inflammation. At clinics that treat both injury and systemic health, this awareness becomes part of the intake conversation.
How Alcohol Acts as a Carcinogen and the Seven Types of Cancer Linked to Drinking
Alcohol is classified as a Group 1 carcinogen by the International Agency for Research on Cancer. Observational, biological, and genetic studies have confirmed a causal link at seven sites: female breast, colorectum, esophagus, liver, oral cavity (mouth), pharynx (throat), and larynx (voice box) (Office of the Surgeon General, 2025). In 2019, an estimated 96,730 alcohol-related cancer cases occurred in the United States, with the largest share being breast cancer in women (approximately 44,180 cases, or 16.4 percent of total breast cancers that year).
Ethanol’s primary metabolite is acetaldehyde, a highly reactive compound that forms DNA adducts and interferes with DNA repair. When acetaldehyde accumulates—especially in individuals with genetic variants that slow its clearance—it promotes mutations. Alcohol also generates reactive oxygen species that damage cellular membranes and DNA, creating oxidative stress. Chronic low-grade inflammation follows, elevating cytokines that support a microenvironment favorable to tumor growth. In the liver, repeated injury leads to fibrosis and cirrhosis, which themselves raise hepatocellular carcinoma risk. In the breast, alcohol increases circulating estrogen levels, stimulating hormone-sensitive tissue. In the upper aerodigestive tract, alcohol acts as a solvent that enhances the absorption of other carcinogens, such as those from tobacco.
Dose matters. Two drinks per day is estimated to produce about five additional cancers per 100 women and three additional cancers per 100 men compared with abstinence (Office of the Surgeon General, 2025). Even lower intakes carry measurable risk for breast, mouth, and throat cancers. These mechanisms operate independently of any musculoskeletal complaint. Yet, they intersect with pain management because patients seeking relief for back or joint pain may use alcohol for its short-term sedative effect, unknowingly compounding long-term risk.
Symptoms and Comorbidities of Alcohol Related Cancer Risk Affecting the Whole Body
Symptoms of alcohol-related cancers vary by site but often include persistent pain, unexplained weight loss, fatigue, difficulty swallowing, changes in bowel habits, or a new mass. Comorbidities amplify both cancer risk and musculoskeletal burden. Obesity, diabetes, and alcoholic liver disease raise the chance of more advanced disease and poorer survival (Abraham et al., 2025). Alcoholic myopathy produces proximal muscle weakness and wasting through suppressed protein synthesis and mitochondrial dysfunction. Bone mineral density declines because alcohol inhibits osteoblast activity, increasing osteoporosis and fracture risk. Peripheral neuropathy from toxic effects and nutritional deficiency (especially thiamine) causes burning pain, numbness, and gait instability that can be mistaken for radiculopathy.
Sleep architecture suffers. Alcohol shortens sleep onset yet suppresses REM early, and fragments sleep later, reducing restorative deep sleep when growth hormone peaks (National Institute on Alcohol Abuse and Alcoholism, 2026). Next-day pain sensitivity rises, muscle tension increases, and tissue repair slows. Medication interactions further complicate care: alcohol potentiates opioid sedation and respiratory depression, heightens acetaminophen hepatotoxicity, and increases gastrointestinal bleeding risk with NSAIDs. These overlapping problems create a cycle in which pain drives drinking, drinking worsens healing and cancer risk, and both feed systemic inflammation.
Chronic pain and alcohol use disorder frequently co-occur. Shared central nervous system mechanisms involving reward and stress pathways mean that each condition can worsen the other (Maleki et al., 2024). Musculoskeletal pain, in particular, is both a consequence and a driver of heavier drinking. Patients may report that alcohol “takes the edge off” stiffness, only to awaken with greater fatigue and tighter muscles.
Physiological Mechanisms Behind Alcohol’s Impact on Cancer and Musculoskeletal Health
Ethanol is metabolized primarily by alcohol dehydrogenase to acetaldehyde, then by aldehyde dehydrogenase to acetate. When capacity is exceeded, acetaldehyde binds DNA and proteins, forming adducts that mutate genes regulating cell growth. Cytochrome P450 2E1 induction further generates free radicals, depleting glutathione and amplifying oxidative damage. Inflammatory signaling via NF-κB elevates TNF-α, IL-6, and other cytokines that promote angiogenesis and inhibit apoptosis.
In skeletal muscle, alcohol suppresses the Akt/mTOR pathway that drives protein synthesis while activating degradation pathways involving myostatin and ubiquitin ligases. Mitochondrial dysfunction reduces ATP production, leading to weakness and delayed repair after strain or injury. In bone, osteoblast differentiation and collagen synthesis are impaired, shifting remodeling toward resorption. Tendon and ligament collagen remodeling is disrupted, weakening the extracellular matrix. In the nervous system, direct toxicity plus B-vitamin deficiency demyelinate peripheral nerves, producing the stocking-glove sensory loss of alcoholic neuropathy.
These same processes delay recovery from soft-tissue or spinal injury. Growth factors needed for angiogenesis and cell migration are suppressed, and the inflammatory phase of healing is prolonged rather than resolved. Clinically, patients who continue drinking during rehabilitation often show slower gains on functional measures such as the Oswestry Disability Index and greater night pain. The reasoning for addressing alcohol is therefore both oncologic and orthopedic: reducing exposure lowers mutation burden and simultaneously restores the metabolic environment required for musculoskeletal repair.
What Chiropractic Care Is and How It Fits Into Multidisciplinary Non-Surgical Treatment
Chiropractic care is a non-surgical, hands-on discipline focused on diagnosing, treating, and preventing neuromusculoskeletal disorders, particularly those involving the spine and extremities. Doctors of Chiropractic use spinal and joint adjustments—controlled, specific forces applied to restricted segments—to restore mobility, reduce abnormal afferent input, and decrease protective muscle spasm. Soft-tissue techniques, therapeutic exercise, and patient education complement the adjustment. The goal is to improve joint mechanics, normalize proprioceptive signaling, and allow the nervous system to down-regulate pain.
In an integrative setting, chiropractic care is not practiced in isolation. It follows medical screening for red-flag conditions (fracture, infection, malignancy, progressive neurologic deficit) and is coordinated with functional medicine assessments that examine nutrition, inflammation, and metabolic contributors. Non-surgical treatments such as spinal decompression, acupuncture, and progressive loading programs work alongside adjustments because each addresses a different layer of the same problem: mechanical restriction, soft-tissue fibrosis, and deconditioning. The clinical reasoning is that pain is rarely purely structural; it is maintained by a combination of joint dysfunction, muscle guarding, inflammatory mediators, and central sensitization. Addressing multiple layers simultaneously produces more durable improvement than any single modality.
The Collaborative Team at Injury Medical Clinic PA: Dr. Jimenez and Dr. Cardenas Working Together
At Injury Medical Clinic PA in El Paso, Texas, the multidisciplinary model places medical direction and collaborative physician oversight beside chiropractic expertise. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine with more than 40 years of experience, serves as Medical Director and Collaborative Physician. Her role includes reviewing systemic red flags, managing internal-medicine comorbidities, and providing the medical authority required for advanced diagnostics or referral when needed. Dr. Alexander Jimenez, dual-licensed as a Doctor of Chiropractic and Board Certified Family Practice Nurse Practitioner, applies both scopes in the same visit: he performs the neuromusculoskeletal examination and chiropractic interventions while also conducting nurse-practitioner-level medical evaluation for medication safety, laboratory interpretation, and care coordination.
This structure is common in integrative injury clinics precisely because personal-injury, sports, and chronic-pain patients frequently present with overlapping mechanical and medical issues. Functional medicine testing (nutrient status, inflammatory markers, metabolic panels) informs nutrition and lifestyle plans. Rehabilitation specialists guide graded exercise. The team therefore integrates chiropractic adjustments and soft-tissue care (Dr. Jimenez) with internal-medicine oversight (Dr. Cardenas), functional medicine, personal-injury documentation, and rehabilitation under one coordinated plan. Patients avoid fragmented care in which one provider treats the spine while another manages diabetes or alcohol-related laboratory abnormalities. The shared goal is root-cause resolution, not symptom suppression.
How Integrative Chiropractic Care Reduces Musculoskeletal Pain and Related Comorbidities
Spinal adjustments reduce musculoskeletal pain through several measurable pathways. Mechanoreceptor activation in the joint capsule and surrounding muscles inhibits nociceptive transmission at the spinal cord level (gate-control mechanism). Restored segmental mobility decreases abnormal muscle tone and the secondary ischemia that perpetuates pain. Improved proprioception re-educates movement patterns so that protective guarding diminishes over time. Clinical observations at the clinic show that patients who combine adjustments with graded exercise report faster reductions in Oswestry scores and better sleep once alcohol intake is also addressed.
Comorbidities improve because the same interventions support systemic recovery. Better spinal mechanics and reduced pain lower reliance on medications that interact with alcohol. Improved mobility permits the physical activity that counters alcoholic myopathy and bone loss. Patient education on sleep hygiene and nutrition—delivered within the same visit that includes medical screening—addresses the inflammatory and metabolic drivers. When alcohol-related neuropathy is present, careful neurologic examination distinguishes it from radiculopathy; laboratory evaluation for deficiencies can be ordered under medical direction, and chiropractic care focuses on maintaining joint function while the underlying deficiency is corrected. The reasoning is that musculoskeletal pain and systemic comorbidities share inflammatory and mechanical pathways; treating both simultaneously interrupts the cycle more effectively than sequential, siloed care.
Building Chiropractic Care and Non-Surgical Treatments Into Your Daily Health and Wellness Routine
Non-surgical treatments become sustainable when they are framed as skill-building rather than passive fixes. A typical integrative plan begins with medical clearance and red-flag screening, followed by a short course of adjustments to restore mobility, concurrent soft-tissue work to address fibrosis, and progressive therapeutic exercise that the patient continues at home or in the clinic’s fitness space. Nutritional counseling targets protein intake and anti-inflammatory patterns that support muscle and bone repair. Sleep hygiene education reduces the need for evening alcohol. Periodic re-evaluation tracks function objectively.
Patients learn to recognize early stiffness and apply simple mobility drills before pain escalates. Because the plan is coordinated with the medical director, laboratory follow-up for metabolic or nutritional issues occurs in parallel. The result is a routine that includes periodic chiropractic maintenance, daily movement, mindful alcohol limits (or abstinence when indicated), and medical oversight of comorbidities. Clinical experience shows that individuals who adopt this layered approach report not only less pain but also improved energy, better sleep, and greater confidence in managing their health without reliance on escalating medication or invasive procedures.
Clinical Observations From Dr Alexander Jimenez on Alcohol Injury Recovery and Holistic Care
In clinical practice, patients recovering from soft-tissue or spinal injury who reduce or pause alcohol often describe clearer sleep, less morning stiffness, and faster progress with rehabilitation. Those who continue drinking frequently note delayed gains and greater reliance on pain medication. Red-flag screening is routine: unexplained weight loss, night pain, or progressive neurologic change in a patient with significant alcohol history prompts earlier medical evaluation rather than prolonged assumption of purely mechanical pain. Once serious pathology is excluded, chiropractic care focuses on restoring joint mobility and guiding graded loading.
The dual license allows the same clinician to review medication lists for alcohol interactions and to order or interpret basic laboratory work when indicated. At the same time, Dr. Cardenas provides internal medicine direction for more complex comorbidities. Functional medicine principles further personalize care by addressing nutrient gaps and inflammatory drivers that alcohol exacerbates. These observations align with published evidence that alcohol impairs tissue repair and independently elevates cancer risk; they also underscore the practical value of keeping medical screening and chiropractic rehabilitation under one coordinated roof.
Conclusion and Next Steps for Informed Health Choices
The rebound in public awareness of alcohol’s cancer risk is welcome, yet nearly half of adults still lack clear knowledge. The same exposure that raises lifetime cancer risk also slows musculoskeletal healing, fragments sleep, and worsens pain-related comorbidities. Integrative chiropractic care, delivered within a multidisciplinary team that includes medical direction from an experienced internist, offers a non-surgical pathway to reduce pain, restore function, and support broader wellness. By combining evidence-based adjustments and rehabilitation with medical oversight, functional medicine, and patient education, clinics such as Injury Medical Clinic PA help individuals interrupt harmful cycles and build sustainable health routines.
Readers are encouraged to discuss personal alcohol use and any persistent pain with qualified clinicians who can screen for red flags and coordinate appropriate care. Awareness, followed by coordinated action, remains the most effective step.
Abraham, I., et al. (2025). Risk of cancer from alcohol higher for those with certain comorbidities. Cancer Epidemiology. (As reported in related coverage.)
Maleki, N., Thompson, B. L., Janiuk, K., et al. (2024). Managing pain in patients with comorbid alcohol use disorder and chronic pain. Current Addiction Reports, 11, 459–474. doi.org/10.1007/s40429-024-00563-1
National Institute on Alcohol Abuse and Alcoholism. (2026). Alcohol’s effects on sleep and recovery. (Referenced in clinical literature.)
alcohol cancer risk, Annenberg poll 2026, Surgeon General alcohol advisory, seven types of cancer alcohol, chiropractic care El Paso, Dr Alexander Jimenez, Dr Maria Guadalupe Cardenas, Injury Medical Clinic PA, multidisciplinary non-surgical treatment, musculoskeletal pain alcohol, integrative chiropractic, functional medicine El Paso, personal injury chiropractic, alcohol and back pain, evidence-based chiropractic, red flag screening back pain, non-surgical pain relief, health and wellness routine, acetaldehyde carcinogenesis, alcoholic myopathy, sleep disruption alcohol pain
How Alcohol, Poor Sleep, and Inflammation May Affect Back Pain Recovery
Abstract: Back pain recovery involves more than joints, discs, and muscles. Sleep, alcohol use, inflammation, nutrition, and stress can influence rehabilitation. Alcohol does not directly cause every back condition, but it can fragment sleep, alter pain sensitivity, and interfere with healthy recovery habits. An integrative plan can combine chiropractic care, therapeutic exercise, clinical screening, and medical coordination to address mechanical pain and the recovery environment.
By Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP
Back pain often feels mechanical. A person bends, lifts, sits too long, or gets injured, and the lower back starts hurting. That makes it natural to focus only on the painful joint, muscle, disc, or nerve.
But recovery happens in a whole person. The spine may need better movement, stronger muscle coordination, and time for irritated tissues to recover. Meanwhile, the brain needs restorative sleep, and the body needs adequate nutrition and hydration.
Alcohol can interact with several of those systems. The point is not that alcohol automatically causes low back pain. Low back pain is multifactorial, and many people develop it without drinking. The better question is whether alcohol is making overall rehabilitation harder.
Alcohol Can Make Sleep Look Better While Making Sleep Quality Worse
Falling asleep is not restorative sleep
Some people use alcohol because it makes them drowsy. That effect can create the impression that alcohol helps sleep. Physiologically, sedation is not the same as healthy sleep architecture.
The National Institute on Alcohol Abuse and Alcoholism notes that alcohol can contribute to fragmented sleep and earlier awakening. Even moderate doses may alter rapid eye movement sleep, and alcohol can aggravate sleep-disordered breathing in susceptible people (National Institute on Alcohol Abuse and Alcoholism [NIAAA], n.d.-b).
A patient may spend enough hours in bed yet wake unrefreshed. Fatigue can reduce exercise quality, activity, and adherence.
Poor sleep can amplify pain
Sleep and musculoskeletal pain can reinforce one another. A 2024 systematic review and meta-analysis involving more than 116,000 participants found that sleep problems were prospectively associated with a higher risk of chronic musculoskeletal pain (Runge et al., 2024). A 2026 integrative review also found that sleep disturbance, inflammation, and persistent pain can interact in ways that may complicate rehabilitation (de Freitas et al., 2026).
Mechanistically, poor sleep may weaken descending pain inhibition, the nervous system’s natural “volume control” for painful signals. Sleep restriction has also been associated with changes in inflammatory mediators such as interleukin-6, tumor necrosis factor-alpha, and C-reactive protein.
Those biomarkers are mechanisms, not clinical outcomes. A change in an inflammatory marker does not prove a spinal disc has healed. The outcomes that matter are whether the patient sleeps better, moves better, tolerates exercise, and returns to function.
Alcohol and Pain Sensitivity Have a Complicated Relationship
Short-term numbing can become a poor long-term strategy
Alcohol can temporarily reduce pain perception. That is one reason some people with chronic pain use it for relief. However, NIAAA describes alcohol and pain as a bidirectional relationship. Prolonged heavy use and withdrawal can increase pain sensitivity, creating a cycle in which a person drinks for relief and later experiences more discomfort (NIAAA, n.d.-c).
Not everyone who drinks will develop hyperalgesia. Dose, frequency, health history, medications, and individual biology matter.
Alcohol can also interact dangerously with medications used for pain, sleep, or muscle spasm. Combining alcohol with opioids or other sedating drugs can increase respiratory depression and overdose risk. Patients using pain medicines, sleep aids, or other prescriptions should review alcohol use with their clinician or pharmacist.
Inflammation and Tissue Recovery: What the Evidence Means
Heavy use can disturb immune and repair pathways
Inflammation is part of normal healing. After tissue stress, inflammatory signaling helps coordinate repair. Problems can arise when signaling becomes excessive, prolonged, or poorly regulated.
NIAAA reports that binge drinking and chronic heavy alcohol use can alter immune signaling, contribute to systemic inflammation, and impede recovery from tissue injury. Heavy exposure can also affect gut-barrier integrity and inflammatory signaling (NIAAA, n.d.-a).
Skeletal muscle research adds another layer. Controlled studies and reviews suggest substantial alcohol exposure can suppress muscle protein synthesis and disrupt pathways involved in muscle adaptation. In one exercise study, a large post-exercise alcohol dose reduced myofibrillar protein synthesis even when participants consumed protein (Parr et al., 2014).
That study used a high dose in an exercise setting. It does not prove that one drink prevents a strained back from healing. It does show why alcohol deserves consideration when rehabilitation depends on rebuilding strength and adapting to exercise.
Back Pain Still Requires a Proper Clinical Diagnosis
Lifestyle factors should never replace a back evaluation.
Low back pain may involve muscle strain, joint irritation, disc injury, radiculopathy, stenosis, degeneration, trauma, or other conditions. Persistent symptoms may require neurological examination, imaging, laboratory testing, or referral.
Red flags such as progressive weakness, bowel or bladder changes, saddle numbness, fever, unexplained weight loss, major trauma, or concern for infection, fracture, or cancer warrant prompt assessment.
Clinical screening protects patient autonomy. Instead of blaming alcohol, stress, or poor sleep for every symptom, the clinician asks what is mechanical, neurological, systemic, and modifiable.
An Integrative Plan Addresses the Spine and the Recovery Environment
Chiropractic care and therapeutic exercise
For appropriately screened mechanical low back pain, chiropractic care may be one part of a conservative plan. Guidelines support several nonsurgical options, including education, exercise, spinal manipulation, and multidisciplinary care for selected patients (George et al., 2021; World Health Organization [WHO], 2023).
The goal is not simply to “put the spine back in place.” Manual care may reduce pain and improve mobility so the patient can participate in active rehabilitation. Therapeutic exercise then builds capacity through graded walking, core control, hip strengthening, mobility work, balance, and progressive resistance based on diagnosis and tolerance.
The target is measurable: sit longer, lift safely, walk farther, sleep better, return to work, or resume recreation. If alcohol repeatedly disrupts sleep, hydration, nutrition, or exercise adherence, reducing intake may improve the conditions under which rehabilitation works.
Patients with ongoing pain should be asked about sleep duration, insomnia, snoring, breathing pauses, restless sleep, bedtime alcohol use, caffeine timing, and medication effects. Dr. Jimenez’s Insomnia Solutions Using Integrative Chiropractic Care offers practical sleep-hygiene strategies that can complement musculoskeletal rehabilitation.
Medical coordination keeps the plan safe
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines chiropractic and advanced-practice medical training to connect structural evaluation with broader health screening. When appropriate, laboratory data can help assess metabolic, inflammatory, nutritional, liver, or medication-related concerns that may influence recovery.
Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician, serves as Medical Director and Collaborative Physician, overseeing complex comorbidities, risk stratification, and treatment coordination. Injury Medical Chiropractic and Functional Medicine Clinic also includes nurse-practitioner expertise focused on soft-tissue injury. Clinic materials describe this multidisciplinary structure as one of the few in El Paso, Texas, able to coordinate chiropractic rehabilitation, medical evaluation, functional screening, and advanced conservative treatments.
A practical recovery plan may include consistent sleep and wake times, hydration, sufficient protein, regular movement, prescribed exercise, medication review, and an honest look at alcohol use. Some patients may benefit from reducing or avoiding alcohol, especially when it is being used as a sleep aid or pain reliever.
People who drink heavily or regularly should not abruptly stop without medical guidance if withdrawal is possible. Alcohol withdrawal can be dangerous and may require supervised treatment.
The most useful question is not, “Is alcohol the cause of my back pain?” It is, “What factors are helping or slowing my recovery?”
At El Paso Back Clinic, the goal is to identify mechanical pain generators, screen for medical concerns, improve movement, and help patients build a recovery environment that supports better sleep, safer pain control, and consistent rehabilitation. Patients should cross-check alcohol changes, medications, supplements, and medical concerns with their primary provider or treating medical team.
Better recovery often comes from treating the painful structure while improving the biological conditions that allow the body to adapt safely.
Why the Base of Your Skull May Hurt After a Car Accident
After a rear-end collision on I-10 or Loop 375, many people focus on the stiff, aching feeling in the neck and shoulders. They notice they can’t fully turn their head. Their muscles feel tight, and certain positions make everything worse. However, what often goes unrecognized is that the same forces can produce persistent discomfort right at the base of the skull. This is the sub-occipital region where the upper neck meets the occiput. Patients often treat this as “just neck stiffness.” As a result, they may not connect it to the need for a broader evaluation of headache patterns that may develop days or weeks later.
Pain near the base of the skull after trauma does not automatically mean occipital neuralgia or cervicogenic headache. Those are specific clinical diagnoses that require more than pain location. The same area can be involved in myofascial tension or post-traumatic headache patterns. Additionally, migraine can become more frequent after injury. Multiple factors can be at play, too. Distinguishing among them matters because the treatment path and the documentation needed for recovery both depend on an accurate picture of what is driving the symptoms.
How Collision Forces Affect the Upper Neck and Occiput
In a typical rear-end impact, the head accelerates rapidly and then decelerates. The upper cervical segments (C1–C3) and the small sub-occipital muscles experience shear and stretch forces. These muscles—rectus capitis posterior major and minor, obliquus capitis superior and inferior—help control fine head movement and are richly supplied with sensory receptors. When they become irritated, or when protective guarding sets in, patients feel a deep, aching, or pressure-like discomfort at the base of the skull. This discomfort can radiate upward. Alternatively, it can feel worse with sustained postures, such as driving or looking at a screen.
Ligaments and facet joints in the upper cervical spine can also be stressed. Because sensory information from these structures converges with fibers from the trigeminal system in the brainstem (the trigeminocervical complex), the brain can perceive irritation in the upper neck as head pain. This is true even when the primary problem is mechanical. As a result, this referral pattern is common after whiplash-type forces. However it is only one possible contributor.
Why Location Alone Does Not Confirm a Specific Diagnosis
Occipital neuralgia involves irritation or entrapment of the greater, lesser, or third occipital nerves. It typically produces sharper, shooting, or electric-like pain that starts at the skull base and radiates toward the vertex or behind the eye, often with scalp tenderness. The pain is usually unilateral and can be provoked by pressure along the nerve pathway or by certain neck movements. Diagnosis rests on the characteristic quality and distribution of pain, along with clinical findings. Temporary relief after a diagnostic nerve block can also support the impression. However, discomfort location alone is not sufficient.
Cervicogenic headache is a secondary headache attributed to a disorder of the cervical spine or its soft tissues. Formal criteria (ICHD-3) require evidence of a cervical source capable of producing headache, along with a clear link—such as onset or worsening that matches the cervical problem, reproduction of the familiar head pain by neck movement or sustained posture, restricted cervical motion, and improvement when the cervical disorder improves. Pain that simply starts near the base of the skull does not meet these requirements. Many post-collision patients have restricted upper-cervical motion and sub-occipital tenderness without meeting full criteria for cervicogenic headache.
Other possibilities include:
Myofascial pain from trigger points in the sub-occipital group, upper trapezius, or semispinalis capitis that refer pain into the head.
Post-traumatic headache that may take a migraine-like or tension-type form and can coexist with neck findings.
Mixed presentations in which neck mechanics lower the threshold for an underlying migraine pattern that becomes more frequent after trauma.
A thorough evaluation looks at headache quality, frequency, associated features (nausea, light or sound sensitivity, visual changes), and the relationship to neck movement. It also includes neurological screening and objective measures of cervical motion and soft-tissue findings. Imaging may be indicated in selected cases. Still, many relevant findings are clinical.
What a Broader Evaluation Looks Like in Practice
Patients who come in focused only on neck stiffness often benefit when the clinician also asks about headache days. It is important to discuss whether the head pain starts at the base of the skull and moves forward. The clinician should also ask whether certain neck positions reliably trigger it. Evaluation should also cover how it affects sleep, concentration, and daily activities. Digital range-of-motion measurements, segmental palpation, and provocative testing help document the mechanical component. Also, when headache frequency is rising, a simple headache diary helps track whether the pattern is stabilizing or worsening.
Conservative care can address the mechanical contributors without assuming a single diagnosis. Gentle upper-cervical mobilization or adjustment, myofascial release of the sub-occipital muscles, postural retraining, and graded exercises for deep neck flexors often reduce both neck restriction and the referred component of head discomfort. When indicated, neurofunctional acupuncture or electroacupuncture may help modulate local muscle tension and pain pathways. These approaches are chosen because they target stressed structures while minimizing the need for prolonged medication. They also reduce the likelihood of needing more invasive procedures.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, brings dual-licensure training that allows simultaneous attention to soft-tissue mechanics and the broader medical context of post-traumatic symptoms. Working with Medical Director Dr. Maria Guadalupe Cardenas, MD (board-certified in internal medicine), the team can coordinate laboratory evaluation when metabolic or inflammatory factors may be amplifying recovery. Additionally, they provide oversight when headache patterns require medical attention. Injury Medical Clinic PA is one of the only integrated clinics in El Paso that combines this dual-scope expertise under one roof. This arrangement allows soft-tissue findings, functional measures, and medical direction to be documented together. As a result, this coordination supports both clinical decision-making and the clear records often needed when attorneys evaluate causation after collisions on local freeways.
Supporting Recovery While Protecting Patient Choice
Beneficence is served when care targets the actual drivers of symptoms—whether mechanical restriction, muscle guarding, or a developing headache pattern—rather than treating every base-of-skull complaint the same way. Patients typically gain improved neck motion, reduced frequency or intensity of associated head discomfort, better sleep, and a clearer sense of which activities remain limited. Non-maleficence is supported by prioritizing non-invasive options first. Moreover, many people improve with targeted chiropractic and soft-tissue work without progressing to chronic reliance on analgesics or prematurely considering injections or surgery. Explaining the differential clearly reinforces autonomy. This helps the patient understand why a broader headache evaluation is useful even when the most obvious complaint is neck stiffness. Shared records and coordinated communication with the patient’s existing medical team keep the individual in control of decisions.
Objective documentation—timed motion measurements, consistent examination findings, and correlation with the mechanism of injury—helps distinguish traumatic aggravation of upper-cervical structures from pre-existing conditions under the Texas Eggshell Plaintiff rule. When the records show that the collision produced measurable changes in the region that can refer pain into the head, both clinical care and the legal file are strengthened. In addition, the clinic’s resources on integrated headache management, occipital neuralgia approaches, post-accident headache relief, and the role of chiropractic findings in establishing causation also discuss how cervical findings intersect with headache patterns.
If neck stiffness after a collision is accompanied by discomfort at the base of the skull, or if headaches seem to be increasing, a focused evaluation that looks beyond the neck alone can clarify the picture and guide the next steps in recovery.
References
International Headache Society. (2018). The International Classification of Headache Disorders (3rd ed.). Cephalalgia, 38(1), 1–211. doi.org/10.1177/0333102417738202
Bogduk, N., & Govind, J. (2009). Cervicogenic headache: An assessment of the evidence on clinical diagnosis, invasive tests, and treatment. The Lancet Neurology, 8(10), 959–968. doi.org/10.1016/S1474-4422(09)70209-1
Barmherzig, R., & Kingston, W. (2019). Occipital neuralgia and cervicogenic headache: Diagnosis and management. Current Neurology and Neuroscience Reports, 19(7), Article 20. doi.org/10.1007/s11910-019-0933-z
Headache Classification Committee of the International Headache Society. (2018). Headache attributed to trauma or injury to the head and/or neck. In The International Classification of Headache Disorders (3rd ed.). Cephalalgia, 38(1), 1–211.
Bogduk, N. (2001). Cervicogenic headache: Anatomic basis and pathophysiologic mechanisms. Current Pain and Headache Reports, 5(4), 382–386. doi.org/10.1007/s11916-001-0029-7
Explore how causation combined with chiropractic care can alleviate discomfort and improve quality of life for better health from neck pain.
Abstract: Understanding Neck Pain, Whole-Body Symptoms, and the Path to Recovery
Neck pain is more than discomfort between the shoulders and the base of the skull. The cervical spine protects the spinal cord, supports the head, positions the eyes, contributes to balance, and provides movement needed for work, driving, sleep, exercise, and ordinary family life. When cervical muscles, joints, discs, ligaments, or nerves become irritated, the consequences may spread far beyond the neck. A person may experience stiffness, headaches, shoulder pain, tingling into an arm, reduced concentration, fatigue, poor sleep, or fear of movement. Some of these problems arise directly from a cervical disorder; others are associated conditions that require their own evaluation rather than being automatically attributed to the spine.
In this educational guide, I explain the anatomy and physiology of neck pain, its many possible causes, the differences between mechanical pain and dangerous medical conditions, and how symptoms affect physical function and emotional well-being. I describe how chiropractic care, therapeutic exercise, soft-tissue treatment, ergonomic changes, and coordinated medical oversight may support recovery without surgery when appropriate. I also examine the special challenge of personal injury causation: showing that an accident occurred, that a particular injury exists, and that a medically reasonable explanation connects the two. Texas law requires a sound evidentiary foundation, not simply a diagnosis made after a collision.
The approach discussed here reflects coordinated care at Injury Medical Clinic PA in El Paso. I work as a chiropractor and family nurse practitioner alongside Dr. Maria Guadalupe Cardenas, MD, an internist with over four decades of experience who serves as Medical Director and Collaborative Physician. We consider biomechanics, neurological examination, rehabilitation, medical illnesses, medications, sleep, and patient goals together, while respecting each clinician’s distinct responsibilities. The goal is not to promise that every symptom will disappear. It is to identify important diagnoses, protect patient safety, use the best available evidence, document meaningful progress, and help people return to the activities they value.
This article is educational, not a diagnosis or individualized treatment order. New neurological deficits, suspected fracture, stroke-like symptoms, infection signs, or severe headache after trauma require immediate medical assessment.
Why Neck Pain Matters Far Beyond the Cervical Spine
When a person says, “My neck hurts,” the statement may describe many different experiences. One person has a dull ache after eight hours at a desk. Another feels a sharp catch when turning toward traffic. An athlete notices weakness after a collision. A driver develops neck stiffness and headache the morning after being rear-ended. Their complaints may sound similar, but the underlying problems and appropriate next steps can differ greatly. In my clinical work, I start by asking what the patient was doing when symptoms began, what movements provoke them, whether the pain travels, and what has changed in everyday life.
The worldwide burden is considerable. The GBD 2021 Neck Pain Collaborators (2024) estimated that about 203 million people experienced neck pain in 2020 and projected that the number could reach approximately 269 million by 2050. The estimate does not mean every case is severe or traumatic. It does show why prevention, effective triage, and access to conservative care matter. Neck pain affects people who sit for long periods, perform physical labor, care for children, drive for work, play sports, or live with age-related degenerative changes.
The clinical significance of neck pain cannot be measured by an image or a number on a pain scale alone. A patient who rates pain at four out of ten may be unable to shoulder-check while driving, sleep comfortably, or lift a toddler. Someone with a higher score may continue many activities but need to pace. I therefore ask about participation, not just symptoms. How many hours can the person work? Can they turn their head far enough to see an approaching car? How often do they wake at night? Are they avoiding exercise because movement feels threatening? Those answers help shape care and, when an injury claim is involved, create a more complete account of impairment (Blanpied et al., 2017).
Neck pain is a symptom, not a single diagnosis. It may reflect muscle strain, joint sensitivity, disc pathology, nerve root irritation, inflammatory illness, referred pain, or serious but uncommon conditions. A precise explanation begins with understanding the structure and function of the cervical region.
Cervical Spine Anatomy: Seven Vertebrae With Many Responsibilities
The cervical spine contains seven vertebrae labeled C1 through C7. Together with the discs, small joints, ligaments, muscles, nerves, and surrounding blood vessels, these structures permit a remarkable combination of mobility and protection. C1, the atlas, supports the skull. C2, the axis, helps permit head rotation. Lower cervical segments contribute importantly to flexion, extension, side-bending, and combined turning. No single joint completes a normal head movement on its own. Several levels cooperate while muscles guide and stabilize them.
The cervical spinal canal contains the spinal cord. From this central structure, nerve roots exit through openings called neural foramina. Those roots transmit information between the brain and the upper limbs, including movement commands, touch, position sense, and many reflexes. In the neck, structures operate very close together. A painful joint can limit movement and encourage muscle guarding. A disc or narrowing of a neural opening may irritate a nerve root. In contrast, a problem affecting the spinal cord can cause changes in hand coordination, walking, balance, or bladder function that call for a different level of urgency.
The spine also supports the senses. Vision, vestibular information from the inner ear, and sensory input from neck muscles and joints help you know where your head is in space. When pain alters cervical movement or muscular control, some people feel less steady or experience movement-related dizziness. Yet dizziness has many other causes, including vestibular disorders, low blood pressure, medication effects, concussion, and vascular disease. Dizziness alone never establishes a cervical origin.
I explain anatomy to patients because understanding the system can reduce unnecessary fear. A neck that feels stiff is not automatically “out of place,” and a noisy joint is not automatically damaged. The neck is a living, adaptable structure. Recovery generally depends on making a correct diagnosis, selecting safe movement, rebuilding capacity, and addressing associated health factors.
Cervical Discs: Load Sharing, Nerve Space, and Disc Findings on MRI
Between most cervical vertebral bodies sits an intervertebral disc, composed of a gel-like nucleus pulposus surrounded by layers of fibrous tissue called the annulus fibrosus. The disc helps distribute load and allows controlled motion. It is not a simple cushion that can always be “pushed back” into position. Its structure changes with age, loading history, genetics, and disease. An MRI may describe disc desiccation, reduced height, a bulge, a protrusion, or an extrusion. These words describe imaging features; they do not, on their own, determine whether the disc is painful or whether a collision caused the finding.
A cervical disc problem becomes especially relevant when the clinical picture matches its location. For example, a patient with neck pain traveling into an arm, altered sensation in a particular pattern, reduced reflexes, or weakness may have cervical radiculopathy. The clinician compares the neurological examination with imaging when imaging is indicated. A left-sided disc finding may be less convincing as the sole explanation for isolated right-sided symptoms. Likewise, a common age-related bulge without nerve compression should not automatically become the centerpiece of a personal injury claim.
Discs contain biologically active cells that respond to mechanical load and inflammatory signals. Injury or degeneration can change the local chemical environment. In some cases, inflammatory mediators near a nerve root contribute to pain even when physical compression seems modest. This helps explain why pain intensity is not always proportional to the size of a disc abnormality. It also explains why treatment should target the person and functional deficits, rather than an image alone.
When reviewing a cervical MRI, I discuss both its findings and its limits. The scan can reveal anatomy that requires referral or additional care, but it cannot reliably date many degenerative abnormalities. Clinical correlation means matching imaging with symptoms, exam findings, prior records, and the course of recovery. This is essential in medical care and equally important when answering a causation question (American College of Radiology [ACR], 2024a).
Facet Joints, Ligaments, and the Deep Stabilizing Muscles
Each cervical motion segment contains small facet joints behind the vertebral bodies. These joints help guide movement and transfer forces. Their capsules contain sensory nerve endings that may become irritated with injury, repetitive loading, or degenerative change. A patient with facet-related pain may describe local stiffness, pain with rotation or extension, or aching toward the shoulder blade. However, no single symptom or palpation finding conclusively identifies a facet joint as the source. In selected persistent cases, specialist diagnostic blocks may be considered when the result would change care.
Ligaments connect bones and help limit excessive motion. An acute sprain is an injury to ligamentous tissue, while a strain involves muscle or tendon. These terms are often used together after whiplash, but their meanings should not be blurred. Significant ligament instability requires appropriate imaging and specialist judgment before hands-on cervical treatment. Ordinary muscle tenderness does not prove a ligament tear, and post-crash pain does not establish structural instability.
The deep cervical flexors and deep extensors perform important stabilizing and position-sensing roles. Larger muscles, including the trapezius, levator scapulae, sternocleidomastoid, and scalene muscles, help position the head and shoulder girdle. After pain begins, people often recruit large superficial muscles more forcefully while moving with less variety. This protective pattern can become exhausting. It may also contribute to persistent tightness even after the original tissue irritation has improved.
Researchers, including James Elliott and collaborating research groups, have studied cervical muscle composition in people with persistent whiplash-associated disorders. MRI investigations have reported differences in fatty infiltration of some deep cervical muscles between more severely affected groups and controls. These are group-level associations, not a diagnostic stamp proving a particular accident. They support careful study of muscle function and the inclusion of graded conditioning in rehabilitation, while reminding us to interpret each image cautiously (Karlsson et al., 2016; Smith et al., 2020).
Cervical Nerves and Why Neck Pain Can Reach the Shoulder, Arm, or Hand
The nervous system communicates through electrical signaling and chemical transmission. Sensory neurons carry information toward the spinal cord, while motor pathways help activate muscles. A patient with irritated cervical nerve tissue may experience shooting pain, pins-and-needles, burning, numbness, or weakness. These symptoms deserve more attention than ordinary local soreness because they can indicate a nerve-root disorder. The exact pattern matters, but textbook maps overlap, and individual presentations vary.
The clinician checks arm and hand strength, reflexes, sensation, and symptom reproduction through appropriate tests. A diminished biceps reflex, for example, means something different from a diffuse feeling that the entire hand is numb. Problems outside the neck can mimic cervical radiculopathy. Carpal tunnel syndrome, ulnar neuropathy, shoulder disease, peripheral neuropathy, and some systemic illnesses can cause similar symptoms. In uncertain cases, electrodiagnostic studies or specialist assessment may help distinguish peripheral nerve entrapment from cervical-root disease (Coker et al., 2024).
It is important to separate radiculopathy from myelopathy. Radiculopathy primarily involves a nerve root and often produces arm symptoms. Myelopathy involves spinal cord dysfunction and may cause clumsy hands, gait changes, abnormal reflexes, or leg symptoms. Suspected myelopathy changes the treatment plan immediately. It is not a condition to manage with routine cervical manipulation while awaiting spontaneous improvement.
A patient-friendly explanation is that nerves are communication pathways, not merely “wires” that get pinched. They can become mechanically sensitive, inflamed, or impaired by conditions affecting multiple parts of the body. Treatment starts with identifying what is actually involved. The aim is to protect neurological function, reduce avoidable irritation, and restore activity while monitoring for worsening deficits.
Pain Physiology: Nociception, Inflammation, and the Brain’s Protective Response
Nociception is the process by which specialized nerve endings detect potentially damaging mechanical, chemical, or thermal conditions. Pain is the experience the nervous system creates in response to many influences, including nociceptive input, prior learning, attention, sleep, expectations, stress, and the surrounding situation. Pain is real whether imaging shows a dramatic abnormality or not. At the same time, pain is not a direct ruler measuring tissue damage. This distinction is useful when symptoms feel larger than the visible findings.
After an injury, inflammatory cells and local tissues release signaling molecules that help coordinate healing. Some of those signals temporarily lower the threshold of pain-sensitive nerves. The area may feel tender or unusually reactive, and nearby muscles may stiffen protectively. This response can be helpful for a short period because it encourages caution. Problems develop when ongoing sensitivity and avoidance lead to loss of strength, poor sleep, reduced confidence, and less activity. A person may begin to anticipate pain even during safe movement.
Peripheral sensitization describes heightened responsiveness of nerve endings near affected tissue. Central sensitization refers to altered processing within the central nervous system and may contribute to some persistent pain states. These concepts should not be used as catch-all explanations when a diagnosis is uncertain. They describe possible mechanisms, not an accusation that pain is imaginary. Before applying them, clinicians must assess neurological disease, inflammatory conditions, infection, fracture, and other medical explanations when indicated.
In practice, these mechanisms explain why an individualized plan can combine reassurance, graded movement, sleep support, hands-on care, and medical assessment. Each intervention addresses a different part of the problem. Passive relief may make activity more comfortable, but sustainable gains often depend on progressively rebuilding capacity. This is why I ask what a patient can do today, what they could do before symptoms began, and what meaningful change we can measure over time.
Whiplash After a Car Accident: Mechanism, Symptoms, and Clinical Uncertainty
Whiplash is an acceleration-deceleration event involving the head and neck, commonly associated with motor vehicle collisions. In a rear-end impact, the vehicle and torso may move forward while the head initially lags, followed by changes in cervical posture and acceleration. The precise sequence depends on seat position, restraint geometry, head orientation, impact direction, and the circumstances of the crash. Side impacts, falls, and sporting collisions may also produce neck trauma. The term “whiplash” describes an injury mechanism; whiplash-associated disorder refers to the clinical consequences.
Some people have neck pain and stiffness without neurological abnormalities. Others have headache, shoulder pain, altered movement, dizziness, sleep disturbance, or arm symptoms. Not every complaint has the same cause. The patient may have a coexisting concussion, shoulder injury, vestibular disorder, or preexisting degenerative condition. The examination must sort through these possibilities rather than assume that all symptoms flow from a single sprain.
The amount of visible vehicle damage is not a reliable stand-alone measure of injury severity. Nor does a description of a low-speed collision prove that serious tissue injury occurred. Vehicle details contribute to mechanism analysis, but medical conclusions must still be tied to contemporaneous symptoms, physical findings, risk factors, imaging when indicated, and reasonable alternatives. An expert should not infer a specific disc injury from property damage photographs alone.
The early days after a collision are especially important. A person may initially notice generalized soreness and later recognize focal neck pain, headache, or restricted turning. Delayed reporting is possible, but it is not automatic proof of a causal relationship. Accurate documentation should record the earliest remembered symptom, how it changed, what care was obtained, and whether another event occurred. However, never dismiss immediate emergency warning signs as routine delayed whiplash symptoms.
Common Neck Pain Symptoms: Reading the Pattern Instead of Guessing the Cause
The first step in treating neck pain is describing what the patient actually experiences. Pain quality, location, timing, radiation, and triggers can direct the examination. A deep ache after a long workday suggests a different investigation from sudden severe neck pain after a fall. Someone who wakes with stiffness but improves after gentle movement may need a different plan than someone whose arm weakness is progressively worsening. Symptoms provide clues, but clinical interpretation requires examination rather than an internet diagnosis.
Common symptoms include:
Local aching or tenderness near the cervical muscles and joints.
Reduced range of motion, especially when turning the head or looking upward.
Muscle guarding, tightness, or spasms around the neck and shoulder girdle.
Pain between the shoulder blades or discomfort that spreads toward the upper back.
Headache that may accompany neck pain or be provoked by certain neck movements.
Arm pain, numbness, tingling, or weakness that raises concern for nerve involvement.
Movement-related dizziness or a sense of imbalance that requires differential diagnosis.
Sleep disruption, fatigue, and difficulty concentrating associated with persistent discomfort.
The order in which symptoms appear can matter. If a patient reports a new symptom during recovery, I revisit the history and examination rather than simply adding it to the original diagnosis. A new weakness, an increasingly severe headache, or a change in walking may signal a problem requiring urgent reassessment. Conversely, fluctuating soreness during a graded exercise program can occur without a new structural injury. Context determines the response.
It is tempting to divide patients into “minor” and “major” pain categories based on a single number. A more useful clinical picture includes severity, irritability, and functional consequences. Irritability asks how easily symptoms begin, how intense they become, and how long they last after activity. This information guides how much movement or manual treatment is reasonable. It also provides a practical baseline for judging recovery.
Mechanical Neck Pain and Muscle Strain
Mechanical neck pain is a broad term for symptoms influenced by movement, position, or physical loading without a clearly identified serious medical condition. It may arise from several structures at once. A worker who spends hours looking down may report tenderness, reduced rotation, and aching around the shoulder blades. Someone who lifts a heavy object with their arms extended may develop discomfort in the cervical and shoulder muscles. The clinical goal is to determine which tasks exceed present capacity and which movements are safe enough to restore.
A muscle strain can involve microscopic damage or overload of muscle fibers and associated connective tissue. The body responds with an inflammatory and repair process. Most uncomplicated strains do not require advanced imaging, but trauma severity and examination findings can change that decision. Management often starts with tolerable movement, symptom control, and temporary modification of activities that sharply increase pain. Prolonged avoidance may reduce conditioning and increase apprehension.
I explain that muscle tightness can be both a primary problem and a secondary protective response. If a painful cervical joint causes the surrounding muscles to tense, forceful stretching may aggravate the situation. On the other hand, gentle range-of-motion practice, heat in an appropriate setting, relaxation of excess muscular guarding, and progressive endurance work may improve comfort. The treatment is adjusted to tissue irritability, age, medical history, and the person’s actual goals.
The patient should leave with clear answers to three questions: what activities are safe, what changes would be concerning, and how progress will be measured. A home plan might initially use comfortable neck turns and walking, then advance to scapular control and resistance work. Manual care may help create a window for active rehabilitation, but it is not a substitute for restoring strength and confidence in movement.
Cervical Radiculopathy: When Arm Symptoms accompany Neck Pain
Cervical radiculopathy occurs when a cervical nerve root becomes irritated or dysfunctional. Patients may notice pain extending from the neck or shoulder region into the arm, tingling in the fingers, altered sensation, diminished reflexes, or muscle weakness. Pain may be severe even when imaging appears modest, and some people have relatively little neck pain despite prominent arm symptoms. A thoughtful neurological examination is therefore crucial (Coker et al., 2024).
Possible contributors include a disc herniation, age-related neural foraminal narrowing, inflammatory irritation, or combinations of these processes. The clinician should not assume that numb fingers always come from the neck. Median or ulnar nerve entrapment, diabetes-associated neuropathy, and other peripheral disorders may produce similar complaints. I compare symptom distribution with motor function, reflexes, sensory findings, provocative tests, and medical history. If the findings conflict, we reconsider the working diagnosis.
Many patients can begin with conservative management when serious neurological compromise is absent. Depending on the case, treatment may include education, activity modification, appropriately selected exercises, symptom-modifying manual techniques, and medical management. A person with pronounced nerve irritability may initially tolerate small movements better than aggressive stretching or high-force interventions. Persistent or worsening objective weakness, signs of spinal cord involvement, or uncontrolled pain may require imaging and specialist referral.
Research does not support presenting a single nonsurgical technique as a guaranteed cure. A systematic review of conservative care for cervical radiculopathy found that evidence for several interventions remained low or very low in certainty (Plener et al., 2023). More recent reviews comparing surgery with nonsurgical care report a nuanced picture: surgery may offer earlier relief or benefit selected patients, while pooled long-term outcomes can be similar among appropriately selected groups. Those findings do not erase the need for prompt surgical assessment when neurological deterioration or other indications are present (Dar et al., 2026; Kale et al., 2026).
Cervical Myelopathy and Other Neurological Warning Signs
Degenerative cervical myelopathy or traumatic spinal cord compromise should not be confused with ordinary neck stiffness. Spinal cord dysfunction can produce difficulty with buttons or handwriting, repeated dropping of objects, loss of fine motor coordination, unsteady walking, unusual reflexes, and sometimes bowel or bladder changes. Some patients do not report dramatic neck pain. The neurological changes themselves become the most important part of the story.
When I hear about progressive hand clumsiness or gait disturbance, my objective shifts from providing routine pain relief to identifying possible cord disease and arranging appropriate medical assessment. Symptoms may come from several conditions, so the diagnosis requires clinical examination and often MRI. A concerning symptom does not prove myelopathy, but it justifies caution. Manipulation should not proceed as though the person has uncomplicated mechanical neck pain while the possibility of cord compression remains unresolved.
Weakness should be described carefully. A person may feel weak because pain prevents a strong effort, while another has genuine loss of nerve-mediated muscle force. Recording the specific movement, comparison with the opposite side, reflexes, sensation, and change over time is more informative than simply writing “weakness.” This principle matters for both treatment and medicolegal documentation.
The long-term goal is to prevent avoidable harm. Some diagnoses require medications, injections, or specialist surgery rather than a predominantly chiropractic plan. The advantage of multidisciplinary care is not that one team can treat every condition in-house. It is that concerning findings can be recognized, communicated, and directed to the right professional without unnecessary delay.
Cervicogenic Headache and the Neck-Head Connection
A cervicogenic headache is a headache attributed to a disorder of the cervical spine or related structures. The upper neck and head share interacting sensory pathways, often discussed through the trigeminocervical complex. Pain signals originating in upper cervical tissues may be perceived in regions of the head, while headaches of other origins can make the neck feel sore. This convergence explains why location alone cannot separate one headache disorder from another.
A patient may report pain beginning in the upper neck and traveling toward the back of the head or temple, sometimes associated with restricted cervical movement. Those findings raise a possibility but do not establish the diagnosis. Migraine frequently includes neck pain, sensitivity to light, nausea, and changes in activity tolerance. Tension-type headache, occipital neuralgia, temporomandibular disorders, and post-traumatic headache can overlap. A new or unusually severe headache after injury requires evaluation for dangerous causes before being labeled cervicogenic.
When cervical dysfunction is contributing, selected manual therapy and exercise approaches may reduce symptoms. A systematic review published in 2026 found that manual therapy may provide short-term relief for cervicogenic headache, while the certainty of evidence for durable effects and the added benefits of combined treatment was limited (Martins et al., 2026). That result supports trying well-selected care and measuring response, but does not promise that every headache will resolve through spinal adjustments.
Clinical observation can help refine the hypothesis. Does the headache change when cervical movement improves? Do sleep and function recover together? Is headache frequency actually decreasing in a diary? These questions matter because a brief feeling of relaxation after treatment does not equal sustained improvement. When migraine or another primary headache disorder is present, chiropractic care may address coexisting mechanical neck symptoms, but evidence-based headache medicine remains essential.
Occipital Neuralgia and Pain at the Back of the Head
Occipital neuralgia involves irritation or dysfunction of nerves supplying the back of the scalp. People may describe brief shooting, electric, stabbing, or burning pain beginning near the upper neck and moving toward the scalp. Tenderness over an occipital nerve may occur. However, similar discomfort can accompany migraine, cervicogenic headache, local muscle sensitivity, and other conditions. A precise diagnosis depends on characteristic symptoms, examination, and sometimes the response to a specialist diagnostic nerve block.
Why does the distinction matter? Because the treatment target changes. If a patient has prominent upper-neck muscle guarding alongside an established occipital neuralgia diagnosis, gentle soft-tissue techniques and movement rehabilitation may address the muscular component. They do not necessarily correct the underlying nerve disorder. Persistent neuralgic pain may benefit from medical management, specialist assessment, or carefully selected procedures. When a patient reports a sudden new severe posterior headache with other neurological signs, urgent vascular or neurological causes must be considered instead of assuming benign neuralgia.
I also discuss sleep positioning and activities that compress sensitive tissues, such as prolonged pressure against a rigid headrest. A supportive pillow can help comfort, but no pillow shape has been established as a universal treatment. The goal is to find a position that allows rest while keeping the neck comfortable. Excessive attention to perfectly straight posture can increase muscle tension and unnecessary fear.
A symptom diary may clarify whether pain is brief and electric, constant and aching, or accompanied by nausea and light sensitivity. This seemingly simple documentation can prevent misclassification. It also helps medical specialists understand whether treatment is changing the condition that matters most to the patient.
Neck Pain, Dizziness, Balance Problems, and Concussion
Patients sometimes say that their neck injury makes them dizzy. A physiological basis for considering a cervical sensorimotor contribution exists because receptors in neck muscles and joints provide information used alongside vision and vestibular signals. When these inputs disagree, a person may experience disorientation or unsteadiness. Yet cervicogenic dizziness remains a diagnosis of exclusion, and clinicians should not attribute symptoms to the neck before investigating important alternatives.
A motor vehicle collision can produce a concussion even without a direct blow to the skull. A patient may report headache, light sensitivity, slowed thinking, nausea, sleep changes, or difficulty concentrating. Other causes include benign positional vertigo, inner-ear injury, medication effects, dehydration, cardiovascular problems, and uncommon but dangerous vascular injuries. Different problems can coexist. Testing cervical range of motion alone cannot confirm or rule out a concussion.
The CDC (2025) notes that concussion symptoms can appear after a delay and that worsening headache, repeated vomiting, weakness, unusual confusion, seizures, or other danger signs warrant emergency evaluation. That advice is particularly important for patients who interpret every post-collision symptom as whiplash. A properly coordinated care plan can include concussion assessment, vestibular rehabilitation, cervical rehabilitation, and medical follow-up, but each component should be chosen based on findings.
For someone with motion sensitivity, early exercises may be deliberately small and carefully paced. The aim is not to force the nervous system to tolerate severe dizziness. It is to identify the source, establish safety, and gradually reintroduce appropriate sensory and movement challenges. Objective balance measures, symptom logs, and reassessment help determine whether the approach is working or whether the diagnosis must be reconsidered.
Neck Pain, Sleep Disturbance, and Daytime Fatigue
Sleep disruption is one of the most important and frequently underestimated effects of persistent neck pain. A patient may fall asleep normally but wake every time they turn their head. Another may struggle to find a comfortable position. Repeated awakenings can reduce restorative sleep and leave the person tired, irritable, or less able to cope with discomfort the next day. Pain and sleep influence each other in both directions, creating a cycle that can persist even as some tissues heal.
The first step is to ask what is actually interrupting sleep. Is it mechanical discomfort, arm tingling, worry, snoring, medication, or another medical condition? Treating cervical movement limitations will not correct untreated sleep apnea, but better neck comfort may reduce one barrier to restful sleep. A multidisciplinary clinic is well placed to distinguish these contributors and recommend the appropriate next evaluation.
During rehabilitation, I generally emphasize practical sleep habits rather than an expensive collection of accessories. A regular schedule, a comfortable pillow height, fewer prolonged static positions before bed, and manageable daytime activity are reasonable starting points. If symptoms are severe enough to prevent normal rest, medication options and medical review may be appropriate. A pillow that supports the head without forcing end-range rotation is usually more helpful than trying to achieve an idealized posture.
We can track sleep alongside pain and function. Nighttime awakenings, time to fall back asleep, and morning stiffness are useful patient-reported measures. If sleep improves while walking tolerance, work participation, and neck movement also improve, the trend provides a more complete description of recovery than a single pain score. It does not, by itself, identify the anatomical source or prove legal causation.
Neck Pain, Stress, Anxiety, and Fear of Movement
An injury can alter how safe the world feels. A driver who experiences a collision may become tense while approaching intersections. An employee injured at work may worry about losing income. Someone with arm tingling may fear permanent nerve damage even when examination findings are reassuring. These emotions do not mean the symptoms are fabricated. They are understandable human responses that can influence muscle guarding, attention, sleep, activity, and participation.
Fear-avoidance behavior occurs when a person reduces activity because movement seems likely to cause harm. Temporary protection may be appropriate after acute trauma, but prolonged avoidance can reduce strength and endurance. Pain catastrophizing is a research term for patterns of thinking that amplify threat and helplessness; it should not be used as a character judgment. A 2025 systematic review found low- to moderate-certainty evidence connecting higher psychological distress and catastrophizing with persistent or recurrent nonspecific neck pain (Yu et al., 2025).
A compassionate rehabilitation plan makes room for these factors without replacing proper medical evaluation with psychological explanations. I explain the working diagnosis, discuss reassuring findings, identify activities that can be practiced safely, and invite questions. A patient who understands why an exercise was chosen is more likely to perform it consistently. When post-traumatic stress, anxiety, depression, or significant fear restricts function, collaboration with appropriately trained mental health professionals may be important.
Progress can include confidence as well as physical performance. Can the patient ride in a car without gripping the seat? Can they turn their head safely? Do they feel able to resume an enjoyable activity? These are meaningful goals. However, neither the presence nor absence of distress determines whether a cervical injury exists, and psychological scores are not substitutes for neurological testing or medical causation analysis.
Neck Pain, Jaw Pain, and Shoulder Dysfunction
The jaw, upper back, shoulders, and neck operate in a connected movement system. A person who clenches the teeth may also hold tension in the neck muscles. Someone with a painful shoulder may elevate the shoulder girdle and change how the cervical muscles work. Conversely, a patient with cervical radiculopathy may experience pain that feels like a shoulder problem. These relationships explain why a regional examination is sometimes more useful than treating only the spot the patient points to.
Temporomandibular disorders can cause jaw pain, clicking, chewing discomfort, and headache. Cervical dysfunction may coexist, but not every jaw problem originates in the spine. A patient with dental pain, jaw locking, or progressive inability to open the mouth needs appropriate dental or medical assessment. Likewise, a rotator cuff tear, shoulder arthritis, or adhesive capsulitis requires shoulder-focused examination and may need distinct treatment.
I often ask patients to perform simple functional tasks: raise an arm, reach behind the back, turn the head while seated, and describe which movement reproduces the familiar complaint. We evaluate whether the pain changes with neck position, shoulder loading, or both. This makes treatment more precise. For someone whose shoulder weakness stems from a cervical nerve-root problem, repeated shoulder massage alone may miss the main issue. For someone with isolated shoulder disease, an intensive cervical treatment program may be unnecessary.
Integrated rehabilitation addresses the relevant components together. Exercises might restore scapular control, thoracic mobility, cervical endurance, and upper-limb strength. The exact combination depends on examination findings. A shoulder and neck program should not be described as a universal solution, but as a measured response to a patient-specific movement pattern.
Neck Pain, Migraine, Tension-Type Headache, and Other Comorbidities
Comorbidity means another condition exists alongside the main complaint. It does not necessarily mean one caused the other. In people with neck pain, relevant comorbidities may include migraine, tension-type headache, sleep disorder, anxiety, depression, osteoarthritis, chronic widespread pain, diabetes, vestibular conditions, or previous concussion. Some share risk factors or influence recovery. Others are unrelated conditions that happen to occur in the same person.
This distinction is crucial. A patient with migraine may also have tender cervical muscles, especially during attacks. Treating muscular discomfort can be useful, but it does not prove that a cervical joint caused the migraine. A person with diabetes may have hand numbness from peripheral neuropathy rather than a new cervical lesion. An older patient with osteoarthritis may develop new pain after a collision even though degenerative imaging findings were present beforehand. The clinical task is to identify the active contributors and avoid turning temporal association into unsupported cause-and-effect claims.
When I review comorbidities, I look for conditions that affect safety, prognosis, and treatment selection. Bone fragility may change which manual techniques are safe. Anticoagulant use changes the evaluation of trauma and bleeding risks. Diabetes can affect neuropathy assessment and recovery. Sleep problems may lower pain tolerance and exercise adherence. Depression or anxiety may influence participation, but neither discredits the patient’s report of symptoms.
Our medical director and clinical team can help coordinate these issues, with external specialist referral when appropriate. The benefit of comprehensive assessment is not that more laboratory testing is always better. It is that testing and treatment match plausible medical questions. A careful plan avoids both undertreating important illness and adding low-value interventions that do not address a defined problem.
How Neck Pain Changes Driving, Work, Family Life, and Independence
The cervical spine participates in movements people perform without consciously thinking about them. We turn to check a blind spot, look down to read a recipe, lift our eyes toward a shelf, carry groceries, cradle a child, and adjust our posture to speak with someone. Functional disability occurs when pain, stiffness, weakness, fatigue, or fear makes these activities difficult. Two people with similar MRI findings may have very different levels of disability, which is why a treatment plan must be grounded in what the patient needs to do.
Consider driving. A patient recovering from a cervical sprain may have enough comfort to sit in a car but insufficient rotation to see through the side window. The person may compensate by turning the entire torso or avoiding certain routes. This is not merely an inconvenience. Safe driving requires attention, vision, and appropriate movement. We assess whether the patient can perform driving-related tasks before recommending a return to unrestricted driving. If medication causes sedation or neurological symptoms affect coordination, the question extends beyond cervical range of motion.
Work demands are similarly varied. A computer programmer may need sustained attention and frequent position changes. A warehouse employee may lift, reach overhead, and repeatedly look upward. A nurse may reposition patients. A mechanic may work underneath equipment with the neck extended. A professional driver may require prolonged sitting and frequent head turns. Writing “return to work as tolerated” without considering these demands can lead to an unsafe or unrealistic plan.
Family life matters as much. People describe missing a child’s sporting event, being unable to prepare meals, avoiding intimacy because of discomfort, or losing confidence in household tasks. These are valid elements of health-related quality of life. I ask patients to identify specific tasks and rate their ability to complete them. The resulting goals are more meaningful than generic instructions to “improve posture.” In a personal injury setting, they also provide a transparent record of how the condition affected participation, without requiring exaggerated claims.
Occupational Neck Pain in Office Workers and Technology Professionals
Extended computer work does not automatically cause neck injury. The body can tolerate many postures, and no single sitting position is proven to prevent all neck pain. Problems are more likely when prolonged exposure, limited movement variation, workload, stress, insufficient recovery, and reduced conditioning combine in someone sensitive to these factors. A laptop placed low on a desk can encourage sustained downward gaze. Still, the practical solution is often to adjust the workstation and vary activity rather than demand perfect alignment all day.
My occupational assessment includes screen height, chair and desk fit, keyboard and mouse placement, breaks, phone habits, and the physical demands outside work. If a patient spends ten hours typing but also lifts heavy weights after work, both exposures may matter. We distinguish a task that triggers symptoms from a claim that the task is the sole cause of a structural lesion. A symptom diary may show that changing the screen arrangement helps, but that improvement alone does not identify the injured anatomical tissue.
A reasonable program uses short movement breaks, comfortable rotation and extension, scapular endurance, and progressive strengthening. The goal is load tolerance: helping tissues and the nervous system tolerate ordinary tasks with less discomfort. A worker may benefit from a sit-stand arrangement, yet prolonged standing in a fixed posture can also become uncomfortable. Variety usually matters more than adherence to a rigid posture rule.
Where a worker reports new arm numbness, severe headache, or weakness, an ergonomic explanation is not enough. We conduct the appropriate neurological and medical assessment. In occupational medicine, it is important to separate symptoms associated with prolonged work demands from a specific traumatic injury, and to document whether the job aggravates an existing condition. Clear terminology protects both the worker and the clinical record’s accuracy.
Sports-Related Neck Pain and Safe Return to Performance
Athletes expose the cervical spine to forces that vary by sport. Football, wrestling, gymnastics, cycling, volleyball, and weightlifting place different demands on head control, shoulder girdle strength, balance, and rapid movement. A strain during training differs from neck pain after a direct axial load or collision. The mechanism, neurological examination, and trauma history determine whether the athlete needs emergency assessment, imaging, or a simple training modification.
The decision to return to performance should not depend solely on feeling better at rest. An athlete may need sufficient cervical range of motion, muscular endurance, reaction capacity, sport-specific strength, and confidence to tolerate contact or rapid movement. A person returning to overhead lifting must coordinate the upper back, shoulders, and neck under increasing load. A wrestler may need to resist rotational forces, while a cyclist needs to maintain visual orientation in an extended riding position. These tasks require different testing.
Progressive rehabilitation might move from comfortable active range of motion to deep neck muscle training, then scapular and trunk strengthening, and finally sport-specific drills. Training loads increase according to symptom response, neurological safety, movement quality, and performance goals. If an athlete has a suspected concussion, cervical instability, progressive neurological symptoms, or a significant structural injury, return-to-play decisions require more specialized clearance. No hands-on adjustment substitutes for that process.
This principle applies beyond sports. A person can reach maximum medical improvement in the sense of relative medical stabilization and still need conditioning before returning to full athletic performance. Conversely, an athlete may regain high performance but retain a diagnosed condition that merits follow-up. Medical status, disability, and performance are related measures, not interchangeable labels.
Neck Pain in Older Adults and People With Preexisting Degeneration
Aging can change discs, facets, bone density, and muscle function. Many older adults remain active and independent despite these changes. Cervical spondylosis refers broadly to degenerative changes of the cervical spine, and these findings are not automatically painful. An older patient with a degenerative MRI finding may have had no meaningful neck symptoms before a fall or collision. The event may cause a new soft-tissue injury or aggravate an existing symptomatic condition. A thoughtful assessment must distinguish those possibilities.
Safety becomes particularly important when bone health is compromised. Osteoporosis, inflammatory arthritis, prolonged corticosteroid use, malignancy, or a history of fracture can alter the risk associated with manual interventions. A patient with known rheumatoid arthritis may require assessment for cervical instability. A person taking anticoagulants after a fall may need urgent medical evaluation, even with minimal external bruising. These factors influence imaging decisions and the appropriateness of cervical manipulation.
Older adults may also face obstacles that complicate recovery: reduced strength, poor balance, multiple medications, sleep disturbance, and limited access to transportation. A successful rehabilitation plan may focus on getting in and out of a car, performing household tasks, walking safely, and turning the head without losing balance. These goals may be more important to the patient than regaining every degree of motion measured in a clinic.
In a personal injury case, preexisting degeneration should neither be ignored nor used as an automatic reason to dismiss a new complaint. The evidence should address prior symptoms, treatment history, functional baseline, mechanism, clinical course, and any interval changes. A defensible opinion can recognize both chronic anatomy and new functional deterioration without claiming that an accident created every preexisting MRI abnormality.
Pregnancy, Chronic Illness, and Other Factors That Change the Neck Pain Plan
Some patients need modifications because of pregnancy, connective-tissue disorders, inflammatory disease, hypermobility, active infection, malignancy, or significant cardiovascular conditions. A safe approach begins with history and examination, not a fixed chiropractic protocol. Pregnancy may change sleep positions and exercise tolerance; it does not mean every neck intervention is unsafe. Still, when risk factors exist, coordinate treatment selection with the appropriate obstetric clinician.
Hypermobility deserves attention because a person can have a large range of motion and still feel unstable or fatigued. Aggressive stretching may not address the problem. These patients may benefit from carefully dosed muscular endurance and movement-control work. If a hereditary connective-tissue condition or vascular disorder is suspected, the evaluation becomes more complex. The clinician should avoid equating flexibility with a need for further manipulation.
Patients with autoimmune disease, diabetes, thyroid dysfunction, or systemic inflammatory illness may have symptoms that overlap with mechanical neck pain. A fever, unexplained weight loss, pronounced morning stiffness, unusual fatigue, or joint swelling can change the differential diagnosis. Functional medicine discussions may help organize relevant medical history, nutrition, sleep, and lifestyle factors. Still, disease-specific testing must follow accepted clinical indications rather than broad assumptions that all neck pain represents systemic inflammation.
Dr. Cardenas’s internal medicine role is particularly useful when medical comorbidities influence treatment safety or prognosis. Medication reconciliation, targeted laboratory assessment, chronic disease management, and referral decisions are examples of complementary functions. The chiropractic team focuses on mechanical, neurological, and rehabilitative findings, while the medical team evaluates broader health risks. Working together should reduce fragmented decision-making, not blur professional responsibilities.
Neck Pain Red Flags: When Immediate Medical Evaluation Comes First
A life-threatening disorder does not cause most neck pain. However, a small number of conditions require urgent assessment, and missing them can be dangerous. Red flags are features that raise concern for fracture, spinal cord injury, infection, cancer, arterial dissection, or another serious illness. A red flag is not automatically a diagnosis. It is a reason to ask more focused questions, examine carefully, and sometimes arrange urgent imaging or referral (Blanpied et al., 2017; Rushton et al., 2023).
Seek emergency medical care for neck pain accompanied by concerning features such as:
New or progressive arm or leg weakness, marked walking difficulty, or loss of hand coordination.
Sudden severe or unusual headache or neck pain, especially with double vision, speech difficulty, facial droop, imbalance, or other neurological signs.
Significant trauma with suspected fracture or instability.
Fever, severe neck stiffness, or systemic illness suggesting possible infection.
Loss of consciousness, repeated vomiting, increasing confusion, seizure, or another serious head injury sign.
New bowel or bladder disturbance associated with possible spinal cord dysfunction.
Patients sometimes confuse a normal temporary increase in exercise soreness with a red flag. We explain the difference clearly. Mild soreness after unfamiliar muscle work may improve within a manageable time. Progressive weakness, severe neurological symptoms, and systemic signs require evaluation rather than waiting for the next appointment. A good conservative-care practice must be willing to stop treatment and refer when the evidence points outside its safe scope.
This is also why chiropractic adjustments are not automatic on the first visit, especially after trauma. Safety screening comes before technique selection. If fracture, vascular disease, instability, infection, or significant cord compression is suspected, hands-on cervical treatment may be inappropriate until further assessment is complete. Patient safety remains the highest priority even when a person wants immediate relief.
Cervical Artery Disorders and Informed Consent Before Manual Treatment
The vertebral and carotid arteries supply blood to important regions of the brain. Cervical artery dissection is uncommon, but it can present with head or neck pain before obvious stroke-like symptoms appear. Because a person with an evolving vascular problem may initially seek care for pain that resembles a musculoskeletal complaint, clinicians must consider this possibility in the history and examination. The International IFOMPT Cervical Framework emphasizes clinical reasoning, recognition of concerning symptoms, and appropriately adapted examination before planned cervical interventions (Rushton et al., 2023).
Severe new unilateral neck pain or headache, unusual dizziness, visual disturbance, difficulty speaking, facial sensory changes, and other neurological symptoms should not be casually labeled muscle spasm. The clinical picture may require urgent medical referral. A negative single office test does not reliably guarantee the absence of vascular disease. Historical positional screening methods cannot replace comprehensive clinical judgment.
Patients also deserve a clear discussion of manual-therapy risks, benefits, and alternatives. Some techniques may cause temporary soreness. Serious adverse events are rare but potentially severe, and the relationship between cervical manipulation and arterial events is difficult to study because an evolving dissection can cause pain before a person seeks care. The appropriate clinical response is neither to dismiss all concerns nor to claim that any neck movement is inevitably dangerous. We use individualized screening and informed consent, and we select lower-force or non-thrust approaches when appropriate.
For certain patients, active exercise, gentle mobilization, soft-tissue work away from the cervical arteries, or specialist-guided management may be preferable to high-velocity cervical manipulation. When risk cannot be assessed adequately, do not proceed with treatment. Choosing not to manipulate is sometimes the most clinically sound decision a chiropractor can make.
How a Comprehensive Neck Pain Evaluation Begins
The examination starts with a history that is specific enough to explain the patient’s story. I ask when symptoms began, how they changed, what the patient could do before the problem, and which activities now provoke or relieve it. After trauma, I document the event in concrete terms: direction of impact when known, seating position, restraint use, head position, immediate symptoms, emergency care, subsequent changes, and other possible injuries. When details are uncertain, the record should say so rather than filling gaps with confident-sounding guesses.
Next comes a focused medical review. Current medications, prior surgeries, headache history, neurological disorders, systemic illness, and previous neck treatment may change the differential diagnosis. Some patients have a history of intermittent neck soreness but no prior arm symptoms or work restrictions. Others had significant limitations before the event. Both situations deserve faithful documentation. A medical record should distinguish reported history from independently reviewed records.
The physical examination can include posture and movement observation, cervical and shoulder range of motion, palpation, neurological tests, selected orthopedic maneuvers, upper-limb function, balance assessment, and a functional task relevant to the patient’s complaint. The precise components depend on the presentation. For instance, a patient with arm numbness needs a more detailed neurological evaluation than someone with uncomplicated localized stiffness after a day of gardening.
I explain what each finding does and does not prove. Tenderness demonstrates sensitivity at the examined location; it does not identify the microscopic state of every ligament. Reduced range of motion may reflect pain, fear, guarding, or a mechanical restriction. A positive provocative test can support a hypothesis but rarely stands alone. Converging evidence from history, examination, investigations, and clinical course is more persuasive than any isolated finding.
Objective Testing: Range of Motion, Strength, Reflexes, and Function
A common misconception is that all objective information must come from an MRI. In reality, well-conducted clinical measurements can be highly useful. Cervical range-of-motion testing describes whether and how far the patient can turn, bend, or extend. Repeated testing under similar conditions can show progress. Strength testing may reveal a focal deficit, while reflex and sensory testing provide information about nervous system function. Functional tests describe what these findings mean in real life.
Measurements require attention to reliability. If one visit records head rotation while the trunk is free to move, and the next holds the shoulders still, a numerical difference may reflect the method rather than a true change in cervical motion. Likewise, strength scored informally is less precise than standardized testing. I try to use consistent positions, instructions, and documentation. When measurement uncertainty exists, we should acknowledge it rather than present false precision.
Validated questionnaires add another dimension. The Neck Disability Index asks about activities such as personal care, lifting, reading, work, driving, sleeping, and recreation. A pain scale captures intensity but not necessarily participation. A Patient-Specific Functional Scale can focus on tasks the individual chooses. These tools are valuable because they can be repeated to monitor change in a standardized way (Blanpied et al., 2017).
If function improves, it supports a conclusion that the patient is making progress under the overall plan. It does not establish which treatment component produced the improvement, whether natural healing contributed, or whether an accident caused every diagnosis. Clinical testing serves patient care first. Its medicolegal value comes from transparency, consistency, and relevance to the question being asked.
Imaging Decisions: When X-Ray, CT, and MRI Help
Imaging should answer a defined clinical question. X-rays can show alignment and certain bony changes but do not directly display the spinal cord or most soft tissues in detail. CT is often especially useful for evaluating suspected acute bony injury after trauma. MRI provides better information about discs, the spinal cord, nerve-root surroundings, and many soft-tissue structures. None of these modalities is necessary for every patient with neck pain.
The ACR Appropriateness Criteria distinguish acute traumatic cervical injury from nontraumatic pain and from suspected radiculopathy. Clinical rules such as the Canadian C-spine Rule and NEXUS criteria help clinicians determine when imaging may be needed after certain blunt-trauma presentations. For uncomplicated nontraumatic neck pain without red flags, advanced imaging is often not the first step. For chronic radiculopathy, MRI may be appropriate, particularly when symptoms persist or the result would influence treatment or referral (ACR, 2024a, 2024b).
Imaging is especially important when the clinical findings suggest a lesion that could threaten neurological function. At the same time, incidental degenerative findings are common enough that a scan can mislead if read without context. A radiology report may accurately describe a disc bulge while the clinician concludes that the patient’s main problem is a different disorder. These judgments require evidence, not simply a preference for or against imaging.
In my published clinical case discussion, “Evaluating Cervical Spine Injury with Advanced Imaging,” I describe a post-collision patient who presented for a second-opinion evaluation after cervical and arm complaints. The case illustrates why documenting symptom patterns, neurological findings, previous care, and the reason for further investigation matters. A published case report can demonstrate a diagnostic thought process, but it does not prove that the same imaging or treatment decision is right for every patient (Jimenez, 2017).
What Chiropractic Care Is and Where It Fits in Modern Neck Pain Treatment
Chiropractic care is a regulated health profession focused on assessing, diagnosing, and conservatively managing musculoskeletal conditions, particularly those involving the spine and related neuromuscular function. Chiropractic clinicians may use manual therapy, joint mobilization, spinal manipulation, therapeutic exercise, patient education, and other approaches within the scope of their licensing and training. A chiropractic visit should involve clinical reasoning, safety screening, shared decision-making, and appropriate referral. It is not simply an appointment to crack the neck.
A spinal adjustment is one possible intervention, not a required treatment for every patient. In high-velocity, low-amplitude manipulation, a trained clinician delivers a brief, controlled movement to a selected joint. Other approaches use slower mobilization, low-force instruments, positional techniques, or no manual intervention. The audible sound sometimes associated with a thrust is generally related to joint cavitation. This does not mean a vertebra was dangerously displaced or that its position was permanently corrected.
The most defensible purpose of manual therapy is to help improve symptoms and movement in an appropriately selected patient. It may alter local mechanical sensitivity, change sensory input, reduce muscle guarding, or make exercise easier. Researchers continue to study the mechanisms. A meaningful clinical response can occur without proving that a specific bone was “put back in place.” The explanation we give a patient should match the available scientific evidence, not rely on dramatic anatomical claims.
I view chiropractic care as one part of active recovery. If an intervention briefly eases neck rotation, I use that opportunity to help the patient practice movement and strengthen the muscles needed to maintain function. If an intervention does not lead to meaningful improvement, we reassess. If the findings indicate significant neurological disease, infection, fracture, or vascular pathology, the correct action may be referral rather than another adjustment. This is how chiropractic practice can fit responsibly within an integrative medical model.
What the Latest Evidence Says About Manual Therapy and Exercise
The clinical literature is encouraging in some areas and uncertain in others. In a 2025 Cochrane systematic review, Chacko and colleagues examined manual therapy combined with exercise for adults with neck pain. Compared with no treatment, the combination may meaningfully improve pain and function. Compared with placebo, the review found a more limited effect: a moderate functional improvement was possible, but pain reduction was not clearly demonstrated for the primarily chronic cases studied. The review also identified limitations in study quality, reporting, and the evidence base for acute neck pain (Chacko et al., 2025).
This matters because an honest article should not claim that chiropractic treatment cures all forms of neck pain. Evidence-based care means interpreting who was studied, what the comparison treatment was, how long the benefits lasted, and how certain the results were. A treatment may be reasonable even when evidence is not perfect, but uncertainty should be disclosed. Shared decision-making involves discussing expected benefits, alternatives, risks, cost, and the patient’s preferences.
The 2017 neck pain clinical practice guideline from Blanpied and colleagues organizes treatment according to patterns such as mobility deficits, movement-coordination impairments, referred pain, and radiating pain. That framework supports selecting interventions according to findings rather than giving all patients the same set of techniques. It also emphasizes outcomes, patient participation, and the need to recognize serious pathology. These principles remain clinically relevant alongside the newer research.
I explain the difference between short-term symptom modulation and lasting recovery. A person may feel better immediately after massage or mobilization, but if the neck is deconditioned and the work environment remains demanding, symptoms can return. Exercise alone may be challenging when pain is highly irritable. A thoughtful combination can use a brief symptom-relief intervention to support gradual strengthening. The program’s value is judged by sustained function, not by how dramatic the treatment feels during the appointment.
Cervical Joint Mobilization and Low-Force Treatment Options
Joint mobilization uses controlled, usually slower movements within a comfortable range to address stiffness or movement-related pain. It may be selected when a patient is sensitive to sudden movements, prefers a gentler approach, or has clinical factors that make thrust techniques less attractive. Mobilization can target the cervical or thoracic region, depending on the examination. The clinician should explain why they are treating a particular area and what outcome is expected.
For example, a patient with limited cervical rotation but no neurological red flags may have muscular guarding and stiff movement patterns. Gentle mobilization, paired with active neck turns, may help the person explore a comfortable range. If the patient becomes markedly dizzy, develops unusual symptoms, or reports worsening neurological complaints, stop the technique and reconsider the diagnosis. Ignoring the patient’s reaction does not make treatment safer.
Low-force interventions can also help individuals who do not want manipulation. Some benefit from exercise instruction, soft-tissue care, or thoracic movement training without direct cervical thrust procedures. Choosing a different technique is not a failure of chiropractic care. It shows the clinician is tailoring treatment to the individual.
A good plan should specify the clinical reason for the intervention, the expected short-term change, and the method used to test that change. If the goal is improved rotation, measure it consistently before and after and track how it behaves over subsequent visits. If the goal is better tolerance for computer work, ask about work duration and symptom recovery rather than relying only on a treatment-table impression.
Soft-Tissue Therapy and Why Muscles Sometimes Remain Guarded
Soft-tissue therapies include several methods intended to address muscle discomfort and movement restriction. These may involve gentle massage, manual pressure, movement-assisted techniques, or other clinically appropriate interventions. Their effects may arise from sensory modulation, relaxation, altered muscle activation, or changes in the person’s willingness to move. Claims that routine massage permanently breaks up every adhesion or mechanically realigns every fiber usually exceed what clinicians can demonstrate.
Following a cervical strain, muscles may guard to protect a sensitive area. Repeated guarding can create soreness and fatigue. A brief course of soft-tissue treatment may reduce tenderness enough to permit comfortable exercise. However, working aggressively on highly irritable tissue can worsen symptoms. The appropriate dose depends on stage of healing, sensory sensitivity, medical history, and patient preference.
I use hands-on treatment as part of a sequence. We first identify the movement or activity the patient wants to regain. We select a technique that may make that task easier. We then repeat the task or practice a related exercise and check whether the change helps. This approach allows the intervention to support functional recovery instead of becoming an isolated ritual.
For a patient whose upper trapezius feels constantly tight, the longer-term solution may include shoulder strength, breaks from sustained work, improved sleep, and an appropriate activity plan. Massage can be useful, but it should not be described as the sole correction for a problem involving workload, nervous system sensitivity, and deconditioning. When tenderness is unexplained or accompanied by systemic warning signs, further medical evaluation takes priority.
Deep Neck Flexor Training and Cervical Movement Control
The small muscles that help control the head and neck can become less efficient when a patient experiences persistent pain. Deep cervical flexor training aims to improve low-load control and endurance, often using gentle nodding motions rather than large forceful movements. The goal is not to strengthen one magical muscle that solves all cervical pain. It is to restore coordinated participation of different muscles during ordinary tasks.
A patient may initially practice a small chin-nod movement while lying comfortably, keeping the jaw relaxed and avoiding excessive recruitment of large superficial muscles. Explain and supervise the exercise when first prescribed. If the movement triggers headache, severe discomfort, or neurological symptoms, it needs modification or reassessment. A person with high irritability may start with very brief holds, while a well-conditioned athlete may progress to more demanding endurance tasks later.
As tolerance improves, the program may incorporate rotation, resisted movements, and whole-body activities. Neck muscles work with the shoulder girdle and trunk during daily life. Training only in a lying position cannot fully prepare someone to lift boxes, drive, or play sports. Eventually, strengthening must resemble the activities the patient intends to resume.
Progress is monitored through movement quality, symptom behavior, endurance, and function. A patient who can hold a gentle nod longer but still cannot turn while driving may need a different emphasis. Rehabilitation is not a contest to perform the hardest exercise. It is the process of finding the right challenge, then increasing it as the person adapts safely.
Scapular and Thoracic Rehabilitation for Neck Pain
The neck does not move independently of the upper back and shoulders. The thoracic spine provides a base for cervical movement, while the scapular muscles help position the shoulder girdle during reaching, lifting, and desk work. When a patient holds the shoulders elevated or has reduced thoracic mobility, the cervical muscles may work harder than necessary for certain tasks. This connection supports examining the entire upper-quarter movement system.
A program might include comfortable thoracic extension, controlled shoulder-blade movement, rows, modified wall slides, or resistance training. I don’t prescribe these exercises because every person’s scapulae are “misaligned.” I choose them when testing shows a deficit in strength, endurance, control, or load tolerance. Too much corrective emphasis can make patients self-conscious about every posture. I prefer to teach useful movement options rather than demand an unnatural position throughout the day.
The training dose must fit the patient’s capacity. Someone recovering from acute whiplash may need a light band and a few comfortable repetitions. A construction worker preparing to return to repetitive lifting needs a more demanding progression. The program should account for shoulder pain, dizziness, cardiovascular fitness, and the person’s ability to practice consistently at home.
This is particularly important when a patient improves during clinic visits but struggles at work. The gap may reflect insufficient strength or endurance for the actual task. We then adjust the rehabilitation plan, perhaps adding graded carrying, reaching, or overhead activity. Real-world function is the outcome that ultimately matters.
Chiropractic Care for Neck Pain Relief | El Paso, TX (2025 Recovery Guide) Chiropractic Treatment- Video
Gradual Return to Activity Instead of Prolonged Rest
After a serious injury, temporary protection may be necessary. For many uncomplicated mechanical neck pain and whiplash presentations, however, prolonged inactivity is not a desirable long-term strategy. Muscles lose conditioning, movement confidence may fall, and ordinary tasks can begin to feel more threatening. The challenge is to distinguish safe movement from activity that could aggravate an unstable fracture, serious neurological disorder, or another condition requiring restrictions.
I describe rehabilitation as graded exposure. We start with an activity the person can perform safely and predictably, then increase its duration, range, resistance, or complexity. A patient who can turn the head only a little may practice comfortable motion several times during the day. A patient who can work at a computer for twenty minutes may build tolerance with breaks and progressively longer periods. The plan should not force the person through severe symptoms to prove toughness.
A temporary increase in symptoms can occur during exercise, especially after a period of reduced activity. The clinician and patient agree on reasonable limits and reassessment criteria. If soreness worsens progressively, lasts unusually long, or is accompanied by neurological changes, the program is modified. Pushing through new weakness or severe radiating pain is not an evidence-based requirement for recovery.
The same approach applies to returning to recreation. Walking may be an early step; strength training and sport-specific tasks may follow. Progress is individualized rather than dictated by an arbitrary number of visits. This respects the fact that tissue healing, pain sensitivity, conditioning, and social demands do not always change at the same pace.
Cervical Traction and Decompression: Selecting Patients Carefully
Cervical traction uses a controlled pulling force intended to temporarily reduce compressive loading or alter symptoms in some patients with cervical conditions. Consider it for selected cases of radicular pain when assessment suggests possible benefit and contraindications have been excluded. The treatment’s effectiveness depends on the diagnosis, dosage, technique, and the patient’s response. It should not be advertised as permanently restoring the original height or structure of every damaged disc.
The clinician must assess whether traction is appropriate. Instability, certain fractures, severe osteoporosis, significant spinal cord compromise, and some other conditions may make it unsuitable. A patient with increasing neurological deficits requires more than routine decompression sessions. During treatment, the clinician monitors symptom behavior. Improvement in arm symptoms might support continuing a cautious trial; worsening weakness or spreading numbness calls for reassessment.
If traction provides temporary relief, it may support active rehabilitation rather than replace it. The patient still needs strategies to manage daily loading and regain cervical and shoulder function. Insurance documentation and medical-necessity decisions should reflect the specific indication, expected measurable benefit, and response. Simply owning a decompression device is not proof that treatment is needed.
For radiculopathy, the evidence remains mixed, and the stronger clinical message is to use a thoughtful multimodal plan rather than promise that traction is a cure. Patients should understand the uncertainty and alternatives, including exercise, medical evaluation, medication when indicated, and specialist consultation for persistent or progressive problems.
Acupuncture, Heat, Cold, and Other Adjunctive Neck Pain Treatments
Many people ask whether acupuncture, heat, cold, electrotherapy, laser, or shockwave can make the neck heal faster. These modalities differ in mechanism, evidence quality, intended use, cost, and risk. They should not be grouped as proven tissue-regeneration treatments. For uncomplicated neck pain, some may provide temporary symptom relief. That can be clinically valuable if it helps a patient sleep or engage in exercise, but the rationale must remain realistic.
Heat may feel soothing for muscular guarding and stiffness. Cold can help with short-term comfort after an acute strain when the person prefers it. Neither is a substitute for evaluation after significant trauma. Acupuncture may be considered as a symptom-management option for certain patients, with attention to provider training, bleeding risk, and patient preferences. Electrical stimulation or photobiomodulation may be proposed in selected settings, but the evidence for specific cervical diagnoses and protocols varies.
A common problem arises when several passive modalities are scheduled indefinitely without clear measures of benefit. The patient may report that the session feels relaxing but still misses work and avoids everyday activity. This should trigger a reconsideration of priorities. A useful adjunct demonstrably supports a defined goal and does not displace more important care.
In the clinic, I prefer to explain each tool in plain language. We identify the proposed mechanism, the evidence supporting that use, the risks, the expected duration of benefit, and the endpoint for continuing or stopping it. More treatments do not automatically mean better treatment. A coordinated plan is valuable because it reduces unnecessary or overlapping procedures.
Medication, Injections, and Specialty Care as Parts of a Nonsurgical Strategy
An integrative clinic should not treat medication as a failure. Some patients need short-term analgesics or other medical treatment so they can sleep, move, and participate in rehabilitation. Appropriate medication choices depend on age, kidney function, gastrointestinal risk, cardiovascular disease, medication interactions, pregnancy, and other clinical factors. Opioids are generally not first-line long-term treatment for uncomplicated mechanical neck pain because their risks can outweigh sustained benefits.
For selected patients with persistent radicular pain or specific pain generators, a specialist may consider an injection-based procedure. Such decisions require diagnostic clarity, discussion of the quality of evidence, and informed consent. A cervical epidural steroid injection, for example, has specific risks and indications. It is not equivalent to a routine chiropractic procedure and should be performed only by appropriately qualified clinicians in an appropriate setting. Temporary pain relief does not necessarily mean the underlying anatomy has returned to normal.
Surgical consultation is appropriate when serious neurological compromise is suspected or when selected structural conditions fail a reasonable course of nonsurgical management. The purpose of the consultation is not automatically to schedule surgery; it is to compare options based on neurological status, imaging, functional impact, prognosis, and patient preference. Recent evidence reviews show that neither surgery nor nonsurgical care is superior for every person (Dar et al., 2026; Kale et al., 2026).
Dr. Cardenas’s medical oversight and my nurse practitioner role are relevant because medical comorbidities, medication safety, and referrals may need coordination alongside rehabilitation. The patient benefits when the team knows who is responsible for each decision and communicates changes promptly. Integrated care should increase accountability, not obscure it.
Functional Medicine, Nutrition, and Recovery Without Overpromising
Functional medicine in an injury-care context can be understood as a structured interest in lifestyle, nutrition, sleep, physical activity, medical history, and factors that may affect resilience or recovery. The most useful questions are concrete. Is the patient eating adequately while recovering? Is a sleep disorder reducing daytime capacity? Does diabetes affect neurological symptoms? Is a medication contributing to dizziness? Does the person need help building a sustainable exercise routine?
A balanced dietary pattern, adequate protein, appropriate energy intake, hydration, and correction of documented nutritional deficiencies support general health. However, no single supplement has been established as a reliable cure for whiplash, a cervical disc herniation, or personal-injury-related neck pain. Routine extensive laboratory panels without a clinical indication can create misleading findings and unnecessary expense. I distinguish evidence for general health from evidence that a specific nutritional intervention repairs a particular cervical tissue.
Sleep, tobacco exposure, physical activity, and stress management are reasonable topics because they affect overall health and may influence treatment participation. For someone whose recovery has slowed due to poor conditioning, gradual resistance training may matter more than adding another passive procedure. For someone with a medical illness, coordination with the treating physician may be the highest priority.
The interdisciplinary purpose is to identify modifiable contributors while avoiding the claim that every chronic symptom has one hidden metabolic cause. We can be curious without being speculative. Patients deserve a clear explanation of which recommendations are well supported, which are optional adjuncts, and which remain uncertain.
Coordinated El Paso Care With Dr. Alexander Jimenez and Dr. Maria Guadalupe Cardenas
At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, the care model combines chiropractic, advanced practice nursing, medical direction, and rehabilitation. I serve as Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, bringing chiropractic assessment and family nurse practitioner training into the management of musculoskeletal and related medical presentations. Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of experience, serves as the practice’s Medical Director and Collaborative Physician. Her verified National Provider Identifier is 1164426748, and her Texas medical license number is J2933.
Dr. Cardenas’s medical role may include evaluating systemic illness, reviewing medications, providing medical direction, assessing risk, coordinating diagnostics, and making appropriate referrals. My work emphasizes cervical biomechanical evaluation, relevant neurological and medical assessment within my licensed responsibilities, nonoperative treatment planning, and functional rehabilitation. In a complicated case, the team can connect the physical findings with chronic disease management, imaging needs, and rehabilitation milestones. This is a recognizable multidisciplinary model in integrative and injury care; it does not imply that every service is appropriate for every patient.
For example, imagine an older patient who has neck pain after a collision, takes anticoagulant medication, reports intermittent hand numbness, and wants to return to caring for a spouse. A careful plan must do more than address muscle tenderness. We need to review trauma-related risks, investigate neurological symptoms, coordinate medication considerations, and choose safe exercise and manual options. If imaging or specialist consultation is needed, it should occur before treatment that might be unsafe.
The benefit of coordination is a shared, updated clinical picture. Each team member contributes expertise without automatically declaring that every complaint has the same cause. The patient’s goals remain central: reducing pain where possible, improving safe movement, preventing avoidable harm, and restoring participation in daily life.
Clinical Observations Published by Dr. Jimenez and How to Interpret Them
In my publicly available El Paso Back Clinic writing, I have emphasized three recurring observations: understanding the mechanism of injury, documenting the patient’s baseline, and revising treatment based on measured function rather than a rigid schedule. The clinic’s published materials describe a young manual laborer whose recovery from one collision was complicated by a later collision. The purpose of discussing that example is not to generalize one patient’s outcome to everyone. It shows why a second event requires a fresh examination instead of simply extending the first plan (Jimenez, n.d.).
The same clinical writings discuss delayed recognition of symptoms after some crashes. A patient who had the head turned toward a window may describe a different sequence of stiffness and headache from someone looking straight ahead. Such observations can guide the questions I ask. They do not establish a universal rule that delayed pain is always traumatic or that all low-speed collisions cause cervical damage. Clinical experience generates hypotheses, but causation must still be supported by the relevant record and scientific reasoning.
I also describe cervical injury cases in which a focused examination and advanced imaging became important after persistent symptoms. These reports highlight the value of asking whether the original working diagnosis still fits. If a patient develops new radicular findings, continued treatment for uncomplicated strain without reassessment may be inadequate. Conversely, if repeat examinations show improvement and no concerning features, escalating to imaging or procedures may add little value.
A single clinic observation cannot prove efficacy in the way a well-designed randomized trial can. Natural recovery, patient selection, co-interventions, expectations, and other influences can change outcomes. I therefore present published clinical observations as practice-based perspectives, not controlled research. Their strongest contribution is explaining how a treating clinician organizes questions, documents change, and knows when a plan must be adjusted.
Neck Pain After Personal Injury: Why Medical Causation Must Be Explained
Medical causation asks whether a particular event caused or materially contributed to a particular medical condition. It is distinct from a medical diagnosis. A clinician may accurately diagnose cervical radiculopathy and still be unable to determine from the available information whether a recent motor vehicle collision caused it, aggravated an earlier disorder, or happened near the time when symptoms emerged for another reason. The difference is not technical wordplay. It protects the reliability of clinical opinions and makes medical records more useful to patients, insurers, attorneys, and courts.
In a Texas personal injury lawsuit, a plaintiff generally must establish that the defendant’s legally relevant conduct caused the event and that the event caused compensable injury. JLG Trucking, LLC v. Garza (2015) emphasizes the importance of evaluating other potentially causal events, including a later collision. In Guevara v. Ferrer (2007), the Texas Supreme Court explained that expert medical causation evidence is generally required for conditions outside the common knowledge and experience of ordinary jurors. The court also recognized a narrower category of obvious injuries and logically traceable events for which lay evidence can sometimes support causation.
Therefore, it would be inaccurate to say that every minor neck strain requires the same type of expert testimony, or that chronology alone proves all cervical diagnoses. A simple visible injury and a complex assertion that an accident caused disc pathology, neurological deficits, and years of treatment raise different evidentiary demands. Legal causation, medical causation, and medical necessity must each be addressed appropriately in the specific case, with qualified legal advice on the applicable rules.
A well-supported medical opinion should clearly state its assumptions. It identifies the diagnosed condition, reviews relevant history, explains why the event could cause or aggravate it, discusses whether the timing and findings fit, and evaluates reasonably supported alternatives. It should distinguish what is known from what remains uncertain. In court, confidence cannot be a substitute for evidence.
The Difference Between a New Injury and an Aggravated Preexisting Condition
Many patients have cervical degeneration, previous minor strains, or an earlier history of intermittent pain. A later accident may cause a new injury, aggravate an existing condition, or have no demonstrated causal relationship to the symptoms under review. Distinguishing these possibilities can be difficult because imaging findings often predate symptoms and medical records may be incomplete. The clinician must be willing to describe more than one contributing factor when the evidence supports it.
Suppose a patient had an old MRI showing a small disc protrusion but worked full-time without arm symptoms or restrictions. After a collision, the patient reports new radiating pain and weakness, and examination identifies a new neurological deficit. The sequence raises a medically reasonable question of traumatic aggravation, especially if the findings are consistent and alternative explanations are considered. It does not prove that the collision newly created the protrusion. The appropriate opinion may involve an exacerbation of symptoms or a superimposed injury rather than an assertion that the entire degenerative condition began on the accident date.
Now consider another patient who had substantial neck and arm symptoms for months before a collision, with little documented change afterward. A crash alone should not transform all preexisting treatment into accident-related care. A sound analysis must compare before-and-after function, symptom quality, objective findings, healthcare utilization, and other exposures. This protects the integrity of care even when the conclusions are less certain than a party might prefer.
A treating clinician can document changes and offer opinions within the limits of training and available evidence. Complex causation questions may require specialists, biomechanical expertise, or other qualified experts. We should not confuse a persuasive medical narrative with proof that every related expense was necessarily caused by one event.
The Four-Part Clinical Chain Connecting an Accident to Cervical Injury
One useful way to organize a medical causation analysis is to examine four connected questions. What happened? What condition exists? Is there a plausible mechanism connecting the event to the condition? What other explanations need consideration? This approach does not replace the legal standard, but it helps the clinician avoid circular reasoning and maintain an evidence-based structure.
First, reconstruct the event from reliable sources. The history may include the direction of impact, vehicle position, head rotation, restraint use, airbag deployment, the patient’s activities, and immediate responses. In workplace incidents, the details may involve lifting, falling, twisting, or being struck. Second, define the condition through history, examination, and tests when warranted. “Neck pain” is not interchangeable with “C5-C6 disc extrusion” or “cervical radiculopathy.” Each diagnosis carries a different degree of specificity and requires an appropriate foundation.
Third, evaluate biological plausibility. A rapid acceleration-deceleration mechanism can be compatible with cervical soft-tissue injury, but the mechanism alone cannot determine the injury. A fracture generally calls for imaging and clinical evidence; nerve-root injury requires neurological and sometimes imaging correlation. Fourth, examine alternative causes, including prior symptoms, age-related changes, other accidents, inflammatory conditions, nerve entrapment, and events occurring during recovery.
The conclusion should match the evidence. It may be reasonable to describe a soft-tissue strain as consistent with an accident while remaining uncertain whether a chronic disc abnormality was newly produced. It may also be reasonable to find that a second event caused a new deterioration. Responsible opinions can contain uncertainty. Causation is an investigation, not a slogan.
Why Symptom Timing Helps but Does Not Prove the Cause
Temporality means that one event occurred before another. If a person had no neck pain on Monday, was involved in a collision on Tuesday, and sought care for new pain on Wednesday, that sequence is important evidence. It does not automatically show that every later diagnosis was caused by the collision. Other factors may have contributed, and some findings may have existed before the event without causing symptoms. At the same time, an absence of immediate severe pain does not prove that an injury is unrelated to trauma.
A careful timeline separates the first symptom, the first medical contact, the date of a diagnosis, and the date of imaging. They may all be different. The first MRI may be obtained weeks after an accident, but the MRI date does not establish when a chronic disc feature developed. Similarly, a new diagnostic label may appear during treatment because testing became more specific, not because a new injury suddenly occurred on that date.
Documentation should describe any interval events. Did the patient return to heavy lifting? Was there a second collision, fall, or sports injury? Did a new symptom begin after a period of improvement? These details can be crucial when comparing competing explanations. The Texas Supreme Court’s discussion in JLG Trucking v. Garza (2015) makes the relevance of a later accident especially clear.
Patients benefit from keeping a truthful timeline rather than trying to make every detail fit a predetermined legal theory. A diary can record when symptoms occurred, what activities were possible, and which treatments were received. Accurate records are more persuasive than an implausibly perfect account that ignores ordinary variability or uncertainty.
Alternative Causation and Why Second Accidents Matter
Alternative causation does not mean that any hypothetical cause automatically defeats an injury claim. It means the evidence should support medically plausible explanations. If a patient was in two collisions, the clinician must investigate both. If the person developed arm symptoms before an accident, the timing deserves attention. If imaging reveals severe longstanding stenosis, that finding may be relevant even when the collision also contributed to symptoms.
In JLG Trucking v. Garza, evidence of a second collision was relevant to whether the first defendant’s conduct caused the damages being claimed. The court’s reasoning emphasizes that decision-makers should be able to consider evidence that bears on competing causal explanations. From a clinical perspective, a second event is an opportunity for a new baseline assessment. The clinician documents current complaints, compares prior examinations, and identifies any meaningful change in function or neurological status.
A later event does not necessarily erase the effects of the first one. A patient may have residual symptoms that were already improving when another injury occurred. The analysis should attempt to separate the effects when reasonably possible and honestly describe when the records do not allow precise allocation. Simply assigning all symptoms to the first event or all symptoms to the second creates an unreliable picture.
This is one reason I value repeated, standardized outcome measures. If cervical rotation, grip strength, and work participation were measured before and after each event, the resulting timeline may support a clearer explanation. The measurements are not infallible, but they can help establish that an actual functional change occurred, rather than relying only on memories reconstructed months or years later.
Imaging in Court: What an MRI Can and Cannot Establish
An MRI is powerful evidence about anatomy. It can identify a disc extrusion, neural compression, or spinal cord signal abnormality. But imaging usually cannot determine the exact age or cause of many degenerative disc findings. A post-accident MRI cannot be read as a timestamp automatically linking every abnormality to the collision. Even a clinically important finding may have predated the event. Conversely, many painful soft-tissue injuries have no dramatic MRI correlate.
The examiner should ask whether earlier imaging exists. A pre-event scan showing no particular disc lesion followed by a clearly new finding may strengthen a temporal argument, although differences in equipment, technique, and reporting still matter. Without an earlier scan, the reasoning must rely on the total clinical record. Discuss other possible contributors, such as age-related changes or previous symptoms, rather than concealing them.
Radiology language must also be used accurately. A disc bulge, protrusion, extrusion, and annular fissure are not interchangeable. A report describing mild foraminal narrowing cannot automatically justify a diagnosis of severe nerve injury. Conversely, clinical signs of nerve compromise deserve appropriate attention even if a static scan appears less impressive than expected. The patient’s history and examination remain essential.
Medical testimony should identify the evidence supporting each anatomical and causal assertion. If the clinician says a collision aggravated a preexisting disc condition, the explanation should describe how the symptoms or findings changed and why that interpretation is more plausible than other supported possibilities. The law demands a sound basis for complex medical claims, not merely the presence of an image in the file (Guevara v. Ferrer, 2007).
Chiropractic Records as Evidence of Functional Change
Chiropractic records can contribute meaningfully to a personal injury case because they often document repeated observations over time. A well-maintained file may include the initial mechanism history, symptom maps, cervical range of motion, neurological examination, functional limitations, treatment plan, patient-reported response, re-evaluation results, and referral decisions. These details may help explain what was present at different recovery points.
The strongest records are not necessarily the longest. Specificity and consistency matter. “Patient better” is less informative than a note documenting that the person now turns the head sufficiently for a particular task, sleeps with fewer interruptions, and has improved a standardized disability score. A significant new complaint should lead to a revised examination or appropriate referral rather than being copied into a repetitive template. Do not invent or exaggerate objective findings.
Careful records also distinguish treatment response from causation. If a patient improves after mobilization and exercise, that may justify continuing a time-limited plan. It does not prove that a specific collision created the underlying disorder. The patient might have improved through natural healing, active rehabilitation, other medical care, or a combination of factors. A transparent clinician explains these limits while still documenting observed progress.
A medical-legal report should also separate facts, patient reports, clinical interpretations, and opinions. For example, a patient can report that a collision occurred at a certain speed. Still, unless the clinician has an appropriate independent basis, the medical report should not present that estimate as an established engineering fact. Accurate source attribution makes the record more trustworthy.
Medical Necessity, Reasonable Care, and Maximum Medical Improvement
Medical necessity asks whether a particular service is appropriate for an identified clinical problem and whether its expected benefit justifies its use. It is distinct from whether the condition was caused by an accident. A patient may have an accident-related injury yet receive a treatment that is not supported by the clinical findings. Another patient may appropriately require treatment for a condition unrelated to the incident being litigated. These questions should not be collapsed into one conclusion.
A reasonable plan states the diagnosis, functional goals, treatment methods, frequency or trial period, expected measurable outcomes, and reassessment schedule. Care may be more frequent when symptoms are highly irritable or function is greatly restricted, then taper as the patient learns a home program. No scientifically defensible universal number of visits applies to every neck injury. When a patient is not improving, repeating the same intervention indefinitely without reconsidering diagnosis or goals is difficult to justify.
Maximum medical improvement, or MMI, commonly refers to a stage of relative medical stabilization, though its formal meaning depends on the legal or administrative context. It should not be confused with complete recovery, absence of pain, or restoration of elite athletic performance. A person may reach MMI while retaining limitations or needing general conditioning. A different person may recover full function before an expected administrative timeline.
Documentation should explain why treatment ends, changes, or shifts to a self-management program. A conclusion that the patient has improved should be supported by symptom trends, functional measurements, examination findings, and the individual’s goals. In court or an insurance review, such explanations are more meaningful than unsupported declarations that every procedure was necessary solely because it was performed.
Treating Clinicians, Expert Witnesses, and the Limits of a Medical Opinion
A treating clinician observes symptoms, performs examinations, makes diagnoses, prescribes or recommends care within the applicable scope, and monitors response. An expert witness may be asked to explain specialized medical questions under legal evidentiary rules. One person may serve both roles in a particular case, but a treatment relationship does not automatically qualify someone to opine on every biomechanical, neurological, economic, or legal subject. Qualifications and the opinion’s foundation matter.
For a straightforward cervical strain, clinical history and examination may be sufficient for many care decisions. A case alleging a highly specific traumatic disc injury, complex nerve damage, permanent disability, or causation after multiple incidents may require a more detailed analysis and specialized expertise. The exact testimony required depends on the claims and governing law. The Texas Supreme Court has repeatedly stressed the distinction between conditions familiar to ordinary experience and complex medical questions that require expert evidence (Guevara v. Ferrer, 2007; JLG Trucking v. Garza, 2015).
A responsible opinion uses appropriately qualified evidence and avoids certainty beyond the record. The clinician may need to say that symptoms are consistent with a collision. Still, the available data cannot definitively distinguish a new disc injury from aggravation of a preexisting condition. Such candor does not undermine the purpose of healthcare. It keeps treatment and documentation trustworthy, regardless of which party requested the report.
For patients, the practical message is that good medical care and good legal documentation overlap, but they are not identical. Health and safety come first. The record should accurately describe the patient. Legal professionals evaluate how that record fits the claims and burdens of proof. This division of responsibilities improves the quality of both clinical and courtroom decisions.
A Hypothetical Rear-End Collision With Delayed Neck Pain
Consider an educational scenario in which a person is stopped at a traffic light, and another vehicle strikes the rear bumper. At the scene, the driver is shaken but reports no significant pain. The following morning, the driver notices cervical stiffness, aching toward the shoulders, and headache. The history is compatible with a possible whiplash-associated disorder, but it does not establish the diagnosis. The first step is to ask about head injury signs, new neurological symptoms, the precise sequence of complaints, and any immediate medical evaluation.
A clinician performs an appropriate physical and neurological examination and decides whether the trauma meets criteria for imaging. If no serious findings are present, a conservative plan may include education, gentle movement, symptom management, and progressive exercise. The patient identifies specific functional goals, such as driving safely, returning to work, and sleeping without repeated awakenings. At re-evaluation, we compare baseline and current measures. If headache symptoms change or arm weakness emerges, we must reconsider the diagnosis and plan.
If a lawsuit follows, the medical record can describe a plausible mechanism, symptoms appearing close to the event, relevant examination findings, and the observed course. It should not imply that delayed symptoms prove a disc tear or that lack of immediate pain excludes trauma. In this hypothetical example, the strength of the causation opinion depends on the total evidence, including prior cervical problems and other possible causes. This is an illustrative scenario, not an actual patient record or a promise about a legal outcome.
A Hypothetical Construction Worker With Preexisting Cervical Degeneration
Imagine a construction worker who previously had occasional neck soreness but completed normal lifting tasks and had not missed work. After a fall, the worker reports a new pattern of arm pain and trouble gripping tools. Imaging reveals degenerative narrowing and a disc abnormality. The challenge is to determine which symptoms and limitations were present beforehand, whether the fall caused a new injury or aggravated an existing disorder, and whether current neurological deficits correlate with the available imaging.
The immediate clinical priority is safety. The clinician examines strength, sensation, reflexes, gait, and possible cord signs. The clinician arranges appropriate imaging or referral when indicated. Rehabilitation is planned around the worker’s demands, progressing from tolerable movement to carrying, reaching, lifting, and job-specific tasks. Care is modified if neurological symptoms worsen. A worker with a persistent neurological deficit should not be returned to hazardous activity merely because resting pain has improved.
From a causation standpoint, the historical record matters. Prior treatments, work ability, absence or presence of arm symptoms, and examinations before the event may help identify an actual change. The clinician can explain that degeneration and trauma may coexist, but should not represent a new MRI as proof that the entire anatomical condition began with the fall. In this way, careful medicine can support an honest analysis without minimizing the worker’s experience.
A Hypothetical Patient With Two Accidents During Recovery
In another educational example, a patient begins care after a collision with documented cervical pain, reduced rotation, and difficulty sleeping. Over several weeks, the person improves substantially and returns to most daily activities. Before complete recovery, a second collision occurs. The patient then reports new arm symptoms and a return of severe headaches. A clinician who assumes that all symptoms belong to the original injury may miss a new problem. A clinician who attributes every complaint to the second event may ignore documented residual deficits from the first.
The appropriate response is a new assessment. We preserve the pre-second-accident records, document the second event and symptom chronology, repeat relevant neurological and functional tests, and decide whether imaging or specialist care is needed. The resulting comparisons may clarify which problems were improving and which appeared or worsened after the new trauma. They may also reveal limitations in what can be apportioned medically.
This scenario reflects the broader clinical lesson illustrated by published observations on El Paso Back Clinic and the legal relevance of later accidents discussed in JLG Trucking v. Garza (2015). Thorough records can help explain change, but they should not manufacture certainty where events overlap. The primary purpose remains appropriate care after each injury.
Building a Sustainable Neck Health Routine After the Acute Phase
Once a clinician has excluded serious pathology and established a suitable plan, recovery increasingly depends on habits patients can control. I encourage a simple, repeatable wellness routine rather than a complicated list of treatments that requires constant supervision. Adjust the routine to symptoms, diagnosis, and occupational or athletic demands. It must not replace medical follow-up for progressive neurological deficits or other red flags.
A reasonable framework may include:
Daily movement variety: Change positions periodically and use comfortable neck and shoulder movements.
Progressive strengthening: Build cervical, scapular, and general muscular capacity with an individualized program.
Aerobic activity: Walk, cycle, or perform another appropriate activity to support conditioning and participation.
Sleep consistency: Address barriers to rest, including pain, medications, and possible sleep disorders.
Workstation adaptation: Arrange equipment to reduce unnecessarily prolonged or awkward exposure without obsessing over perfect posture.
Symptom tracking: Record functional gains and important changes, not only pain fluctuations.
Follow-up when needed: Seek reassessment for new deficits, loss of progress, or failure to meet goals.
In early recovery, the routine may be brief. The person might practice a few comfortable turns, walk for several minutes, and use gentle shoulder exercises. Later, the program may include resistance training, longer walks, work simulation, or sport-specific conditioning. Progression should be based on response, not a calendar alone. The aim is to reduce dependence on recurring passive treatment and build confidence in managing normal symptom variations.
Frequently Asked Questions About Neck Pain and Chiropractic Care
Can neck pain cause headaches?
Neck disorders can contribute to certain headache patterns, including cervicogenic headache, but migraine and other primary headaches can also cause neck discomfort. Location and muscle tenderness alone do not confirm the source. Evaluation is especially important for a new, severe, or unusual headache, or when neurological symptoms accompany it.
Can neck pain cause tingling in the fingers?
Yes, cervical radiculopathy may produce tingling or numbness in an arm or hand. Yet peripheral nerve entrapment, diabetes-associated neuropathy, and other disorders can cause similar symptoms. A focused neurological examination helps determine the next step. Progressive objective weakness warrants prompt medical attention.
Does a normal MRI mean the pain is imaginary?
No. Many painful muscle, ligament, joint, and sensitization-related conditions do not create a dramatic MRI finding. Imaging is one piece of evidence. Interpret a normal or relatively unremarkable scan alongside the patient’s history, examination, and functional limitations. It does not automatically prove or disprove accident-related causation.
Can a chiropractor treat neck pain without making adjustments?
Yes. Chiropractic care can include assessment, education, exercise, low-force mobilization, soft-tissue techniques, and referral coordination. Not every patient needs a thrust adjustment. Treatment selection should consider safety, patient preference, diagnosis, and objective response.
How quickly should neck pain improve after a collision?
There is no universal timeline. Many uncomplicated cases improve over weeks, while some people develop persistent symptoms. Prognosis depends on injury severity, neurological findings, prior health, symptom burden, sleep, psychosocial factors, and participation in rehabilitation. A lack of expected progress should prompt reassessment rather than repeating the same intervention endlessly.
Is chiropractic care safe for every cervical condition?
No. A suspected fracture, instability, spinal cord compromise, vascular disorder, infection, or certain other conditions may make cervical manipulation inappropriate. A clinician must screen for red flags and discuss risks and alternatives. Selecting exercise, low-force care, or referral can be the safest option.
Does improvement after chiropractic care prove the accident caused the injury?
No. Treatment response can show that symptoms or function changed during care, but it does not independently establish the cause of the original condition. A medical causation opinion requires the history, examination, relevant investigations, a plausible mechanism, and consideration of alternatives.
What if neck pain started several days after the accident?
Delayed recognition of symptoms can occur. Document the timing honestly alongside the mechanism, other injuries, activities between the event and onset, and any subsequent medical findings. Delay does not prove or automatically disprove the relationship. Sudden severe or worsening neurological symptoms still demand urgent evaluation.
When is surgery considered for cervical pain?
Surgical assessment may be indicated for significant spinal cord compression, progressive neurological impairment, selected structural disorders, or persistent symptoms that have not responded to appropriate conservative care. A consultation helps compare options. Most uncomplicated mechanical neck pain does not require surgery, while some serious conditions should not be managed conservatively without specialist input.
Can neck pain affect mood, concentration, and sleep?
Yes. Persistent pain can interrupt rest, increase fatigue, reduce concentration, and contribute to anxiety or depressed mood. These effects are real and relevant to treatment. They may also arise from separate medical or psychological conditions, so the assessment should not assume that every symptom has a cervical origin.
What should I document after a personal injury?
Record the event accurately, seek needed medical care, preserve relevant records, and report symptoms and functional changes truthfully. During treatment, standardized measurements, meaningful goals, and clear notes on progress or setbacks can help. Do not invent details or pressure a clinician to assign a diagnosis that the evidence does not support.
Can someone with old degenerative changes still have a new injury?
Yes. Degenerative features and a new traumatic condition may coexist. A collision may also aggravate a previously symptomatic or asymptomatic disorder. The conclusion must rest on a before-and-after comparison, mechanism, examination, imaging when relevant, and alternative explanations, not on the presence of degeneration alone.
Conclusion: Evidence-Based Neck Pain Care That Restores Function and Respects the Facts
Neck pain can influence much more than a small region of the spine. The cervical system helps coordinate movement, sensation, vision, balance, work, recreation, and sleep. Pain may arise from muscles, joints, discs, nerves, or other conditions, and overlapping symptoms require a careful differential diagnosis. The best plan begins with safety, explains the findings in understandable language, and uses measurable goals to guide progress.
Chiropractic care, when properly selected, can contribute to a comprehensive nonsurgical strategy that includes patient education, gentle manual treatment when appropriate, therapeutic exercise, progressive strengthening, and practical lifestyle support. The evidence is strongest for a measured, individualized approach rather than claims that one technique cures every condition. Medical assessment and specialist care remain essential when the diagnosis or the patient’s safety requires them.
At Injury Medical Clinic PA in El Paso, I integrate the chiropractic and rehabilitation perspective with my advanced practice nursing training and the medical oversight of Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. Together with the broader team, we aim to address mechanical, neurological, functional, and medical concerns without confusing association with causation or treatment response with proof of an accident-related injury.
For personal injury patients, an accurate record of the mechanism, baseline function, diagnosis, alternative explanations, treatment response, and changes over time can help explain the injury in a clinically and legally responsible manner. The same commitment to accuracy that protects the patient also makes the evidence more useful in court. The ultimate goal is to help each person regain safe movement, independence, and confidence while remaining candid about the limits of available knowledge.
Blanpied, P. R., Gross, A. R., Elliott, J. M., Devaney, L. L., Clewley, D., Walton, D. M., Sparks, C., & Robertson, E. K. (2017). Neck pain: Revision 2017. Journal of Orthopaedic & Sports Physical Therapy, 47(7), A1-A83.
Chacko, N., Gross, A. R., Miller, J., Santaguida, P. L., Burnie, S. J., Gelley, G. M., Paquin, J. P., Duranai, M. R., Langevin, P., Chopra-Tandon, N., Chak, N. T., Hoving, J. L., & Bobos, P. (2025). Manual therapy with exercise for neck pain. Cochrane Database of Systematic Reviews, 2025(12), CD011225.
neck pain treatment El Paso, cervical spine pain, neck pain symptoms, neck pain comorbidities, chiropractic care for neck pain, integrative chiropractic El Paso, whiplash injury recovery, car accident neck injury, personal injury medical causation, Texas medical causation, cervical radiculopathy, cervical disc injury, cervical myelopathy warning signs, cervicogenic headache, occipital neuralgia, chiropractic rehabilitation, neck pain physical therapy, nonsurgical neck pain treatment, functional medicine and neck pain, cervical spine MRI, medical documentation after car accident, accident related neck pain, Dr Alexander Jimenez, Dr Maria Guadalupe Cardenas, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, El Paso Back Clinic, neurological examination, deep neck flexor exercise, spinal manipulation safety, neck pain and sleep, neck pain and stress, cervical injury causation, Texas personal injury evidence
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine