The One-Sided Carry: What a Laptop Bag, Tool Case, or Work Tote Can Do to Your Back and Hips
Abstract: A laptop bag, tool case, or work tote may feel harmless because each trip is short. But carrying the same load on the same side can change how your trunk, shoulder, hips, and legs share the work. This article explains asymmetrical loading, what clinicians look for, and practical ways to redistribute load and build capacity.
The Bag Is Not “Putting Your Spine Out”
Picture a network engineer leaving a parking lot with a laptop bag over the right shoulder. The bag is not extremely heavy, and the walk is only ten minutes. Yet by Thursday, the right shoulder feels elevated, the left low back feels tight, and one hip seems tired on stairs.
That pattern does not prove the bag has “misaligned” the spine. A better explanation is compensation.
When weight hangs on one side, the body has to keep the center of mass controlled while walking. The trunk may lean or stiffen, one shoulder may elevate, the pelvis may shift, and the hips may produce different forces from side to side. Classic biomechanical research found that asymmetric load carriage changed trunk muscle demands and hip and knee moments during walking (DeVita et al., 1991). Human bodies tolerate asymmetry every day. Concern grows when repetition exceeds a person’s strength, endurance, recovery, or tissue tolerance.
Why Repetition Matters More Than One Carry
Load-carriage research shows that load size and placement can alter posture, walking mechanics, and balance. A systematic review of backpack studies found changes such as more trunk flexion, altered hip and ankle motion, shorter strides, and higher cadence while carrying loads (Liew et al., 2016). Another systematic review found that load carriage can reduce postural stability, with load magnitude and placement influencing the effect (Martin et al., 2023).
These studies do not mean every worker carrying a bag will develop pain. They support a practical idea: the body adapts to repeated demands.
Think about the total “dose”:
How heavy is the bag?
How far do you carry it?
How many times per shift?
Do you always use the same side?
Are you climbing stairs or walking uneven ground?
Are you already fatigued from sitting, lifting, driving, or poor sleep?
Do you have enough trunk, hip, and shoulder endurance for the task?
A moderate load repeated many times can become more meaningful than one unusually heavy carry.
What Your Trunk and Hips Do With an Uneven Load
Carrying involves a coordinated system that includes the rib cage, spinal muscles, pelvis, hips, legs, and feet.
Trunk compensation
If a bag pulls downward on the right, your body may lean, brace, or rotate to keep its center of mass controlled. Some people stiffen through the torso; others allow more side-to-side motion. Either strategy can increase fatigue.
Shoulder elevation
A slipping strap can encourage shoulder hiking. Over time, neck and shoulder muscles may stay active longer than necessary, contributing to fatigue, tightness, headaches, or discomfort between the shoulder blades.
Hip loading
The hips help control the pelvis every time one foot leaves the ground. With an uneven load, one side may need to work differently to stabilize the body. Asymmetric carrying has been shown to change hip moments during walking, although the response depends on load, placement, speed, and the individual (DeVita et al., 1991).
Walking changes
People often shorten their stride, adjust cadence, change pelvic movement, or spend more time stabilizing when loads increase. These are normal adaptations, not proof of damage. Problems are more likely when the strategy becomes uncomfortable, inefficient, or difficult to recover from.
Signs the Carrying Pattern Deserves Attention
Occasional muscle fatigue is not automatically a medical problem. However, repeated symptoms that follow a predictable carrying pattern deserve a closer look.
Useful clues include:
pain that builds during or after carrying;
one shoulder consistently feeling higher or more tense;
aching on one side of the low back or outer hip;
symptoms that improve when the bag is removed or sides are changed;
reduced walking tolerance;
numbness, tingling, or weakness;
pain that changes how you climb stairs, bend, or lift.
Severe pain after trauma, progressive weakness, loss of bowel or bladder control, saddle-region numbness, fever, unexplained weight loss, or other major neurological or systemic symptoms require timely medical evaluation.
What a Chiropractic Assessment Should Actually Examine
At El Paso Back Clinic, the goal should not be to look at a shoulder bag and declare that the spine is “out.” A useful assessment asks what tissues and movements are struggling and why.
A clinician may examine spinal and hip range of motion, tenderness, neurological findings, gait, single-leg balance, trunk endurance, hip strength, shoulder mechanics, and how the patient carries. The examination may also consider work demands, prior injuries, training level, footwear, and recovery.
Watching the patient walk with the actual laptop bag or tool case can be especially informative.
Does the trunk lean?
Does the shoulder hike?
Does pain appear after several minutes?
Can symptoms improve by changing strap position, load distribution, or carrying side?
That information turns treatment from a generic back-pain plan into a task-specific rehabilitation strategy.
Treatment Should Improve Capacity, Not Create Dependence
For mechanical back or hip symptoms, chiropractic care may be one part of a broader plan to improve movement and reduce pain. Current guidance for chronic primary low back pain supports individualized nonsurgical care that can include education, structured exercise, and selected physical therapies such as spinal manipulation (World Health Organization, 2023).
The practical goal is to help the patient tolerate real life again.
A plan may include:
chiropractic manipulation or mobilization when appropriate;
hip and thoracic mobility work;
trunk endurance exercises;
progressive hip-abductor and gluteal strengthening;
loaded carries that gradually rebuild tolerance;
gait and stair training;
shoulder and scapular endurance work;
work-specific lifting and carrying practice.
If persistent musculoskeletal pain or muscle guarding limits rehabilitation, acupuncture or electroacupuncture may sometimes be added as an adjunct after appropriate evaluation. Evidence suggests electroacupuncture may reduce nonspecific low-back pain when combined with standard care, although certainty is limited and it should not replace diagnosis, exercise, or progressive conditioning (Hsieh et al., 2024).
The simplest fix is often not “stop carrying.” It is improving how you manage the load.
First, remove items you do not need. Bags can slowly collect chargers, tools, notebooks, bottles, and backup equipment.
Second, keep the load close to your body. A load that swings far from the trunk creates more movement to control.
Third, use two straps when practical. A well-fitted backpack can distribute load more evenly than a one-shoulder tote. For heavier occupational equipment, waist or hip support may help redistribute part of the load depending on the design.
Fourth, switch sides if the task requires one-handed or one-shoulder carrying. Changing sides doesn’t eliminate the load, but it reduces repetition of the same pattern.
Fifth, break long carries into shorter trips when possible. A rolling case or cart may be smarter than carrying everything at once.
Finally, build capacity. Stronger hips, trunk muscles, shoulders, and legs make carrying less costly. Progressive conditioning also respects autonomy: instead of telling patients their bodies are fragile, it teaches them how to prepare for the work they choose to do.
Coordinated Care for Back and Hip Symptoms in El Paso
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines chiropractic and medical training to evaluate mechanical, neurological, and broader health contributors to pain. When medical complexity requires oversight, he collaborates with Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of experience.
That integrated model supports three principles. Beneficence means choosing care that restores function and addresses the likely cause. Non-maleficence means starting with appropriate noninvasive, drug-free strategies when reasonable while recognizing when imaging, medication, injections, or referral may be needed. Autonomy means explaining findings clearly so the patient can decide how to proceed and coordinate with an existing medical team.
A laptop bag, tool case, or work tote is rarely the whole story. The useful question is whether repeated one-sided loading is exceeding your current capacity. When assessment, load redistribution, chiropractic care, rehabilitation, and progressive conditioning match your job’s actual demands, the goal isn’t just to feel better on the treatment table. It is to walk, carry, climb, work, and recover with confidence.
Why Your Back Hurts Monday After a Weekend of Yard Work, Cleaning, or Home Projects
Abstract
You felt fine Friday. By Sunday evening, the yard is clean, the garage is organized, and your lower back remembers every bend, lift, twist, and carry. Often, the issue is not one “bad lift.” It is a sudden workload jump that exceeds what your back, hips, and supporting muscles were prepared to handle. This guide explains why that happens, how to move safely through Monday, and when back pain needs prompt medical evaluation.
The Weekend Workload Jump
Monday through Friday, a desk worker may spend hours sitting. A data center employee may alternate between computer work and equipment checks. An Amazon employee may repeat familiar tasks their body has adapted to.
Then Saturday arrives.
Suddenly, that person spends hours raking, pulling weeds, scrubbing floors, painting, climbing ladders, lifting soil, carrying boxes, or moving furniture. Research links greater exposure to lifting and carrying, non-neutral postures, and combined mechanical demands with increased odds of chronic low-back pain (Jahn et al., 2023). That does not mean bending is dangerous. Dose, repetition, recovery, conditioning, and individual capacity matter.
A weekend project can compress a large amount of unfamiliar work into one afternoon.
Why Your Muscles Feel So Tired
Your spine does not work alone. Muscles of the trunk, hips, abdomen, and legs share the job of controlling movement and transferring force.
When you rake, vacuum, shovel, paint, or lift repeatedly, those muscles produce force again and again. As fatigue builds, movement may become less coordinated. You may reach farther, twist while carrying, rush transitions, or rely more on the lower back because the hips and legs are tired.
Next-day soreness can reflect muscle stress or irritated tissues. It does not automatically mean a disc “slipped” or something is permanently damaged.
Most low-back pain is classified as nonspecific, meaning clinicians cannot tie it to one dangerous structural disease or single injured tissue (World Health Organization [WHO], 2023). A careful examination is more important than guessing based on pain location alone.
Hip Mobility Helps Share the Load
Your hips help you squat, hinge, step, and rotate. If they are stiff after a week of limited movement or unprepared for hours of weekend activity, the body may borrow motion elsewhere.
Imagine lifting a bag of mulch. If your ankles, knees, and hips work comfortably, you share the task. If your legs fatigue, you may bend more through the lumbar spine or hold the load farther away.
That does not make spinal bending inherently harmful. The larger picture includes total workload, task variety, strength, recovery, previous symptoms, and individual response. The goal is enough mobility, strength, and confidence for your whole body to participate.
Monday Morning: Keep Moving, but Scale the Load
When your back feels stiff Monday morning, you may want to barely move. For many uncomplicated episodes, current guidance instead encourages staying active and continuing normal activities as tolerated (National Institute for Health and Care Excellence [NICE], 2016; WHO, 2023).
Try a graded Monday:
Before work, take a short walk and use gentle hip and trunk movements.
During sitting tasks, change position regularly instead of chasing one “perfect” posture.
When standing, shift your stance and take brief walking breaks.
When lifting, temporarily reduce load size, keep objects close when practical, and let your legs and hips share the effort.
Break large jobs into smaller sets instead of testing your back with one heavy effort.
If movement sharply increases leg pain, numbness, or weakness, stop and seek clinical guidance.
What Chiropractic and Rehabilitation Can Add
A useful back evaluation should do more than ask where it hurts. It should examine how you move and what your workday requires.
At El Paso Back Clinic, an integrative examination may include spinal and hip motion, neurological screening, strength, gait, lifting mechanics, symptom behavior, and the activities that triggered the flare. The goal is to identify what can be modified and what needs further medical investigation.
Guidelines support exercise, education, and selected manual therapies for low-back pain. Manual therapy, including spinal manipulation or mobilization, is best used within a broader plan that includes active rehabilitation rather than as a stand-alone solution (George et al., 2021; NICE, 2016).
For the right patient, chiropractic care may reduce pain and restore comfortable movement, making progressive exercise easier. Rehabilitation then builds the capacity that weekends and workdays demand.
Build Capacity, Not Fear
A good recovery plan does not teach you that your back is fragile. It helps you understand current capacity and gradually expand it.
That may include:
hip-hinge and squat patterns;
trunk endurance and control;
progressively heavier carrying;
pushing and pulling;
hip and thoracic mobility;
walking and aerobic conditioning; and
task-specific lifting for home or work.
This is beneficence in practical terms: care should help you function better, not simply chase a pain score. It also supports autonomy. You should understand what clinicians find, what options are available, and what each option can realistically accomplish.
Appropriate non-invasive care may help reduce unnecessary reliance on medications or invasive procedures for some nonspecific cases. Avoiding harm also means recognizing when conservative care is not enough.
Red Flags: When Back Pain Needs Urgent Care
Seek urgent medical evaluation if back pain comes with new or progressive neurological problems, especially:
increasing weakness in one or both legs;
numbness around the groin, inner thighs, or saddle area;
new loss of bladder or bowel control;
severe walking difficulty caused by neurological weakness; or
rapidly worsening numbness or coordination loss.
Suspected cauda equina syndrome requires urgent assessment and typically prompt lumbar MRI because delayed treatment can risk permanent neurological loss (American College of Radiology, 2021).
Back pain after major trauma, pain with fever, unexplained weight loss, a cancer history, significant immune suppression, or other serious systemic symptoms also deserve medical assessment. Red-flag screening separates ordinary mechanical flare-ups from conditions requiring different care.
Prepare for the Next Weekend
Build capacity during the week. Walk. Strength train. Practice lifting. Vary your sitting. Break long chores into shorter blocks. Alternate bending tasks with upright tasks. Use carts or ask for help with unusually heavy objects. Increase workload gradually instead of going from five quiet workdays to six nonstop hours of home renovation.
At Injury Medical Clinic PA in El Paso, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, combines chiropractic structural care, mechanical rehabilitation, and medical assessment as a Doctor of Chiropractic and board-certified Family Practice Nurse Practitioner. Dr. Maria Guadalupe Cardenas, MD, a board-certified Internal Medicine physician with more than 40 years of experience, serves as Medical Director, Clinical Director, and collaborative physician, providing medical oversight when symptoms, medications, metabolic conditions, laboratory findings, or risk factors require broader evaluation.
This integrated model keeps the patient in charge. Chiropractic and rehabilitation can address mechanical problems, while medical evaluation investigates symptoms that do not fit a routine musculoskeletal pattern. Care can coordinate with your existing medical team.
If Monday back pain repeats after active weekends, ask, “What workload am I asking my body to handle, and how can I build the capacity to handle it better?” That conversation can turn a frustrating Monday pattern into a practical plan for stronger lifting, easier sitting, better recovery, and more confidence when the next weekend project arrives again. Schedule a multidisciplinary evaluation if recurring pain is limiting work, home projects, sleep, or confidence.
Reversing Severe Lumbago and Disc Compression from Amazon Fulfillment Shifts
Abstract: Severe low-back pain after fulfillment work or delivery routes can feel like a one-way road toward surgery. Yet many cases deserve a careful conservative evaluation first. This guide explains how repetitive bending, sorting, vehicle vibration, and lifting can aggravate lumbago and disc-related pain; where mechanical alignment and selected non-surgical decompression may fit; how medical oversight screens red flags; and how Amazon workers can use practical lifting limits to reduce repeat flares.
When a Shift Starts Loading the Lumbar Spine
A warehouse associate may begin a shift feeling stiff. Hours later, repeated low-bin reaches, package twisting, sorting, pallet work, or lifting away from the body can turn stiffness into severe lumbago. Delivery drivers add prolonged sitting, road vibration, repeated cabin exits, carrying, and awkward curbside lifts.
The problem is often cumulative. When the trunk bends and rotates while a load stays away from the body, spinal muscles must generate more force to control movement. Repetition can fatigue those tissues and degrade movement quality. NIOSH treats load weight, reach distance, vertical height, twisting, lifting frequency, duration, and grip quality as factors that change lifting risk (NIOSH, 2024).
That matters because “safe lifting” is not one universal number. A box manageable at waist height may be too demanding on the floor, far from the body, poorly gripped, or lifted repeatedly near the end of a long shift.
Why Pain Can Spike After the Shift
Symptoms may intensify after clocking out because fatigued muscles provide less support, sitting stiffens the hips, and irritated tissues remain sensitive after repeated loading. Delayed soreness doesn’t mean a disc suddenly worsened. Track which movements, loads, positions, and recovery habits consistently increase or decrease symptoms across workdays.
What “Disc Compression” Really Means
Between the lumbar vertebrae, intervertebral discs distribute load and allow movement. A disc is not a jelly doughnut that simply pops out and can be pushed back into place. It is a load-bearing structure with a fibrous outer ring and softer inner region. Repeated flexion, compression, rotation, aging, prior injury, and anatomy can contribute to disc changes.
Pain may come from several overlapping sources:
Irritated lumbar joints or surrounding soft tissues
Protective muscle spasm and reduced hip motion
Disc-related inflammation or mechanical sensitivity
A disc herniation that irritates a nerve root
Deconditioning after repeated pain episodes and activity avoidance
This is why a structural examination matters. The goal is to match symptoms with movement findings, neurologic testing, work demands, and imaging when indicated. Low-back guidelines support exercise, education, and selected manual or mobilization approaches as part of conservative care rather than a single passive treatment (George et al., 2021).
Step One: Restore Motion Without Forcing the Spine
At El Paso Back Clinic, targeted mechanical care begins with a practical question: which movements are limited, painful, unstable, or poorly coordinated?
One worker may have stiff hips that force repeated lumbar bending. Another may have painful lumbar joints that limit extension. A driver can show a different pattern after hours of seated flexion and vibration.
Chiropractic adjustments and non-thrust joint mobilization may improve mobility and reduce pain when the examination supports them. Guidelines report benefit from joint mobilization for many people with chronic low-back pain, including some with leg symptoms (George et al., 2021). Care should pair manual treatment with rehabilitation so improved motion becomes usable strength.
The Functional Target
The patient gains something measurable: easier standing, smoother walking, less guarded bending, better sleep positions, safer transitions from a delivery van, and more confidence handling daily tasks. Those functional gains matter more than trying to make every spinal image look “perfect.”
Step Two: Use Non-Surgical Decompression Carefully
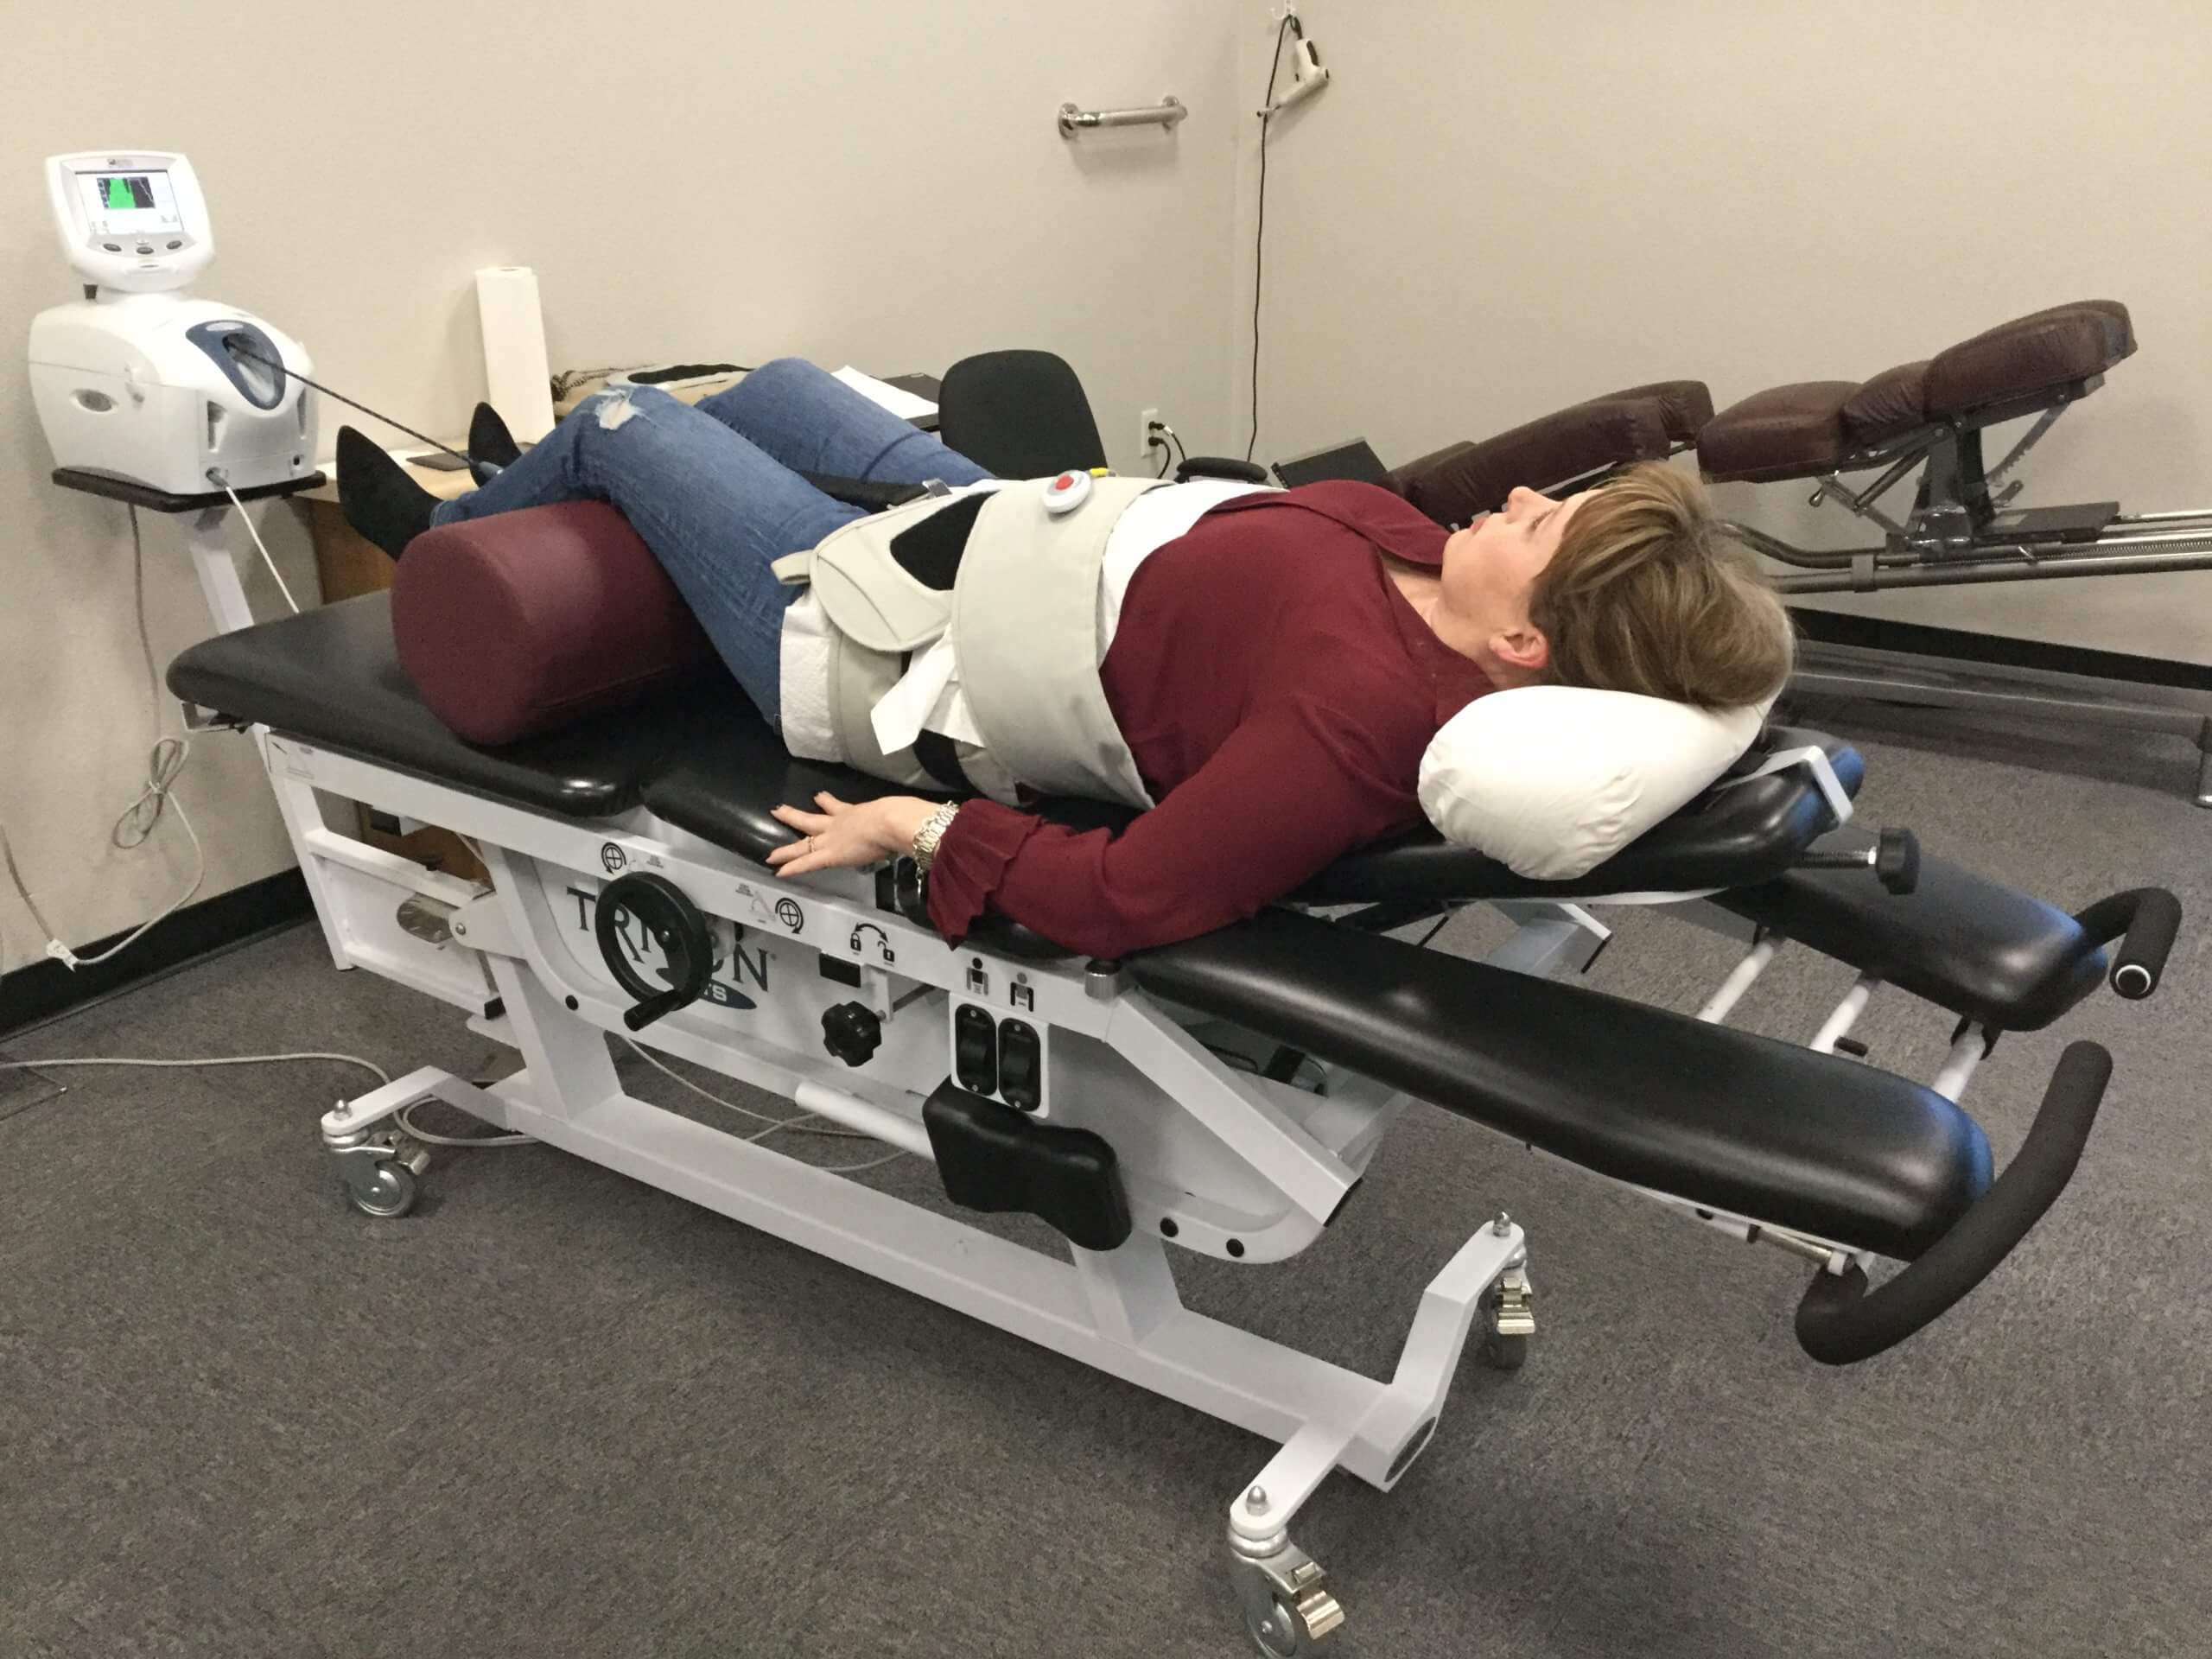
Non-surgical spinal decompression is commonly described as controlled lumbar traction or unloading. The practical aim is to reduce mechanical stress temporarily and create a position in which painful tissues or irritated nerve roots may become less sensitive.
The evidence requires precision. A systematic review found short-term improvements in pain and disability when certain mechanical traction forms were added to treatment for lumbar radiculopathy, but study quality and results varied (Vanti et al., 2021). WHO guidance for chronic primary low-back pain advises against routine traction for most patients, so decompression should not become an automatic protocol for every painful back (World Health Organization, 2023).
For a selected patient, decompression may be one tool within movement retraining, strengthening, work modification, and medical evaluation. It should never be sold as a guaranteed way to “reinflate” a disc or permanently reverse degeneration.
Preventing Unnecessary Surgery Without Delaying Necessary Surgery
Avoiding surgery is valuable when recovery is safe with conservative care. Lumbar discectomy can be appropriate for selected patients, yet it still carries risks such as recurrent herniation, wound complications, dural tears, reoperation, and neurologic complications (Bombieri et al., 2022).
The safer message is not “never have surgery.” It is “earn the decision with the right evaluation.” Recent spine recommendations support surgery when conservative treatment fails and emphasize urgent or early surgery for cauda equina syndrome or progressive severe neurologic deficits (Costa et al., 2024).
Seek urgent assessment for new bowel or bladder dysfunction, saddle-region numbness, rapidly worsening leg weakness, or serious neurologic changes. Fever, major trauma, unexplained weight loss, or concern for infection, fracture, or cancer also deserves prompt review.
This is non-maleficence in practice: use the least invasive reasonable option when it is safe, but never let a desire to avoid surgery delay care for a true emergency.
Step Three: Set Proactive Lifting Limits
For Amazon associates, prevention must survive the workday. “Lift with your legs” is not enough.
Use these rules:
Bring the package close before standing up.
Turn with the feet instead of twisting under load.
Reduce load size when the object starts low, high, or far away.
Use team lifting or mechanical assistance for demanding or awkward items.
Break up repeated lifting when possible with task rotation or brief recovery periods.
Stop treating pain as a test of toughness; a changing neurologic symptom deserves evaluation.
The Revised NIOSH Lifting Equation is useful because it does not assume every worker should lift the same weight in every position. It calculates a recommended weight limit using task conditions and a lifting index that reflects physical demand. NIOSH recommends keeping the lifting index or composite lifting index at or below 1.0 when evaluating two-handed lifting tasks (NIOSH, 2024).
Integrated Oversight: Structure, Medicine, and Patient Choice
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural alignment, mechanical rehabilitation, and advanced medical diagnostics. He holds Texas Advanced Practice Nursing License #1191402, Prescriptive Authority #59628, and NPI #1205907805. His dual licensure lets the clinic coordinate musculoskeletal examination with broader medical assessment and appropriate advanced interventions.
Dr. Maria Guadalupe Cardenas, MD, is Board Certified in Internal Medicine, has more than 40 years of experience, and holds Texas Medical License #J2933 and NPI #1164426748. As Medical Director, Clinical Director, and Collaborative Physician at Injury Medical Clinic PA in El Paso, she provides internal medicine oversight, risk stratification, interpretation of indicated laboratory tests, and comorbidity coordination.
That collaboration supports beneficence: the plan centers on the patient’s best functional outcome. It supports non-maleficence by screening for medical risks before aggressive treatment and using non-invasive, drug-sparing options when appropriate. It also protects autonomy. Patients are taught what the examination shows, what each option can and cannot reasonably do, and when another specialist or their existing medical team should be involved.
A Better Goal Than “Toughing It Out”
Severe lumbago after warehouse or delivery work is not a character test. The goal is to interrupt the overload cycle before pain, guarding, deconditioning, and poor mechanics reinforce one another.
A conservative plan can include targeted joint care, selected decompression, progressive trunk and hip rehabilitation, work-specific lifting education, and medical oversight. The target is direct: more comfortable movement, safer lifting, better sleep, and the ability to work without organizing each day around the next flare.
Multidisciplinary Call to Action
If repeated bending, sorting, driving, or lifting causes severe low-back pain, start with a coordinated evaluation. El Paso Back Clinic can assess mechanical function, neurologic findings, lifting demands, and medical risks, then explain conservative options and when to refer. Bring your imaging, medication list, job demands, and questions. The final decision remains yours, supported by clear information and coordinated chiropractic and medical care.
Server Rack to Desk Chair: Why Data Center and IT Work Can Trigger Chronic Low-Back Pain—and What You Can Do About It
A shift can change quickly. For one hour, you sit and answer tickets. The next, you are standing on a server-room floor, crouching behind a rack, reaching for cables, or lifting hardware. By day’s end, your low back may feel tight, tired, or familiar.
For El Paso’s IT professionals, data center technicians, and network teams, recurring low-back pain rarely comes down to one “bad posture.” Sitting, standing, bending, twisting, and lifting can contribute to symptoms, but no single exposure consistently explains every case (Swain et al., 2020). The better question is which combined loads, habits, and recovery limits keep your back irritated.
Why Tech Work Can Become a Mechanical Load Problem
Your lumbar spine is built to move and carry load. Problems can appear when tissues face more stress than they comfortably recover from.
Long desk sessions reduce movement variety. Prolonged standing can also become uncomfortable; substantial occupational standing has been associated with more low-back symptoms, though it has not been proven that standing itself causes pain (Coenen et al., 2018). Add crouching, cable work, twisting, and equipment lifting, and the demand changes again.
The goal is not to fear movement. It is to improve how well your body handles it.
Sitting, Hip Stiffness, and the “Locked Up” Feeling
After hours seated, many workers stand feeling stiff through the hips and lower back. It is tempting to blame “tight hip flexors,” but low-back pain is more complex than one muscle group.
Limited hip motion can change how you bend, squat, or reach. The lumbar region may then take on more motion during some tasks. Hip mobility, trunk control, and movement variety can therefore be reasonable rehabilitation targets without claiming that tight hips automatically cause back pain.
Standing on Concrete Is Not Automatically Better Than Sitting
A standing desk may help, but standing all day is not a cure. Technical workspaces may require long periods on firm surfaces while monitoring equipment.
Variation is usually practical: sit, stand, walk, change foot position, and move when the job permits. NIOSH identifies static posture, heavy physical work, lifting, bending, and twisting among contributors to work-related musculoskeletal stress (National Institute for Occupational Safety and Health [NIOSH], 2024a).
Think “best next position,” not “perfect position.”
Crouching, Cable Work, and Rack-Side Repetition
Working behind equipment can place you in deep hip flexion, kneeling, squatting, rotation, or sustained forward bending. None is inherently dangerous. Trouble may develop when exposure is prolonged, repeated, heavily loaded, or performed while fatigued.
Bring tools closer. Raise work when possible. Use a kneeling pad or stable support when appropriate. Alternate sides instead of always rotating one way. Brief movement breaks can reduce unnecessary repetition.
Lifting Hardware: Control the Load, Not Just Your Back
Servers, batteries, monitors, and UPS components can be awkward or hard to grip. Safe lifting is not simply “keep your back straight.” Weight, distance, height, twisting, frequency, grip, and repetition matter. The Revised NIOSH Lifting Equation estimates physical stress from two-handed lifts and supports safer job design (NIOSH, 2024b).
Get close to the load, use a stable stance, avoid rushed twisting, and use team lifts or assistance when appropriate. Lifting limits should reflect the task and your current capacity.
What a Structural Assessment Should Actually Look For
Recurring low-back pain deserves more than a quick label.
At El Paso Back Clinic, a mechanical assessment can consider spinal and pelvic motion, painful patterns, hip mobility, trunk endurance, lifting mechanics, neurological findings, and positions that change symptoms. The goal is not to claim every painful back is “out of alignment,” but to identify modifiable findings and whether conservative care is appropriate.
Imaging is not necessary for every episode. History and examination help determine when testing may be appropriate. New bowel or bladder problems, saddle numbness, progressive leg weakness, major trauma, fever, or systemic symptoms require prompt medical evaluation.
Mechanical Rehabilitation: Build Capacity for Your Real Job
Rehabilitation should prepare you for work, not only help you feel better on a treatment table. Clinical guidelines support exercise and selected manual therapies for many people with acute or chronic low-back pain (George et al., 2021).
For an IT professional, rehabilitation might include hip mobility, trunk endurance, hinging, graded lifting, strength, walking tolerance, and desk-position changes. A data center technician may also need loaded carries, squat tolerance, kneeling transitions, reaching, and controlled rotation.
The plan should progress with your response. Some people need mobility; others need strength, endurance, or confidence with painful movements. Patient autonomy matters: you should understand what is tested, why treatment is suggested, alternatives, and how progress will be measured.
Where Chiropractic Care and Decompression Fit
Chiropractic care may be one part of conservative treatment when examination indicates manual care is appropriate. Guidelines include spinal manipulation among options that may help some people with chronic low-back pain, especially when paired with active care rather than used alone (World Health Organization [WHO], 2023).
“Decompression” requires careful thinking. WHO does not recommend routine traction for chronic primary low-back pain because the supporting evidence is uncertain (WHO, 2023). Decompression should not be sold as a guaranteed disc fix or universal answer.
If decompression is considered, it should follow examination, fit the symptom pattern, have clear goals, and be reassessed. Beneficence means choosing care for your clinical needs—not applying the same protocol to everyone.
Integrated Care When Back Pain Is More Than Mechanical
Persistent pain can be influenced by sleep, stress, metabolic health, medication use, recovery, and other medical factors. An integrated team can help when those issues matter.
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges chiropractic structural care, mechanical rehabilitation, and functional medical assessment. Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, provides medical direction and oversight for complex medical or metabolic concerns and clinically appropriate laboratory evaluation.
Collaboration does not remove your voice. You remain the informed decision-maker.
A Better Back Strategy for El Paso Tech Workers
Whether your day moves from an El Paso desk to a server room, network closet, help-desk station, or equipment floor, your back needs more than perfect posture. It needs movement variety, smart load management, recovery, and enough strength for the work.
Start with small changes: interrupt long sitting, vary standing, improve workstation reach, keep loads close, plan awkward lifts, and build capacity gradually. If pain keeps returning, limits work, radiates into the leg, or changes how you move, seek a qualified evaluation.
At El Paso Back Clinic, our goal is to identify changeable drivers, explain your options clearly, and coordinate structural chiropractic care, mechanical rehabilitation, and medical oversight when indicated. We build the safest plan around your findings, goals, and informed choices. That approach supports safer movement, stronger function, and more confident workdays ahead.
References
Coenen, P., Willenberg, L., Parry, S., Shi, J. W., Romero, L., Blackwood, D. M., Maher, C. G., Healy, G. N., Dunstan, D. W., & Straker, L. M. (2018). Associations of occupational standing with musculoskeletal symptoms: A systematic review with meta-analysis. British Journal of Sports Medicine, 52(3), 176–183. https://doi.org/10.1136/bjsports-2016-096795
George, S. Z., Fritz, J. M., Silfies, S. P., Schneider, M. J., Beneciuk, J. M., Lentz, T. A., Gilliam, J. R., Hendren, S., & Norman, K. S. (2021). Interventions for the management of acute and chronic low back pain: Revision 2021. Journal of Orthopaedic & Sports Physical Therapy, 51(11), CPG1–CPG60. https://doi.org/10.2519/jospt.2021.0304
Swain, C. T. V., Pan, F., Owen, P. J., Schmidt, H., & Belavy, D. L. (2020). No consensus on causality of spine postures or physical exposure and low back pain: A systematic review of systematic reviews. Journal of Biomechanics, 102, 109312. https://doi.org/10.1016/j.jbiomech.2019.08.006
World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. World Health Organization. https://www.who.int/publications/i/item/9789240081789
Unlocking Tendon Healing: An Inside Look at Percutaneous Tenotomy
Abstract
Chronic tendon pain, or tendinopathy, can be debilitating and significantly affect quality of life. Traditional treatments often provide only temporary relief, leaving patients searching for more definitive solutions. In this educational post, I will explore a groundbreaking, minimally invasive procedure known as percutaneous tenotomy. We will get into the science behind this ultrasound-guided technique, which removes damaged tendon tissue to stimulate the body’s natural healing processes. Specifically, we will examine the two leading methods, Tenex and TenJet, and discuss their applications for conditions like tennis elbow, Achilles tendinopathy, and plantar fasciitis. As we explore the mechanics of this procedure, I will also explain how we at Injury Medical Clinic integrate this advanced medical intervention into our comprehensive, multidisciplinary approach. This includes integrative chiropractic care, functional medicine, and personalized rehabilitation, all under the medical direction of Dr. Maria Guadalupe Cardenas, MD, to ensure our patients achieve optimal, long-lasting recovery.
As a practitioner with dual credentials in chiropractic (DC) and as an advanced practice registered nurse (APRN), I have dedicated my career to bridging gaps between medical disciplines. My goal has always been to find the most effective, evidence-based solutions for my patients. Today, I want to share insights into a fascinating procedure that has revolutionized how we treat chronic tendon pain: percutaneous tenotomy. This technique, once confined to surgical suites, is now a powerful tool accessible in an office setting, offering hope to those suffering from persistent tendinopathies.
At our practice, Injury Medical Clinic, we pride ourselves on a collaborative, integrative model. Our medical director and collaborative physician, Dr. Maria Guadalupe Cardenas, MD, an internist with over 40 years of experience, provides essential medical oversight. This partnership allows us to combine my expertise in chiropractic, functional medicine, and rehabilitation with her deep knowledge of internal medicine. This combination ensures that when we recommend and facilitate a procedure like percutaneous tenotomy, it is part of a holistic and well-managed treatment plan designed for comprehensive healing.
Understanding Chronic Tendinopathy: When Rest Isn’t Enough
Before we explore the solution, let’s understand the problem. Tendinopathy is not simply inflammation, as the term “tendinitis” might suggest. It’s a degenerative condition where the collagen fibers that make up the tendon begin to break down. This often happens with repetitive overuse, which prevents the tendon from healing properly. Instead of organized, strong collagen, the body lays down a disorganized, weak, and painful matrix of scar tissue. This abnormal tissue is metabolically inactive, has a poor blood supply, and doesn’t respond well to conservative treatments like rest, ice, or stretching.
Clinically, I see patients who have been struggling for months, or even years, with conditions such as:
Tennis Elbow (Lateral Epicondylitis or Extensor Carpi Radialis Brevis Tendinopathy)
Golfer’s Elbow (Medial Epicondylitis)
Jumper’s Knee (Patellar Tendinopathy)
Achilles Tendinopathy
Plantar Fasciitis (Plantar Fasciopathy)
These individuals often report a cycle of pain, temporary relief, and frustrating recurrence. This is precisely where a more targeted intervention becomes necessary.
Percutaneous Tenotomy: A Minimally Invasive Revolution
Percutaneous tenotomy is a cutting-edge, FDA-approved procedure designed to precisely remove the damaged, degenerative tissue from a tendon under ultrasound guidance. The term “percutaneous” means “through the skin,” highlighting its minimally invasive nature. Unlike open surgery, which requires large incisions and longer recovery times, percutaneous tenotomy is performed through a very small entry point, often requiring just a sterile bandage afterward.
The core principle is simple but powerful: by selectively debriding (removing) the diseased tissue, we create a controlled injury that triggers the body’s natural inflammatory and healing cascade. This process brings fresh blood, growth factors, and specialized cells to the area, encouraging new, healthy tendon tissue to grow.
Leading researchers in musculoskeletal medicine have shown that this targeted debridement is key to breaking the cycle of chronic pain and dysfunction (Knutsen et al., 2023). It’s a precise and elegant solution that addresses the root cause of the problem.
The Two Leading Techniques: Tenex and TenJet
Two primary technologies currently dominate the market for percutaneous tenotomy. While both achieve the same goal, they use different mechanisms.
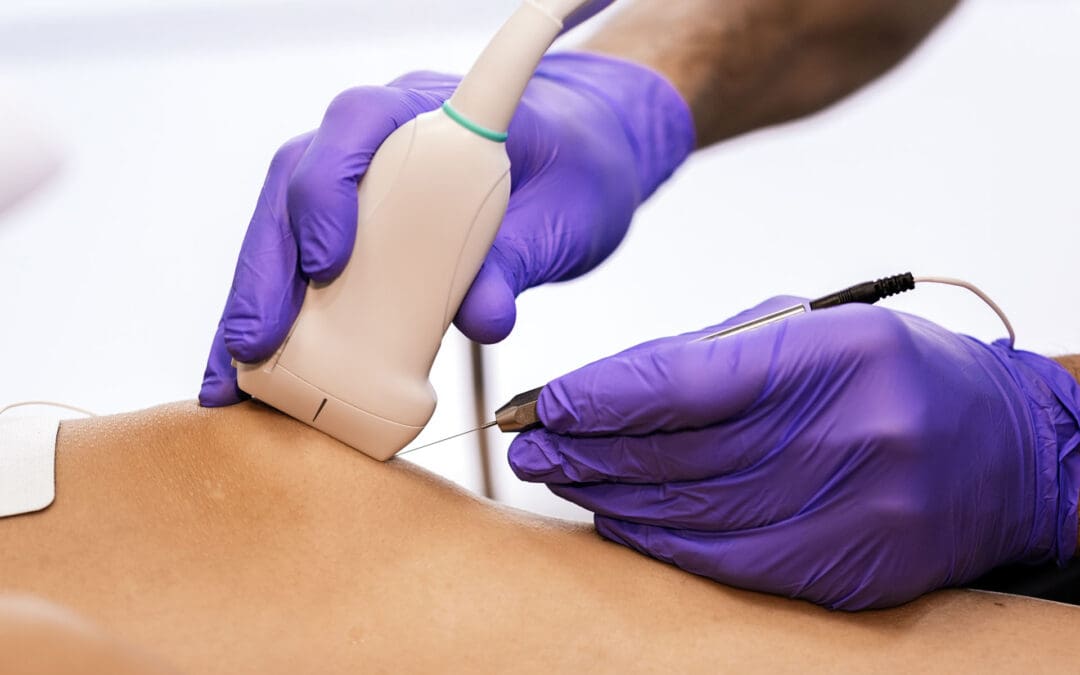
Tenex Health TX System: This technique relies on phacoemulsification, the same ultrasonic energy used in modern cataract surgery. A specialized handheld instrument uses a small, 18-gauge double-lumen needle. The needle tip vibrates at an ultrasonic frequency, emulsifying (liquefying) the targeted pathologic tissue. At the same time, a second lumen within the needle suctions the emulsified debris out of the body. This is performed in real time under direct ultrasound visualization, ensuring that only damaged tissue is removed while the surrounding healthy tendon is preserved.
TenJet System: This technology offers an alternative to ultrasonic energy. It uses a high-velocity, pressurized stream of saline to create a “cutting” effect. The focused water jet precisely dissects and removes the degenerated tissue, which is then aspirated away through the same instrument.
In our collaborative network, we often use the Tenex device for its precision and effectiveness. The procedure is typically performed in an office or a minor procedure suite, making it incredibly convenient for patients. A foot pedal controls the device, and the settings are calibrated for the specific tendon and severity of the condition.
A Glimpse into the Procedure: Debriding Tennis Elbow
To help you visualize how the device works, let’s walk through a typical procedure for extensor carpi radialis brevis tendinopathy, commonly known as tennis elbow. This is one of the most common and well-studied applications for percutaneous tenotomy.
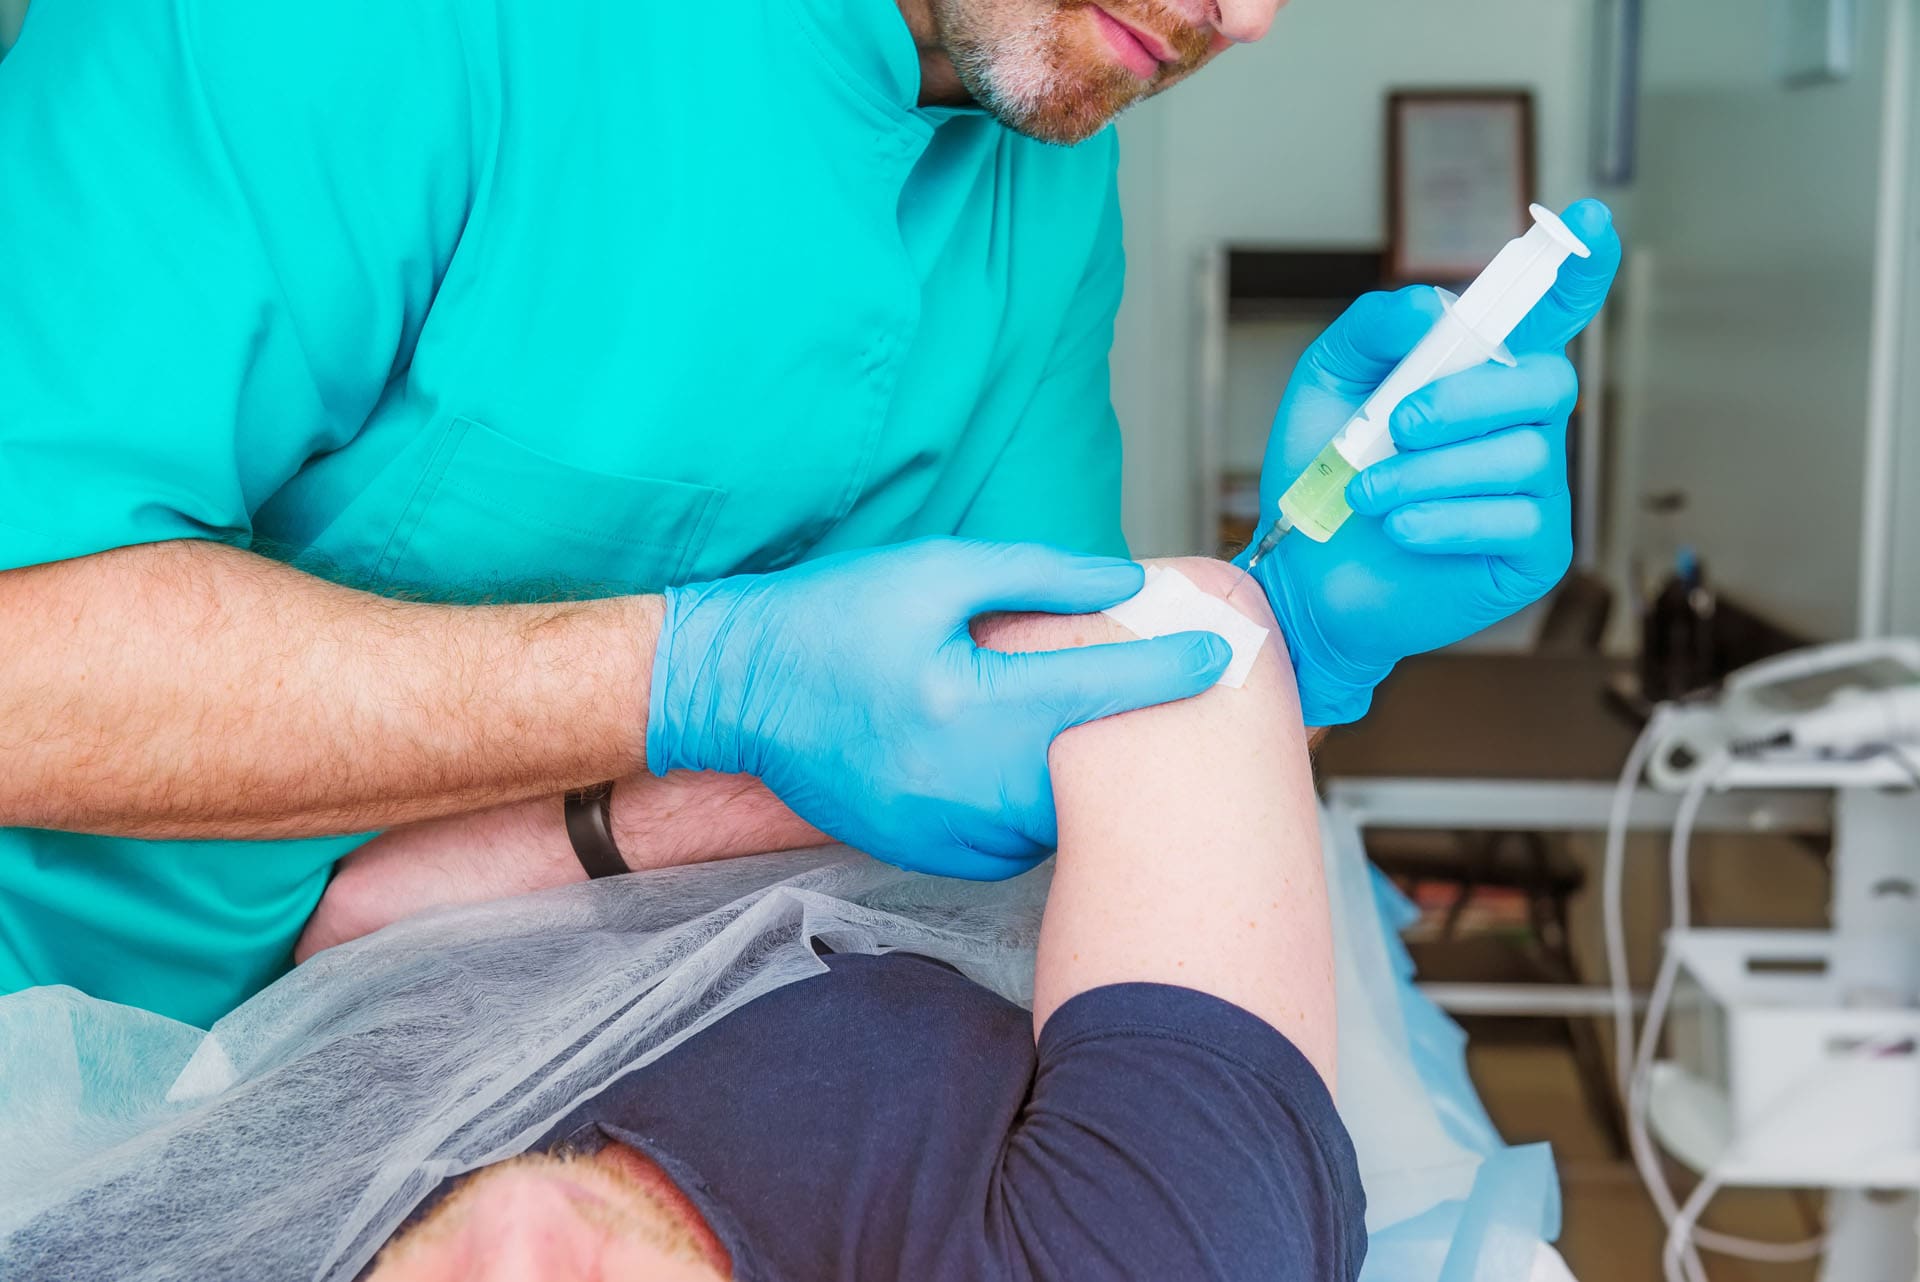
Preparation and Sterilization: The patient is positioned comfortably, and the area is prepped using a sterile technique. The ultrasound probe itself is covered with a sterile sheath to maintain a clean field. Local anesthetic numbs the area completely, ensuring the procedure is painless.
Ultrasound Visualization: The first and most critical step is using the ultrasound to identify the exact location and extent of the tendinopathy. The damaged tissue appears distinct on the screen—often hypoechoic (darker) and thickened compared with the bright, organized fibers of a healthy tendon.
Needle Insertion: Under continuous ultrasound guidance, the provider carefully inserts the Tenex needle through the skin and advances it directly into the degenerated tissue. Real-time imaging lets the provider see the needle tip at all times, ensuring pinpoint accuracy.
Debridement: The provider activates the device with the foot pedal. The ultrasonic tip begins to vibrate, and the provider moves the needle back and forth through the diseased tissue in a technique similar to fenestration (a needling procedure that promotes bleeding and healing). You can often hear a subtle hum as the device works. The device simultaneously suctioned away the emulsified, unhealthy tissue.
Completion: The entire “cutting time” is remarkably short, typically ranging from 30 seconds to two minutes. Once the provider has sufficiently debrided the pathologic area, they remove the needle and apply a small bandage.
This removes the source of pain and creates fertile ground for true healing to begin. Studies have demonstrated significant improvements in pain and function following this procedure for various tendinopathies (Seng et al., 2016).
Our Integrative Approach: Beyond the Procedure
At Injury Medical Clinic, performing a procedure like percutaneous tenotomy is just one part of a larger, more comprehensive approach. True and lasting recovery requires a multi-faceted approach that supports the body’s healing journey from every angle. This is where our unique integrative model, supervised by Dr. Cardenas, truly shines.
1. The Role of Integrative Chiropractic Care
As a chiropractor, I focus on the biomechanical integrity of the entire musculoskeletal system. The tendon issue didn’t arise in isolation. It often results from underlying biomechanical faults, postural imbalances, or compensatory movement patterns. My role, both before and after the tenotomy procedure, is to:
Assess and Correct Joint Dysfunction: I perform specific chiropractic adjustments to the elbow, wrist, shoulder, and even the spine to restore proper joint mechanics. If the joints don’t move correctly, the attached tendons remain under abnormal stress, hindering recovery and increasing the risk of reinjury.
Address Myofascial Restrictions: Using techniques like Active Release Technique (ART) and Graston Technique, we break down adhesions in the muscles and fascia surrounding the affected tendon. This improves flexibility, reduces muscle tension, and helps the tendon glide smoothly.
Prescribe Rehabilitative Exercises: After the procedure, a carefully graded exercise program is crucial. We start with gentle range-of-motion exercises and progress to eccentric loading exercises. Eccentric exercises (lengthening the muscle-tendon unit under load) are scientifically proven to stimulate collagen production and help the new tendon fibers align correctly, making them strong and resilient (Alfredson, 2005).
2. Functional Medicine and Nutritional Support
Healing is a metabolically demanding process. As a Certified Functional Medicine Practitioner (CFMP), I consider the biochemical factors that can support or hinder tissue repair. We may assess for and address:
Systemic Inflammation: Chronic inflammation can impede healing. We recommend anti-inflammatory diets rich in omega-3 fatty acids, antioxidants, and phytonutrients.
Nutrient Deficiencies: Key nutrients like Vitamin C, zinc, manganese, and certain amino acids (proline, glycine) are essential building blocks for collagen. We may recommend targeted supplementation to ensure the body has the raw materials it needs to build a strong new tendon.
Gut Health: Emerging research shows a strong link between gut health and systemic inflammation. Optimizing the gut microbiome can profoundly affect the body’s ability to heal.
3. Medical Oversight and Comprehensive Care
Having Dr. Cardenas as our medical director is invaluable. Her internal medicine expertise ensures we consider all aspects of the patient’s health. She provides medical clearance for procedures, manages any co-existing medical conditions (like diabetes or hypertension) that could affect healing, and can prescribe medications for pain management if necessary. This collaborative oversight ensures patient safety and a truly integrated standard of care that addresses the whole person, not just the injured tendon.
A New Era in Tendon Treatment
Percutaneous tenotomy represents a significant leap forward from older, more invasive methods. When skilled providers use it and integrate it into a comprehensive rehabilitation plan, this powerful tool delivers remarkable outcomes. It bridges the gap between failed conservative care and major surgery.
At our clinic, we use the latest evidence-based research to guide our practice. By combining advanced medical procedures like percutaneous tenotomy with the foundational principles of chiropractic care, functional medicine, and targeted rehabilitation, we create a synergistic healing environment. Our goal is to eliminate your pain, restore your function, strengthen your body, and empower you to return to the activities you love, stronger and more resilient than before.
If you have been struggling with chronic tendon pain, know that there are innovative and effective options available. It may be time to explore a more definitive solution that addresses the true source of your condition.
References
Alfredson, H. (2005). The chronic painful Achilles and patellar tendon: Research on basic biology and treatment. Scandinavian Journal of Medicine & Science in Sports, 15(4), 252–259. https://doi.org/10.1111/j.1600-0838.2005.00478.x
Seng, K., Mohan, P. C. S., & Koh, J. S. B. (2016). Percutaneous ultrasonic tenotomy for chronic tendinopathies: A systematic review. Journal of Orthopaedic Surgery, 24(1), 92–97. https://doi.org/10.1177/160240021602400120
Battlefield Acupuncture and Chiropractic Pain Relief
Abstract
Welcome to our educational series. I’m Dr. Alex Jimenez, and today, we’re exploring a powerful, non-pharmacological tool for pain management: Battlefield Acupuncture (BFA). This post will guide you through the principles and applications of this innovative technique, which uses auricular (ear) acupuncture to provide rapid, significant pain relief. We will explore the neurophysiological mechanisms behind BFA, identify key anatomical points on the ear, and explain their connection to the brain’s pain-processing centers. I’ll explain the step-by-step protocol, from patient assessment to needle insertion, and discuss its effectiveness for both acute and chronic pain conditions. As part of our commitment to integrative care at Injury Medical Clinic, we will also explore how Battlefield Acupuncture seamlessly complements our core chiropractic, physical rehabilitation, and functional medicine strategies. By combining these modalities, we can create a comprehensive, patient-centered treatment plan that addresses pain from multiple angles, promotes faster recovery, and restores function while minimizing the need for medication.
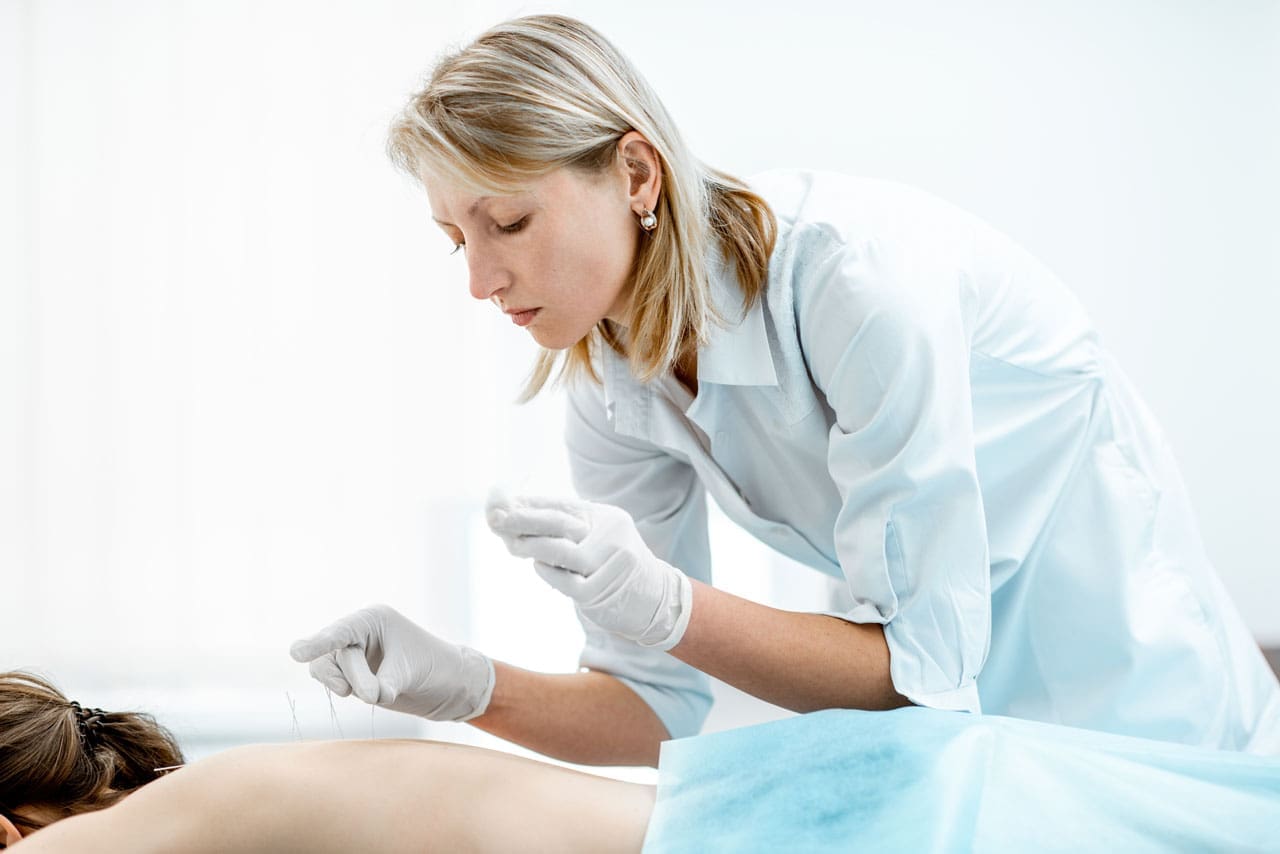
An acupuncturist puts needles into the patient’s back, removing inflammation of the muscles
A Modern Approach to Ancient Healing: Understanding Battlefield Acupuncture
As a clinician dedicated to finding the most effective and evidence-based treatments for my patients, I am constantly exploring advancements in integrative medicine. One of the most remarkable techniques I’ve incorporated into my practice is Battlefield Acupuncture (BFA). Developed by Dr. Richard Niemtzow, a retired Air Force physician, this protocol is a specialized form of auricular acupuncture designed for rapid pain relief in diverse settings, from the front lines of combat to our clinical practice here in El Paso.
The name might sound intense, but the technique is precise, minimally invasive, and incredibly effective. It involves placing small, semi-permanent needles, called ASP® needles (Aiguille Semi-Permanente), at specific points on the ear. These are not your typical acupuncture needles; they are tiny, dart-like needles designed to stay in place for several days, providing continuous stimulation to the nervous system. The primary goal is to interrupt pain signals and modulate the body’s own pain-relieving mechanisms.
The Neurological Blueprint of Pain Relief: How BFA Works
To appreciate how placing a tiny needle in the ear can alleviate pain in the lower back or a knee, we must first understand the intricate connection between the ear and the central nervous system. The external ear, or auricle, is one of the most densely innervated parts of the body, with connections to major nerves like the vagus nerve, trigeminal nerve, and cervical plexus.
Ancient acupuncture charts depicted the ear as a “homunculus,” an inverted fetus map where different parts of the body correspond to specific points on the ear. Modern research has validated this concept, showing that stimulating these auricular points sends signals directly to the brain and influences key areas involved in pain perception and processing.
The BFA protocol targets five specific points that correspond to major pain-processing centers in the brain:
Cingulate Gyrus: This is a crucial part of the limbic system, which governs our emotional response to pain. By targeting this point, we can help detach the emotional suffering and anxiety often associated with chronic pain.
Thalamus: Often called the brain’s “relay station,” the thalamus receives sensory signals from the body and directs them to the appropriate cortical areas for processing. Modulating this point helps to filter and reduce the intensity of incoming pain signals before they even reach conscious awareness.
Omega 2: This point is associated with regulating the autonomic nervous system, helping to shift the body from a “fight-or-flight” (sympathetic) state, which often exacerbates pain, to a “rest-and-digest” (parasympathetic) state that promotes healing.
Point Zero: Considered the “autonomic balance” point of the ear, this area helps to bring the entire body back into a state of physiological equilibrium, or homeostasis.
Shen Men (“Spirit Gate”): A master point used in many forms of acupuncture, Shen Men helps to calm the mind, reduce stress, and has a powerful general analgesic (pain-relieving) effect.
When an ASP needle is inserted, it stimulates these nerve endings, sending a signal along neural pathways to the brainstem and higher brain centers. This process is believed to trigger the release of the body’s own natural painkillers—endorphins and enkephalins—and to downregulate the activity in brain regions that process pain, effectively turning down the “volume” of the pain signal.
The Battlefield Acupuncture Protocol: A Step-by-Step Guide
The BFA protocol is systematic and patient-driven. The patient’s feedback on their pain level at each step determines how we proceed. This ensures the treatment is customized in real-time to achieve the best possible outcome.
Initial Assessment and Preparation
Pain Assessment: Before we begin, I ask the patient to rate their pain on a scale of 0 to 10. I also ask them to perform a simple movement that provokes their pain, such as walking, bending, or rotating their neck. This provides us a functional baseline.
Choosing the Starting Ear: For generalized pain or pain on both sides of the body, we typically start with the ear on the patient’s non-dominant side. If the pain is localized to one side (e.g., right-sided sciatica), we start on the contralateral (opposite) ear.
Sanitization: The ear is thoroughly cleaned with an alcohol swab to ensure a sterile field. While some practitioners may not use gloves, I believe it is prudent to wear them to maintain the highest standards of hygiene for patient safety.
Needle Insertion and Reassessment
The magic of BFA lies in its sequential process. We don’t simply insert all five needles at once.
First Point (Cingulate Gyrus): I begin by inserting the first ASP needle into the Cingulate Gyrus point. I hold the needle with a special applicator and, with a quick, firm press, insert it with a small “click.” It’s surprisingly well tolerated, with most patients feeling only a momentary pinch.
Ambulation and Reassessment: After the first needle is in, I ask the patient to stand up and walk around for a minute. I then ask them to rate their pain again. “Has the pain level decreased?” “Does the movement feel easier?”
Decision Point: If the patient reports a significant reduction in pain (e.g., from an 8 down to a 4) with just one needle, we may stop there. The goal is maximum relief with the minimum number of needles.
Progressing the Protocol: If the pain relief is minimal or non-existent, I proceed to the next point in the sequence, the Thalamus. After inserting the second needle, the patient ambulates and reassesses their pain again. We continue this process through the five points, stopping at any point where the patient experiences substantial relief. If we complete all five points in one ear and the pain is still not adequately controlled, we can then move to the other ear and repeat the process.
The ASP needles are designed to stay in the ear for three to seven days. They are covered by a small adhesive patch, and patients can shower and sleep with them in place. They typically fall out on their own as the skin naturally exfoliates. This provides continuous, low-level stimulation that extends the therapeutic benefit long after the patient leaves our clinic.
Integrating BFA with Chiropractic and Rehabilitative Care
At Injury Medical Clinic, our philosophy is rooted in a multidisciplinary, integrative approach. Under the medical direction of our internist, Dr. Maria Cardenas, we blend various disciplines to create a synergistic healing effect. Battlefield Acupuncture is not a standalone cure but a powerful component of a larger, comprehensive treatment plan.
BFA as a Gateway to Movement and Rehabilitation
One of the biggest obstacles in rehabilitating a musculoskeletal injury, such as a herniated disc or severe sciatica, is pain. Pain creates fear of movement (kinesiophobia), leading to muscle guarding, stiffness, and deconditioning. This creates a vicious cycle where pain leads to immobility, and immobility worsens the pain.
This is where BFA shines. By providing rapid and significant pain relief, it creates a crucial “window of opportunity.” A patient who walked in with 8/10 back pain and could barely bend might, after a BFA treatment, experience a drop to 3/10 pain. This newfound comfort allows them to engage more effectively in the other essential parts of their recovery:
Chiropractic Adjustments: When a patient’s muscles are relaxed and they are not in excruciating pain, they are more receptive to spinal adjustments. The chiropractic adjustment, aimed at restoring proper joint mechanics and relieving nerve pressure, can be performed more gently and effectively. BFA helps break the cycle of muscle spasm that often resists manipulation.
Physical Therapy and Functional Exercise: With pain reduced, patients can participate fully in their prescribed therapeutic exercises. They can perform stretches with a greater range of motion and engage in strengthening exercises without the fear of immediate, sharp pain. This is critical for stabilizing the spine, correcting muscular imbalances, and building the resilience needed to prevent re-injury.
Decompression Therapy: For conditions like disc herniation or spinal stenosis, we use non-surgical spinal decompression. This therapy works best when the patient is relaxed. BFA helps calm the nervous system and reduce the reflexive muscle guarding that can interfere with the gentle traction of the decompression table.
In essence, BFA acts as a catalyst for recovery. It doesn’t replace the foundational work of chiropractic and physical rehabilitation; it enables it. By managing the primary symptom of pain, we empower patients to become active participants in their healing journey, accelerating their return to function and daily life. My clinical observations consistently show that patients who receive BFA alongside their regular chiropractic and rehab programs report faster pain reduction and improved functional outcomes compared to those who receive traditional care alone.
A Patient-Centered, Holistic Vision
Our team, guided by the collaborative expertise of Dr. Cardenas and me, looks at each patient through a holistic lens. We understand that pain is a complex experience influenced by physical, biochemical, and emotional factors. Battlefield Acupuncture fits perfectly within this model because it directly addresses the neurological and emotional components of pain, complementing the biomechanical focus of chiropractic care and the functional focus of physical therapy. This integrated system allows us to provide truly comprehensive care for everything from acute personal injuries to chronic, stubborn pain conditions, always keeping the patient’s well-being and long-term health as our ultimate goal.
References
Niemtzow, R. C. (2018). Battlefield acupuncture: An emerging tool for pharmacists to participate in pain management. Hospital Pharmacy, 53(2), 85–86. https://doi.org/10.1177/0018578718761271
Niemtzow, R. C., Burns, S. M., & Zeliadt, S. B. (2020). Battlefield acupuncture for the provider. Medical Acupuncture, 32(4), 196–203. https://doi.org/10.1089/acu.2020.1449
Abstract: When hormone levels decline with age or menopause, bioidentical hormone replacement therapy (BHRT) can help compensate by easing tight joints, safeguarding bone density, and bolstering muscular strength. Those changes can support better mobility and flexibility. BHRT will not magically make a person more flexible. It may help by lowering joint inflammation, supporting cartilage health, and easing muscle stiffness that often comes with low estrogen or testosterone. Integrative chiropractic care can amplify those advantages by restoring joint motion, reducing nervous-system stress, and improving movement mechanics. This article explains how hormones affect movement, what BHRT can and cannot do, and how a medical doctor and chiropractor work together in El Paso.
Start With What People Usually Feel
Many people notice the same shift. The body feels tighter than it used to. The first steps in the morning take longer. Bending to tie shoes, turning to check a blind spot, or reaching into a high cabinet does not feel as easy.
Some of that comes from less activity, old injuries, or weaker muscles. Hormones also play a role. Estrogen and testosterone do more than affect mood, sleep, and energy. They also affect joints, bones, cartilage, and muscle.
When those hormone levels fall, joints can feel tighter. Bones can lose density. Muscles may not support movement as well. That is why the question isn’t only, “Do I need to stretch more?” It is also “What is happening inside the body that makes stretching harder?”
How Hormone Decline Changes Joints, Bones, and Muscles
Estrogen helps keep joints quieter. It can lower inflammatory signals and help cartilage stay healthier and better lubricated. After menopause, estrogen drops. Joints may then become more prone to swelling and stiffness. The fluid that helps joints glide can decrease. Bone density often declines at the same time, which puts extra stress on the joints (Mobility Bone & Joint Institute, 2025).
Testosterone supports collagen and muscle mass. Collagen is a building block of cartilage, tendons, and ligaments. Muscle acts like a natural brace around a joint. When testosterone is low, repair can slow, muscles can weaken, and joints can feel less stable (BodyLogicMD, 2025; Sota Wellness, n.d.).
People may notice:
Tight hips, shoulders, neck, or knees
Longer morning stiffness
Less energy for walking or exercise
Weaker support around the joints
A higher chance of bone loss
These changes can feed on each other. Pain reduces activity. Less activity weakens muscle. Weaker muscle loads the joints more. Hormone balance may help interrupt that cycle, but movement still has to be restored.
What Bioidentical Hormone Therapy Is
BHRT uses hormones that match the ones the body makes. They are often made from plant sources and then chemically altered to match human estradiol, progesterone, or testosterone.
A clinician usually reviews symptoms and lab work before choosing a plan. Forms can include creams, patches, pellets, or other methods. The dose is meant to be personal, not one-size-fits-all.
It is important to stay careful. Mayo Clinic notes that bioidentical hormones are not proven safer or more effective than standard hormone therapy. Compounded products can also vary in quality (Mayo Clinic, 2024). Hormone therapy is a medical decision. It should be supervised, monitored, and based on a person’s health history. It is not right for everyone.
How BHRT May Support Mobility and Flexibility
BHRT does not stretch a tight muscle or unlock a restricted joint. It can help compensate for hormone decline in ways that make movement easier.
It may ease tight joints. Restoring estrogen and testosterone can reduce inflammatory activity that makes joints ache and feel stiff (BodyLogicMD, 2025; Renew Health & Wellness, 2021).
It may safeguard bone density. Stronger bones provide a more stable base for joints and can lower fracture risk (Balance Hormone Center, n.d.; Desert Sands Aesthetics, n.d.).
It may bolster muscular strength. Better muscle support can make daily movement safer and more controlled (Charleston Pain Relief Center, n.d.; Sota Wellness, n.d.).
It may support cartilage health. Estrogen helps joint lubrication and may slow some cartilage wear. Testosterone can support collagen (BodyLogicMD, 2025).
It may raise energy for activity. When fatigue eases, people can walk, stretch, and train more often. That extra movement can improve flexibility.
Some reports show less joint pain in people using hormone therapy. A few studies have linked estrogen therapy with slower osteoarthritis progression in some groups. Other evidence is mixed. Medical groups do not list joint pain as a main reason to start hormone therapy (Maven Clinic, n.d.). Results vary from person to person.
Why BHRT Will Not Magically Make You More Flexible
Flexibility is the ability of a muscle and joint to move through a useful range. Mobility is a bigger idea. It is flexibility plus strength, control, and healthy connective tissue (Essentrics, 2026).
Hormones can make that range more comfortable. They cannot create it by themselves. People still need:
Regular movement through the full range
Strength around the hips, spine, shoulders, and knees
Better posture and joint mechanics
Enough sleep and recovery
Care for old injuries that never fully resolved
If someone only uses hormone therapy and never addresses stiff joints or weak muscles, flexibility often stays limited. BHRT may lower the background tightness. The body still has to relearn easier movement.
How Integrative Chiropractic Care Fits Into This Treatment
This is where integrative chiropractic care becomes useful. Chiropractic care does not replace estrogen, progesterone, or testosterone. It does not change hormone levels on its own. It can restore the motion that stiffness and poor mechanics have taken away.
Gentle adjustments and soft-tissue work can help joints move again. Better joint motion often means less guarding and less pain. That can lower nervous-system stress. Pain and poor sleep raise cortisol. High cortisol can increase inflammation and make recovery harder (Nightlight Chiropractic, 2025).
Integrative chiropractic care can:
Restore motion in stiff spinal and extremity joints
Reduce muscle tightness around painful areas
Improve posture so joints are not loaded in a crooked way
Lower physical stress on the nervous system
Make walking, stretching, and rehab more comfortable
When joints move better, people can use the muscle and bone support that BHRT may provide. Hormone therapy works on the internal environment. Chiropractic care works on movement mechanics. Together, they can amplify results more than either one alone (Wellness Doctor RX, 2026).
Functional Medicine, Rehabilitation, and Injury Care
Hormone changes are not isolated. Sleep, stress, nutrition, weight, and old injuries all affect how stiff a person feels. Functional medicine looks at those layers. Rehabilitation rebuilds strength and range of motion. Personal injury care addresses the extra tightness that can follow a car accident or work strain.
A useful plan often includes:
A review of symptoms, injury history, and labs
Medical oversight when hormone therapy is being considered
Chiropractic care to restore joint motion
Rehab to build strength through the new range
Nutrition and lifestyle support for bone, muscle, and inflammation
The goal is not to stack random treatments. The goal is to help the body move with less pain and more control.
A Team Approach at Injury Medical Clinic PA
At Injury Medical Clinic PA in El Paso, Texas, this kind of layered care is built into the clinic model. Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine. She has more than 40 years of experience as an internist (NPI #1164426749, Texas MD License #J2933). Serves as medical director and collaborative physician. Provides medical evaluation, diagnosis, and oversight, including review of hormone-related concerns.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, provides chiropractic care and integrative clinical support. He is a chiropractor and board-certified family nurse practitioner. His work includes spinal care, functional medicine, personal injury rehabilitation, and wellness protocols.
This setup is common in integrative and injury-care clinics. An MD provides medical direction. A chiropractor restores joint motion and movement mechanics. The same team can also include functional medicine, rehabilitation, and related services. When appropriate, hormone optimization is paired with alignment work, soft-tissue care, and guided activity so patients can regain motion more safely.
Clinical Observations From Dr. Jimenez
Dr. Jimenez’s clinical observations point to the same idea. Hormone health and musculoskeletal care work better together. Integrative chiropractic care can restore spinal and pelvic alignment, reduce muscle tightness, and improve autonomic balance. That may help patients sleep better, stay more active, and tolerate other therapies more easily (Jimenez, n.d.).
He has noted that pelvic and low-back care can improve hip mechanics. Better hip motion often makes walking and daily tasks feel less restricted. Movement then supports bone health, insulin sensitivity, and mood. In practice, care isn’t just about a single adjustment or a single hormone prescription. It looks at inflammation, nutrition, sleep, alignment, and how the person actually moves (El Paso Back Clinic, n.d.; Jimenez, n.d.).
Patients often do best with a stepwise plan. First, reduce pain and stiffness. Next, restore joint motion. Then build strength and control through that new range.
What to Keep in Mind Before Starting
BHRT is one possible tool, not a flexibility program. A careful clinician will review risks, benefits, labs, and medical history. People with certain health conditions may not be appropriate candidates. Stretching, strength work, and chiropractic care still matter even if hormone levels improve.
A practical next step is a full evaluation. That means looking at how the joints move, how strong the supporting muscles are, and whether hormone changes are part of the picture. From there, the plan can be personal.
The Bottom Line
Can bioidentical hormone therapy help with mobility and flexibility? It can help compensate for hormone decline by easing tight joints, safeguarding bone density, and bolstering muscular strength. It may also lower inflammation, support cartilage, and ease muscle stiffness. It will not magically make someone more flexible.
Integrative chiropractic care can amplify those advantages. It restores joint motion, reduces nervous-system tension, and improves movement mechanics. Together, the two approaches address both the body’s internal chemistry and how it moves.
In El Paso, Injury Medical Clinic PA offers a multidisciplinary model in which Dr. Cardenas provides medical direction, and Dr. Jimenez provides chiropractic and integrative care. That combination is designed to help people move with more comfort, strength, and control.
IFM's Find A Practitioner tool is the largest referral network in Functional Medicine, created to help patients locate Functional Medicine practitioners anywhere in the world. IFM Certified Practitioners are listed first in the search results, given their extensive education in Functional Medicine