ClickCease
+1-915-850-0900 [email protected]
Select Page

Cancer Health

Back Clinic Cancer Health Chiropractic Support Team. Abnormal growth of cells tends to proliferate uncontrollably and, in some cases, metastasize or (spread). As a result, cancer is one disease and a group of more than 100 different diseases. Cancer can involve any tissue of the body and have many different forms in each area. Most cancers are named after the cell or organ where they start. If a cancer spreads (metastasizes), the new tumor bears the same name as the original (primary) tumor. Cancer is the Latin word for crab. The ancients used the word to mean a malignancy, doubtless because of the crab-like tenacity a malignant tumor sometimes seems to show grasping the tissues it invades. Cancer may also be called malignancy, a malignant tumor, or a neoplasm (literally, a new growth). The frequency of specific cancer may depend on gender. For example, skin cancer is the most common type of malignancy for both men and women. The second common type in men is prostate cancer, and for women is breast cancer. Cancer frequency does not equate to cancer mortality. Skin cancers are curable. In comparison, lung cancer is the leading cause of death for both men and women in the United States today. Benign tumors are not cancer, and malignant tumors are cancer. Cancer is not contagious. Cancer Health, In patients experience significant dynamic physical, psychosocial, and financial challenges. With the increasing number of patients with early-stage cancers transitioning to survivorship, there is a critical need to address health promotion and overall well-being.

Alcohol Chronic Back Pain: Understanding the Risks

Alcohol Chronic Back Pain: Understanding the Risks

Alcohol, Chronic Back Pain, and Cancer Awareness: Why Medical Screening Matters

Abstract
Alcohol can quietly undermine sleep quality, medication safety, tissue healing, and long-term cancer risk while masking or worsening musculoskeletal symptoms. Persistent or unexplained back pain is not always a purely mechanical spinal problem and sometimes requires medical evaluation to rule out red-flag conditions. Coordinated physician or nurse practitioner assessment combined with appropriate chiropractic rehabilitation supports safer treatment selection and better recovery outcomes.

Alcohol Chronic Back Pain: Understanding the Risks

Imagine finishing a long day with a drink to “take the edge off” chronic back stiffness, only to wake feeling more fatigued, with tighter muscles and slower recovery. This common pattern hides important biology. Alcohol affects sleep architecture, interacts with common pain medications, slows musculoskeletal repair, and independently raises the risk of several cancers. At the same time, back pain that does not behave like a typical strain sometimes needs medical screening before any hands-on treatment begins. Understanding these connections helps patients make safer choices and receive the right care at the right time.

How Alcohol Disrupts Sleep and Recovery

Even moderate evening drinking can shorten the time it takes to fall asleep, yet it fragments the rest of the night. Alcohol suppresses rapid eye movement (REM) sleep early and then produces rebound fragmentation later, reducing overall sleep efficiency (National Institute on Alcohol Abuse and Alcoholism [NIAAA], 2026). Poor sleep raises pain sensitivity the next day and slows tissue repair because growth hormone and other recovery processes peak during deep sleep stages. For someone already managing back pain, this creates a cycle: alcohol feels helpful at night, yet the resulting sleep loss increases muscle tension, inflammation, and next-day stiffness.

Chronic use also contributes to alcoholic myopathy—muscle wasting and weakness driven by reduced protein synthesis, mitochondrial stress, and impaired regeneration (NIAAA, 2026). Bone density declines with heavier intake because alcohol slows osteoblast activity, the cells that build new bone. Fracture healing can be delayed, and callus formation is weaker. These effects matter for anyone whose back pain involves disc, facet, or soft-tissue loading; slower repair means longer disability and higher risk of reinjury.

Medication Safety and Musculoskeletal Healing

Alcohol interacts with many medications used for back pain. Combining it with opioids deepens sedation and respiratory depression. With acetaminophen, it increases liver stress. Even nonsteroidal anti-inflammatory drugs (NSAIDs) carry higher gastrointestinal risk when alcohol is added. In the recovery window after injury or adjustment, these interactions can turn a routine pain plan into a safety issue.

Beyond drug interactions, alcohol impairs the very processes needed for healing. It promotes systemic inflammation, disrupts collagen remodeling in tendons and ligaments, and reduces the body’s ability to clear waste from strained tissues. Patients who continue drinking while receiving rehabilitation often report slower progress, more night pain, and greater reliance on medication. Reducing or pausing alcohol during active recovery provides the musculoskeletal system a cleaner environment in which to rebuild.

Independent Cancer Risk

Alcohol is classified as a known human carcinogen. Risk rises with total exposure and appears for several common cancers even at levels some people consider moderate (NIAAA, 2026; Office of the Surgeon General, 2025). Established associations include cancers of the oral cavity, pharynx, larynx, esophagus, liver, colorectum, and female breast. Mechanisms include acetaldehyde production (a toxic metabolite), oxidative stress, hormonal shifts (particularly estrogen), and enhanced absorption of other carcinogens.

This cancer risk is independent of back pain yet relevant to screening decisions. Unexplained weight loss, night pain, or progressive symptoms in a person with significant alcohol history may warrant earlier medical work-up rather than prolonged assumption that the pain is only mechanical. The same lifestyle factor that delays soft-tissue healing also elevates lifetime cancer risk, making coordinated medical awareness valuable.

Why Persistent Back Pain Sometimes Needs Medical Evaluation

Most episodes of back pain improve with activity modification, exercise, and conservative care. A smaller subset does not. Red-flag features raise concern for fracture, infection, malignancy, or serious nerve compression and justify medical assessment before or alongside chiropractic care (Downie et al., 2013; Verhagen et al., 2017).

Key historical red flags include:

  • History of cancer (especially breast, lung, prostate, kidney, or thyroid)
  • Unexplained weight loss
  • Age over 50 with new-onset pain, or age under 18
  • Fever, intravenous drug use, or immunosuppression
  • Significant trauma or prolonged corticosteroid use
  • Progressive neurological deficits, saddle anesthesia, or new bowel/bladder dysfunction
  • Pain that is constant, worse at night or at rest, and unrelieved by position change

Physical examination may add point tenderness over bone, neurological deficits, or signs of systemic illness. No single red flag is perfectly accurate, but combinations improve diagnostic utility. A history of cancer plus unexplained weight loss, for example, substantially raises the post-test probability of spinal malignancy. Guidelines therefore recommend medical evaluation when red flags are present, rather than automatically attributing symptoms to mechanical spinal dysfunction.

At Injury Medical Clinic PA, initial encounters routinely include this screening. Dr. Alex Jimenez, DC, APRN, FNP-BC, applies both chiropractic and nurse-practitioner perspectives so mechanical findings are interpreted in a medical context. When red flags appear, further diagnostics or referral can occur without delay, protecting patient safety while still allowing appropriate rehabilitation to proceed once serious pathology is excluded.

Coordinated Physician/Nurse Practitioner Assessment and Chiropractic Rehabilitation

Safe treatment selection begins with accurate triage. Physician or nurse practitioner assessment clarifies medication risks, screens for systemic contributors (including alcohol-related neuropathy or metabolic issues), and decides whether imaging or laboratory work is indicated. Once red flags are addressed, chiropractic care focuses on restoring joint mobility, reducing protective muscle spasm, improving movement patterns, and guiding graded exercise.

This sequence prevents the common error of applying manual therapy to an undiagnosed fracture, infection, or metastatic lesion. It also avoids unnecessary imaging in uncomplicated mechanical pain. Outcome measures such as the Oswestry Disability Index help track functional progress objectively (see clinic resources on assessing lower back pain). Patients who reduce alcohol intake during this phase often notice better sleep, less morning stiffness, and faster mobility gains.

Alcohol-related peripheral neuropathy can further complicate the picture by producing burning pain, numbness, or weakness in the extremities that may be mistaken for radiculopathy. Differentiating the two requires a careful neurological examination and, when indicated, laboratory evaluation for nutritional deficiencies (Jimenez, n.d.; see alcoholic peripheral neuropathy overview).

What Makes the Clinic Distinct in El Paso

Injury Medical Chiropractic and Functional Medicine Clinic is unique in El Paso, Texas, because it integrates a medical director, Dr. Maria Guadalupe Cardenas, MD (board-certified in internal medicine), with a dual-licensed chiropractor and board-certified family practice nurse practitioner who specializes in soft-tissue injury. This structure is the only one in El Paso that combines on-site medical direction and nurse-practitioner assessment with comprehensive chiropractic rehabilitation, advanced soft-tissue therapies, and functional medicine tools under one coordinated team. Patients receive medical screening for red flags, medication safety review, and systemic contributors (including alcohol effects) in the same visit where spinal mechanics and rehabilitation are addressed, reducing fragmentation and supporting safer, root-cause-oriented care.

Practical Steps Patients Can Take

  • Track alcohol intake honestly and note its relationship to sleep quality and next-day pain.
  • Disclose all medications and supplements so interactions can be reviewed.
  • Report red-flag symptoms promptly rather than waiting for them to resolve on their own.
  • Pair any reduction in alcohol with consistent movement, protein intake, and sleep hygiene to support tissue repair.
  • Seek coordinated evaluation when pain persists beyond several weeks, changes character, or is accompanied by systemic symptoms.

These steps empower patients as informed decision-makers while ensuring care remains aligned with their primary medical team.

Multidisciplinary Call to Action
If you are experiencing chronic or unexplained back pain—especially if alcohol use, sleep disruption, or medication concerns are part of the picture—schedule a coordinated evaluation at Injury Medical Clinic PA. Medical screening by the nurse practitioner and medical director team, followed by appropriate chiropractic rehabilitation, can clarify whether your symptoms are mechanical, systemic, or both, and guide a safer path toward improved mobility, better sleep, and reduced reliance on pain medication. Contact the clinic to begin a personalized assessment that prioritizes both root-cause insight and patient safety.


References

Downie, A., Williams, C. M., Henschke, N., Hancock, M. J., Ostelo, R. W. J. G., de Vet, H. C. W., Macaskill, P., Irwig, L., van Tulder, M. W., Koes, B. W., & Maher, C. G. (2013). Red flags to screen for malignancy and fracture in patients with low back pain: Systematic review. BMJ, 347, f7095. https://doi.org/10.1136/bmj.f7095

Jimenez, A. (n.d.). Exploring alcoholic peripheral neuropathy: Symptoms and risks. Injury Medical Clinic PA. https://dralexjimenez.com/exploring-alcoholic-peripheral-neuropathy-symptoms-and-risks/

National Institute on Alcohol Abuse and Alcoholism. (2026). Alcohol’s effects on the body. https://www.niaaa.nih.gov/alcohols-effects-health/alcohols-effects-body

Office of the Surgeon General. (2025). Alcohol and cancer risk: The U.S. Surgeon General’s Advisory. U.S. Department of Health and Human Services. https://www.hhs.gov/surgeongeneral/reports-and-publications/alcohol-cancer/index.html

Verhagen, A. P., Downie, A., Maher, C. G., & Koes, B. W. (2017). Most red flags for malignancy in low back pain guidelines lack empirical support: A systematic review. Pain, 158(10), 1860–1868. https://doi.org/10.1097/j.pain.0000000000000998

Cancer Back Pain

Cancer Back Pain

Back pain and soreness are widespread conditions that affect all genders, races, and lifestyles. The causes for back pain are varied from injury, poor posture, arthritis, age, overuse, etc. If back pain is frequent, perhaps the last assumption is that the pain could be caused by cancer. While it’s far from the most common causes, cancer back pain is possible, which makes consulting a doctor that will figure out the root cause, especially if there are other non-related symptoms, and treat the back pain very important.

Cancer Back Pain

Cancer Back Pain

Back pain that could be caused by cancer usually occurs with other symptoms and include:

  • Back pain that is not related to movement.
  • Pain does not get worse with activity.
  • Back pain usually presents at night or early in the morning and fades away or improves as the day progresses.
  • Back pain persists even after physical therapy or other treatments.
  • Changes in bowel movements or blood in urine or stool.
  • Unexplained, sudden weight loss.
  • Unexplained fatigue/exhaustion.
  • Weakness, tingling, or numbness in the arms or legs.
  • Back pain does not have to be severe to be cancer, as it can range in severity.
  • Having a family history of cancer and these symptoms can increase the risk.

Types of Cancer That Can Contribute To Back Pain

Types of cancer that can form around, in, and near the spine can cause back pain. These include:

Spinal Tumor

  • A spinal tumor can grow in the spinal bone or the membranes around the spinal cord.
  • The spine is a common source for bone metastasis, where cancer starts in one location and spreads to others.
  • 30 to 70 percent of individuals with cancer spreads to the spine, according to the American Association of Neurological Surgeons – AANS.

Lung

  • Lung cancer is one of the most common cancers that can spread to the spine.
  • A lung tumor can press on the spine, affecting nerve transmissions.
  • An individual with lung cancer may notice becoming tired/fatigued more easily, shortness of breath, coughing up blood, and back pain.

Breast

  • Rare but possible breast cancer symptom.
  • Breast cancers can metastasize to the back.
  • Like lung cancers, some breast cancer tumors can press on nerves connected to the spine, causing discomfort and pain.

Gastrointestinal

  • Cancers of the stomach, colon, and rectum can cause back pain.
  • The pain radiates from where the cancer is to the back.

Tissue and Blood Cancers

Blood and tissue cancers like:

  • Multiple myeloma
  • Lymphoma
  • Melanoma
  • Can cause back pain.

Diagnosing Cancer and Back Pain

Medical treatments for back pain-related cancer depend on its type and how advanced it is. A doctor will consider symptoms and medical history when diagnosing possible back pain causes. Because cancer is a rare cause of back pain, a doctor may recommend various treatments before a full cancer work-up. The doctor may order imaging studies and blood testing if the pain persists after chiropractic, physical therapy, or anti-inflammatory medications. These tests will help identify potential cancer markers causing back pain.

  • Treatments usually include chemotherapy and radiation to shrink a tumor.
  • A doctor will recommend surgery to remove a tumor.

Chiropractic

Cancer patients have found chiropractic treatment to be effective for:

  • Pain management.
  • Flexibility improvement.
  • Mobility improvement.
  • Strengthening muscles.
  • Helping to reduce stress.
  • Helping the body function more efficiently.

Chiropractic physiotherapy benefits patients undergoing chemotherapy, as it helps the body withstand the debilitating effects of the treatment based on the whole-body approach.


Body Composition


Don’t Hate Dieting

Individuals hate dieting, usually because they go about it the wrong way. Individuals do not need to starve themselves and live at the gym. Reaching quick weight loss goals might sound appealing; however, going through it for an extended time can make individuals feel:

  • Tired
  • Depressed
  • Unmotivated

Individuals can find a nutrition plan/exercise balance that works for them and their lifestyle. For some individuals, dieting alone is effective, but more than likely, they have increased metabolisms. Trying to lose fat by only cutting calories can be difficult for individuals with smaller metabolisms. The goal is to find a balance between diet and exercise. This does not mean having to go on an extreme diet, skip meals, or cut out entire macronutrient groups like fat or carbs, as the body needs both of these nutrients. Finding a sustainable long-term nutrition plan takes planning and support. A dietician, nutritionist, or health coach can offer a variety of nutrition and exercise plans customized to the individual.

References

Downie, Aron et al. “Red flags to screen for malignancy and fracture in patients with low back pain: a systematic review.” BMJ (Clinical research ed.) vol. 347 f7095. 11 Dec. 2013, doi:10.1136/bmj.f7095

Mabry, Lance M et al. “Metastatic cancer mimicking mechanical low back pain: a case report.” The Journal of manual & manipulative therapy vol. 22,3 (2014): 162-9. doi:10.1179/2042618613Y.0000000056

Vasser, Melinda, and Matthew Koroscil. “When Back Pain Turns Deadly: An Unusual Presentation of Lung Cancer.” Respiratory medicine case reports vol. 29 101009. 28 Jan. 2020, doi:10.1016/j.rmcr.2020.101009

Verhagen, Arianne P et al. “Red flags presented in current low back pain guidelines: a review.” The European spine journal: official publication of the European Spine Society, the European Spinal Deformity Society, and the European Section of the Cervical Spine Research Society vol. 25,9 (2016): 2788-802. doi:10.1007/s00586-016-4684-0

Is Fructose Bad for Your Health?

Is Fructose Bad for Your Health?

Fructose is one of the main components of added sugar. It is a simple type of sugar that makes up about 50 percent of table sugar or sucrose. Table sugar is also made up of glucose or the main energy source of the human body. However, fructose needs to be turned into glucose by the liver before it can be used as fuel for energy by our cells. Fructose, sucrose, and glucose are all naturally found in fruits, vegetables, dairy products, and whole grains as well as in many processed foods. The effects of this simple sugar on our health have been a controversial topic for many years. Research studies are starting to demonstrate the connection between fructose and obesity, diabetes, and even cancer.


What is Fructose?


Fructose, also referred to as fruit sugar, is a monosaccharide or simple sugar like glucose. It’s naturally found in fruits, most root vegetables, agave, and honey. Moreover, it’s commonly added to processed foods as high-fructose corn syrup. The fructose used in high-fructose corn syrup mainly comes from corn, sugar beets, and sugar cane. High-fructose corn syrup is made from cornstarch and it has more of this simple sugar than glucose, compared to regular corn syrup. Fructose has the sweetest taste of the three sugars. It is digested and absorbed differently by the human body. Because monosaccharides are simple sugars, they don’t need to be broken down to be used as fuel for energy by our cells.


Natural foods that are high in fructose can include:


  • apples
  • apple juice
  • pears
  • prunes
  • dry figs
  • sorghum
  • asparagus
  • Jerusalem artichokes
  • chicory roots
  • leeks
  • onions
  • caramel
  • licorice
  • molasses
  • agave syrup
  • honey


Similar to glucose, fructose is absorbed directly into the bloodstream through the small intestine. Healthcare professionals have found that fructose has the least impact on blood sugar levels. It increases blood sugar levels much more gradually than glucose does and it doesn’t seem to immediately affect insulin levels. However, although this simple sugar has the least impact on blood sugar levels than any of the other simple types of sugars, it may ultimately cause more long-term negative effects on the human body. Fructose needs to be turned into glucose by the liver before it can be used as fuel for energy by our cells. Eating excess fructose can increase triglycerides and lead to metabolic syndrome.


Why is Fructose Bad for You?


When people eat a diet that is high in calories and processed foods with lots of high-fructose corn syrup, the liver can become overwhelmed and start turning fructose into fat. Research studies are starting to demonstrate the connection between this simple sugar and an increased risk of developing a variety of health issues, including obesity, type 2 diabetes, and even cancer. Many healthcare professionals also believe that eating excess fructose is one of the main causes of metabolic disorders. However, there currently isn’t enough evidence to demonstrate the full extent to which fructose can contribute to these health issues. Nevertheless, numerous research studies have justified these controversial concerns.


Research studies have demonstrated that eating excess fructose can increase LDL or bad cholesterol which may lead to fat accumulation around the organs and heart disease. As a result, evidence showed that the deposition of fat in the liver due to the negative effects of this simple sugar can also result in non-alcoholic fatty liver disease. Eating excess fructose may also affect body fat regulation. Other research studies have demonstrated that because fructose doesn’t suppress appetite as much as other types of sugars do, it can promote overeating which may lead to obesity, insulin resistance, and type 2 diabetes. Furthermore, evidence has demonstrated that fructose can increase uric acid levels and cause gout.


For information regarding if fructose is bad for your health, please review the following article:

Health implications of fructose consumption: A review of recent data


AS PREVIOUSLY MENTIONED IN THE FOLLOWING ARTICLE, FRUCTOSE IS ONE OF THE MAIN COMPONENTS OF ADDED SUGAR. IT IS A SIMPLE SUGAR THAT MAKES UP APPROXIMATELY 50 PERCENT OF TABLE SUGAR OR SUCROSE. TABLE SUGAR ALSO CONSISTS OF GLUCOSE OR THE MAIN ENERGY SOURCE OF THE HUMAN BODY. HOWEVER, FRUCTOSE NEEDS TO BE CONVERTED INTO GLUCOSE BY THE LIVER BEFORE IT CAN BE UTILIZED AS FUEL FOR ENERGY BY OUR CELLS. FRUCTOSE, SUCROSE, AND GLUCOSE ARE ALL NATURALLY FOUND IN SEVERAL FRUITS, VEGETABLES, DAIRY PRODUCTS, AND WHOLE GRAINS AS WELL AS IN MANY PROCESSED FOODS. THE EFFECTS OF THIS SIMPLE SUGAR ON OUR HEALTH HAVE BEEN A CONTROVERSIAL TOPIC FOR MANY YEARS. RESEARCH STUDIES ARE STARTING TO DEMONSTRATE THE CONNECTION BETWEEN FRUCTOSE AND OBESITY, DIABETES, AND EVEN CANCER. IN THE FOLLOWING ARTICLE, WE DISCUSS IF FRUCTOSE IS BAD FOR YOUR HEALTH. DRINKING SMOOTHIES ADD A HEALTHY NUTRITIONAL BOOST.� -�DR. ALEX JIMENEZ D.C., C.C.S.T. INSIGHTS


Image of sweet and spicy juice recipe.


Sweet and Spicy Juice

Servings: 1
Cook time: 5-10 minutes

� 1 cup honeydew melons
� 3 cups spinach, rinsed
� 3 cups Swiss chard, rinsed
� 1 bunch cilantro (leaves and stems), rinsed
� 1-inch knob of ginger, rinsed, peeled, and chopped
� 2-3 knobs whole turmeric root (optional), rinsed, peeled, and chopped

Juice all ingredients in a high-quality juicer. Best served immediately.


Image of red peppers.


Red peppers have almost 2.5 times more vitamin C than oranges


Citrus fruits like oranges are a great source of vitamin C, however, there are other fruits and vegetables that offer an even better boost of this essential nutrient. Just half a red pepper, eaten raw, offers more than your requirement of vitamin C for the day, according to healthcare professionals. Cut it into crudit�s for a healthy mid-morning or afternoon snack. Red peppers are also rich in a variety of other essential nutrients, including vitamin A, B6, folate, and antioxidants!


The scope of our information is limited to chiropractic, musculoskeletal, physical medicines, wellness, and sensitive health issues and/or functional medicine articles, topics, and discussions. We use functional health & wellness protocols to treat and support care for injuries or disorders of the musculoskeletal system. Our posts, topics, subjects, and insights cover clinical matters, issues, and topics that relate and support directly or indirectly our clinical scope of practice.* Our office has made a reasonable attempt to provide supportive citations and has identified the relevant research study or studies supporting our posts. We also make copies of supporting research studies available to the board and or the public upon request. We understand that we cover matters that require an additional explanation as to how it may assist in a particular care plan or treatment protocol; therefore, to further discuss the subject matter above, please feel free to ask Dr. Alex Jimenez or contact us at 915-850-0900. The provider(s) Licensed in Texas*& New Mexico*�


Curated by Dr. Alex Jimenez D.C., C.C.S.T.


References:


  • Gunnars, Kris. �Is Fructose Bad for You? The Surprising Truth.� Healthline, Healthline Media, 23 Apr. 2018, www.healthline.com/nutrition/why-is-fructose-bad-for-you#section1.
  • Nall, Rachel. �Is Fructose Bad for You? Benefits, Risks, and Other Sugars.� Medical News Today, MediLexicon International, 28 Nov. 2018, www.medicalnewstoday.com/articles/323818.
  • Groves, Melissa. �Sucrose vs Glucose vs Fructose: What’s the Difference?� Healthline, Healthline Media, 8 June 2018, www.healthline.com/nutrition/sucrose-glucose-fructose.
  • Rizkalla, Salwa W. �Health Implications of Fructose Consumption: A Review of Recent Data.� National Center for Biotechnology Information, BioMed Central, 4 Nov. 2010, www.ncbi.nlm.nih.gov/pmc/articles/PMC2991323/.
  • Daniluk, Julie. �5 Health Benefits of Red Peppers. Plus, Our World’s Healthiest Pizza Recipe.� Chatelaine, 26 Feb. 2016, www.chatelaine.com/health/healthy-recipes-health/five-health-benefits-of-red-peppers/.


Three Ways Cruciferous Vegetables Prevent Cancer El Paso, TX.

Three Ways Cruciferous Vegetables Prevent Cancer El Paso, TX.

Research has given us even more reasons to eat our veggies. Several studies have revealed that certain types of vegetables, specifically those known as cruciferous vegetables, have properties that could make them useful in preventing cancer.

What are Cruciferous Vegetables?

Some of the crunchiest, tastiest vegetables belong to the Cruciferae family. Typically cool weather vegetables, they are most notably characterized by four petal flowers somewhat resembling a cross.

These flower buds or the leaves are the parts of these plants that are most often consumed. However, the seeds or roots of some of these vegetables are also edible. Incorporating some of these cruciferous vegetables into your diet may help lower your risk for cancer:

  • Broccoli
  • Cabbage
  • Wasabi
  • Collard greens
  • Bok choi
  • Brussels sprout
  • Arugula
  • Cauliflower
  • Mustard (leaves and seeds)
  • Turnips
  • Horseradish
  • Rutabaga
  • Kale
  • Radish
  • Watercress

What is the Link Between Cruciferous Vegetables and Cancer?

Cruciferous vegetables are packed with nutrients that are believed to lower a person�s risk for several types of cancers, including prostate cancer, colorectal cancer, lung cancer, and breast cancer. This includes the carotenoids zeaxanthin, lutein, and beta-carotene as well as folate and vitamins C, E, and K. They are also rich in minerals and an excellent source of fiber which is well known for preventing colorectal cancer.

This group of vegetables is also a good dietary source of glucosinolates which also has cancer-fighting properties. When intact, the glucosinolates are not effective, but when they are broken down through chewing, processing, and pests, they then make contact with the myrosinase enzyme and initiate a process that releases specific chemicals that can prevent cancer.

cruciferous vegetables prevent cancer el paso tx.

How Cruciferous Vegetables Prevent Cancer

There are three primary ways that cruciferous vegetables can prevent cancer. Researchers have found substantial evidence that shows when they are part of a healthy, clean, low-fat diet, a person�s risk of cancer can be decreased.

  • Glucosinolates � These are chemicals that contain sulfur and are present in all cruciferous vegetables, giving them their trademark bitter flavor and pungent aroma. When this substance is broken down by chewing, preparation, or digestion, it forms certain compounds (indole-3-carbinol and sulforaphane) that scientists have identified as having �anticancer properties.� They do this by impeding the development or growth of cancer. Studies have looked at this effect on mice and rats and found that it is particularly useful in specific organs. Researchers are also looking at other ways the substances can prevent cancer. When working in the body, they:
    • Have anti-inflammatory properties
    • Aid in preventing DNA damage to cells
    • Inhibit the formation of blood vessels in tumors
    • Are antibacterial and antiviral
    • Inhibit the migration of tumor cells, thus halting metastasis
    • Cause cancerous cells to die
    • Aid in causing carcinogens to become inactiveBioactive components � Some studies have shown that the bioactive components of these veggies can affect the biomarkers of processes related to cancer in the human body such as decreasing abnormal cell growth. Genetic encoding of glutathione S-transferase � Glutathione S-transferase is an enzyme that helps the body metabolize and eliminate isothiocyanates. This is important because isothiocyanates prevent the activation of carcinogens, increase the speed at which the carcinogens are removed from the body, and counteract the dangerous effects of active carcinogens.

Best Ways to Consume Cruciferous Vegetables

Cruciferous vegetables are at their most nutritious and have the greatest cancer-fighting properties when they are raw. When the vegetables are chopped and chewed they release the most cancer-fighting chemicals. Likewise, when they are cooked, they lose a great deal of those properties. Steaming or cooking the vegetables very lightly for less than 5 minutes will allow them to retain some of those cancer-fighting properties.

So, make sure that you incorporate cruciferous vegetables into your diet at least three times a week. If you need further guidance, ask our doctor of chiropractic Dr. Jimenez. We're here to help!

6 Day *DETOX DIET* Treatment | El Paso, TX (2019)

Nrf2 Explained: The Keap1-Nrf2 Pathway

Nrf2 Explained: The Keap1-Nrf2 Pathway

Oxidative stress is described as cell damage caused by free radicals, or unstable molecules, which can ultimately affect healthy function. The human body creates free radicals to neutralize bacteria and viruses, however, external factors, such as oxygen, pollution, and radiation, can often also produce free radicals. Oxidative stress has been associated with numerous health issues.


Oxidative stress and other stressors turn on internal protective mechanisms which can help regulate the human body’s antioxidant response. Nrf2 is a protein which senses levels of oxidative stress and enables the cells to protect themselves from internal and external factors. Nrf2 has also been demonstrated to help regulate genes involved in the production of antioxidant enzymes and stress-response genes. The purpose of the article below is to explain the effects of Nrf2 in cancer.


Abstract


The Keap1-Nrf2 pathway is the major regulator of cytoprotective responses to oxidative and electrophilic stress. Although cell signaling pathways triggered by the transcription factor Nrf2 prevent cancer initiation and progression in normal and premalignant tissues, in fully malignant cells Nrf2 activity provides growth advantage by increasing cancer chemoresistance and enhancing tumor cell growth. In this graphical review, we provide an overview of the Keap1-Nrf2 pathway and its dysregulation in cancer cells. We also briefly summarize the consequences of constitutive Nrf2 activation in cancer cells and how this can be exploited in cancer gene therapy.


Keywords: Nrf2, Keap1, Cancer, Antioxidant response element, Gene therapy


Introduction


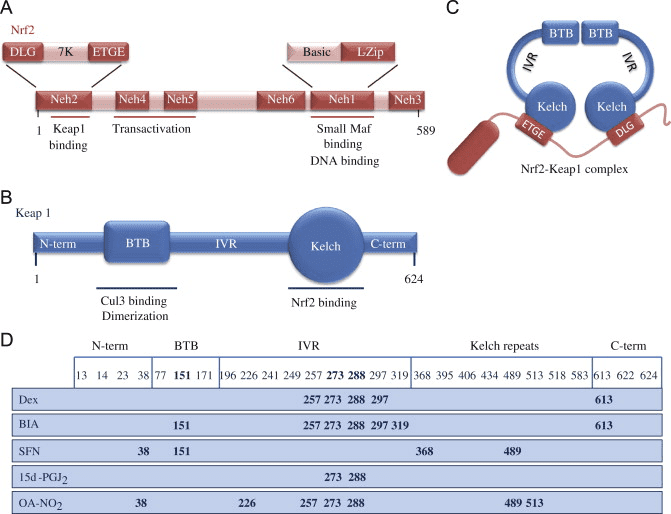
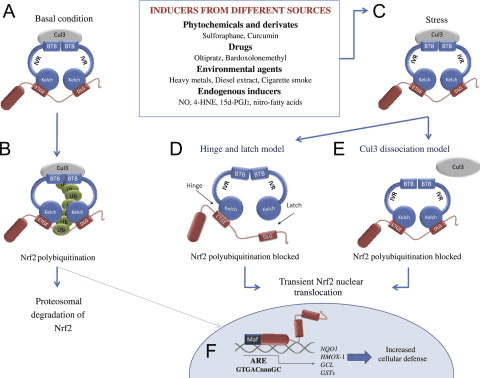
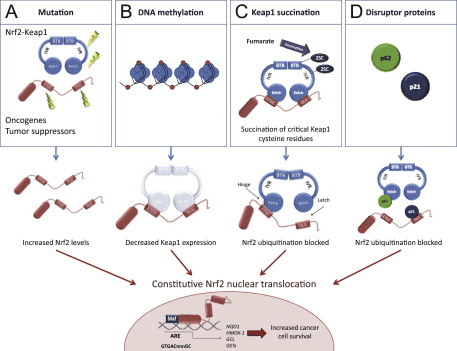
The Keap1-Nrf2 pathway is the major regulator of cytoprotective responses to endogenous and exogenous stresses caused by reactive oxygen species (ROS) and electrophiles [1]. The key signaling proteins within the pathway are the transcription factor Nrf2 (nuclear factor erythroid 2-related factor 2) that binds together with small Maf proteins to the antioxidant response element (ARE) in the regulatory regions of target genes, and Keap1 (Kelch ECH associating protein 1), a repressor protein that binds to Nrf2 and promotes its degradation by the ubiquitin proteasome pathway (Fig. 1). Keap1 is a very cysteine-rich protein, mouse Keap1 having a total of 25 and human 27 cysteine residues, most of which can be modified in vitro by different oxidants and electrophiles [2]. Three of these residues, C151, C273 and C288, have been shown to play a functional role by altering the conformation of Keap1 leading to nuclear translocation of Nrf2 and subsequent target gene expression [3] (Fig. 1). The exact mechanism whereby cysteine modifications in Keap1 lead to Nrf2 activation is not known, but the two prevailing but not mutually exclusive models are (1) the �hinge and latch� model, in which Keap1 modifications in thiol residues residing in the IVR of Keap1 disrupt the interaction with Nrf2 causing a misalignment of the lysine residues within Nrf2 that can no longer be polyubiquitinylated and (2) the model in which thiol modification causes dissociation of Cul3 from Keap1 [3]. In both models, the inducer-modified and Nrf2-bound Keap1 is inactivated and, consequently, newly synthesized Nrf2 proteins bypass Keap1 and translocate into the nucleus, bind to the ARE and drive the expression of Nrf2 target genes such as NAD(P)H quinone oxidoreductase 1 (NQO1), heme oxygenase 1 (HMOX1), glutamate-cysteine ligase (GCL) and glutathione S transferases (GSTs) (Fig. 2). In addition to modifications of Keap1 thiols resulting in Nrf2 target gene induction, proteins such as p21 and p62 can bind to Nrf2 or Keap1 thereby disrupting the interaction between Nrf2 and Keap1 [1], [3] (Fig. 3).


Fig. 1. Structures of Nrf2 and Keap1 and the cysteine code. (A) Nrf2 consists of 589 amino acids and has six evolutionarily highly conserved domains, Neh1-6. Neh1 contains a bZip motif, a basic region � leucine zipper (L-Zip) structure, where the basic region is responsible for DNA recognition and the L-Zip mediates dimerization with small Maf proteins. Neh6 functions as a degron to mediate degradation of Nrf2 in the nucleus. Neh4 and 5 are transactivation domains. Neh2 contains ETGE and DLG motifs, which are required for the interaction with Keap1, and a hydrophilic region of lysine residues (7 K), which are indispensable for the Keap1-dependent polyubiquitination and degradation of Nrf2. (B) Keap1 consists of 624 amino acid residues and has five domains. The two protein�protein interaction motifs, the BTB domain and the Kelch domain, are separated by the intervening region (IVR). The BTB domain together with the N-terminal portion of the IVR mediates homodimerization of Keap1 and binding with Cullin3 (Cul3). The Kelch domain and the C-terminal region mediate the interaction with Neh2. (C) Nrf2 interacts with two molecules of Keap1 through its Neh2 ETGE and DLG motifs. Both ETGE and DLG bind to similar sites on the bottom surface of the Keap1 Kelch motif. (D) Keap1 is rich in cysteine residues, with 27 cysteines in human protein. Some of these cysteines are located near basic residues and are therefore excellent targets of electrophiles and oxidants. The modification pattern of the cysteine residues by electrophiles is known as the cysteine code. The cysteine code hypothesis proposes that structurally different Nrf2 activating agents affect different Keap1 cysteines. The cysteine modifications lead to conformational changes in the Keap1 disrupting the interaction between the Nrf2 DLG and Keap1 Kelch domains, thus inhibiting the polyubiquitination of Nrf2. The functional importance of Cys151, Cys273 and Cys288 has been shown, as Cys273 and Cys288 are required for suppression of Nrf2 and Cys151 for activation of Nrf2 by inducers [1], [3].


Fig. 2. The Nrf2-Keap1 signaling pathway. (A and B) in basal conditions, two Keap1 molecules bind to Nrf2 and Nrf2 is polyubiquitylated by the Cul3-based E3 ligase complex. This polyubiquitilation results in rapid Nrf2 degradation by the proteasome. A small proportion of Nrf2 escapes the inhibitory complex and accumulates in the nucleus to mediate basal ARE-dependent gene expression, thereby maintaining the cellular homeostasis. (C) Under stress conditions, inducers modify the Keap1 cysteines leading to the inhibition of Nrf2 ubiquitylation via dissociation of the inhibitory complex. (D) According to the hinge and latch model, modification of specific Keap1 cysteine residues leads to conformational changes in Keap1 resulting in the detachment of the Nrf2 DLG motif from Keap1. Ubiquitination of Nrf2 is disrupted but the binding with the ETGE motif remains. (E) In the Keap1-Cul3 dissociation model, the binding of Keap1 and Cul3 is disrupted in response to electrophiles, leading to the escape of Nrf2 from the ubiquitination system. In both of the suggested models, the inducer-modified and Nrf2-bound Keap1 is inactivated and, consequently, newly synthesized Nrf2 proteins bypass Keap1 and translocate into the nucleus, bind to the Antioxidant Response Element (ARE) and drive the expression of Nrf2 target genes such as NQO1, HMOX1, GCL and GSTs [1], [3].


Fig. 3. Mechanisms for constitutive nuclear accumulation of Nrf2 in cancer. (A) Somatic mutations in Nrf2 or Keap1 disrupt the interaction of these two proteins. In Nrf2, mutations affect ETGE and DLG motifs, but in Keap1 mutations are more evenly distributed. Furthermore, oncogene activation, such as KrasG12D[5], or disruption of tumor suppressors, such as PTEN [11] can lead to transcriptional induction of Nrf2 and an increase in nuclear Nrf2. (B) Hypermethylation of the Keap1 promoter in lung and prostate cancer leads to reduction of Keap1 mRNA expression, which increases the nuclear accumulation of Nrf2 [6], [7]. (C) In familial papillary renal carcinoma, the loss of fumarate hydratase enzyme activity leads to the accumulation of fumarate and further to succination of Keap1 cysteine residues (2SC). This post-translational modification leads to the disruption of Keap1-Nrf2 interaction and nuclear accumulation of Nrf2 [8], [9]. (D) Accumulation of disruptor proteins such as p62 and p21 can disturb Nrf2-Keap1 binding and results in an increase in nuclear Nrf2. p62 binds to Keap1 overlapping the binding pocket for Nrf2 and p21 directly interacts with the DLG and ETGE motifs of Nrf2, thereby competing with Keap1 [10].


Mechanisms of Activation and Dysregulation of Nrf2 in Cancer


Although cytoprotection provided by Nrf2 activation is important for cancer chemoprevention in normal and premalignant tissues, in fully malignant cells Nrf2 activity provides growth advantage by increasing cancer chemoresistance and enhancing tumor cell growth [4]. Several mechanisms by which Nrf2 signaling pathway is constitutively activated in various cancers have been described: (1) somatic mutations in Keap1 or the Keap1 binding domain of Nrf2 disrupting their interaction; (2) epigenetic silencing of Keap1 expression leading to defective repression of Nrf2; (3) accumulation of disruptor proteins such as p62 leading to dissociation of the Keap1-Nrf2 complex; (4) transcriptional induction of Nrf2 by oncogenic K-Ras, B-Raf and c-Myc; and (5) post-translational modification of Keap1 cysteines by succinylation that occurs in familial papillary renal carcinoma due to the loss of fumarate hydratase enzyme activity [3], [4], [5], [6], [7], [8], [9], [10] (Fig. 3). Constitutively abundant Nrf2 protein causes increased expression of genes involved in drug metabolism thereby increasing the resistance to chemotherapeutic drugs and radiotherapy. In addition, high Nrf2 protein level is associated with poor prognosis in cancer [4]. Overactive Nrf2 also affects cell proliferation by directing glucose and glutamine towards anabolic pathways augmenting purine synthesis and influencing the pentose phosphate pathway to promote cell proliferation [11] (Fig. 4).


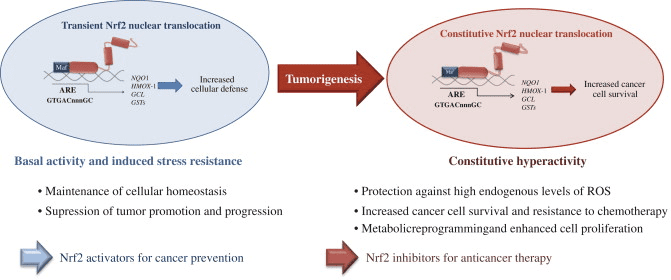
Fig. 4. The dual role of Nrf2 in tumorigenesis. Under physiological conditions, low levels of nuclear Nrf2 are sufficient for the maintenance of cellular homeostasis. Nrf2 inhibits tumor initiation and cancer metastasis by eliminating carcinogens, ROS and other DNA-damaging agents. During tumorigenesis, accumulating DNA damage leads to constitutive hyperactivity of Nrf2 which helps the autonomous malignant cells to endure high levels of endogenous ROS and to avoid apoptosis. Persistently elevated nuclear Nrf2 levels activate metabolic genes in addition to the cytoprotective genes contributing to metabolic reprogramming and enhanced cell proliferation. Cancers with high Nrf2 levels are associated with poor prognosis because of radio and chemoresistance and aggressive cancer cell proliferation. Thus, Nrf2 pathway activity is protective in the early stages of tumorigenesis, but detrimental in the later stages. Therefore, for the prevention of cancer, enhancing Nrf2 activity remains an important approach whereas for the treatment of cancer, Nrf2 inhibition is desirable [4], [11].


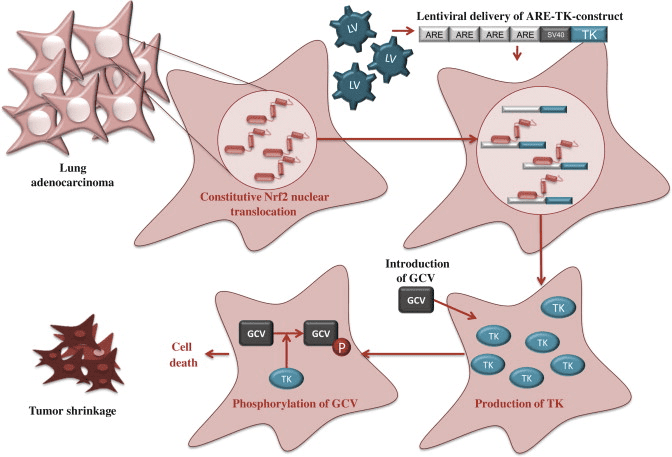
Given that high Nrf2 activity commonly occurs in cancer cells with adverse outcomes, there is a need for therapies to inhibit Nrf2. Unfortunately, due to structural similarity with some other bZip family members, the development of specific Nrf2 inhibitors is a challenging task and only a few studies of Nrf2 inhibition have been published to date. By screening natural products, Ren et al. [12] identified an antineoplastic compound brusatol as an Nrf2 inhibitor that enhances the chemotherapeutic efficacy of cisplatin. In addition, PI3K inhibitors [11], [13] and Nrf2 siRNA [14] have been used to inhibit Nrf2 in cancer cells. Recently, we have utilized an alternative approach, known as cancer suicide gene therapy, to target cancer cells with high Nrf2 levels. Nrf2-driven lentiviral vectors [15] containing thymidine kinase (TK) are transferred into cancer cells with high ARE activity and the cells are treated with a pro-drug, ganciclovir (GCV). GCV is metabolized to GCV-monophosphate, which is further phosphorylated by cellular kinases into a toxic triphosphate form [16] (Fig. 5). This leads to effective killing of not only TK containing tumor cells, but also the neighboring cells due to the bystander effect [17]. ARE-regulated TK/GCV gene therapy can be further enhanced via combining a cancer chemotherapeutic agent doxorubicin to the treatment [16], supporting the notion that this approach could be useful in conjuction with traditional therapies.


Fig. 5. Suicide gene therapy. Constitutive Nrf2 nuclear accumulation in cancer cells can be exploited by using Nrf2-driven viral vector for cancer suicide gene therapy [16]. In this approach, lentiviral vector (LV) expressing thymidine kinase (TK) under minimal SV40 promoter with four AREs is transduced to lung adenocarcinoma cells. High nuclear Nrf2 levels lead to robust expression of TK through Nrf2 binding. Cells are then treated with a pro-drug, ganciclovir (GCV), which is phosphorylated by TK. Triphosphorylated GCV disrupts DNA synthesis and leads to effective killing of not only TK containing tumor cells, but also the neighboring cells due to the bystander effect.


Dr Jimenez White Coat

Nrf2 is a master regulator which triggers the production of powerful antioxidants in the human body which help eliminate oxidative stress. Various antioxidant enzymes, such as superoxide dismutase, or SOD, glutathione, and catalase, are also activated through the Nrf2 pathway. Furthermore, certain phytochemicals like turmeric, ashwagandha, bacopa, green tea, and milk thistle, activate Nrf2. Research studies have found that Nrf2 activation can naturally enhance cellular protection and restore balance to the human body.

Dr. Alex Jimenez D.C., C.C.S.T. Insight


Sulforaphane and Its Effects on Cancer, Mortality, Aging, Brain and Behavior, Heart Disease & More


Isothiocyanates are some of the most important plant compounds you can get in your diet. In this video I make the most comprehensive case for them that has ever been made. Short attention span? Skip to your favorite topic by clicking one of the time points below. Full timeline below.


Key sections:


  • 00:01:14 – Cancer and mortality
  • 00:19:04 – Aging
  • 00:26:30 – Brain and behavior
  • 00:38:06 – Final recap
  • 00:40:27 – Dose


Full timeline:


  • 00:00:34 – Introduction of sulforaphane, a major focus of the video.
  • 00:01:14 – Cruciferous vegetable consumption and reductions in all-cause mortality.
  • 00:02:12 – Prostate cancer risk.
  • 00:02:23 – Bladder cancer risk.
  • 00:02:34 – Lung cancer in smokers risk.
  • 00:02:48 – Breast cancer risk.
  • 00:03:13 – Hypothetical: what if you already have cancer? (interventional)
  • 00:03:35 – Plausible mechanism driving the cancer and mortality associative data.
  • 00:04:38 – Sulforaphane and cancer.
  • 00:05:32 – Animal evidence showing strong effect of broccoli sprout extract on bladder tumor development in rats.
  • 00:06:06 – Effect of direct supplementation of sulforaphane in prostate cancer patients.
  • 00:07:09 – Bioaccumulation of isothiocyanate metabolites in actual breast tissue.
  • 00:08:32 – Inhibition of breast cancer stem cells.
  • 00:08:53 – History lesson: brassicas were established as having health properties even in ancient Rome.
  • 00:09:16 – Sulforaphane’s ability to enhance carcinogen excretion (benzene, acrolein).
  • 00:09:51 – NRF2 as a genetic switch via antioxidant response elements.
  • 00:10:10 – How NRF2 activation enhances carcinogen excretion via glutathione-S-conjugates.
  • 00:10:34 – Brussels sprouts increase glutathione-S-transferase and reduce DNA damage.
  • 00:11:20 – Broccoli sprout drink increases benzene excretion by 61%.
  • 00:13:31 – Broccoli sprout homogenate increases antioxidant enzymes in the upper airway.
  • 00:15:45 – Cruciferous vegetable consumption and heart disease mortality.
  • 00:16:55 – Broccoli sprout powder improves blood lipids and overall heart disease risk in type 2 diabetics.
  • 00:19:04 – Beginning of aging section.
  • 00:19:21 – Sulforaphane-enriched diet enhances lifespan of beetles from 15 to 30% (in certain conditions).
  • 00:20:34 – Importance of low inflammation for longevity.
  • 00:22:05 – Cruciferous vegetables and broccoli sprout powder seem to reduce a wide variety of inflammatory markers in humans.
  • 00:23:40 – Mid-video recap: cancer, aging sections
  • 00:24:14 – Mouse studies suggest sulforaphane might improve adaptive immune function in old age.
  • 00:25:18 – Sulforaphane improved hair growth in a mouse model of balding. Picture at 00:26:10.
  • 00:26:30 – Beginning of brain and behavior section.
  • 00:27:18 – Effect of broccoli sprout extract on autism.
  • 00:27:48 – Effect of glucoraphanin on schizophrenia.
  • 00:28:17 – Start of depression discussion (plausible mechanism and studies).
  • 00:31:21 – Mouse study using 10 different models of stress-induced depression show sulforaphane similarly effective as fluoxetine (prozac).
  • 00:32:00 – Study shows direct ingestion of glucoraphanin in mice is similarly effective at preventing depression from social defeat stress model.
  • 00:33:01 – Beginning of neurodegeneration section.
  • 00:33:30 – Sulforaphane and Alzheimer’s disease.
  • 00:33:44 – Sulforaphane and Parkinson’s disease.
  • 00:33:51 – Sulforaphane and Hungtington’s disease.
  • 00:34:13 – Sulforaphane increases heat shock proteins.
  • 00:34:43 – Beginning of traumatic brain injury section.
  • 00:35:01 – Sulforaphane injected immediately after TBI improves memory (mouse study).
  • 00:35:55 – Sulforaphane and neuronal plasticity.
  • 00:36:32 – Sulforaphane improves learning in model of type II diabetes in mice.
  • 00:37:19 – Sulforaphane and duchenne muscular dystrophy.
  • 00:37:44 – Myostatin inhibition in muscle satellite cells (in vitro).
  • 00:38:06 – Late-video recap: mortality and cancer, DNA damage, oxidative stress and inflammation, benzene excretion, cardiovascular disease, type II diabetes, effects on the brain (depression, autism, schizophrenia, neurodegeneration), NRF2 pathway.
  • 00:40:27 – Thoughts on figuring out a dose of broccoli sprouts or sulforaphane.
  • 00:41:01 – Anecdotes on sprouting at home.
  • 00:43:14 – On cooking temperatures and sulforaphane activity.
  • 00:43:45 – Gut bacteria conversion of sulforaphane from glucoraphanin.
  • 00:44:24 – Supplements work better when combined with active myrosinase from vegetables.
  • 00:44:56 – Cooking techniques and cruciferous vegetables.
  • 00:46:06 – Isothiocyanates as goitrogens.


Acknowledgments


This work was supported by the Academy of Finland, the Sigrid Juselius Foundation and the Finnish Cancer Organisations.


In conclusion, nuclear factor (erythroid-derived 2)-like 2, also known as NFE2L2 or Nrf2, is a protein which increases the production of antioxidants which protect the human body against oxidative stress. As described above, the stimulation of the Nrf2 pathway are being studies for the treatment of diseases caused by oxidative stress, including cancer. The scope of our information is limited to chiropractic and spinal health issues. To discuss the subject matter, please feel free to ask Dr. Jimenez or contact us at�915-850-0900�.


Curated by Dr. Alex Jimenez


Referenced from:�Sciencedirect.com


Green Call Now Button H .png


Additional Topic Discussion: Relieving Knee Pain without Surgery


Knee pain is a well-known symptom which can occur due to a variety of knee injuries and/or conditions, including�sports injuries. The knee is one of the most complex joints in the human body as it is made-up of the intersection of four bones, four ligaments, various tendons, two menisci, and cartilage. According to the American Academy of Family Physicians, the most common causes of knee pain include patellar subluxation, patellar tendinitis or jumper’s knee, and Osgood-Schlatter disease. Although knee pain is most likely to occur in people over 60 years old, knee pain can also occur in children and adolescents. Knee pain can be treated at home following the RICE methods, however, severe knee injuries may require immediate medical attention, including chiropractic care.


blog picture of cartoon paper boy


EXTRA EXTRA | IMPORTANT TOPIC: Recommended El Paso, TX Chiropractor


***

How Chiropractic Can Be Used As Supportive Care For Cancer

How Chiropractic Can Be Used As Supportive Care For Cancer

Cancer puts a tremendous amount of stress on the body. Cancer treatments add to that stress, affecting the organs as well as the musculoskeletal system. Pain is a common complaint among cancer patients. They experience a variety of aches and pains including headaches, neck pain, muscle tension, and back pain as well as painful peripheral neuropathy. They may also have mobility problems and difficulty walking.

Many cancer patients have found chiropractic care to be a very effective treatment for pain management and to improve flexibility, mobility, and muscle strength. They find it helps to reduce stress and helps the body function more efficiently.

It provides these benefits without the use of medication or invasive treatments. For patients undergoing chemotherapy, it is very beneficial because chiropractic�s whole body approach to wellness helps to combat the debilitating effects of the treatment.

Benefits of Chiropractic Care for Cancer Patients

There are many different reasons that cancer patients may seek chiropractic treatment. Cancer is, in itself, very hard on the body. The disease can cause headaches, muscle stiffness, neck pain, and back pain. However, the treatments can also cause problems.

Patients undergoing radiation treatment must lie on a table for extended periods of time which can be very uncomfortable. Surgery can cause pain in the joints and connective tissues. Chemotherapy drugs can cause unpleasant side effects including nausea, neuropathy, and headaches.

Some of the ways chiropractic care can help cancer patients include:

  • The relief of nausea, headaches, and fatigue
  • Improved balance
  • Alleviation of neck and back pain and stiffness
  • Reduction of joint inflammation
  • Better mobility
  • Restoration of nerve function
  • Reduced muscle tension

Often cancer patients have also reported improvements beyond the typical musculoskeletal complaints that chiropractic treats. Reduced effects of peripheral neuropathy, improved digestion, and even easier respiratory function are just some of the added benefits.

cancer chiropractic support el paso tx.

Chiropractic Treatment Approaches

Chiropractors use a drug-free, hands-on approach to treatment for a wide range of issues. It restores nerve function, corrects musculoskeletal problems, and helps to bring the body back into proper alignment. It is non-invasive and offers patients a safe, natural alternative to medications and other treatments that can have unwanted side effects.

One barrier that may prevent a patient from seeking chiropractic care is the common misconception that it is aggressive and forceful, even painful. The truth is, most chiropractic techniques are very gentle, applying very low force and some no force at all.

Most are also not painful at all and work quickly to enhance the range of motion and increase energy as well as reduce pain. It can help relieve a patient�s symptoms while helping them stay strong while they undergo treatment.

Some of the chiropractic treatment options that are used for cancer patients include:

  • Spinal manipulation
  • Ice
  • Heat
  • Hands-on adjustments
  • Non-force techniques
  • Electrical muscle stimulation
  • Massage
  • Special instrument applications
  • Traction

The Whole-Body Wellness Advantage

Whole body wellness is an integral part of chiropractic care. It can involve diet modification, lifestyle changes, exercise, and stress reduction practices.

When a chiropractor treats a cancer patient � or any patient � he or she will look beyond the obvious issues or symptoms to find the root of the problem and ways to help the body heal itself. Sometimes this may involve supplements, vitamins, or minerals that will aid in correcting the condition. Other times it may simply be a matter of getting the body to a healthy state where it is strong enough to combat the condition or heal from injury.

The treatment is individualized and tailored specifically to the patient�s needs and lifestyle. For instance, many conditions benefit from weight loss or exercise, and many pain issues respond well to adjustments in diet and stress reduction. Chiropractic looks at the whole body and works to provide it with what it needs to get strong and get healthy.

Chiropractor Recommended

Prostate Cancer, Nutrition And Dietary Interventions

Prostate Cancer, Nutrition And Dietary Interventions

Prostate Cancer: Abstract

Prostate cancer (PCa) remains a leading cause of mortality in US men and the prevalence continues to rise world-wide especially in countries where men consume a �Western-style� diet. Epidemiologic, preclinical and clinical studies suggest a potential role for dietary intake on the incidence and progression of PCa. 'This minireview provides an overview of recent published literature with regard to nutrients, dietary factors, dietary patterns and PCa incidence and progression. Low carbohydrates intake, soy protein, omega-3 (w-3) fat, green teas, tomatoes and tomato products and zyflamend showed promise in reducing PCa risk or progression. A higher saturated fat intake and a higher ?-carotene status may increase risk. A �U� shape relationship may exist between folate, vitamin C, vitamin D and calcium with PCa risk. Despite the inconsistent and inconclusive findings, the potential for a role of dietary intake for the prevention and treatment of PCa is promising. The combination of all the beneficial factors for PCa risk reduction in a healthy dietary pattern may be the best dietary advice. This pattern includes rich fruits and vegetables, reduced refined carbohydrates, total and saturated fats, and reduced cooked meats. Further carefully designed prospective trials are warranted.

Keywords: Diet, Prostate cancer, Nutrients, Dietary pattern, Lifestyle, Prevention, Treatment, Nutrition, Dietary intervention, Review

Introduction: Prostate Cancer

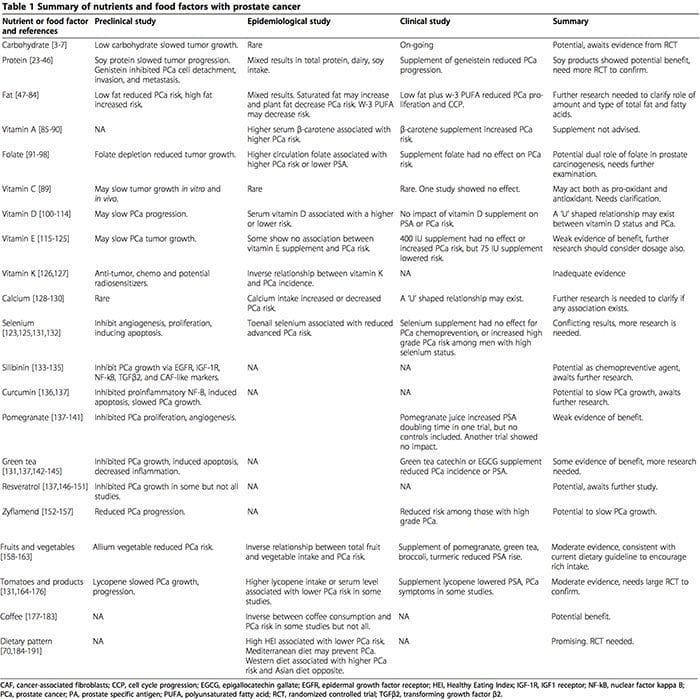
Prostate cancer (PCa) is the second most common cancer in men, with nearly a million new cases diagnosed worldwide per year [1], with approximately a six-fold higher incidence in Western than in non-Western countries. Diet, lifestyle, environmental and genetic factors are hypothesized to play a role in these differences. This review focuses on the latest evidence of the potential role of dietary factors on PCa and includes epidemiologic and clinical trial evidence for the impact of protein, fat, carbohydrate, fiber, phytochemicals, other food components, whole foods and dietary patterns on PCa incidence, development and/or progression. Data from meta-analyses or well-designed randomized trials and prospective studies are emphasized in this review. It should be noted that studies of dietary intake or nutrition and cancer are often subject to various limitations and thus complicate interpretation of results. For example, when a study is designed to examine the effect of the amount of fat intake, alteration in fat intake inevitably will change intake of protein and/or carbohydrate, and may change the intake of other nutrients as well. As a result, it is difficult to attribute the effect to change in fat intake alone. In addition, the impact of macronutrients potentially involves aspects of both absolute quantity and the type of macronutrients consumed. Both aspects may potentially affect cancer initiation and/or development independently, but they are not always distinguishable in research designs. Though this topic was recently reviewed [2], given the extensive new literature on the topic, an updated review is presented herein and a summary table is provided for a quick reference (Table 1).

Nutrients Carbohydrates Given the hypothesis that insulin is a growth factor for PCa, it has been hypothesized that reducing carbohydrates and thus lowering serum insulin may slow PCa growth [3]. Indeed, in animal models, either a no-carbohydrate ketogenic diet (NCKD) [4,5] or a low-carbohydrate diet (20% kcal as carbohydrate) has favorable effects on slowing prostate tumor growth [6,7]. In human studies, one�study found that high intake of refined carbohydrates was associated with increased risk of PCa [7]. In addition to the amount of carbohydrates, type of carbohydrates may impact on PCa but research has been inconclusive. The potential to reduce PCa risk and progression via impacting carbohydrate metabolism is actively being investigated with Metformin. Metformin reduced PCa cell proliferation and delayed progression in vitro and in vivo, respectively [8-10] and reduced incident risk and mortality in humans [11-13]. Two single arm clinical trials also showed a positive effect of metformin in affecting markers of PCa proliferation and progression [14,15]. However, other retrospective cohort studies have not supported an effect of metformin on recurrence or incident risk of PCa [16-22]. Despite the potential for reducing either total or simple carbohydrates in benefiting PCa control, evidence is lacking from randomized controlled trials (RCT). Two randomized trials are on-going examining the impact of a low-carbohydrate diet (approximately 5% kcal) on the PSA doubling time among PCa patients post radical prostatectomy (NCT01763944) and on glycemic response among patients initiating androgen deprivation therapy (ADT) (NCT00932672 ). Findings from these trials will shed light on the effect of carbohydrate intake on markers of PCa progression and the role of reduced carbohydrate intake on offsetting the side effects of ADT.

Protein

The ideal level of protein intake for optimal overall health or prostate health is unclear. Despite the popularity of low carbohydrate diets that are high in protein, recent human studies reported that low protein intake was associated with lower risk for cancer and overall mortality among men 65 and younger. Among men older than 65, low protein intake was associated with a higher risk for cancer and overall mortality [23]. In animal models the ratio between protein and carbohydrate impacted on cardiometabolic health, aging and longevity [24]. The role of dietary protein and the protein to carbohydrate ratio on PCa development and progression requires further study.

Animal-Based Proteins

Studying protein intake, like all aspects of nutritional science, can be challenging. For example, animal meat, which is a source of protein in Western diets, is composed not only of protein, but also of fat, cholesterol, minerals and other nutrients. The amount of these nutrients including fatty acids may vary from one animal meat to the other. Previous studies in human have shown that consumption of skinless poultry, which is lower in cholesterol and saturated fat than many red meats, was not associated with the recurrence or progression of PCa [25]. However, consumption of baked poultry was inversely associated with advanced PCa [26,27], while cooked red meat was associated with increased advanced PCa risk [26,27]. Thus, how the food is prepared may modify its impact on PCa risk and progression. Overall, fish consumption may be associated with reduced PCa mortality, but high temperature cooked fish may contribute to PCa carcinogenesis [28]. Thus, it may be advisable to consume fish regularly but cooking temperature should be kept moderate.

Dairy-Based Protein

Another common protein source is dairy products, such as milk, cheese and yogurt. Previous studies have shown that dairy increased overall PCa risk but not with aggressive or lethal PCa [29,30]. In addition, both whole milk and low-fat milk consumption were reported to either promote or delay PCa progression [29,31]. In the Physicians Health follow up cohort with 21,660 men, total dairy consumption was found to be associated with increased PCa incidence [32]. In particular, low fat or skim milk increased low grade PCa, whereas whole milk increased fatal PCa risk. Though the exact component(s) of dairy products driving these associations is unknown, the high concentrations of saturated fat and calcium may be involved. A cross-sectional study of 1798 men showed that dairy protein was positively associated with serum IGF-1 [33] levels which may stimulate initiation or progression of PCa. Thus, further research is needed to clarify the relationship between dairy intake and PCa. There is insufficient data to provide recommendations specifically related to dairy or dairy protein and PCa risk or progression.

Plant-Based Proteins

Soy and soy-based products are rich in protein and phytoestrogens that may facilitate PCa prevention, but its role on PCa is unclear. In a study in mice, intake of soy products was associated with decreased hepatic aromatase, 5?-reductase, expression of androgen receptor and its regulated genes, FOXA1, urogenital tract weight and PCa tumor progression [34]. A recent randomized trial of 177 men with high-risk disease after radical prostatectomy found that soy protein supplementation for two years had no effect on risk of PCa recurrence [35]. Although epidemiological and pre-clinical studies [36,37] support a potential role for soy/soy isoflavones in PCa risk reduction or progression, a meta-analysis did not find significant impact of soy intake in PSA levels, sex hormone-binding globulin, testosterone, free testosterone, estradiol or dihydrotestosterone [38]. Another RCT in patients before prostatectomy also did not find any effect of soy isoflavone supplement up to six weeks on PSA, serum total testosterone, free testosterone, total estrogen, estradiol or total cholesterol [39]. Since most RCTs�conducted have been small and of short duration, further examination is needed.

Many studies have continued to examine the primary isoflavone in soy, genistein, and its effect on PCa. The potential for genistein to inihibit PCa cell detachment, invasion and metastasis is reported [40]. Genistein may modify glucose update and glucose transporter (GLUT) expression in PCa cells [41], or exert its anti-tumor effect by down regulating several microRNAs [42]. Studies using tumor cells and animal models suggest genistein may compete with and block endogenous estrogens from binding to the estrogen receptor, thereby inhibiting cellular proliferation, growth, and inducing differentiation and, specifically, genistein may inhibit cell detachment, protease production, cell invasion and thus prevent metastasis [36,40,43]. However, neither plasma nor urinary genistein levels were associated with PCa risk in case control studies [44,45]. In a phase 2 placebo-controlled RCT with 47 men, supplementation of 30 mg genistein for three to six weeks significantly reduced androgen-related markers of PCa progression [46]. In addition, genistein may be beneficial in improving cabazitaxel chemotherapy in metastatic castration-resistant PCa [37]. Clinical studies are warranted to further examine the role of soy and soy isoflavones for PCa prevention or treatment. A definitive recommendation regarding protein intake for PCa prevention or treatment is not available yet.

Fat

Research findings examining fat consumption with PCa risk or progression are conflicting. Both the total absolute intake [47] of dietary fat and the relative fatty acid composition may independently relate to PCa initiation and/or progression. While animal studies repeatedly show that reducing dietary fat intake slows tumor growth [48-50] and high fat diets, especially animal fat and corn oil increase PCa progression [51], human data are less consistent. Case�control studies and cohort studies have shown either no association between total fat consumption and PCa risk [52-55] or an inverse association between fat intake and PCa survival, particularly among men with localized PCa [47]. In addition, a cross-sectional study showed that fat intake expressed as percent of total calorie intake was positively associated with PSA levels in 13,594 men without PCa [56]. Given these conflicting data, it is possible that the type of fatty acid [56] rather than total amount may play an important role in PCa development and progression. A study found plasma saturated fatty acids to be positively associated with PCa risk in a prospective cohort of 14,514 men of the Melbourne Collaborative Cohort Study [57]. In addition, another study found that eating more plant-based fat was associated with reduced PCa risk [58]. These studies support the current dietary guideline of eating less animal-based fat and more plant-based fat.

The data regarding omega-6 (w-6) and omega-3 (w-3) polyunsaturated fatty acid (PUFA) consumption and PCa risk are also conflicting. While there are data to support a link between increased w-6 PUFA intake (mainly derived from corn oil) and risk of overall and high-grade PCa [57,59], not all data support such a link [60]. In fact, a greater polyunsaturated fat intake was associated with a lower all cause mortality among men with nonmetastatic PCa in the Health Professionals Follow-up study [58]. The postulated mechanism linking w-6 PUFAs and PCa risk is the conversion of arachidonic acid (w-6 PUFA) to eicosanoids (prostaglandin E-2, hydroxyeicosatetraenoic acids and epoxyeicosatrienoic acids) leading to inflammation and cellular growth [61]. Conversely, w-3 PUFAs, which are found primarily in cold water oily fish, may slow growth of PCa through a number of mechanisms [61-63]. In a study of 48 men with low risk PCa under active surveillance, repeat biopsy in six months showed that prostate tissue w-3 fatty acids, especially eicosapentaenoic acid (EPA), may protect against PCa progression [64]. In vitro and animal studies suggest that w-3 PUFAs induce anti-inflammatory, pro-apoptotic, antiproliferative and anti-angiogenic pathways [65,66]. Moreover, a mouse study comparing various types of fat found that only the fish oil diet (that is, omega-3 based diet) slowed PCa growth relative to other dietary fats [67]. In regards to human data, a phase II randomized trial showed that a low-fat diet with w-3 supplementation four to six weeks prior to radical prostatectomy decreased PCa proliferation and cell cycle progression (CCP) score [62,68]. A low-fat fish oil diet resulted in decreased 15(S)- hydroxyeicosatetraenoic acid levels and lowered CCP score relative to a Western diet [69]. The potential benefits of omega-3 fatty acids from fish are supported by epidemiological literature showing that w-3 fatty acid intake was inversely associated with fatal PCa risk [70,71]. Despite the promise of omega-3 fatty acids, not all studies agree. Supplementing 2 g alpha-linolenic acid (ALA) per day for 40 months in 1,622 men with PSA <4 ng/ml did not change their PSA [72]. However, another study found that a high blood serum n-3 PUFA and docosapentaenoic acid (DPA) was associated with reduced total PCa risk while high serum EPA and docosahexaenoic acid (DHA) was possibly associated with increased high-grade PCa risk [73]. Further research is required to understand better the role of omega-3 PUFAs in PCa prevention or treatment.

Cholesterol

Many pre-clinical studies have shown that the accumulation of cholesterol contributes to the progression of PCa [74-76]. It was suggested that a high cholesterol in Lin et al. BMC Medicine (2015) 13:3 Page 5 of 15 circulation may be a risk factor for solid tumors, primarily through the upregulation of cholesterol synthesis, inflammatory pathways [77] and intratumoral steroidogenesis [78]. According to a recent study with 2,408 men scheduled for biopsy, serum cholesterol was independently associated with prediction of PCa risk [79]. Consistent with the cholesterol findings, usage of the cholesterol lowering drug statin post radical prostatectomy (RP) was significantly associated with reduced risk of biochemical recurrence in 1,146 radical prostatectomy patients [80]. Another study also showed that statins may reduce PCa risk by lowering progression [81]. Although the mechanism has not been established, more recent studies also showed that a low high-density lipoprotein (HDL) cholesterol level was associated with a higher risk for PCa and, thus, a higher HDL was protective [81-84]. These findings support the notion that a heart-healthy dietary intervention that lowers cholesterol may benefit prostate health also.

Vitamins & Minerals

Herein we will review the recent data on vitamins A, B complex, C, D, E, and K and selenium. In the two large clinical trials: the Carotene and Retinol Efficacy Trial (CARET; PCa was a secondary outcome) and the National Institutes of Health-American Association of Retired Persons (NIH-AARP) Diet and Health prospective cohort study, excessive multivitamin supplementation was associated with a higher risk of developing aggressive PCa, particularly among those taking individual ?-carotene supplements [85,86]. Similarly, high serum ?-carotene levels were associated with a higher risk for PCa among 997 Finnish men in the Kuopio Ischaemic Heart Disease Risk Factor cohort [87]. However, ?-carotene supplement was not found to affect risk for lethal PCa during therapy [88], or in the Danish prospective cohort study of 26,856 men [89]. Circulating retinol also was not associated with PCa risk in a large case�control study [90]. Thus, the association between vitamin A and PCa is still unclear.

Preclinical evidence suggests folate depletion may slow tumor growth, while supplementation has no effect on growth or progression, but may directly lead to epigenetic changes via increases in DNA methylation [91]. Two meta-analyses also showed that circulating folate levels were positively associated with an increased risk of PCa [92,93], while dietary or supplemental folate had no effect on PCa risk [94] in a cohort study with 58,279 men in the Netherlands [95] and a case�control study in Italy and Switzerland [96]. In fact, one study of a cohort of men undergoing radical prostatectomy at several Veterans Administration facilities across the US even showed that higher serum folate levels were associated with lower PSA and, thus, lower risk for biochemical failure [97]. Another study using data from the 2007 to 2010 National Health and Nutrition Examination Survey showed that a higher folate status may be protective against elevated PSA levels among 3,293 men, 40-years old and older, without diagnosed PCa [98]. It was suggested that folate may play a dual role in prostate carcinogenesis and, thus, the complex relationship between folate and PCa awaits further investigation [99].

Despite the potential role of vitamin C (ascorbic acid) as an antioxidant in anticancer therapy, trials examining dietary intake or supplementation of vitamin C are few. A RCT showed no effect of vitamin C intake on PCa risk [89]. Furthermore, vitamin C at high doses may act more as a pro-oxidant than antioxidant, complicating the research design and interpretation.

The primary active form of vitamin D, 1,25 dihydroxyvitamin D3 (calcitriol) aids in proper bone formation, induces differentiation of some immune cells, and inhibits pro-tumor pathways, such as proliferation and angiogenesis, and has been suggested to benefit PCa risk [100]; however, findings continue to be inconclusive. More recent studies found that increased serum vitamin D levels were associated with decreased PCa risk [101,102]. Further, supplementing vitamin D may slow PCa progression or induce apoptosis in PCa cells [103-105]. Other studies, however, reported either no impact of vitamin D supplement on PSA [106] or no effect of vitamin D status on PCa risk [107,108]. Some studies contrarily reported that a lower vitamin D status was associated with a lower PCa risk in older men [109], or a higher serum vitamin D was associated with a higher PCa risk [110,111]. A study even suggested that a �U� shaped relationship may exist between vitamin D status and PCa and the optimal range of circulating vitamin D for PCa prevention may be narrow [112]. This is consistent with the findings for other nutrients that a greater intake of a favorable nutrient may not always be better.

A recent study showed that the association between vitamin D and PCa was modulated by vitamin D-binding protein [113] which may have partially explained the previous inconsistent findings. Further, a meta-analysis investigating the association between Vitamin D receptor (VDR) polymorphisms (BsmI and FokI) and PCa risk reported no relationship with PCa risk [114]. Thus, the role of vitamin D in PCa remains unclear.

In a large randomized trial with a total of 14,641 US male physicians ?50-years old, participants randomly received 400 IU of vitamin E every other day for an overall mean of 10.3 (13.8) years. Vitamin E supplementation had no immediate or long-term effects on the risk of total cancers or PCa [115]. However, a moderate dose of vitamin E supplement (50 mg or about 75 IU) resulted in lower PCa risk among 29,133 Finnish male smokers [116]. Multiple preclinical studies suggest vitamin E slows tumor growth, partly due to inhibiting DNA synthesis and inducing�apoptotic pathways [117]. Unfortunately, human studies have been less than supportive. Two observational studies (the Cancer Prevention Study II Nutrition Cohort and the NIH-AARP Diet and Health Study) both showed no association between vitamin E supplementation and PCa risk [118,119]. However, a higher serum ?-tocopherol but not the ?-tocopherol level was associated with decreased risk of PCa [120,121] and the association may be modified by genetic variations in vitamin E related genes [122]. On the contrary, a prospective randomized trial, the Selenium and Vitamin E Cancer Prevention Trial (SELECT), showed vitamin E supplementation significantly increased PCa risk [123] and that a higher plasma ?-tocopherol level may interact with selenium supplements to increase high grade PCa risk [124]. This finding is consistent with a case-cohort study of 1,739 cases and 3,117 controls that showed vitamin E increased PCa risk among those with low selenium status but not those with high selenium status [125]. Thus, more research is needed to examine the association between vitamin E and PCa and the dose effect and interaction with other nutrients should be considered.

Vitamin K has been hypothesized to help prevent PCa by reducing bioavailable calcium. Preclinical studies show the combination of vitamins C and K have potent antitumor activity in vitro and act as chemo- and radiosensitizers in vivo [126]. To date, few studies have investigated this, although one study using the European Prospective Investigation into Cancer and Nutrition (EPIC)-Heidelberg cohort found an inverse relationship between vitamin K (as menaquinones) intake and PCa incidence [127]. Little to no preclinical studies have been conducted to examine the role of calcium with PCa. Retrospective and meta-analyses suggest increased or reduced PCa risk with increased calcium intake, while others suggest no association [128,129]. Another study suggests a �U�-shaped association, where very low calcium levels or supplementation are both associated with PCa [130].

Selenium, on the other hand, has been hypothesized to prevent PCa. While in vitro studies suggested that selenium inhibited angiogenesis and proliferation while inducing apoptosis [131], results from SELECT showed no benefit of selenium alone or in combination with vitamin E for PCa chemoprevention [123]. Further, selenium supplementation did not benefit men with low selenium status but increased the risk of high-grade PCa among men with high selenium status in a randomly selected cohort of 1,739 cases with high-grade (Gleason 7�10) PCa and 3,117 controls [125]. A prospective Netherlands Cohort Study, which included 58,279 men, 55- to 69-years old, also showed that toenail selenium was associated with a reduced risk of advanced PCa [132]. Further research is needed to clarify the role of selenium with PCa.

Phytochemicals

Along with vitamins and minerals [2], plants contain phytochemicals with potential anti-cancer effects. Typically not considered essential compounds, phytochemicals have antioxidant and anti-inflammatory properties.

Silibinin is a polyphenolic flavonoid found in the seeds of milk thistle. It has been shown in vitro and in vivo to inhihit PCa growth by targeting epidermal growth factor receptor (EGFR), IGF-1 receptor (IGF-1R), and nuclear factor-kappa B (NF-kB) pathways [133,134]. A recent study showed that silibinin may be useful in PCa prevention by inhibiting TGF?2 expression and cancerassociated fibroblast (CAF)-like biomarkers in the human prostate stromal cells [135]. Thus, silibinin is a promising candidate as a PCa chemopreventive agent that awaits further research.

Curcumin is used as food additive in Asia and as an herbal medicine for inflammation [136]. In vitro, curcumin inhibits the pro-inflammatory protein NF-?B while inducing apoptosis through increased expression of proapoptotic genes [137]. In vivo, curcumin slows PCa growth in mice while sensitizing tumors to chemo- and radiotherapies [136]; however, no human trial has examined its impact on PCa.

Pomegranate

The peel and fruit of pomegranates and walnuts are rich in ellagitannins (punicalagins). These phytochemicals are readily metabolized to the active form ellagic acid by gut flora [138]. Preclinical experiments show ellagitannins inhibit PCa proliferation and angiogenesis under hypoxic conditions and induce apoptosis [137,138]. In prospective trials in men with a rising PSA after primary treatment, pomegranate juice or POMx, a commercially available pomegranate extract, increased the PSA doubling time relative to baseline [139,140], although no trials included a placebo group. Results are pending from a prospective placebo RCT using pomegranate extract in men with a rising PSA. However, in a placebo controlled trial, two pills of POMx daily for up to four weeks prior to radical prostatectomy had no impact on tumor pathology or oxidative stress or any other tumor measures [141].

Green Tea

Green tea contains a number of antioxidant polyphenols including catechins, such as epigallocatechin gallate (EGCG), epigallocatechin (EGC), (?)-epicatechin-3-gallate (ECG) and (?)-epicatechin. Preclinical studies suggest EGCG inhibits PCa growth, induces intrinsic and extrinsic apoptotic pathways and decreases inflammation by inhibiting NFkB [137]. Furthermore, the antioxidant properties of EGCG are 25 to 100 times more potent than vitamins C and E [131]. In a prospective randomized preprostatectomy trial, men consuming brewed green tea Lin et al. BMC Medicine (2015) 13:3 Page 7 of 15 prior to surgery had increased levels of green tea polyphenols in their prostate tissue [142]. In a small proof-ofprinciple trial with 60 men, daily supplementation of 600 mg green tea catechin extract reduced PCa incidence by 90% (3% versus 30% in the placebo group) [143]. Another small trial also showed that EGCG supplement resulted in a significant reduction in PSA, hepatocyte growth factor and vascular endothelial growth factor in men with PCa [144]. These studies suggest green tea polyphenols may lower PCa incidence and reduce PCa progression but more research is needed to confirm and clarify its mechanism [137,143,145].

Resveratrol

While most in vitro studies suggest resveratrol inhibits PCa growth [146-148], resveratrol suppresses tumor growth in some [137] but not all animal models [149], possibly due to limited bioavailability [150,151]. To date, there are no clinical trials investigating the preventive or therapeutic effects of resveratrol on PCa.

Zyflamend

Zyflamend is an anti-inflammatory mixture of herbs that has been shown to reduce PCa progression by lowering the expression of markers including pAKT, PSA, histone deacetylases and androgen receptor in animal models and PCa cell line [152-154]. Despite its anti-cancer potential [155], very few studies have been conducted in humans [156,157]. In an open-label Phase I trial of 23 patients with high-grade prostatic intraepithelial neoplasia, Zyflamend alone or in conjunction with other dietary supplements for 18 months reduced the risk for developing PCa [156]. More RCTs in humans are needed to confirm the efficacy and clinical application of this herbal supplement.

Other Whole Foods Fruits & Vegetables

Fruits and vegetables are rich sources of vitamins, minerals and phytochemicals. Several epidemiologic studies found inverse relationships between total fruit and vegetable intake [158], and cruciferous vegetable intake and PCa risk [159,160]. Allium vegetables, such as garlic, leeks, chives, and shallots, contain multiple sulfurous phytochemicals that were suggested to enhance the immune system, inhibit cell growth, modulate expression of androgen-responsive genes and induce apoptosis [161]. Although the number of published studies is limited, both preclinical and epidemiologic data suggest allium vegetable intake may be protective against PCa, particularly localized disease [162]. A randomized trial with 199 men also found that a blend supplement of pomegranate, green tea, broccoli and turmeric significantly reduced the rate of rise in PSA in men with PCa [163].

Tomatoes & Tomato Products

A number of studies have examined the association between tomatoes and tomato products with PCa but the findings are inconclusive. The antioxidant lycopene, which is rich in tomatoes, has also been studied specifically for its impact on PCa. In vitro, lycopene halts the cell cycle in several PCa cell lines and decreases IGF-1 signaling by inducing IGF-1 binding proteins [131]. While some animal studies found lycopene specifically slows PCa growth [164] or reduces PCa epithelial cells at stages of initiation, promotion and progression [165], two studies found conflicting findings between tomato paste and lycopene [166,167]. Prospective human studies found higher lycopene consumption [168,169] or higher serum levels were associated with lower PCa risk [170], but others have not [171,172]. Prostatic lycopene concentration below a 1 ng/mg threshold was associated with PCa at six-month follow-up biopsy (P = 0.003) [173]. Two short-term preprostatectomy trials using tomato sauce or lycopene supplementation demonstrated lycopene uptake in prostate tissue and antioxidant and potential anticancer effects [174,175]. While several clinical trials suggested an inverse relationship between lycopene supplementation, PSA levels and decreases in cancerrelated symptoms [171,176], no large-scale randomized trials have tested the role of lycopene or tomato products on PCa prevention or treatment.

Coffee

Coffee contains caffeine and several unidentified phenolic compounds that may serve as antioxidants. Epidemiological studies suggest an inverse relationship between coffee consumption and PCa risk, mainly for advanced or lethal stage disease, and the findings were independent of caffeine content [177,178]. Although several epidemiological studies [179-182] found no association between coffee consumption and PCa risk, a recent meta-analysis of prospective studies concluded that coffee consumption may reduce PCa risk [183]. The potential mechanism(s) and pathway(s) involved are unknown but may include antioxidant, anti-inflammatory effects, glucose and insulin metabolism, and potential impact on IGF-I and circulating sex hormones.

Dietary Patterns

Even though many single nutrients or food factors have been examined for their impact or association with PCa risk or progression, the results have largely been inconclusive. A potential reason for the inconsistency is the fact that the impact of single nutrient or food factor may be too small to be detected. In addition, nutrients naturally existing in foods often are highly correlated and may interact with each other and, thus, affect the impact on PCa. Thus, dietary pattern analysis has received an increasing Lin et al. BMC Medicine (2015) 13:3 Page 8 of 15 interest but research has been limited and the existing results have been inconclusive. In a cohort of 293,464 men, a high dietary quality, as indicated by the Healthy Eating Index (HEI) score, was associated with a lower risk of total PCa risk [70]. The Mediterranean diet, which is high in vegetables, olive oil, complex carbohydrates, lean meats and antioxidants, is consistently recommended to patients for prevention of cardiovascular disease and obesity [184], and may show promise in PCa prevention [185]. Fish and omega-3 fatty acid consumption in the Mediterranean pattern were significantly and inversely associated with fatal PCa risk. In addition, adherence to the Mediterranean diet after diagnosis of non-metastatic PCa was associated with lower overall mortality [186]. Whereas, a Western pattern with high intakes of red meats, processed meats, fried fish, chips, high-fat milk and white bread, was associated with a higher risk for PCa [187].

Furthermore, Asian countries with high consumption of omega-3 PUFAs, soy and green tea-based phytochemicals, have lower PCa incidences versus countries consuming a �Western-style� diet [188]. However, not all studies [189-191] supported an association between certain dietary pattern and risk of PCa. It is possible that the methodology used in identifying dietary patterns may not have captured all the dietary factors associated with PCa risk. Alternatively, each dietary pattern may contain both beneficial and harmful components resulting in an overall null association. More research is needed to continue searching for dietary patterns that combine most of the beneficial nutrients/food factors for PCa and limit most of the negative nutrients/ food factors.

Future Direction For Clinical Trials

Based on the multitude of epidemiologic, preclinical and clinical trials described in this review, dietary interventions for the prevention and treatment of PCa hold great promise. In addition, several dietary factors and vitamins/supplements may be associated with PCa risk and/ or progression of disease. Prospective randomized trials are clearly indicated to identify specific nutrients or combination therapies for the prevention and treatment of PCa.

Recently, active surveillance (AS) has emerged as a viable option for men with lower risk PCa. Men on AS are motivated to adhere to diet and lifestyle modifications [192], making this subset a good target for dietary intervention and quality of life trials [193]. PCa survivors who are more active and report �healthy� eating habits (that is, consuming low-fat, low-refined carbohydrate diets rich in fruits and vegetables) have better overall quality of life versus their inactive, unhealthy counterparts [194]. Thus, more randomized trials are warranted to determine the overall long-term effects of dietary intervention in this population. Specifically, key questions to address in future trials are: 1) Can dietary interventions delay the need for treatment in men on AS; 2) Can dietary interventions prevent recurrence for men after treatment; 3) Can dietary interventions delay progression among men with recurrent disease and, thus, delay the need for hormonal therapy; 4) Can dietary interventions reduce the side effects of PCa treatments including hormonal therapy and newer targeted therapies; and 5) Is there any role for dietary interventions alone or combined with targeted therapies in men on hormonal therapy to prevent castrate-resistance or after the emergence of castrate resistance disease? Because increasing evidence shows that metabolic abnormalities increase risk for PCa, lifestyle intervention that improves metabolic profile is a win-win option for PCa prevention and treatment [195,196].

Conclusions: Prostate Cancer

Future research is required to determine the ideal diet for PCa prevention or treatment. However, several dietary factors and some dietary patterns hold promise in reducing PCa risk or progression and are consistent with current dietary guidelines for Americans [197]. For counseling patients on diet for primary and secondary PCa prevention, many believe �heart healthy equals prostate healthy.� Thus, given the current inconclusive results, the best dietary advice for PCa prevention or management seems to include: increasing fruits and vegetables, replacing refined carbohydrates with whole grains, reducing total and saturated fat, reducing overcooked meats and consuming a moderate amount of calories or reducing carbohydrates with a primary goal of obtaining and maintaining a healthy body weight.

Competing interests The authors declare that they have no competing interests.

Authors� contributions P-HL and SF conducted the review, P-HL drafted the manuscript and SF and WA edited and provided critical input. All authors read and approved the final manuscript.

Acknowledgements Funding was provided by grants 1K24CA160653 (Freedland), NIH P50CA92131 (W. Aronson). This manuscript is the result of work supported with resources and the use of facilities at the Veterans Administration Medical Center, West Los Angeles (W. Aronson).

Author details 1 Department of Medicine, Division of Nephrology, Duke University Medical Center, Box 3487, Durham, NC 27710, USA. 2 Urology Section, Department of Surgery, Veterans Affairs Greater Los Angeles Healthcare System, Los Angeles, CA, USA. 3 Department of Urology, UCLA School of Medicine, Los Angeles, CA, USA. 4 Urology Section, Department of Surgery, Durham Veterans Affairs Medical Center, Division of Urology, Durham, NC, USA. 5 Duke Prostate Center, Departments of Surgery and Pathology, Duke University Medical Center, Durham, NC, USA.


blank
References:

1. Center MM, Jemal A, Lortet-Tieulent J, Ward E, Ferlay J, Brawley O, Bray F:
International variation in prostate cancer incidence and mortality rates.
Eur Urol 2012, 61:1079�1092.
2. Masko EM, Allott EH, Freedland SJ: The relationship between nutrition and
prostate cancer: is more always better? Eur Urol 2013, 63:810�820.
3. Mavropoulos JC, Isaacs WB, Pizzo SV, Freedland SJ: Is there a role for a
low-carbohydrate ketogenic diet in the management of prostate cancer?
Urology 2006, 68:15�18.
4. Freedland SJ, Mavropoulos J, Wang A, Darshan M, Demark-Wahnefried W,
Aronson WJ, Cohen P, Hwang D, Peterson B, Fields T, Pizzo SV, Isaacs WB:
Carbohydrate restriction, prostate cancer growth, and the insulin-like
growth factor axis. Prostate 2008, 68:11�19.
5. Mavropoulos JC: Buschemeyer WC 3rd, Tewari AK, Rokhfeld D, Pollak M,
Zhao Y, Febbo PG, Cohen P, Hwang D, Devi G, Demark-Wahnefried W,
Westman EC, Peterson BL, Pizzo SV, Freedland SJ: The effects of varying
dietary carbohydrate and fat content on survival in a murine LNCaP
prostate cancer xenograft model. Cancer Prev Res (Phila Pa) 2009,
2:557�565.
6. Masko EM, Thomas JA 2nd, Antonelli JA, Lloyd JC, Phillips TE, Poulton SH,
Dewhirst MW, Pizzo SV, Freedland SJ: Low-carbohydrate diets and
prostate cancer: how low is �low enough�? Cancer Prev Res (Phila) 2010,
3:1124�1131.
7. Drake I, Sonestedt E, Gullberg B, Ahlgren G, Bjartell A, Wallstrom P, Wirf�lt E:
Dietary intakes of carbohydrates in relation to prostate cancer risk: a
prospective study in the Malmo Diet and Cancer cohort. Am J Clin Nutr
2012, 96:1409�1418.
8. Zhang J, Shen C, Wang L, Ma Q, Xia P, Qi M, Yang M, Han B: Metformin
inhibits epithelial-mesenchymal transition in prostate cancer cells:
Involvement of the tumor suppressor miR30a and its target gene SOX4.
Biochem Biophys Res Commun 2014, 452:746�752.
9. Lee SY, Song CH, Xie YB, Jung C, Choi HS, Lee K: SMILE upregulated by
metformin inhibits the function of androgen receptor in prostate cancer
cells. Cancer Lett 2014, 354:390�397.
10. Demir U, Koehler A, Schneider R, Schweiger S, Klocker H: Metformin antitumor
effect via disruption of the MID1 translational regulator complex
and AR downregulation in prostate cancer cells. BMC Cancer 2014, 14:52.
11. Margel D: Metformin to prevent prostate cancer: a call to unite. Eur Urol
2014. doi:10.1016/j.eururo.2014.05.012. [Epub ahead of time]
12. Margel D, Urbach DR, Lipscombe LL, Bell CM, Kulkarni G, Austin PC, Fleshner
N: Metformin use and all-cause and prostate cancer-specific mortality
among men with diabetes. J Clin Oncol 2013, 31:3069�3075.
13. Tseng CH: Metformin significantly reduces incident prostate cancer risk
in Taiwanese men with type 2 diabetes mellitus. Eur J Cancer 2014,
50:2831�2837.
14. Joshua AM, Zannella VE, Downes MR, Bowes B, Hersey K, Koritzinsky M,
Schwab M, Hofmann U, Evans A, van der Kwast T, Trachtenberg J, Finelli A,
Fleshner N, Sweet J, Pollak M: A pilot �window of opportunity�
neoadjuvant study of metformin in localised prostate cancer. Prostate
Cancer Prostatic Dis 2014, 17:252�258.
15. Rothermundt C, Hayoz S, Templeton AJ, Winterhalder R, Strebel RT, Bartschi
D, Pollak M, Lui L, Endt K, Schiess R, R�schoff JH, Cathomas R, Gillessen S:
Metformin in Chemotherapy-naive Castration-resistant Prostate Cancer:
A Multicenter Phase 2 Trial (SAKK 08/09). Eur Urol 2014, 66:468�474.
16. Allott EH, Abern MR, Gerber L, Keto CJ, Aronson WJ, Terris MK, Kane CJ,
Amling CL, Cooperberg MR, Moorman PG, Freedland SJ: Metformin does
not affect risk of biochemical recurrence following radical
prostatectomy: results from the SEARCH database. Prostate Cancer
Prostatic Dis 2013, 16:391�397.
17. Rieken M, Kluth LA, Xylinas E, Fajkovic H, Becker A, Karakiewicz PI, Herman
M, Lotan Y, Seitz C, Schramek P, Remzi M, Loidl W, Pummer K, Lee RK,
Faison T, Scherr DS, Kautzky-Willer A, Bachmann A, Tewari A, Shariat SF:
Association of diabetes mellitus and metformin use with biochemical
recurrence in patients treated with radical prostatectomy for prostate
cancer. World J Urol 2014, 32:999�1005.
18. Margel D, Urbach D, Lipscombe LL, Bell CM, Kulkarni G, Austin PC, Fleshner
N: Association between metformin use and risk of prostate cancer and
its grade. J Natl Cancer Inst 2013, 105:1123�1131.
19. Franciosi M, Lucisano G, Lapice E, Strippoli GF, Pellegrini F, Nicolucci A:
Metformin therapy and risk of cancer in patients with type 2 diabetes:
systematic review. PLoS One 2013, 8:e71583.
20. Kaushik D, Karnes RJ, Eisenberg MS, Rangel LJ, Carlson RE, Bergstralh EJ:
Effect of metformin on prostate cancer outcomes after radical
prostatectomy. Urol Oncol 2014, 32:43 e41�47.
21. Bensimon L, Yin H, Suissa S, Pollak MN, Azoulay L: The use of metformin in
patients with prostate cancer and the risk of death. Cancer Epidemiol
Biomarkers Prev 2014, 23:2111�2118.
22. Tsilidis KK, Capothanassi D, Allen NE, Rizos EC, Lopez DS, van Veldhoven K,
Sacerdote C, Ashby D, Vineis P, Tzoulaki I, Ioannidis JP: Metformin does not
affect cancer risk: a cohort study in the U.K. Clinical Practice Research
Datalink analyzed like an intention-to-treat trial. Diabetes Care 2014,
37:2522�2532.
23. Levine ME, Suarez JA, Brandhorst S, Balasubramanian P, Cheng CW, Madia F,
Fontana L, Mirisola MG, Guevara-Aguirre J, Wan J, Passarino G, Kennedy BK,
Wei M, Cohen P, Crimmins EM, Longo VD: Low protein intake is associated
with a major reduction in IGF-1, cancer, and overall mortality in the 65
and younger but not older population. Cell Metab 2014, 19:407�417.
24. Solon-Biet SM, McMahon AC, Ballard JW, Ruohonen K, Wu LE, Cogger VC,
Warren A, Huang X, Pichaud N, Melvin RG, Gokarn R, Khalil M, Turner N,
Cooney GJ, Sinclair DA, Raubenheimer D, Le Couteur DG, Simpson SJ: The
ratio of macronutrients, not caloric intake, dictates cardiometabolic
health, aging, and longevity in ad libitum-fed mice. Cell Metab 2014,
19:418�430.
25. Richman EL, Stampfer MJ, Paciorek A, Broering JM, Carroll PR, Chan JM:
Intakes of meat, fish, poultry, and eggs and risk of prostate cancer
progression. Am J Clin Nutr 2010, 91:712�721.
26. Joshi AD, John EM, Koo J, Ingles SA, Stern MC: Fish intake, cooking
practices, and risk of prostate cancer: results from a multi-ethnic
case�control study. Cancer Causes Control 2012, 23:405�420.
27. Joshi AD, Corral R, Catsburg C, Lewinger JP, Koo J, John EM, Ingles SA,
Stern MC: Red meat and poultry, cooking practices, genetic susceptibility
and risk of prostate cancer: results from a multiethnic case�control
study. Carcinogenesis 2012, 33:2108�2118.
28. Catsburg C, Joshi AD, Corral R, Lewinger JP, Koo J, John EM, Ingles SA,
Stern MC: Polymorphisms in carcinogen metabolism enzymes, fish
intake, and risk of prostate cancer. Carcinogenesis 2012, 33:1352�1359.
29. Pettersson A, Kasperzyk JL, Kenfield SA, Richman EL, Chan JM, Willett WC,
Stampfer MJ, Mucci LA, Giovannucci EL: Milk and dairy consumption
among men with prostate cancer and risk of metastases and prostate
cancer death. Cancer Epidemiol Biomarkers Prev 2012, 21:428�436.
30. Deneo-Pellegrini H, Ronco AL, De Stefani E, Boffetta P, Correa P,
Mendilaharsu M, Acosta G: Food groups and risk of prostate cancer: a
case�control study in Uruguay. Cancer Causes Control 2012, 23:1031�1038.
31. Park SY, Murphy SP, Wilkens LR, Stram DO, Henderson BE, Kolonel LN:
Calcium, vitamin D, and dairy product intake and prostate cancer risk:
the Multiethnic Cohort Study. Am J Epidemiol 2007, 166:1259�1269.
32. Song Y, Chavarro JE, Cao Y, Qiu W, Mucci L, Sesso HD, Stampfer MJ,
Giovannucci E, Pollak M, Liu S, Ma J: Whole milk intake is associated with
prostate cancer-specific mortality among U.S. male physicians. J Nutr Feb
2013, 143:189�196.
33. Young NJ, Metcalfe C, Gunnell D, Rowlands MA, Lane JA, Gilbert R, Avery
KN, Davis M, Neal DE, Hamdy FC, Donovan J, Martin RM, Holly JM: A crosssectional
analysis of the association between diet and insulin-like growth
factor (IGF)-I, IGF-II, IGF-binding protein (IGFBP)-2, and IGFBP-3 in men in
the United Kingdom. Cancer Causes Control 2012, 23:907�917.
34. Christensen MJ, Quiner TE, Nakken HL, Lephart ED, Eggett DL, Urie PM:
Combination effects of dietary soy and methylselenocysteine in a mouse
model of prostate cancer. Prostate 2013, 73:986�995.
35. Bosland MC, Kato I, Zeleniuch-Jacquotte A, Schmoll J, Enk Rueter E,
Melamed J, Kong MX, Macias V, Kajdacsy-Balla A, Lumey LH, Xie H, Gao W,
Walden P, Lepor H, Taneja SS, Randolph C, Schlicht MJ, Meserve-Watanabe
H, Deaton RJ, Davies JA: Effect of soy protein isolate supplementation on
biochemical recurrence of prostate cancer after radical prostatectomy: a
randomized trial. JAMA 2013, 310:170�178.
36. Chiyomaru T, Yamamura S, Fukuhara S, Yoshino H, Kinoshita T, Majid S, Saini
S, Chang I, Tanaka Y, Enokida H, Seki N, Nakagawa M, Dahiya R: Genistein
inhibits prostate cancer cell growth by targeting miR-34a and oncogenic
HOTAIR. PLoS One 2013, 8:e70372.
37. Zhang S, Wang Y, Chen Z, Kim S, Iqbal S, Chi A, Ritenour C, Wang YA, Kucuk
O, Wu D: Genistein enhances the efficacy of cabazitaxel chemotherapy
in metastatic castration-resistant prostate cancer cells. Prostate 2013,
73:1681�1689.38. van Die MD, Bone KM, Williams SG, Pirotta MV: Soy and soy isoflavones in
prostate cancer: a systematic review and meta-analysis of randomized
controlled trials. BJU Int 2014, 113:E119�E130.
39. Hamilton-Reeves JM, Banerjee S, Banerjee SK, Holzbeierlein JM, Thrasher JB,
Kambhampati S, Keighley J, Van Veldhuizen P: Short-term soy isoflavone
intervention in patients with localized prostate cancer: a randomized,
double-blind, placebo-controlled trial. PLoS One 2013, 8:e68331.
40. Pavese JM, Krishna SN, Bergan RC: Genistein inhibits human prostate
cancer cell detachment, invasion, and metastasis. Am J Clin Nutr 2014,
100:431S�436S.
41. Gonzalez-Menendez P, Hevia D, Rodriguez-Garcia A, Mayo JC, Sainz RM:
Regulation of GLUT transporters by flavonoids in androgen-sensitive and
-insensitive prostate cancer cells. Endocrinology 2014, 155:3238�3250.
42. Hirata H, Hinoda Y, Shahryari V, Deng G, Tanaka Y, Tabatabai ZL, Dahiya R:
Genistein downregulates onco-miR-1260b and upregulates sFRP1 and
Smad4 via demethylation and histone modification in prostate cancer
cells. Br J Cancer 2014, 110:1645�1654.
43. Handayani R, Rice L, Cui Y, Medrano TA, Samedi VG, Baker HV, Szabo NJ,
Shiverick KT: Soy isoflavones alter expression of genes associated with
cancer progression, including interleukin-8, in androgen-independent
PC-3 human prostate cancer cells. J Nutr 2006, 136:75�82.
44. Travis RC, Allen NE, Appleby PN, Price A, Kaaks R, Chang-Claude J, Boeing H,
Aleksandrova K, Tj�nneland A, Johnsen NF, Overvad K, Ram�n Quir�s J,
Gonz�lez CA, Molina-Montes E, S�nchez MJ, Larra�aga N, Casta�o JM,
Ardanaz E, Khaw KT, Wareham N, Trichopoulou A, Karapetyan T, Rafnsson
SB, Palli D, Krogh V, Tumino R, Vineis P, Bueno-de-Mesquita HB, Stattin P,
Johansson M, et al: Prediagnostic concentrations of plasma genistein and
prostate cancer risk in 1,605 men with prostate cancer and 1,697
matched control participants in EPIC. Cancer Causes Control 2012,
23:1163�1171.
45. Jackson MD, McFarlane-Anderson ND, Simon GA, Bennett FI, Walker SP:
Urinary phytoestrogens and risk of prostate cancer in Jamaican men.
Cancer Causes Control 2010, 21:2249�2257.
46. Lazarevic B, Hammarstr�m C, Yang J, Ramberg H, Diep LM, Karlsen SJ,
Kucuk O, Saatcioglu F, Task�n KA, Svindland A: The effects of short-term
genistein intervention on prostate biomarker expression in patients with
localised prostate cancer before radical prostatectomy. Br J Nutr 2012,
108:2138�2147.
47. Epstein MM, Kasperzyk JL, Mucci LA, Giovannucci E, Price A, Wolk A,
H�kansson N, Fall K, Andersson SO, Andr�n O: Dietary fatty acid intake and
prostate cancer survival in Orebro County, Sweden. Am J Epidemiol 2012,
176:240�252.
48. Kobayashi N, Barnard RJ, Said J, Hong-Gonzalez J, Corman DM, Ku M,
Doan NB, Gui D, Elashoff D, Cohen P, Aronson WJ: Effect of low-fat diet on
development of prostate cancer and Akt phosphorylation in the Hi-Myc
transgenic mouse model. Cancer Res 2008, 68:3066�3073.
49. Ngo TH, Barnard RJ, Cohen P, Freedland S, Tran C, deGregorio F, Elshimali
YI, Heber D, Aronson WJ: Effect of isocaloric low-fat diet on human
LAPC-4 prostate cancer xenografts in severe combined immunodeficient
mice and the insulin-like growth factor axis. Clin Cancer Res 2003,
9:2734�2743.
50. Huang M, Narita S, Numakura K, Tsuruta H, Saito M, Inoue T, Horikawa Y,
Tsuchiya N, Habuchi T: A high-fat diet enhances proliferation of
prostate cancer cells and activates MCP-1/CCR2 signaling. Prostate 2012,
72:1779�1788.
51. Chang SN, Han J, Abdelkader TS, Kim TH, Lee JM, Song J, Kim KS, Park JH,
Park JH: High animal fat intake enhances prostate cancer progression
and reduces glutathione peroxidase 3 expression in early stages of
TRAMP mice. Prostate 2014, 74:1266�1277.
52. Bidoli E, Talamini R, Bosetti C, Negri E, Maruzzi D, Montella M, Franceschi S,
La Vecchia C: Macronutrients, fatty acids, cholesterol and prostate cancer
risk. Ann Oncol 2005, 16:152�157.
53. Park SY, Murphy SP, Wilkens LR, Henderson BE, Kolonel LN: Fat and meat
intake and prostate cancer risk: the multiethnic cohort study. Int J Cancer
2007, 121:1339�1345.
54. Wallstrom P, Bjartell A, Gullberg B, Olsson H, Wirfalt E: A prospective study
on dietary fat and incidence of prostate cancer (Malmo, Sweden).
Cancer Causes Control 2007, 18:1107�1121.
55. Crowe FL, Key TJ, Appleby PN, Travis RC, Overvad K, Jakobsen MU,
Johnsen NF, Tj�nneland A, Linseisen J, Rohrmann S, Boeing H, Pischon T,
Trichopoulou A, Lagiou P, Trichopoulos D, Sacerdote C, Palli D, Tumino R,
Krogh V, Bueno-de-Mesquita HB, Kiemeney LA, Chirlaque MD, Ardanaz E,
S�nchez MJ, Larra�aga N, Gonz�lez CA, Quir�s JR, Manjer J, Wirf�lt E, Stattin
P, et al: Dietary fat intake and risk of prostate cancer in the European
Prospective Investigation into Cancer and Nutrition. Am J Clin Nutr 2008,
87:1405�1413.
56. Ohwaki K, Endo F, Kachi Y, Hattori K, Muraishi O, Nishikitani M, Yano E:
Relationship between dietary factors and prostate-specific antigen in
healthy men. Urol Int 2012, 89:270�274.
57. Bassett JK, Severi G, Hodge AM, MacInnis RJ, Gibson RA, Hopper JL,
English DR, Giles GG: Plasma phospholipid fatty acids, dietary fatty acids
and prostate cancer risk. Int J Cancer 2013, 133:1882�1891.
58. Richman EL, Kenfield SA, Chavarro JE, Stampfer MJ, Giovannucci EL, Willett
WC, Chan JM: Fat intake after diagnosis and risk of lethal prostate cancer
and all-cause mortality. JAMA Intern Med 2013, 173:1318�1326.
59. Williams CD, Whitley BM, Hoyo C, Grant DJ, Iraggi JD, Newman KA, Gerber
L, Taylor LA, McKeever MG, Freedland SJ: A high ratio of dietary n-6/n-3
polyunsaturated fatty acids is associated with increased risk of prostate
cancer. Nutr Res 2011, 31:1�8.
60. Chua ME, Sio MC, Sorongon MC, Dy JS: Relationship of dietary intake of
omega-3 and omega-6 fatty acids with risk of prostate cancer
development: a meta-analysis of prospective studies and review of
literature. Prostate Cancer 2012, 2012:826254.
61. Berquin IM, Edwards IJ, Kridel SJ, Chen YQ: Polyunsaturated fatty acid
metabolism in prostate cancer. Cancer Metastasis Rev 2011, 30:295�309.
62. Aronson WJ, Kobayashi N, Barnard RJ, Henning S, Huang M, Jardack PM, Liu
B, Gray A, Wan J, Konijeti R, Freedland SJ, Castor B, Heber D, Elashoff D, Said
J, Cohen P, Galet C: Phase II prospective randomized trial of a low-fat diet
with fish oil supplementation in men undergoing radical prostatectomy.
Cancer Prev Res (Phila) 2011, 4:2062�2071.
63. Hughes-Fulford M, Li CF, Boonyaratanakornkit J, Sayyah S: Arachidonic acid
activates phosphatidylinositol 3-kinase signaling and induces gene
expression in prostate cancer. Cancer Res 2006, 66:1427�1433.
64. Moreel X, Allaire J, Leger C, Caron A, Labonte ME, Lamarche B, Julien P,
Desmeules P, T�tu B, Fradet V: Prostatic and dietary omega-3 fatty acids
and prostate cancer progression during active surveillance. Cancer Prev
Res (Phila) 2014, 7:766�776.
65. Spencer L, Mann C, Metcalfe M, Webb M, Pollard C, Spencer D, Berry D,
Steward W, Dennison A: The effect of omega-3 FAs on tumour angiogenesis
and their therapeutic potential. Eur J Cancer 2009, 45:2077�2086.
66. Gu Z, Suburu J, Chen H, Chen YQ: Mechanisms of omega-3 polyunsaturated
fatty acids in prostate cancer prevention. Biomed Res Int 2013, 2013:824563.
67. Lloyd JC, Masko EM, Wu C, Keenan MM, Pilla DM, Aronson WJ, Chi JT,
Freedland SJ: Fish oil slows prostate cancer xenograft growth relative to
other dietary fats and is associated with decreased mitochondrial and
insulin pathway gene expression. Prostate Cancer Prostatic Dis 2013,
16:285�291.
68. Williams CM, Burdge G: Long-chain n-3 PUFA: plant v. marine sources.
Proc Nutr Soc 2006, 65:42�50.
69. Galet C, Gollapudi K, Stepanian S, Byrd JB, Henning SM, Grogan T, Elashoff
D, Heber D, Said J, Cohen P, Aronson WJ: Effect of a low-fat fish oil diet
on proinflammatory eicosanoids and cell-cycle progression score in
men undergoing radical prostatectomy. Cancer Prev Res (Phila) 2014,
7:97�104.
70. Bosire C, Stampfer MJ, Subar AF, Park Y, Kirkpatrick SI, Chiuve SE, Hollenbeck
AR, Reedy J: Index-based dietary patterns and the risk of prostate cancer
in the NIH-AARP diet and health study. Am J Epidemiol 2013, 177:504�513.
71. Aronson WJ, Barnard RJ, Freedland SJ, Henning S, Elashoff D, Jardack PM,
Cohen P, Heber D, Kobayashi N: Growth inhibitory effect of low fat diet
on prostate cancer cells: results of a prospective, randomized dietary
intervention trial in men with prostate cancer. J Urol 2010, 183:345�350.
72. Brouwer IA, Geleijnse JM, Klaasen VM, Smit LA, Giltay EJ, de Goede J,
Heijboer AC, Kromhout D, Katan MB: Effect of alpha linolenic acid
supplementation on serum prostate specific antigen (PSA): results from
the alpha omega trial. PLoS One 2013, 8:e81519.
73. Chua ME, Sio MC, Sorongon MC, Morales ML Jr: The relevance of serum
levels of long chain omega-3 polyunsaturated fatty acids and prostate
cancer risk: A meta-analysis. Can Urol Assoc J 2013, 7:E333�E343.
74. Yue S, Li J, Lee SY, Lee HJ, Shao T, Song B, Cheng L, Masterson TA, Liu X,
Ratliff TL, Cheng JX: Cholesteryl ester accumulation induced by PTEN loss
and PI3K/AKT activation underlies human prostate cancer
aggressiveness. Cell Metab 2014, 19:393�406.

75. Sun Y, Sukumaran P, Varma A, Derry S, Sahmoun AE, Singh BB: Cholesterolinduced
activation of TRPM7 regulates cell proliferation, migration,
and viability of human prostate cells. Biochim Biophys Acta 1843,
2014:1839�1850.
76. Murai T: Cholesterol lowering: role in cancer prevention and treatment.
Biol Chem 2014. doi:10.1515/hsz-2014-0194. [Epub ahead of time]
77. Zhuang L, Kim J, Adam RM, Solomon KR, Freeman MR: Cholesterol
targeting alters lipid raft composition and cell survival in prostate cancer
cells and xenografts. J Clin Invest 2005, 115:959�968.
78. Mostaghel EA, Solomon KR, Pelton K, Freeman MR, Montgomery RB:
Impact of circulating cholesterol levels on growth and intratumoral
androgen concentration of prostate tumors. PLoS One 2012,
7:e30062.
79. Morote J, Celma A, Planas J, Placer J, de Torres I, Olivan M, Carles J,
Revent�s J, Doll A: Role of serum cholesterol and statin use in the risk of
prostate cancer detection and tumor aggressiveness. Int J Mol Sci 2014,
15:13615�13623.
80. Allott EH, Howard LE, Cooperberg MR, Kane CJ, Aronson WJ, Terris MK,
Amling CL, Freedland SJ: Postoperative statin use and risk of biochemical
recurrence following radical prostatectomy: results from the Shared
Equal Access Regional Cancer Hospital (SEARCH) database. BJU Int 2014,
114:661�666.
81. Jespersen CG, Norgaard M, Friis S, Skriver C, Borre M: Statin use and risk of
prostate cancer: A Danish population-based case�control study,
1997�2010. Cancer Epidemiol 2014, 38:42�47.
82. Meyers CD, Kashyap ML: Pharmacologic elevation of high-density
lipoproteins: recent insights on mechanism of action and atherosclerosis
protection. Curr Opin Cardiol 2004, 19:366�373.
83. Xia P, Vadas MA, Rye KA, Barter PJ, Gamble JR: High density lipoproteins
(HDL) interrupt the sphingosine kinase signaling pathway. A possible
mechanism for protection against atherosclerosis by HDL. J Biol Chem
1999, 274:33143�33147.
84. Kotani K, Sekine Y, Ishikawa S, Ikpot IZ, Suzuki K, Remaley AT: High-density
lipoprotein and prostate cancer: an overview. J Epidemiol 2013,
23:313�319.
85. Soni MG, Thurmond TS, Miller ER 3rd, Spriggs T, Bendich A, Omaye ST:
Safety of vitamins and minerals: controversies and perspective. Toxicol
Sci 2010, 118:348�355.
86. Neuhouser ML, Barnett MJ, Kristal AR, Ambrosone CB, King I, Thornquist M,
Goodman G: (n-6) PUFA increase and dairy foods decrease prostate
cancer risk in heavy smokers. J Nutr 2007, 137:1821�1827.
87. Karppi J, Kurl S, Laukkanen JA, Kauhanen J: Serum beta-carotene in relation
to risk of prostate cancer: the Kuopio Ischaemic Heart Disease Risk
Factor study. Nutr Cancer 2012, 64:361�367.
88. Margalit DN, Kasperzyk JL, Martin NE, Sesso HD, Gaziano JM, Ma J, Stampfer
MJ, Mucci LA: Beta-carotene antioxidant use during radiation therapy
and prostate cancer outcome in the Physicians� Health Study. Int J Radiat
Oncol Biol Phys 2012, 83:28�32.
89. Roswall N, Larsen SB, Friis S, Outzen M, Olsen A, Christensen J, Dragsted LO,
Tj�nneland A: Micronutrient intake and risk of prostate cancer in a
cohort of middle-aged, Danish men. Cancer Causes Control 2013,
24:1129�1135.
90. Gilbert R, Metcalfe C, Fraser WD, Donovan J, Hamdy F, Neal DE, Lane JA,
Martin RM: Associations of circulating retinol, vitamin E, and 1,25-
dihydroxyvitamin D with prostate cancer diagnosis, stage, and grade.
Cancer Causes Control 2012, 23:1865�1873.
91. Bistulfi G, Foster BA, Karasik E, Gillard B, Miecznikowski J, Dhiman VK,
Smiraglia DJ: Dietary folate deficiency blocks prostate cancer progression
in the TRAMP model. Cancer Prev Res (Phila) 2011, 4:1825�1834.
92. Collin SM: Folate and B12 in prostate cancer. Adv Clin Chem 2013,
60:1�63.
93. Tio M, Andrici J, Cox MR, Eslick GD: Folate intake and the risk of prostate
cancer: a systematic review and meta-analysis. Prostate Cancer Prostatic
Dis 2014, 17:213�219.
94. Vollset SE, Clarke R, Lewington S, Ebbing M, Halsey J, Lonn E, Armitage J,
Manson JE, Hankey GJ, Spence JD, Galan P, B�naa KH, Jamison R, Gaziano
JM, Guarino P, Baron JA, Logan RF, Giovannucci EL, den Heijer M, Ueland
PM, Bennett D, Collins R, Peto R, B-Vitamin Treatment Trialists' Collaboration:
Effects of folic acid supplementation on overall and site-specific cancer
incidence during the randomised trials: meta-analyses of data on 50,000
individuals. Lancet 2013, 381:1029�1036.
95. Verhage BA, Cremers P, Schouten LJ, Goldbohm RA, van den Brandt PA:
Dietary folate and folate vitamers and the risk of prostate cancer
in The Netherlands Cohort Study. Cancer Causes Control 2012,
23:2003�2011.
96. Tavani A, Malerba S, Pelucchi C, Dal Maso L, Zucchetto A, Serraino D, Levi F,
Montella M, Franceschi S, Zambon A, La Vecchia C: Dietary folates and
cancer risk in a network of case�control studies. Ann Oncol 2012,
23:2737�2742.
97. Moreira DM, Banez LL, Presti JC Jr, Aronson WJ, Terris MK, Kane CJ, Amling
CL, Freedland SJ: High serum folate is associated with reduced
biochemical recurrence after radical prostatectomy: results from the
SEARCH Database. Int Braz J Urol 2013, 39:312�318. discussion 319.
98. Han YY, Song JY, Talbott EO: Serum folate and prostate-specific antigen in
the United States. Cancer Causes Control 2013, 24:1595�1604.
99. Rycyna KJ, Bacich DJ, O'Keefe DS: Opposing roles of folate in prostate
cancer. Urology 2013, 82:1197�1203.
100. Gilbert R, Martin RM, Beynon R, Harris R, Savovic J, Zuccolo L, Bekkering GE,
Fraser WD, Sterne JA, Metcalfe: Associations of circulating and dietary
vitamin D with prostate cancer risk: a systematic review and dose�
response meta-analysis. Cancer Causes Control 2011, 22:319�340.
101. Schenk JM, Till CA, Tangen CM, Goodman PJ, Song X, Torkko KC, Kristal AR,
Peters U, Neuhouser ML: Serum 25-hydroxyvitamin d concentrations and
risk of prostate cancer: results from the Prostate Cancer Prevention Trial.
Cancer Epidemiol Biomarkers Prev 2014, 23:1484�1493.
102. Schwartz GG: Vitamin D, in blood and risk of prostate cancer: lessons
from the Selenium and Vitamin E Cancer Prevention Trial and the
Prostate Cancer Prevention Trial. Cancer Epidemiol Biomarkers Prev 2014,
23:1447�1449.
103. Giangreco AA, Vaishnav A, Wagner D, Finelli A, Fleshner N, Van der Kwast T,
Vieth R, Nonn L: Tumor suppressor microRNAs, miR-100 and -125b, are
regulated by 1,25-dihydroxyvitamin D in primary prostate cells and in
patient tissue. Cancer Prev Res (Phila) 2013, 6:483�494.
104. Hollis BW, Marshall DT, Savage SJ, Garrett-Mayer E, Kindy MS, Gattoni-Celli S:
Vitamin D3 supplementation, low-risk prostate cancer, and health
disparities. J Steroid Biochem Mol Biol 2013, 136:233�237.
105. Sha J, Pan J, Ping P, Xuan H, Li D, Bo J, Liu D, Huang Y: Synergistic effect
and mechanism of vitamin A and vitamin D on inducing apoptosis of
prostate cancer cells. Mol Biol Rep 2013, 40:2763�2768.
106. Chandler PD, Giovannucci EL, Scott JB, Bennett GG, Ng K, Chan AT, Hollis
BW, Emmons KM, Fuchs CS, Drake BF: Null association between Vitamin D
and PSA levels among black men in a Vitamin D supplementation trial.
Cancer Epidemiol Biomarkers Prev 2014, 23:1944�1947.
107. Skaaby T, Husemoen LL, Thuesen BH, Pisinger C, Jorgensen T, Roswall N,
Larsen SC, Linneberg A: Prospective population-based study of the
association between serum 25-hydroxyvitamin-D levels and the
incidence of specific types of cancer. Cancer Epidemiol Biomarkers Prev
2014, 23:1220�1229.
108. Holt SK, Kolb S, Fu R, Horst R, Feng Z, Stanford JL: Circulating levels of
25-hydroxyvitamin D and prostate cancer prognosis. Cancer Epidemiol
2013, 37:666�670.
109. Wong YY, Hyde Z, McCaul KA, Yeap BB, Golledge J, Hankey GJ, Flicker L:
In older men, lower plasma 25-hydroxyvitamin D is associated with
reduced incidence of prostate, but not colorectal or lung cancer.
PLoS One 2014, 9:e99954.
110. Xu Y, Shao X, Yao Y, Xu L, Chang L, Jiang Z, Lin Z: Positive association
between circulating 25-hydroxyvitamin D levels and prostate cancer risk:
new findings from an updated meta-analysis. J Cancer Res Clin Oncol
2014, 140:1465�1477.
111. Meyer HE, Robsahm TE, Bjorge T, Brustad M, Blomhoff R: Vitamin D, season,
and risk of prostate cancer: a nested case�control study within
Norwegian health studies. Am J Clin Nutr 2013, 97:147�154.
112. Kristal AR, Till C, Song X, Tangen CM, Goodman PJ, Neuhauser ML, Schenk
JM, Thompson IM, Meyskens FL Jr, Goodman GE, Minasian LM, Parnes HL,
Klein EA: Plasma vitamin D and prostate cancer risk: results from the
Selenium and Vitamin E Cancer Prevention Trial. Cancer Epidemiol
Biomarkers Prev 2014, 23:1494�1504.
113. Weinstein SJ, Mondul AM, Kopp W, Rager H, Virtamo J, Albanes D:
Circulating 25-hydroxyvitamin D, vitamin D-binding protein and risk of
prostate cancer. Int J Cancer 2013, 132:2940�2947.
114. Guo Z, Wen J, Kan Q, Huang S, Liu X, Sun N, Li Z: Lack of association
between vitamin D receptor gene FokI and BsmI polymorphisms and�prostate cancer risk: an updated meta-analysis involving 21,756 subjects. Tumour Biol 2013, 34:3189�3200115. Wang L, Sesso HD, Glynn RJ, Christen WG, Bubes V, Manson JE, Buring JE,
Gaziano JM: Vitamin E and C supplementation and risk of cancer in men:
posttrial follow-up in the Physicians� Health Study II randomized trial.
Am J Clin Nutr 2014, 100:915�923.
116. Virtamo J, Taylor PR, Kontto J, Mannisto S, Utriainen M, Weinstein SJ,
Huttunen J, Albanes D: Effects of alpha-tocopherol and beta-carotene
supplementation on cancer incidence and mortality: 18-year
postintervention follow-up of the Alpha-tocopherol, Beta-carotene
Cancer Prevention Study. Int J Cancer 2014, 135:178�185.
117. Basu A, Imrhan V: Vitamin E and prostate cancer: is vitamin E succinate a
superior chemopreventive agent? Nutr Rev 2005, 63:247�251.
118. Lawson KA, Wright ME, Subar A, Mouw T, Hollenbeck A, Schatzkin A,
Leitzmann MF: Multivitamin use and risk of prostate cancer in the
National Institutes of Health-AARP Diet and Health Study. J Natl Cancer
Inst 2007, 99:754�764.
119. Calle EE, Rodriguez C, Jacobs EJ, Almon ML, Chao A, McCullough ML,
Feigelson HS, Thun MJ: The American Cancer Society Cancer Prevention
Study II Nutrition Cohort: rationale, study design, and baseline
characteristics. Cancer 2002, 94:2490�2501.
120. Weinstein SJ, Peters U, Ahn J, Friesen MD, Riboli E, Hayes RB, Albanes D:
Serum alpha-tocopherol and gamma-tocopherol concentrations and
prostate cancer risk in the PLCO Screening Trial: a nested case�control
study. PLoS One 2012, 7:e40204.
121. Cui R, Liu ZQ, Xu Q: Blood alpha-tocopherol, gamma-tocopherol levels
and risk of prostate cancer: a meta-analysis of prospective studies.
PLoS One 2014, 9:e93044.
122. Major JM, Yu K, Weinstein SJ, Berndt SI, Hyland PL, Yeager M, Chanock S,
Albanes D: Genetic variants reflecting higher vitamin e status in men are
associated with reduced risk of prostate cancer. J Nutr May 2014,
144:729�733.
123. Klein EA, Thompson IM Jr, Tangen CM, Crowley JJ, Lucia MS, Goodman PJ,
Minasian LM, Ford LG, Parnes HL, Gaziano JM, Karp DD, Lieber MM, Walther
PJ, Klotz L, Parsons JK, Chin JL, Darke AK, Lippman SM, Goodman GE,
Meyskens FL Jr, Baker LH: Vitamin E and the risk of prostate cancer: the
Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA 2011,
306:1549�1556.
124. Albanes D, Till C, Klein EA, Goodman PJ, Mondul AM, Weinstein SJ, aylor PR,
Parnes HL, Gaziano JM, Song X, Fleshner NE, Brown PH, Meyskens FL Jr,
Thompson IM: Plasma tocopherols and risk of prostate cancer in the
Selenium and Vitamin E Cancer Prevention Trial (SELECT). Cancer Prev Res
(Phila) 2014, 7:886�895.
125. Kristal AR, Darke AK, Morris JS, Tangen CM, Goodman PJ, Thompson IM,
Meyskens FL Jr, Goodman GE, Minasian LM, Parnes HL, Lippman SM,
Klein EA: Baseline selenium status and effects of selenium and vitamin e
supplementation on prostate cancer risk. J Natl Cancer Inst 2014,
106:djt456.
126. Jamison JM, Gilloteaux J, Taper HS, Summers JL: Evaluation of the in vitro
and in vivo antitumor activities of vitamin C and K-3 combinations
against human prostate cancer. J Nutr 2001, 131:158S�160S.
127. Nimptsch K, Rohrmann S, Kaaks R, Linseisen J: Dietary vitamin K intake
in relation to cancer incidence and mortality: results from the
Heidelberg cohort of the European Prospective Investigation into
Cancer and Nutrition (EPIC-Heidelberg). Am J Clin Nutr 2010,
91:1348�1358.
128. Ma RW, Chapman K: A systematic review of the effect of diet in prostate
cancer prevention and treatment. J Hum Nutr Diet 2009, 22:187�199.
quiz 200�182.
129. Bristow SM, Bolland MJ, MacLennan GS, Avenell A, Grey A, Gamble GD, Reid
IR: Calcium supplements and cancer risk: a meta-analysis of randomised
controlled trials. Br J Nutr 2013, 110:1384�1393.
130. Williams CD, Whitley BM, Hoyo C, Grant DJ, Schwartz GG, Presti JC Jr, Iraggi
JD, Newman KA, Gerber L, Taylor LA, McKeever MG, Freedland SJ: Dietary
calcium and risk for prostate cancer: a case�control study among US
veterans. Prev Chronic Dis 2012, 9:E39.
131. Hori S, Butler E, McLoughlin J: Prostate cancer and diet: food for thought?
BJU Int 2011, 107:1348�1359.
132. Geybels MS, Verhage BA, van Schooten FJ, Goldbohm RA, van den Brandt
PA: Advanced prostate cancer risk in relation to toenail selenium levels.
J Natl Cancer Inst 2013, 105:1394�1401.
133. Singh RP, Agarwal R: Prostate cancer chemoprevention by silibinin: bench
to bedside. Mol Carcinog 2006, 45:436�442.
134. Ting H, Deep G, Agarwal R: Molecular mechanisms of silibinin-mediated
cancer chemoprevention with major emphasis on prostate cancer.
AAPS J 2013, 15:707�716.
135. Ting HJ, Deep G, Jain AK, Cimic A, Sirintrapun J, Romero LM, Cramer SD,
Agarwal C, Agarwal R: Silibinin prevents prostate cancer cell-mediated
differentiation of naive fibroblasts into cancer-associated fibroblast
phenotype by targeting TGF beta2. Mol Carcinog 2014. doi:10.1002/
mc.22135. [Epub ahead of time]
136. Goel A, Aggarwal BB: Curcumin, the golden spice from Indian saffron, is a
chemosensitizer and radiosensitizer for tumors and chemoprotector and
radioprotector for normal organs. Nutr Cancer 2010, 62:919�930.
137. Khan N, Adhami VM, Mukhtar H: Apoptosis by dietary agents for
prevention and treatment of prostate cancer. Endocr Relat Cancer 2010,
17:R39�R52.
138. Heber D: Pomegranate ellagitannins. In Herbal Medicine: Biomolecular and
Clinical Aspects. 2nd edition. Edited by Benzie IF, Wachtel-Galor S. Boca
Raton, FL: CRC Press; 2011.
139. Pantuck AJ, Leppert JT, Zomorodian N, Aronson W, Hong J, Barnard RJ,
Seeram N, Liker H, Wang H, Elashoff R, Heber D, Aviram M, Ignarro L,
Belldegrun A: Phase II study of pomegranate juice for men with rising
prostate-specific antigen following surgery or radiation for prostate
cancer. Clin Cancer Res 2006, 12:4018�4026.
140. Paller CJ, Ye X, Wozniak PJ, Gillespie BK, Sieber PR, Greengold RH, Stockton
BR, Hertzman BL, Efros MD, Roper RP, Liker HR, Carducci MA: A randomized
phase II study of pomegranate extract for men with rising PSA following
initial therapy for localized prostate cancer. Prostate Cancer Prostatic Dis
2013, 16:50�55.
141. Freedland SJ, Carducci M, Kroeger N, Partin A, Rao JY, Jin Y, Kerkoutian S,
Wu H, Li Y, Creel P, Mundy K, Gurganus R, Fedor H, King SA, Zhang Y,
Heber D, Pantuck AJ: A double-blind, randomized, neoadjuvant study of
the tissue effects of POMx pills in men with prostate cancer before
radical prostatectomy. Cancer Prev Res (Phila) 2013, 6:1120�1127.
142. Wang P, Aronson WJ, Huang M, Zhang Y, Lee RP, Heber D, Henning SM:
Green tea polyphenols and metabolites in prostatectomy tissue:
implications for cancer prevention. Cancer Prev Res (Phila) 2010,
3:985�993.
143. Kurahashi N, Sasazuki S, Iwasaki M, Inoue M, Tsugane S: Green tea
consumption and prostate cancer risk in Japanese men: a prospective
study. Am J Epidemiol 2008, 167:71�77.
144. McLarty J, Bigelow RL, Smith M, Elmajian D, Ankem M, Cardelli JA: Tea
polyphenols decrease serum levels of prostate-specific antigen,
hepatocyte growth factor, and vascular endothelial growth factor in
prostate cancer patients and inhibit production of hepatocyte growth
factor and vascular endothelial growth factor in vitro. Cancer Prev Res
(Phila) 2009, 2:673�682.
145. Bettuzzi S, Brausi M, Rizzi F, Castagnetti G, Peracchia G, Corti A:
Chemoprevention of human prostate cancer by oral administration of
green tea catechins in volunteers with high-grade prostate intraepithelial
neoplasia: a preliminary report from a one-year proof-of-principle study.
Cancer Res 2006, 66:1234�1240.
146. Fraser SP, Peters A, Fleming-Jones S, Mukhey D, Djamgoz MB: Resveratrol:
inhibitory effects on metastatic cell behaviors and voltage-gated Na(+)
channel activity in rat prostate cancer in vitro. Nutr Cancer 2014,
66:1047�1058.
147. Oskarsson A, Spatafora C, Tringali C, Andersson AO: Inhibition of CYP17A1
activity by resveratrol, piceatannol, and synthetic resveratrol analogs.
Prostate 2014, 74:839�851.
148. Ferruelo A, Romero I, Cabrera PM, Arance I, Andres G, Angulo JC: Effects of
resveratrol and other wine polyphenols on the proliferation, apoptosis
and androgen receptor expression in LNCaP cells. Actas Urol Esp Jul-Aug
2014, 38:397�404.
149. Osmond GW, Masko EM, Tyler DS, Freedland SJ, Pizzo S: In vitro and in vivo
evaluation of resveratrol and 3,5-dihydroxy-4?-acetoxy-trans-stilbene in
the treatment of human prostate carcinoma and melanoma. J Surg Res
2013, 179:e141�e148.
150. Baur JA, Sinclair DA: Therapeutic potential of resveratrol: the in vivo
evidence. Nat Rev Drug Discov 2006, 5:493�506.
151. Klink JC, Tewari AK, Masko EM, Antonelli J, Febbo PG, Cohen P, Dewhirst
MW, Pizzo SV, Freedland SJ: Resveratrol worsens survival in SCID mice with prostate cancer xenografts in a cell-line specific manner, through paradoxical effects on oncogenic pathways. Prostate 2013, 73:754�762.

152. Huang EC, Zhao Y, Chen G, Baek SJ, McEntee MF, Minkin S, Biggerstaff JP,
Whelan J: Zyflamend, a polyherbal mixture, down regulates class I and
class II histone deacetylases and increases p21 levels in castrate-resistant
prostate cancer cells. BMC Complement Altern Med 2014, 14:68.
153. Huang EC, McEntee MF, Whelan J: Zyflamend, a combination of herbal
extracts, attenuates tumor growth in murine xenograft models of
prostate cancer. Nutr Cancer 2012, 64:749�760.
154. Yan J, Xie B, Capodice JL, Katz AE: Zyflamend inhibits the expression and
function of androgen receptor and acts synergistically with bicalutimide
to inhibit prostate cancer cell growth. Prostate 2012, 72:244�252.
155. Kunnumakkara AB, Sung B, Ravindran J, Diagaradjane P, Deorukhkar A, Dey
S, Koca C, Tong Z, Gelovani JG, Guha S, Krishnan S, Aggarwal BB: Zyflamend
suppresses growth and sensitizes human pancreatic tumors to
gemcitabine in an orthotopic mouse model through modulation of
multiple targets. Int J Cancer 2012, 131:E292�E303.
156. Capodice JL, Gorroochurn P, Cammack AS, Eric G, McKiernan JM, Benson
MC, Stone BA, Katz AE: Zyflamend in men with high-grade prostatic
intraepithelial neoplasia: results of a phase I clinical trial. J Soc Integr
Oncol 2009, 7:43�51.
157. Rafailov S, Cammack S, Stone BA, Katz AE: The role of Zyflamend, an
herbal anti-inflammatory, as a potential chemopreventive agent against
prostate cancer: a case report. Integr Cancer Ther 2007, 6:74�76.
158. Askari F, Parizi MK, Jessri M, Rashidkhani B: Fruit and vegetable intake in
relation to prostate cancer in Iranian men: a case�control study.
Asian Pac J Cancer Prev 2014, 15:5223�5227.
159. Liu B, Mao Q, Cao M, Xie L: Cruciferous vegetables intake and risk of
prostate cancer: a meta-analysis. Int J Urol 2012, 19:134�141.
160. Richman EL, Carroll PR, Chan JM: Vegetable and fruit intake after
diagnosis and risk of prostate cancer progression. Int J Cancer 2012,
131:201�210.
161. Hsing AW, Chokkalingam AP, Gao YT, Madigan MP, Deng J, Gridley G,
Fraumeni JF Jr: Allium vegetables and risk of prostate cancer: a
population-based study. J Natl Cancer Inst 2002, 94:1648�1651.
162. Chan R, Lok K, Woo J: Prostate cancer and vegetable consumption.
Mol Nutr Food Res 2009, 53:201�216.
163. Thomas R, Williams M, Sharma H, Chaudry A, Bellamy P: A double-blind,
placebo-controlled randomised trial evaluating the effect of a
polyphenol-rich whole food supplement on PSA progression in men
with prostate cancer-the UK NCRN Pomi-T study. Prostate Cancer Prostatic
Dis 2014, 17:180�186.
164. Yang CM, Lu IH, Chen HY, Hu ML: Lycopene inhibits the proliferation of
androgen-dependent human prostate tumor cells through activation of
PPARgamma-LXRalpha-ABCA1 pathway. J Nutr Biochem 2012, 23:8�17.
165. Qiu X, Yuan Y, Vaishnav A, Tessel MA, Nonn L, van Breemen RB: Effects of
lycopene on protein expression in human primary prostatic epithelial
cells. Cancer Prev Res (Phila) 2013, 6:419�427.
166. Boileau TW, Liao Z, Kim S, Lemeshow S, Erdman JW Jr, Clinton SK: Prostate
carcinogenesis in N-methyl-N-nitrosourea (NMU)-testosterone-treated
rats fed tomato powder, lycopene, or energy-restricted diets. J Natl
Cancer Inst 2003, 95:1578�1586.
167. Konijeti R, Henning S, Moro A, Sheikh A, Elashoff D, Shapiro A, Ku M,
Said JW, Heber D, Cohen P, Aronson WJ: Chemoprevention of prostate
cancer with lycopene in the TRAMP model. Prostate 2010, 70:1547�1554.
168. Giovannucci E, Rimm EB, Liu Y, Stampfer MJ, Willett WC: A prospective
study of tomato products, lycopene, and prostate cancer risk. J Natl
Cancer Inst 2002, 94:391�398.
169. Zu K, Mucci L, Rosner BA, Clinton SK, Loda M, Stampfer MJ, Giovannucci E:
Dietary lycopene, angiogenesis, and prostate cancer: a prospective
study in the prostate-specific antigen era. J Natl Cancer Inst 2014,
106:djt430.
170. Gann PH, Ma J, Giovannucci E, Willett W, Sacks FM, Hennekens CH, Stampfer
MJ: Lower prostate cancer risk in men with elevated plasma lycopene
levels: results of a prospective analysis. Cancer Res 1999, 59:1225�1230.
171. Kristal AR, Till C, Platz EA, Song X, King IB, Neuhouser ML, Ambrosone CB,
Thompson IM: Serum lycopene concentration and prostate cancer risk:
results from the Prostate Cancer Prevention Trial. Cancer Epidemiol
Biomarkers Prev 2011, 20:638�646.
172. Kirsh VA, Mayne ST, Peters U, Chatterjee N, Leitzmann MF, Dixon LB, Urban
DA, Crawford ED, Hayes RB: A prospective study of lycopene and tomato
product intake and risk of prostate cancer. Cancer Epidemiol Biomarkers
Prev 2006, 15:92�98.
173. Mariani S, Lionetto L, Cavallari M, Tubaro A, Rasio D, De Nunzio C, Hong
GM, Borro M, Simmaco M: Low prostate concentration of lycopene is
associated with development of prostate cancer in patients with highgrade
prostatic intraepithelial neoplasia. Int J Mol Sci 2014, 15:1433�1440.
174. Kucuk O, Sarkar FH, Djuric Z, Sakr W, Pollak MN, Khachik F, Banerjee M,
Bertram JS, Wood DP Jr: Effects of lycopene supplementation in patients
with localized prostate cancer. Exp Biol Med (Maywood) 2002, 227:881�885.
175. Chen L, Stacewicz-Sapuntzakis M, Duncan C, Sharifi R, Ghosh L, van
Breemen R, Ashton D, Bowen PE: Oxidative DNA damage in prostate
cancer patients consuming tomato sauce-based entrees as a whole-food
intervention. J Natl Cancer Inst 2001, 93:1872�1879.
176. van Breemen RB, Sharifi R, Viana M, Pajkovic N, Zhu D, Yuan L, Yang Y,
Bowen PE, Stacewicz-Sapuntzakis M: Antioxidant effects of lycopene in
African American men with prostate cancer or benign prostate hyperplasia:
a randomized, controlled trial. Cancer Prev Res (Phila) 2011, 4:711�718.
177. Shafique K, McLoone P, Qureshi K, Leung H, Hart C, Morrison DS: Coffee
consumption and prostate cancer risk: further evidence for inverse
relationship. Nutr J 2012, 11:42.
178. Wilson KM, Kasperzyk JL, Rider JR, Kenfield S, van Dam RM, Stampfer MJ,
Giovannucci E, Mucci LA: Coffee consumption and prostate cancer risk
and progression in the Health Professionals Follow-up Study. J Natl
Cancer Inst 2011, 103:876�884.
179. Bosire C, Stampfer MJ, Subar AF, Wilson KM, Park Y, Sinha R: Coffee
consumption and the risk of overall and fatal prostate cancer in the
NIH-AARP Diet and Health Study. Cancer Causes Control 2013, 24:1527�1534.
180. Arab L, Su LJ, Steck SE, Ang A, Fontham ET, Bensen JT, Mohler JL: Coffee
consumption and prostate cancer aggressiveness among African and
Caucasian Americans in a population-based study. Nutr Cancer 2012,
64:637�642.
181. Phillips RL, Snowdon DA: Association of meat and coffee use with cancers
of the large bowel, breast, and prostate among Seventh-Day Adventists:
preliminary results. Cancer Res 1983, 43:2403 s�2408s.
182. Hsing AW, McLaughlin JK, Schuman LM, Bjelke E, Gridley G, Wacholder S,
Chien HT, Blot WJ: Diet, tobacco use, and fatal prostate cancer: results
from the Lutheran Brotherhood Cohort Study. Cancer Res 1990,
50:6836�6840.
183. Cao S, Liu L, Yin X, Wang Y, Liu J, Lu Z: Coffee consumption and risk of
prostate cancer: a meta-analysis of prospective cohort studies.
Carcinogenesis 2014, 35:256�261.
184. Nordmann AJ, Suter-Zimmermann K, Bucher HC, Shai I, Tuttle KR,
Estruch R, Briel M: Meta-analysis comparing Mediterranean to low-fat
diets for modification of cardiovascular risk factors. Am J Med 2011,
124:841�851. e842.
185. Kapiszewska M: A vegetable to meat consumption ratio as a relevant
factor determining cancer preventive diet. The Mediterranean versus
other European countries. Forum Nutr 2006, 59:130�153.
186. Kenfield SA, Dupre N, Richman EL, Stampfer MJ, Chan JM, Giovannucci EL:
Mediterranean diet and prostate cancer risk and mortality in the Health
Professionals Follow-up Study. Eur Urol 2014, 65:887�894.
187. Ambrosini GL, Fritschi L, de Klerk NH, Mackerras D, Leavy J: Dietary patterns
identified using factor analysis and prostate cancer risk: a case control
study in Western Australia. Ann Epidemiol 2008, 18:364�370.
188. Baade PD, Youlden DR, Krnjacki LJ: International epidemiology of prostate
cancer: geographical distribution and secular trends. Mol Nutr Food Res
2009, 53:171�184.
189. Muller DC, Severi G, Baglietto L, Krishnan K, English DR, Hopper JL, Giles GG:
Dietary patterns and prostate cancer risk. Cancer Epidemiol Biomarkers Prev
2009, 18:3126�3129.
190. Tseng M, Breslow RA, DeVellis RF, Ziegler RG: Dietary patterns and prostate
cancer risk in the National Health and Nutrition Examination Survey
Epidemiological Follow-up Study cohort. Cancer Epidemiol Biomarkers Prev
2004, 13:71�77.
191. Wu K, Hu FB, Willett WC, Giovannucci E: Dietary patterns and risk of
prostate cancer in U.S. men. Cancer Epidemiol Biomarkers Prev 2006,
15:167�171.
192. Daubenmier JJ, Weidner G, Marlin R, Crutchfield L, Dunn-Emke S, Chi C,
Gao B, Carroll P, Ornish D: Lifestyle and health-related quality of life of
men with prostate cancer managed with active surveillance. Urology
2006, 67:125�130.

193. Parsons JK, Newman VA, Mohler JL, Pierce JP, Flatt S, Marshall J: Dietary
modification in patients with prostate cancer on active surveillance: a
randomized, multicentre feasibility study. BJU Int 2008, 101:1227�1231.
194. Mosher CE, Sloane R, Morey MC, Snyder DC, Cohen HJ, Miller PE,
Demark-Wahnefried W: Associations between lifestyle factors and quality
of life among older long-term breast, prostate, and colorectal cancer
survivors. Cancer 2009, 115:4001�4009.
195. Bhindi B, Locke J, Alibhai SM, Kulkarni GS, Margel DS, Hamilton RJ, Finelli A,
Trachtenberg J, Zlotta AR, Toi A, Hersey KM, Evans A, van der Kwast TH,
Fleshner NE: Dissecting the association between metabolic syndrome
and prostate cancer risk: analysis of a large clinical cohort. Eur Urol 2014.
doi:10.1016/j.eururo.2014.01.040. [Epub ahead of time]
196. Esposito K, Chiodini P, Capuano A, Bellastella G, Maiorino MI, Parretta E,
Lenzi A, Giugliano D: Effect of metabolic syndrome and its components
on prostate cancer risk: meta-analysis. J Endocrinol Invest 2013,
36:132�139.
197. U.S. Department of Agriculture and U.S. Department of Health and
Human Services. Dietary Guidelines for Americans, 2010. 7th edition.
Washington, DC: U.S. Government Printing Office, December, 2010.


Close Accordion

Mastodon